
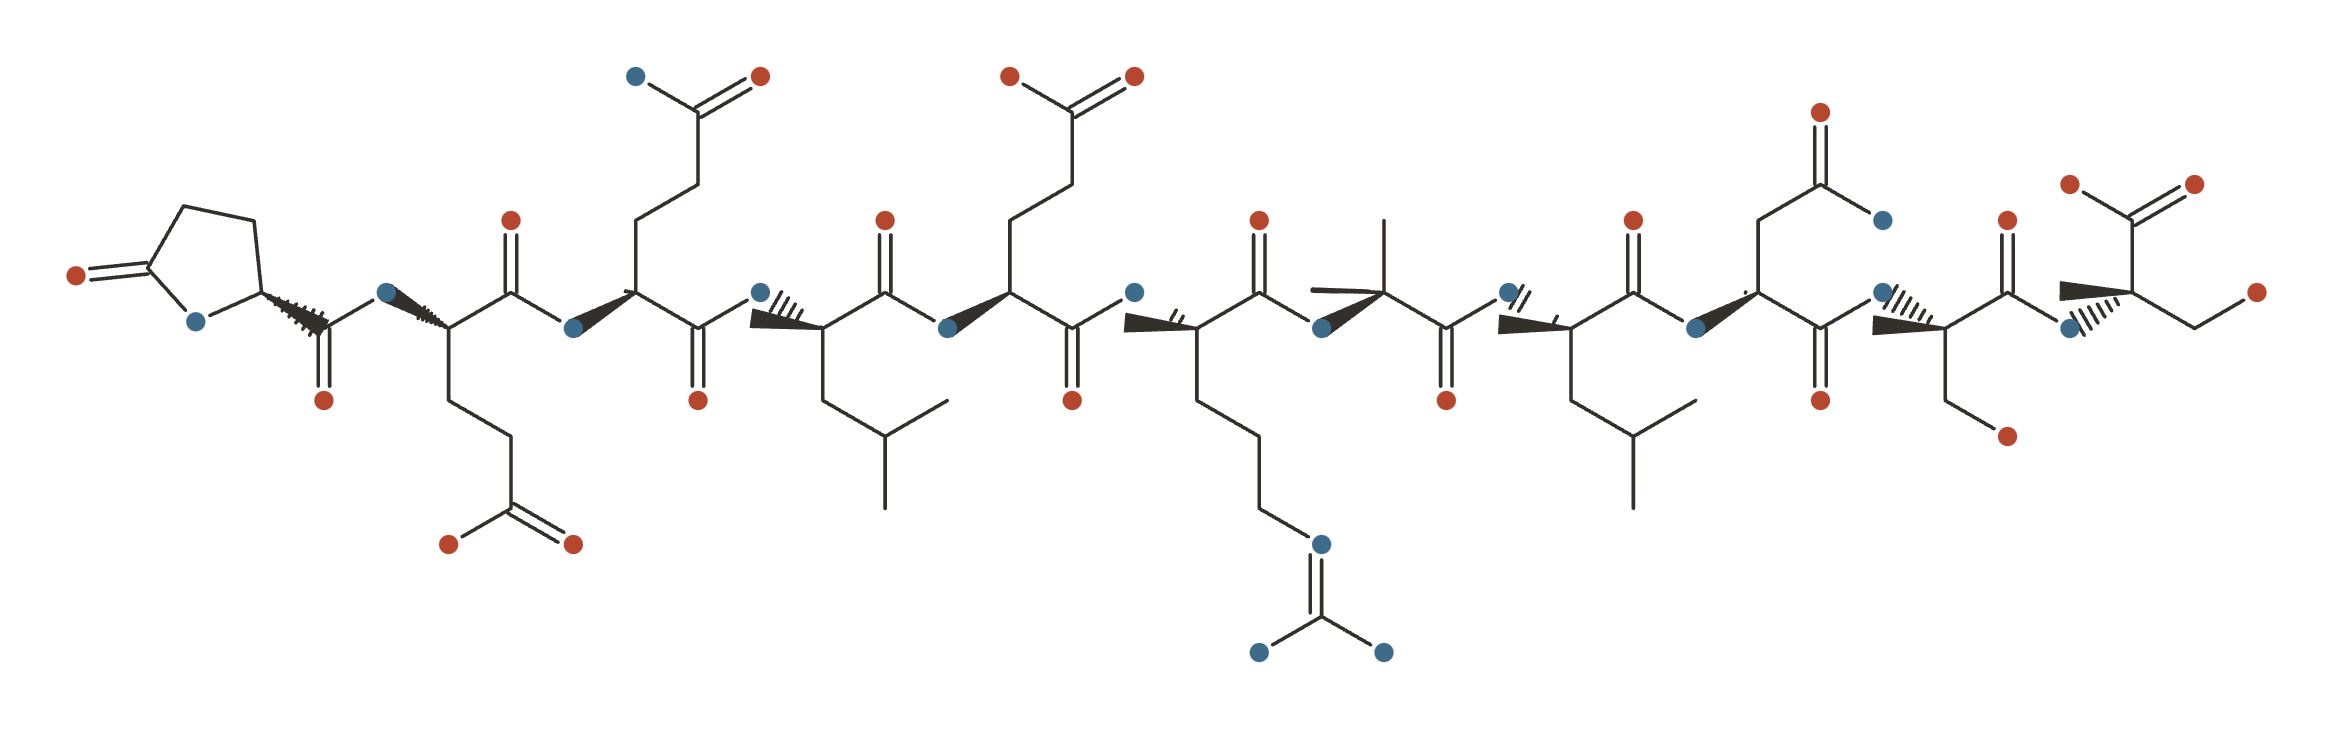
ARA-290 (Cibinetide)
An 11-amino-acid erythropoietin-derived peptide that activates the innate repair receptor without raising red-cell count; tested in small trials, never approved.

ARA-290 (Cibinetide) at a Glance
ARA-290 (cibinetide) is an 11-amino-acid peptide derived from erythropoietin, engineered to keep one half of EPO’s activity and discard the other. EPO signals through two distinct receptors: one drives red-blood-cell production, the other — the innate repair receptor — mediates tissue protection. ARA-290 activates only the second, so it aims at repair and neuropathic pain without raising haematocrit or thrombosis risk. It is investigational, studied mainly in small-fibre neuropathy and sarcoidosis.
History & Development
ARA 290 is an attempt to keep erythropoietin’s tissue-protective effects while discarding the one everybody knows it for. EPO builds red blood cells - and that is precisely the property this peptide was engineered to lose.
| First described | Human trials in sarcoidosis-associated small-fibre neuropathy from 2012 1Reference 1RCTSafety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT)View study → |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Supplied and developed by Araim Pharmaceuticals 1Reference 1RCTSafety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT)View study → |
| Origin | An 11-amino-acid peptide modelled on the three-dimensional structure of erythropoietin |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Araim Pharmaceuticals |
| Development status | Investigational - small trials only; never approved |
Discovery
Erythropoietin does two separate jobs. It drives red-cell production through the classical EPO receptor homodimer, and it protects injured tissue through a different receptor entirely - the innate repair receptor, a heterocomplex of the EPO receptor and the beta-common receptor. The second effect is useful in nerve injury and inflammation; the first is what makes EPO dangerous to give for that purpose, since raising haematocrit brings thrombotic risk.
ARA 290, also called cibinetide, is an 11-amino-acid peptide modelled from EPO’s three-dimensional structure to engage only the innate repair receptor 1Reference 1RCTSafety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT)View study →. It is non-erythropoietic by design: it does not raise red-cell count, which is the whole reason it exists.
Development & ownership
ARA 290 has been developed by Araim Pharmaceuticals, which supplied the compound for the published human trials 1Reference 1RCTSafety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT)View study →.
Its clinical record is small and concentrated in one place: small-fibre neuropathy, particularly in sarcoidosis. A randomized, double-blind placebo-controlled pilot gave 2 mg intravenously three times weekly for four weeks and found it safe with reduced neuropathic symptoms 1Reference 1RCTSafety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT)View study →; a follow-up reported improved symptoms alongside increased corneal nerve fibre density 2Reference 2RCTARA 290 improves symptoms in patients with sarcoidosis-associated small nerve fiber loss and increases corneal nerve fiber density — human (RCT)View study → - an objective structural endpoint rather than a questionnaire, which is what makes this programme more interesting than its size suggests. A further trial extended it to neuropathic symptoms and metabolic control in type 2 diabetes 35Reference 35Clinical trialARA 290, a nonerythropoietic peptide engineered from erythropoietin, improves metabolic control and neuropathic symptoms in patients with type 2 diabetesView study →.
The programme has not progressed beyond these small studies. The largest human trial on record enrolled 64 participants, and the longest human exposure anywhere is 28 days.
How it reached the market
It has not been approved anywhere. ARA 290 circulates as an unapproved research peptide, marketed for nerve pain and inflammation on the strength of trials that were genuine but very small - and with no human data at all beyond four weeks of use.
What It's Used For
ARA-290 — international nonproprietary name cibinetide — is an 11-amino-acid peptide (pGlu-Glu-Gln-Leu-Glu-Arg-Ala-Leu-Asn-Ser-Ser) copied from the aqueous face of helix B of erythropoietin (EPO), the part of the hormone that does not touch the classical EPO receptor. The design premise is unusually clean and worth stating up front, because it is the most interesting fact about the molecule: EPO’s tissue-protective and anti-inflammatory effects are carried by a different receptor from its blood-making effects. The innate repair receptor (IRR) — a heterocomplex of the EPO receptor and the β-common receptor (CD131) — mediates repair; the EPO-receptor homodimer mediates erythropoiesis and, with it, the rise in hematocrit and the thrombotic risk that has repeatedly sunk EPO as a tissue-protective drug 30,
ARA-290 was engineered to hit the first and miss the second.
A citation warning that governs this whole page: EPO’s enormous literature is not ARA-290 evidence. Erythropoietin has been given to hundreds of thousands of patients; cibinetide has been given to roughly 130 people in published trials. Vendor and community write-ups routinely borrow EPO’s neuroprotection and cardioprotection data to sell the peptide. Every study cited below administered ARA-290 (or its identically-structured precursor names, pHBSP / helix B surface peptide) — not EPO, not darbepoetin, not carbamylated EPO.
The evidence posture is early-stage human plus a broad, shallow preclinical literature. Unusually for a peptide sold on this market, ARA-290 has genuine randomized human data — but it is confined to one indication cluster (small-fiber neuropathy), four registered trials totalling 133 participants, and a maximum exposure of 28 days. Everything else — cardioprotection, kidney protection, autoimmunity, wound healing, bone, metabolic syndrome — is rodent, pig, or cell culture. Two papers in this literature have been retracted 28,
Route is load-bearing: cibinetide is injection-only (intravenous in the first trial, subcutaneous thereafter) with a plasma half-life of about two minutes; there is no oral pharmacology and an oral product cannot work. It has never been approved by any regulator, its sponsor’s development program has been silent since 2017, and it is sold gray-market as an unapproved research chemical.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Two rows in this table mean “tested and failed,” not “untested.” Depression and diabetic macular edema sit near the bottom because human studies were run and did not support the use — a different and worse situation than the animal-only rows above them, which are merely unproven in people.
This is ARA-290’s best-evidenced use and the only one with replicated human data. Sarcoidosis frequently damages small sensory and autonomic nerve fibers, producing pain and dysautonomia that immunosuppression treats poorly — a genuine unmet need, and a rare disease, which is why the compound holds orphan status.
Trial one (n=22, intravenous). A double-blind, placebo-controlled exploratory trial gave 22 sarcoidosis patients with documented small-fiber neuropathy ARA-290 2 mg intravenously three times weekly, or placebo, for four weeks. The Small Fiber Neuropathy Screening List score improved significantly versus placebo (Δ −11.5 vs −2.9), as did the pain and physical-functioning dimensions of the SF-36. No safety concerns arose on clinical or laboratory assessment 1Reference 1RCTSafety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT)View study →. The result that usually gets dropped: the Brief Pain Inventory and the Fatigue Assessment Scale “improved significantly but equivalently in both patient groups” — that is, they did not separate from placebo — and the depressive-symptom inventory did not move at all. Every endpoint in this trial was a patient-reported questionnaire.
Trial two (subcutaneous, 28 days). A second blinded placebo-controlled trial switched to daily subcutaneous dosing and added an objective measure. Neuropathic symptoms improved, and so did corneal nerve-fiber density, cutaneous temperature sensitivity, and exercise capacity on the six-minute walk test 2Reference 2RCTARA 290 improves symptoms in patients with sarcoidosis-associated small nerve fiber loss and increases corneal nerve fiber density — human (RCT)View study →. This is the study that first suggested a disease-modifying rather than purely analgesic effect.
Trial three — the Phase 2b (n=64, NCT02039687). Sponsored by Araim Pharmaceuticals, this 28-day randomized trial compared cibinetide 1, 4 and 8 mg/day subcutaneously against placebo, with change in corneal nerve-fiber area (CNFA) as the pre-specified primary endpoint. It was met — but only in part. Placebo-corrected mean change in CNFA was 109 µm² (95% CI −429 to 647) at 1 mg, 697 µm² (159 to 1236; p = 0.012) at 4 mg, and 431 µm² (−130 to 992) at 8 mg. Only the middle dose reached significance, which is not the dose-response you would like to see. Regenerating GAP-43-positive intra-epidermal nerve fibers also increased at 4 mg (p = 0.035), and CNFA change correlated with both GAP-43 change and six-minute-walk change. Pain improved significantly in all groups, including placebo, and the placebo-corrected pain reduction in the moderate-to-severe subgroup at 4 mg reached only p = 0.157 3Reference 3RCTCibinetide improves corneal nerve fiber abundance in patients with sarcoidosis-associated small nerve fiber loss and neuropathic pain — human (RCT, Phase 2b)View study →. Results are posted on ClinicalTrials.gov; serious adverse events occurred in 2 of 16 (1 mg), 0 of 16 (4 mg), 1 of 14 (8 mg) and 0 of 16 (placebo) participants — small numbers, no dose relationship, in a population with active systemic disease.
On the corneal endpoint — read this before reading the result. Corneal confocal microscopy is a genuinely clever, non-invasive way to count and measure the small nerve fibers in the cornea, and it detects regeneration more sensitively than a skin biopsy 4Reference 4Clinical trialCorneal nerve fiber size adds utility to the diagnosis and assessment of therapeutic response in patients with small fiber neuropathy — human (diagnostic / biomarker study, not a trial)View study →. That is why it was chosen. But it is a surrogate: it measures nerve morphology, not symptoms, function, or quality of life. A drug can grow nerve fibers that are visible under a microscope without a patient noticing anything. In this program, the morphology endpoints moved and the pain endpoints largely did not — so the surrogate is carrying the case, and whether it predicts clinical benefit is the unanswered question. An expert review of the first two trials framed the prospects as promising 5Reference 5ReviewARA 290 for treatment of small fiber neuropathy in sarcoidosis — reviewView study →; that review predates the Phase 2b pain result.
Gap: No Phase 3 has ever been registered. All human trials are ≤28 days, the largest is 64 patients, the pivotal endpoint is a surrogate, the clinically meaningful pain endpoint was not significant, and durability beyond a month is untested.
A Phase 2 study had subjects with type 2 diabetes and painful neuropathy self-administer subcutaneous ARA-290 4 mg daily or placebo for 28 days, then followed them a further month. The cibinetide group showed improvement in HbA1c and lipid profiles across the 56-day window; neuropathic symptoms on the PainDetect questionnaire improved significantly; and among subjects whose baseline corneal nerve-fiber density was more than one standard deviation below normal, CNFD rose significantly versus no change on placebo. No safety issues were identified 6Reference 6RCTARA 290, a nonerythropoietic peptide engineered from erythropoietin, improves metabolic control and neuropathic symptoms in patients with type 2 diabetes — human (RCT, Phase 2)View study →.
Three cautions the usual summaries omit. The published abstract reports the metabolic improvements descriptively — it does not state a significance level for HbA1c or lipids, and the authors’ own conclusion is that the peptide “may benefit” both and “deserves continued clinical evaluation.” The nerve-density result is a subgroup finding, not the whole cohort. And I could not match this publication to a ClinicalTrials.gov record: the only registered ARA-290 diabetes trial (NCT01933529, Karolinska, 24 subjects estimated) has different primary endpoints — oral glucose tolerance and insulin secretion — its status is listed as UNKNOWN, and no results have ever been posted. The published study appears to be unregistered.
Gap: One small, short, apparently unregistered human Phase 2 with self-reported and surrogate endpoints, not powered for glycemic or hard neuropathy outcomes, never replicated.
Analgesia in rats is the most replicated preclinical finding for this peptide. In a neuritis model, ARA-290 (30 or 120 µg/kg intraperitoneally, daily) prevented the development of mechanical allodynia 10Reference 10AnimalThe erythropoietin-derived peptide ARA290 reverses mechanical allodynia in the neuritis model — animal (rat)View study →.
In a spared-nerve-injury model it produced dose-dependent relief of mechanical and cold allodynia lasting up to 20 weeks, coupled with suppression of the spinal microglial response 9Reference 9AnimalARA 290, a peptide derived from the tertiary structure of erythropoietin, produces long-term relief of neuropathic pain coupled with suppression of the spinal microglia response — animal (rat)View study →.
Mechanistically, part of the effect may be direct rather than immune-mediated: ARA-290 inhibits the TRPV1 ion channel and relieves capsaicin-induced hypersensitivity in cell and behavioral assays 11Reference 11In vitroARA 290 relieves pathophysiological pain by targeting TRPV1 channel: integration between immune system and nociception — in vitro / animal (rodent)View study →.
The human counterpoint belongs here rather than in a footnote. ARA-290 has never had a dedicated human neuropathic-pain trial. In the two sarcoidosis trials that did carry pain instruments, the Brief Pain Inventory failed to separate from placebo 1Reference 1RCTSafety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT)View study → and the placebo-corrected pain reduction in the Phase 2b did not reach significance 3Reference 3RCTCibinetide improves corneal nerve fiber abundance in patients with sarcoidosis-associated small nerve fiber loss and neuropathic pain — human (RCT, Phase 2b)View study →.
Rodent allodynia is not human pain relief, and here the human pain data that exist are the weaker part of the file.
Gap: No dedicated human trial for neuropathic or inflammatory pain outside the sarcoidosis and diabetes small-fiber setting; the mechanistic pain data are entirely rodent or cell-based.
The tissue-protective peptide scaffold was first characterized in the heart, and the animal work here is the strongest preclinical block on the page. In cultured neonatal rat cardiomyocytes and a dilated-cardiomyopathy hamster, helix B surface peptide inhibited TNF-α-induced apoptosis by roughly 70–80% through Akt/ERK/STAT3, matching EPO without erythropoiesis 12Reference 12In vitroCardioprotection by a nonerythropoietic, tissue-protective peptide mimicking the 3D structure of erythropoietin — animal (rat, hamster) / in vitroView study →.
A single bolus of pyroglutamate helix B peptide in a rat myocardial-infarction model was cardioprotective against ischemic damage, comparably to EPO 13Reference 13In vitroA small nonerythropoietic helix B surface peptide based upon erythropoietin structure is cardioprotective against ischemic myocardial damage — animal (rat) / in vitroView study →.
In vitro, ARA-290 also reduced doxorubicin-induced genotoxicity and oxidative stress 15Reference 15In vitroAn engineered non-erythropoietic erythropoietin-derived peptide, ARA290, attenuates doxorubicin-induced genotoxicity and oxidative stress — in vitroView study →.
The healthspan study deserves separate mention because it is unusually well-built for an animal study: a 15-month randomized controlled trial in aging Fischer 344 × Brown Norway rats (n=48 longitudinal, n=144 cross-sectional) found chronic ARA-290 reduced cardiac inflammatory infiltrate and cytokines, enhanced cardiomyocyte autophagy, blunted the age-associated blood-pressure rise, preserved left-ventricular ejection fraction, and lowered a frailty index at 33 months of age 14Reference 14RCTA small erythropoietin derived non-hematopoietic peptide reduces cardiac inflammation, attenuates age associated declines in heart function and prolongs healthspan — animal (rat, 15-month randomised controlled study)View study →. This is the entire basis of ARA-290’s “anti-aging” and “longevity” marketing — and it is a rat study.
A naming note: refs 12Reference 12In vitroCardioprotection by a nonerythropoietic, tissue-protective peptide mimicking the 3D structure of erythropoietin — animal (rat, hamster) / in vitroView study → and 13Reference 13In vitroA small nonerythropoietic helix B surface peptide based upon erythropoietin structure is cardioprotective against ischemic myocardial damage — animal (rat) / in vitroView study → used HBSP and pHBSP respectively. The pyroglutamate-capped form (pHBSP) is ARA-290; the uncapped HBSP is its immediate precursor. They are the same design, not the same molecule, so 12Reference 12In vitroCardioprotection by a nonerythropoietic, tissue-protective peptide mimicking the 3D structure of erythropoietin — animal (rat, hamster) / in vitroView study → is scaffold evidence rather than direct ARA-290 evidence.
Gap: Entirely animal and in vitro. There is no human cardiac, cardiovascular, or longevity trial of ARA-290 of any kind, so every “anti-aging” claim made for it is rodent-only.
Several models show renoprotection. In a pig unilateral renal-ischemia model, intravenous ARA-290 improved glomerular filtration rate over seven days and reduced interstitial fibrosis 16Reference 16ARA290, a non-erythropoietic EPO derivative, attenuates renal ischemia/reperfusion injury — animal (pig)View study →.
In rats, ARA-290 given early after reperfusion improved renal function and reduced inflammation, with earlier administration more effective 17Reference 17AnimalRenoprotective capacities of non-erythropoietic EPO derivative, ARA290, following renal ischemia/reperfusion injury — animal (rat)View study →.
In a rat renal-allograft model it lowered serum creatinine and urea and reduced macrophage infiltration, apparently by inhibiting NF-κB 18Reference 18AnimalEPO derivative ARA290 attenuates early renal allograft injury in rats by targeting NF-κB pathway — animal (rat)View study →.
This cluster carries a specific caution. In 2026, Molecular Medicine published a retraction note for a paper on delayed administration of pHBSP in acute kidney injury 29Reference 29Retraction note: delayed administration of pyroglutamate helix B surface peptide (pHBSP), a novel nonerythropoietic analog of erythropoietin, attenuates acute kidney injury — retraction noticeView study → — the same molecule, the same research area. The three studies cited above are not retracted, but a retraction inside a small literature is a reason to weight the whole cluster down rather than up.
Gap: Animal-only, with a retraction in the adjacent literature. No human renal or transplant trial of ARA-290 exists.
The peptide’s anti-inflammatory action has been tested across rodent autoimmune models, consistently and by different groups. In rat experimental autoimmune neuritis it improved recovery, reduced nerve inflammation, and shifted T-cell phenotype toward regulatory-T and Th2 and away from Th1 19Reference 19AnimalErythropoietin-derived nonerythropoietic peptide ameliorates experimental autoimmune neuritis by inflammation suppression and tissue protection — animal (rat)View study →.
In rat experimental autoimmune encephalomyelitis — the standard multiple-sclerosis model — it reduced severity with lower IL-17, TNF-α and IFN-γ 20Reference 20AnimalTherapeutic effects of nonerythropoietic erythropoietin analog ARA290 in experimental autoimmune encephalomyelitis rat — animal (rat)View study →.
In mouse experimental colitis, cibinetide dampened innate immune cell function via CD131/JAK2-dependent NF-κB inhibition 21Reference 21In vitroCibinetide dampens innate immune cell functions thus ameliorating the course of experimental colitis — animal (mouse) / in vitroView study →.
In mouse lupus models it reduced autoantibodies and nephritis — explicitly without stimulating hematopoiesis 22Reference 22AnimalNon-erythropoietic erythropoietin-derived peptide protects mice from systemic lupus erythematosus — animal (mouse)View study →.
Gap: Every model is rodent. There is no human trial of ARA-290 in any autoimmune or inflammatory disease, and none is registered.
Cibinetide protected isolated human islets under cytokine stress — preserving ATP content and reducing caspase-3/7 activity — and reduced the instant blood-mediated inflammatory reaction that destroys islets during intraportal transplantation in a human blood-loop model; in athymic mice it improved human-islet engraftment 23Reference 23In vitroCibinetide protects isolated human islets in a stressful environment and improves engraftment in the perspective of intraportal islet transplantation — in vitro (human islets) / animal (mouse)View study →. In an allogeneic mouse islet-transplant model it reduced early inflammation and, combined with tacrolimus, improved graft function 24Reference 24AnimalImprovement of islet allograft function using cibinetide, an innate repair receptor ligand — animal (mouse)View study →.
This is the one application where “human” appears in the data, and it is worth being precise about what kind: human tissue in a dish, not human patients. The in-vivo efficacy is mouse.
Gap: No human transplant trial. The human component is in vitro only.
In genetically diabetic (db/db) mice, cibinetide at 30 µg/kg/day subcutaneously improved impaired wound healing — raising VEGF, phospho-Akt, phospho-eNOS and nitrite/nitrate, and improving re-epithelialization, angiogenesis, scar strength and time to closure — through activation of the EPO-receptor/β-common-receptor complex 25Reference 25AnimalActivation of the EPOR-β common receptor complex by cibinetide ameliorates impaired wound healing in mice with genetic diabetes — animal (mouse)View study →.
This single mouse study is the entire evidential basis for ARA-290 being sold as a “healing peptide.”
Gap: One mouse model, one lab, no replication, and no human wound-healing data of any kind.
Cibinetide, which binds only the heteromeric tissue-protective receptor, inhibited osteoclastogenesis in vitro and increased cortical (~5.8%) and trabecular (~5.2%) bone mineral density in wild-type mice over one month; it also blunted EPO-driven expansion of osteoclast progenitors 26Reference 26In vitroThe non-erythropoietic EPO analogue cibinetide inhibits osteoclastogenesis in vitro and increases bone mineral density in mice — in vitro / animal (mouse)View study →. The mechanistic point is interesting — EPO itself reduces bone density by expanding osteoclasts, so splitting the receptors may split that liability too.
Gap: In vitro plus a single short mouse study. No human bone data.
A helix B surface peptide suppressed adipogenesis and macrophage inflammation via an EPO-receptor/PPARγ axis and, in high-fat-diet mice, improved obesity, insulin resistance and adipose inflammation without stimulating hematopoiesis 27Reference 27In vitroNonerythropoietic erythropoietin-derived peptide suppresses adipogenesis, inflammation, obesity and insulin resistance — animal (mouse) / in vitroView study →.
The reason this row is scored so low is a retraction. The most-cited paper in this area — a 2014 British Journal of Pharmacology study reporting that pHBSP decreased susceptibility to diet-induced insulin resistance in mice, improved insulin signaling in skeletal muscle and enhanced mitochondrial biogenesis — has been retracted 28Reference 28AnimalA non-erythropoietic peptide derivative of erythropoietin decreases susceptibility to diet-induced insulin resistance in mice — animal (mouse); retracted publication, cited here only as a retractionView study →. It is cited here only as a retraction, never as evidence. Removing it leaves a single non-retracted mouse paper standing. Note that this is distinct from the type 2 diabetes human trial in application 2, which was a neuropathy-and-metabolic-markers study, not a metabolic-syndrome trial.
Gap: One mouse study after the key paper was withdrawn. No human metabolic-syndrome or obesity trial.
This application was tested in humans and the result was negative. In a double-blind, randomized, parallel-group trial, 36 healthy participants received a single 2 mg dose of ARA-290 or placebo, with neural and cognitive effects assessed one week later (NCT02070783, Leiden University Medical Center, completed; no results posted to the registry). Primary outcomes were neural processing of fearful versus happy faces and behavioral recognition of emotional facial expressions.
The findings did not go the way an antidepressant should. ARA-290-treated individuals showed lower neural responses to happy faces in the fusiform gyrus, and tended toward reduced recognition of happy and disgust expressions. It did produce faster categorization of positive versus negative words and increased attention toward positive images, but no effect on mood or affective symptoms. The authors’ own conclusion: the direction and strength of the effects “do not unequivocally support an antidepressant-like profile” 7Reference 7RCTTesting the antidepressant properties of the peptide ARA290 in a human neuropsychological model of drug action — human (RCT, negative)View study →.
Development for depressive disorders was subsequently discontinued.
Two limits cut both ways: these were healthy volunteers, not depressed patients, and it was a single dose assessed a week later — so this is a failed proof-of-mechanism rather than a failed treatment trial. But it is the only human depression-relevant data that exist, and it is negative.
Gap: No trial in a clinical depressed population has been run or registered, and the program was abandoned.
Also tested in humans, also negative. A Phase 2 trial at the Belfast Health and Social Care Trust recruited treatment-naïve patients with diabetic macular edema and had them self-administer cibinetide 4 mg/day subcutaneously for 12 weeks. Nine patients were recruited; eight completed. This was an uncontrolled, single-arm study analyzed descriptively — no placebo group.
There was no improvement in best-corrected visual acuity (−2.9 ± 5.0 letters), central retinal thickness (+10 ± 94.6 µm), central retinal sensitivity (−0.53 ± 1.9 dB) or tear production (−0.13 ± 7.7 mm). The one measure that improved was the patient-reported NEI VFQ-25 visual-function questionnaire (+2.7 ± 3.1). Some individual participants showed improvements in retinal thickness, tear production, glycemic control and albuminuria. No serious adverse events and — a genuinely useful safety datum — no anti-cibinetide antibodies were detected 8Reference 8Clinical trialA Phase 2 clinical trial on the use of cibinetide for the treatment of diabetic macular edema — human (single-arm Phase 2, null on objective endpoints)View study →.
A double-counting correction. This trial appears in two places and is often presented as two studies. It was published in 2020 under EudraCT 2015-001940-12 / ISRCTN16962255, and separately registered on ClinicalTrials.gov as NCT06626971, which is listed as TERMINATED with the reason “Expiry of study drug — no replacement available.” That registry entry is not a newer, second trial: its actual start date is April 2016 and its completion date August 2017, matching the published study exactly. It was submitted to ClinicalTrials.gov in 2018 and only posted in October 2024. One trial, two registrations, nine patients.
Gap: A single-arm study of nine people with objectively null primary results, which ran out of drug. No controlled DME trial exists and none is planned.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Innate repair receptor (EPO receptor–β-common receptor/CD131 heterocomplex) | Selective agonist — initiates tissue protection and anti-inflammation 30, | All applications |
| Classical EPO-receptor homodimer | No binding → no erythropoiesis and none of EPO’s hematocrit/thrombotic liability 30Reference 30ReviewFlipping the molecular switch for innate protection and repair of tissues: long-lasting effects of a non-erythropoietic small peptide engineered from erythropoietin — reviewView study → | The entire safety premise |
| PI3K/Akt, ERK1/2, STAT3, eNOS | Pro-survival, anti-apoptotic signaling 12, | Cardiacrenalwoundnerve repair |
| NF-κB (p65) | Inhibited → ↓ TNF-α, IL-6, MCP-1 18, | Inflammationtransplantautoimmune models |
| T-cell balance | ↑ regulatory-T / Th2, ↓ Th1 / Th17 19, | Rodent autoimmune models |
| Macrophage / innate immune activation | ↓ inflammatory activation, ↑ phagocytosis 21, | Colitislupustransplant models |
| TRPV1 channel | Direct inhibition → analgesia 11Reference 11In vitroARA 290 relieves pathophysiological pain by targeting TRPV1 channel: integration between immune system and nociception — in vitro / animal (rodent)View study → | Neuropathic and inflammatory pain (rodent) |
| Small-fiber nerve regeneration | ↑ corneal nerve-fiber area and GAP-43⁺ intra-epidermal fibers 2, | The one human-demonstrated effect |
Pharmacokinetics
Route first, because it disqualifies most products sold under this name. Cibinetide is given by injection — intravenously in the first trial (2 mg three times weekly), subcutaneously in every trial since (1–8 mg/day, with 4 mg/day the most-studied dose). An 11-amino-acid peptide has negligible oral bioavailability; no oral formulation has been developed, no oral pharmacology has ever been established, and an oral or sublingual “ARA-290” product cannot deliver intact peptide.
The plasma half-life is on the order of two minutes, reflecting rapid degradation by plasma exopeptidases; in-vitro metabolism work characterizing the peptide for anti-doping purposes identified a principal shortened metabolite and confirmed rapid clearance of the parent 33Reference 33In vitroCharacterization of in vitro generated metabolites of selected peptides <2 kDa prohibited in sports — in vitroView study →. Exact human Cmax, AUC and subcutaneous bioavailability figures are not published.
That short half-life sits oddly beside the durable effects reported in the trials, and the developers’ own explanation is a mechanistic one: the innate repair receptor is thought to “flip a switch,” initiating a repair program that continues long after the peptide has cleared 30Reference 30ReviewFlipping the molecular switch for innate protection and repair of tissues: long-lasting effects of a non-erythropoietic small peptide engineered from erythropoietin — reviewView study →. This is a plausible and explicitly stated hypothesis, not a demonstrated pharmacodynamic model — treat it as the sponsor’s framing. Because the half-life is a genuine liability, medicinal chemists have built a proteolysis-resistant thioether-cyclized helix B peptide (CHBP) to extend exposure 31,
Stability and reconstitution parameters for lyophilized material are essentially absent from the peer-reviewed literature. Analytical work on ARA-290 exists only in the anti-doping detection context 33,
Clinical & regulatory status
ARA-290 / cibinetide is an investigational, unapproved drug. It has never received marketing approval from the FDA, EMA, MHRA, TGA or any other regulator, for any indication, and it is not a dietary supplement. It was developed by Araim Pharmaceuticals, from work by Michael Brines and Anthony Cerami on non-erythropoietic EPO derivatives.
Designations are not approvals. Araim announced in its own press releases that the FDA granted ARA-290 fast-track designation for sarcoidosis-associated small-fiber neuropathy and, subsequently, orphan-drug designation for sarcoidosis; an EU orphan designation has also been reported. These are real and meaningful — orphan status carries fee waivers, tax credits and a seven-year exclusivity period if the drug is ever approved — but every one of them is a designation about a development pathway, granted on the basis of rarity and preliminary promise. None of them is a finding about whether the drug works, and none is a license to sell it. The distinction gets deliberately blurred in vendor copy.
Four registered trials, 133 participants, all Phase 1/2:
| NCT | Indication | Phase | n | Status |
|---|---|---|---|---|
| NCT02039687 | Sarcoidosis small-fiber neuropathy | 2 | 64 | Completed, results posted |
| NCT02070783 | Cognitive/neural effects (depression model) | 1/2 | 36 | Completed, no results posted |
| NCT01933529 | Prediabetes / type 2 diabetes | 2 | 24 (est.) | Unknown status, no results |
| NCT06626971 | Diabetic macular edema | 2 | 9 | Terminated — “expiry of study drug, no replacement available” |
No Phase 3 has ever been registered. The program has been quiet since the 2017 Phase 2b publication: no new ARA-290 trial has been registered in nine years, the depression indication was discontinued, the DME trial ended for want of drug supply, and Araim’s former web domain (araimpharma.com) no longer hosts a pharmaceutical company — it now resolves to unrelated commercial spam. Several secondary write-ups state the company has ceased operations; I could not confirm that from any primary source, so treat “the program has stalled” as an observation and any explanation of why as an inference, not a finding.
Prohibited in sport. WADA’s 2025 Prohibited List, section S2.1.5, prohibits “innate repair receptor agonists, e.g. asialo EPO; carbamylated EPO (CEPO)” at all times, in and out of competition, with the standard catch-all for substances of similar structure or biological effect. ARA-290 is the prototypical IRR agonist and falls squarely within that class, though it is not named on the list itself. Detection methods for it have been published 33,
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 3(Phase 1/2 and 2; one with posted results, one status-unknown) | 0 | 1(drug expiry) | ~60published animal / in vitro studies |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. ARA-290 has never been approved anywhere, for anything. It is an investigational drug that reached Phase 2 and stopped. It is not a dietary supplement and cannot lawfully be sold or marketed for human consumption in the US, UK, EU or Australia; material offered online is labeled “for research use only / not for human consumption,” which is the legally accurate frame for anyone acquiring it. It is not a scheduled or controlled substance — but “not scheduled” is not “approved,” and marketing an unapproved new drug for human use is unlawful in most Western jurisdictions. Athletes subject to anti-doping testing should treat it as banned (see above).
How it’s supplied and administered. Gray-market ARA-290 is sold as a lyophilized (freeze-dried) powder requiring reconstitution with bacteriostatic or sterile water before use. The route is injection — subcutaneous in every trial after the first. Because the plasma half-life is roughly two minutes, trial dosing was daily. Lyophilized peptide is generally stored frozen and reconstituted material refrigerated, but ARA-290-specific stability and shelf-life data are not published, so storage practice here is extrapolated from peptides generally rather than established for this one.
Sourcing reality (this is a safety issue, not a footnote). Every gray-market supply comes from unregulated vendors with no manufacturing oversight, no pharmacopeial quality control and no regulatory accountability. The documented risks across the research-peptide market are: mislabeling — wrong peptide, wrong concentration, or no active at all, none of which is detectable without assay; sub-standard purity, including synthesis by-products and truncated sequences; bacterial endotoxin contamination, which matters far more for an injectable than an oral product; and user-side reconstitution and sterility errors. Third-party certificates of analysis — mass-spec identity, HPLC purity, endotoxin testing — are the only partial check available, and certificates can be and are fabricated. There is a specific added hazard with this molecule: because it is structurally an EPO derivative, a contaminated or misidentified product cannot be assumed to carry the non-erythropoietic property that the real peptide’s entire safety case rests on. No vendor is recommended or linked here.
Safety
Nothing alarming has turned up in ARA-290’s human trials — but the entire human safety record is about 133 people dosed for no more than 28 days each, and outside a trial the realistic risks come from the unregulated injectable supply chain rather than the pharmacology.
- No safety signal in the trials. No dose-limiting toxicity up to 8 mg/day subcutaneously, and no anti-cibinetide antibodies where they were looked for.
- Absence of reported harm is not evidence of safety. Roughly 133 people, all dosed 28 days or less; chronic safety is entirely unknown.
- Unapproved investigational drug. Never approved by any regulator for any indication, and not a dietary supplement.
- Gray-market injectable risk. Mislabeling, sub-standard purity, endotoxin contamination and non-sterile technique are the real-world hazards.
- Interactions not assessed. No controlled human drug-interaction data of any kind exist.
- Prohibited in sport. WADA bans innate repair receptor agonists at all times, with a default four-year ban.
Full Safety & Interactions Detail
Overall posture. In the small, short human trials to date, ARA-290 was reported as well tolerated, with no dose-limiting toxicity up to 8 mg/day subcutaneously and no clinically significant changes on laboratory or clinical assessment 1,
The central safety question is the premise itself, and it deserves a precise answer. The whole point of ARA-290 is “EPO’s tissue protection without EPO’s hematopoietic effects” — which would mean without the rise in hematocrit, and without the thrombotic and hypertensive risk that ended EPO’s career as a tissue-protective drug. How well is that established?
- Mechanistically: strongly. The peptide is built from the region of EPO that does not contact the EPO-receptor homodimer, and it does not bind it 30,
31Reference 30ReviewFlipping the molecular switch for innate protection and repair of tissues: long-lasting effects of a non-erythropoietic small peptide engineered from erythropoietin — reviewView study →Reference 31ReviewFrom erythropoietin to its peptide derivatives: smaller but stronger — reviewView study → . This is not a claim of degree; it is a structural property. - In animals: confirmed, repeatedly and explicitly. Multiple independent rodent studies report tissue protection specifically without stimulation of hematopoiesis, and it is stated as a measured result rather than an assumption in the lupus and metabolic work 22,
27Reference 22AnimalNon-erythropoietic erythropoietin-derived peptide protects mice from systemic lupus erythematosus — animal (mouse)View study →Reference 27In vitroNonerythropoietic erythropoietin-derived peptide suppresses adipogenesis, inflammation, obesity and insulin resistance — animal (mouse) / in vitroView study → . Cardioprotection studies made the same comparison directly against EPO 12,13Reference 12In vitroCardioprotection by a nonerythropoietic, tissue-protective peptide mimicking the 3D structure of erythropoietin — animal (rat, hamster) / in vitroView study →Reference 13In vitroA small nonerythropoietic helix B surface peptide based upon erythropoietin structure is cardioprotective against ischemic myocardial damage — animal (rat) / in vitroView study → . - In humans: supported, but by absence rather than by publication. Every trial monitored laboratory parameters and none reported a hematological abnormality 1,
3, . However, I could not locate a published human hemoglobin or hematocrit dataset for cibinetide. The Phase 2b listed “laboratory parameters” as a secondary outcome but posted only adverse-event counts against it, with no hematology reported.6, 8Reference 1RCTSafety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT)View study →Reference 3RCTCibinetide improves corneal nerve fiber abundance in patients with sarcoidosis-associated small nerve fiber loss and neuropathic pain — human (RCT, Phase 2b)View study →Reference 6RCTARA 290, a nonerythropoietic peptide engineered from erythropoietin, improves metabolic control and neuropathic symptoms in patients with type 2 diabetes — human (RCT, Phase 2)View study →Reference 8Clinical trialA Phase 2 clinical trial on the use of cibinetide for the treatment of diabetic macular edema — human (single-arm Phase 2, null on objective endpoints)View study →
So the correct statement is: the non-erythropoietic property is well-established mechanistically and directly confirmed in animals, and nothing in the human trials contradicts it — but no human trial has published the hemoglobin data that would confirm it outright. That is a good deal stronger than most claims made for peptides on this market, and it is not the same as proven in people.
Adverse effects. With subcutaneous self-administration, the most relevant practical risks are injection-related: injection-site reactions, and — with unregulated material or non-sterile technique — local or systemic infection, abscess, and reactions to endotoxin-contaminated product. These are properties of the route and the supply chain, not of the peptide’s pharmacology, but they are the risks a person outside a trial actually faces.
Interactions. Not assessed. No controlled human drug-interaction study exists and no specific interaction has been established, so none can be responsibly named.
Who should avoid it. Anyone outside a clinical trial, given that it is an unapproved investigational drug with no approved indication anywhere; anyone who cannot source assayed, endotoxin-tested material or maintain sterile injection technique; athletes subject to anti-doping testing; and, by default on absence of data, anyone pregnant, breastfeeding or trying to conceive.
Scope disclosure (honesty, not a claim):
- Human data? Yes, but limited — four registered Phase 1/2 trials totalling 133 participants, largest n=64, all ≤28 days of dosing, plus one unregistered published Phase 2. No Phase 3, no approval anywhere.
- Interactions assessed? No. No controlled drug-interaction data of any kind.
- Pregnancy/lactation assessed? No — no human or animal reproductive data located.
- Long-term safety established? No. The longest human exposure on record is 28 days. Chronic safety is entirely unknown.
- Non-erythropoietic property confirmed in humans? Mechanistically yes, in animals yes, in published human hematology data — not located. See above.
Never imply safety from silence. Where ARA-290 has not been studied — interactions, pregnancy, chronic use, gray-market product identity — the correct statement is “not assessed,” not “safe.”
Not assessed / not established. There are no human pregnancy or lactation data and no published reproductive-toxicology studies for cibinetide. Treat as contraindicated by default.
Dosage
There is no established human dose for ARA-290, and none is recommended here. It is not an approved drug or supplement in any jurisdiction, and every figure below is trial data reported for context, not a personal recommendation — do not read it as a protocol.
The regimens actually studied were: 2 mg intravenously, three times weekly for four weeks (the first sarcoidosis pilot) 1Reference 1RCTSafety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT)View study →; and 1, 4 or 8 mg/day subcutaneously for 28 days in every trial since, with 4 mg/day the dose carried into the Phase 2b, the type 2 diabetes study and the macular edema study 3,
No maintenance schedule has ever been established, because no trial has run longer than 28 days. Oral dosing is pharmacologically meaningless regardless of what a label says (see Pharmacokinetics). This entry is informational only.
References
- Heij L, Niesters M, Swartjes M, et al. (2012). Safety and efficacy of ARA 290 in sarcoidosis patients with symptoms of small fiber neuropathy: a randomized, double-blind pilot study — human (RCT). Mol Med. https://pubmed.ncbi.nlm.nih.gov/23168581/
- Dahan A, Dunne A, Swartjes M, et al. (2013). ARA 290 improves symptoms in patients with sarcoidosis-associated small nerve fiber loss and increases corneal nerve fiber density — human (RCT). Mol Med. https://pubmed.ncbi.nlm.nih.gov/24136731/
- Culver DA, Dahan A, Bajorunas D, et al. (2017). Cibinetide improves corneal nerve fiber abundance in patients with sarcoidosis-associated small nerve fiber loss and neuropathic pain — human (RCT, Phase 2b). Invest Ophthalmol Vis Sci. https://pubmed.ncbi.nlm.nih.gov/28475703/
- Brines M, Culver DA, Ferdousi M, et al. (2018). Corneal nerve fiber size adds utility to the diagnosis and assessment of therapeutic response in patients with small fiber neuropathy — human (diagnostic / biomarker study, not a trial). Sci Rep. https://pubmed.ncbi.nlm.nih.gov/29549285/
- van Velzen M, Heij L, Niesters M, et al. (2014). ARA 290 for treatment of small fiber neuropathy in sarcoidosis — review. Expert Opin Investig Drugs. https://pubmed.ncbi.nlm.nih.gov/24555851/
- Brines M, Dunne AN, van Velzen M, et al. (2015). ARA 290, a nonerythropoietic peptide engineered from erythropoietin, improves metabolic control and neuropathic symptoms in patients with type 2 diabetes — human (RCT, Phase 2). Mol Med. https://pubmed.ncbi.nlm.nih.gov/25387363/
- Cerit H, Veer IM, Dahan A, et al. (2015). Testing the antidepressant properties of the peptide ARA290 in a human neuropsychological model of drug action — human (RCT, negative). Eur Neuropsychopharmacol. https://pubmed.ncbi.nlm.nih.gov/26431906/
- Lois N, Gardner E, McFarland M, et al. (2020). A Phase 2 clinical trial on the use of cibinetide for the treatment of diabetic macular edema — human (single-arm Phase 2, null on objective endpoints). J Clin Med. https://pubmed.ncbi.nlm.nih.gov/32674280/
- Swartjes M, van Velzen M, Niesters M, et al. (2014). ARA 290, a peptide derived from the tertiary structure of erythropoietin, produces long-term relief of neuropathic pain coupled with suppression of the spinal microglia response — animal (rat). Mol Pain. https://pubmed.ncbi.nlm.nih.gov/24529189/
- Pulman KG, Smith M, Mengozzi M, et al. (2013). The erythropoietin-derived peptide ARA290 reverses mechanical allodynia in the neuritis model — animal (rat). Neuroscience. https://pubmed.ncbi.nlm.nih.gov/23262243/
- Zhang W, Yu G, Zhang M (2016). ARA 290 relieves pathophysiological pain by targeting TRPV1 channel: integration between immune system and nociception — in vitro / animal (rodent). Peptides. https://pubmed.ncbi.nlm.nih.gov/26774587/
- Ueba H, Brines M, Yamin M, et al. (2010). Cardioprotection by a nonerythropoietic, tissue-protective peptide mimicking the 3D structure of erythropoietin — animal (rat, hamster) / in vitro. Proc Natl Acad Sci U S A. https://pubmed.ncbi.nlm.nih.gov/20660739/
- Ahmet I, Tae HJ, Juhaszova M, et al. (2011). A small nonerythropoietic helix B surface peptide based upon erythropoietin structure is cardioprotective against ischemic myocardial damage — animal (rat) / in vitro. Mol Med. https://pubmed.ncbi.nlm.nih.gov/21170473/
- Winicki NM, Nanavati AP, Morrell CH, et al. (2022). A small erythropoietin derived non-hematopoietic peptide reduces cardiac inflammation, attenuates age associated declines in heart function and prolongs healthspan — animal (rat, 15-month randomised controlled study). Front Cardiovasc Med. https://pubmed.ncbi.nlm.nih.gov/36741836/
- Shokrzadeh M, Etebari M, Ghassemi-Barghi N (2020). An engineered non-erythropoietic erythropoietin-derived peptide, ARA290, attenuates doxorubicin-induced genotoxicity and oxidative stress — in vitro. Toxicol In Vitro. https://pubmed.ncbi.nlm.nih.gov/32335150/
- van Rijt WG, Nieuwenhuijs-Moeke GJ, van Goor H, et al. (2013). ARA290, a non-erythropoietic EPO derivative, attenuates renal ischemia/reperfusion injury — animal (pig). J Transl Med. https://pubmed.ncbi.nlm.nih.gov/23302512/
- van Rijt WG, Nieuwenhuijs-Moeke GJ, van Goor H, et al. (2013). Renoprotective capacities of non-erythropoietic EPO derivative, ARA290, following renal ischemia/reperfusion injury — animal (rat). J Transl Med. https://pubmed.ncbi.nlm.nih.gov/24225194/
- Yan L, Zhang H, Gao S, et al. (2018). EPO derivative ARA290 attenuates early renal allograft injury in rats by targeting NF-κB pathway — animal (rat). Transplant Proc. https://pubmed.ncbi.nlm.nih.gov/29880388/
- Liu Y, Luo B, Han F, et al. (2014). Erythropoietin-derived nonerythropoietic peptide ameliorates experimental autoimmune neuritis by inflammation suppression and tissue protection — animal (rat). PLoS One. https://pubmed.ncbi.nlm.nih.gov/24603865/
- Chen H, Luo B, Yang X, et al. (2014). Therapeutic effects of nonerythropoietic erythropoietin analog ARA290 in experimental autoimmune encephalomyelitis rat — animal (rat). J Neuroimmunol. https://pubmed.ncbi.nlm.nih.gov/24518674/
- Nairz M, Haschka D, Dichtl S, et al. (2017). Cibinetide dampens innate immune cell functions thus ameliorating the course of experimental colitis — animal (mouse) / in vitro. Sci Rep. https://pubmed.ncbi.nlm.nih.gov/29026145/
- Huang B, Jiang J, Luo B, et al. (2018). Non-erythropoietic erythropoietin-derived peptide protects mice from systemic lupus erythematosus — animal (mouse). J Cell Mol Med. https://pubmed.ncbi.nlm.nih.gov/29570934/
- Yao M, Domogatskaya A, Ågren N, et al. (2021). Cibinetide protects isolated human islets in a stressful environment and improves engraftment in the perspective of intraportal islet transplantation — in vitro (human islets) / animal (mouse). Cell Transplant. https://pubmed.ncbi.nlm.nih.gov/34498509/
- Yao M, Watanabe M, Sun S, et al. (2020). Improvement of islet allograft function using cibinetide, an innate repair receptor ligand — animal (mouse). Transplantation. https://pubmed.ncbi.nlm.nih.gov/32345869/
- Bitto A, Irrera N, Minutoli L, et al. (2018). Activation of the EPOR-β common receptor complex by cibinetide ameliorates impaired wound healing in mice with genetic diabetes — animal (mouse). Biochim Biophys Acta Mol Basis Dis. https://pubmed.ncbi.nlm.nih.gov/29223734/
- Awida Z, Hiram-Bab S, Bachar A, et al. (2021). The non-erythropoietic EPO analogue cibinetide inhibits osteoclastogenesis in vitro and increases bone mineral density in mice — in vitro / animal (mouse). Int J Mol Sci. https://pubmed.ncbi.nlm.nih.gov/35008482/
- Liu Y, Luo B, Shi R, et al. (2015). Nonerythropoietic erythropoietin-derived peptide suppresses adipogenesis, inflammation, obesity and insulin resistance — animal (mouse) / in vitro. Sci Rep. https://pubmed.ncbi.nlm.nih.gov/26459940/
- RETRACTED — Collino M, Benetti E, Rogazzo M, et al. (2014). A non-erythropoietic peptide derivative of erythropoietin decreases susceptibility to diet-induced insulin resistance in mice — animal (mouse); retracted publication, cited here only as a retraction. Br J Pharmacol. https://pubmed.ncbi.nlm.nih.gov/25164531/
- Patel NSA, Kerr-Peterson HL, Brines M, et al. (2026). Retraction note: delayed administration of pyroglutamate helix B surface peptide (pHBSP), a novel nonerythropoietic analog of erythropoietin, attenuates acute kidney injury — retraction notice. Mol Med. https://pubmed.ncbi.nlm.nih.gov/41749083/
- Collino M, Thiemermann C, Cerami A, Brines M (2015). Flipping the molecular switch for innate protection and repair of tissues: long-lasting effects of a non-erythropoietic small peptide engineered from erythropoietin — review. Pharmacol Ther. https://pubmed.ncbi.nlm.nih.gov/25728128/
- Zhang C, Yang C, Zhu T (2017). From erythropoietin to its peptide derivatives: smaller but stronger — review. Curr Protein Pept Sci. https://pubmed.ncbi.nlm.nih.gov/27634443/
- Liu G, Wang J, Wang X, et al. (2024). The protective effect of erythropoietin and its novel derived peptides in peripheral nerve injury — review. Int Immunopharmacol. https://pubmed.ncbi.nlm.nih.gov/38943972/
- Thomas A, Knoop A, Schänzer W, et al. (2017). Characterization of in vitro generated metabolites of selected peptides <2 kDa prohibited in sports — in vitro. Drug Test Anal. https://pubmed.ncbi.nlm.nih.gov/28941172/
- Thomas A, Görgens C, Guddat S, et al. (2016). Simplifying and expanding the screening for peptides <2 kDa by direct urine injection, liquid chromatography, and ion mobility-mass spectrometry — in vitro (analytical method). J Sep Sci. https://pubmed.ncbi.nlm.nih.gov/26578461/
- Brines, M., Dunne, A. N., van Velzen, M., et al. (2014). ARA 290, a nonerythropoietic peptide engineered from erythropoietin, improves metabolic control and neuropathic symptoms in patients with type 2 diabetes. Molecular Medicine. https://pmc.ncbi.nlm.nih.gov/articles/PMC4365069/



