
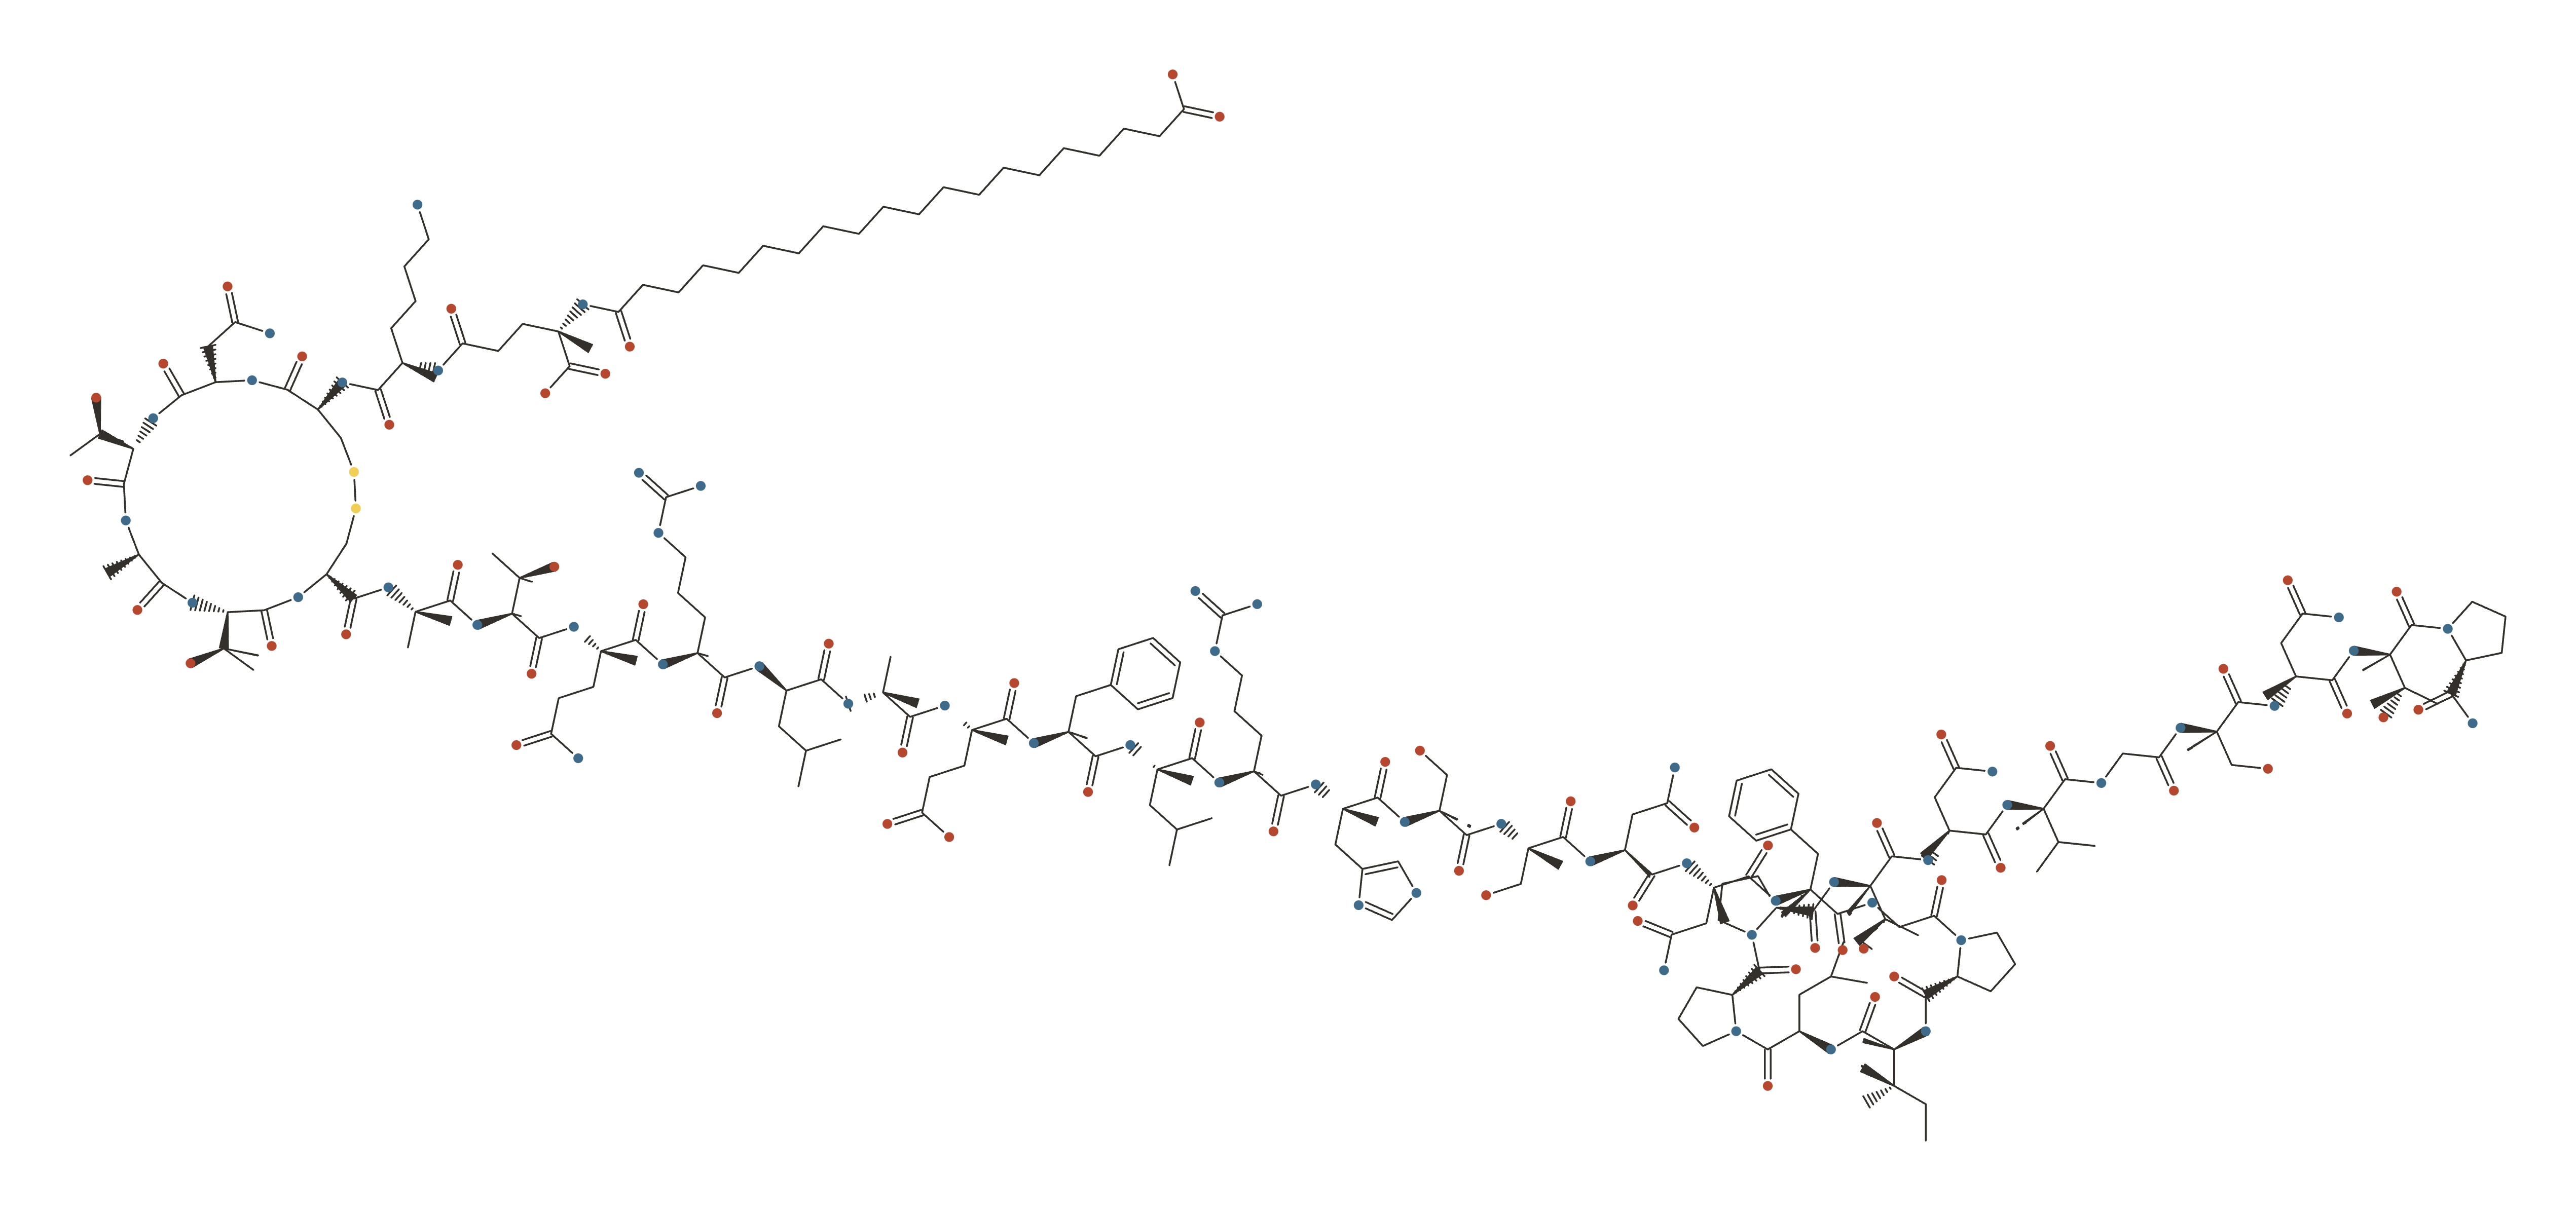
Cagrilintide
An investigational once-weekly injectable amylin analogue for weight management, studied mostly in the semaglutide combination CagriSema. Not approved anywhere.

Cagrilintide at a Glance
Cagrilintide is a long-acting analogue of amylin, a hormone the pancreas releases alongside insulin that slows gastric emptying and signals fullness through a different brain pathway than GLP-1. That independence is the point: it is studied mostly in combination with semaglutide, where two separate satiety signals produce more weight loss than either alone. It is investigational, and the combination is where nearly all of its development sits.
History & Development
Cagrilintide is not a GLP-1 drug, and that is the point of it. It works on amylin - a separate satiety hormone released alongside insulin - which is why pairing it with semaglutide produces more weight loss than either does alone.
| First described | Development of the compound published 2021, as AM833 13Reference 13Development of Cagrilintide, a Long-Acting Amylin Analogue — medicinal chemistry / discoveryView study → |
| Discovered / synthesised by | Novo Nordisk research programme 13Reference 13Development of Cagrilintide, a Long-Acting Amylin Analogue — medicinal chemistry / discoveryView study → |
| Institution | Novo Nordisk, Maloev, Denmark 13Reference 13Development of Cagrilintide, a Long-Acting Amylin Analogue — medicinal chemistry / discoveryView study → |
| Origin | Long-acting acylated amylin analogue; non-selective amylin receptor agonist |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Novo Nordisk |
| Development status | Investigational - phase 3 (REDEFINE programme, as CagriSema); not approved anywhere |
Discovery
Amylin is co-secreted with insulin from pancreatic beta cells and signals fullness through the brainstem - a satiety pathway entirely separate from GLP-1. Native amylin is useless as a drug: it aggregates and has a very short half-life.
Cagrilintide solves that by acylation - attaching a fatty-acid chain that binds albumin and extends the half-life enough for once-weekly dosing, the same strategy behind semaglutide. The development work was published in 2021 under the code AM833, describing a long-acting amylin analogue selected for clinical development in obesity 13Reference 13Development of Cagrilintide, a Long-Acting Amylin Analogue — medicinal chemistry / discoveryView study →. Recent work has localised its weight-lowering effect to brain amylin receptors 1 and 3 20Reference 20eBioMedicine. https://www.thelancet.com/journals/ebiom/article/PIIS2352-3964(25)00280-4/fulltextView study →.
Development & ownership
Cagrilintide has been developed entirely within Novo Nordisk, and its programme has an unusual shape: most of the clinical evidence is for the combination rather than the molecule.
CagriSema - cagrilintide co-formulated with semaglutide 2.4 mg - is what reached phase 3, and its results are the headline figures: -20.4% versus -3.0% on placebo at 68 weeks in REDEFINE 1 (n=3,417). Cagrilintide alone has a phase 2 dose-finding trial (n=706) giving 6.0-10.8% weight loss against 3.0% on placebo at 26 weeks, modestly beating daily liraglutide at the top dose 21Reference 21RCTOnce-weekly cagrilintide for weight management in people with overweight and obesity: a multicentre, randomised, double-blind, placebo-controlled and active-controlled, dose-finding phase 2 trialView study →.
That structure matters for reading any claim about cagrilintide: the strongest numbers belong to a two-drug product, and the molecule’s own contribution is the smaller phase 2 story.
It is not approved by the FDA, the EMA or any other regulator, for any indication, anywhere.
How it reached the market
It has not. Cagrilintide is investigational and available only through clinical trials. Its appearance in grey-market channels - typically sold as an “amylin” peptide alongside GLP-1 compounds - supplies a molecule whose own monotherapy dose-finding is still the most recent word on it.
What It's Used For
Cagrilintide (AM833 / NNC0174-0833) is an investigational drug, not approved by the FDA, the EMA, or any other regulator, for any indication, anywhere in the world. It is also not a GLP-1 agonist, and that is the first thing to get right about it. Cagrilintide is a long-acting analogue of amylin — the pancreatic hormone co-secreted with insulin — engineered by Novo Nordisk with a fatty-diacid side chain that binds albumin and stretches its half-life to about a week. It acts as a dual amylin and calcitonin receptor agonist (a DACRA), engaging AMY1R/AMY3R and the calcitonin receptor to promote satiety and slow gastric emptying 13,
And the combination is the second thing to get right, because it governs how every number below should be read. Most of cagrilintide’s clinical program is CagriSema — cagrilintide co-formulated with semaglutide 2.4 mg. A CagriSema result is not a cagrilintide result. You cannot attribute a combination’s effect to one of its components unless the trial randomized people to that component alone, and the headline figure everyone quotes — roughly −20% body weight at 68 weeks in REDEFINE 1 4Reference 4RCTCoadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity (REDEFINE 1) — human (RCT, phase 3a, n=3,417; includes a cagrilintide-alone arm)View study → — is the combination’s, containing a full therapeutic dose of an already-approved GLP-1 drug. To this compound’s credit, several trials did include a cagrilintide-monotherapy arm, so the molecule’s own contribution is not unknowable; it is separately scored below. The short version is that cagrilintide alone produces meaningful weight loss that a 2026 meta-analysis found comparable to semaglutide, with a higher rate of serious adverse events 18Reference 18Meta-analysisEfficacy and Safety of Cagrilintide and Cagrisema Versus Semaglutide as Anti-Obesity Medications: A Systematic Review and Meta-Analysis — human (systematic review / meta-analysis of 3 RCTs, n=3,545)View study → — which is a very different proposition from the combination headline.
Route is load-bearing: subcutaneous injection, once weekly, oral-inactive. And because no approved cagrilintide product exists anywhere, there is no legitimate supply route for anyone outside a clinical trial — see Sourcing, Route & Legal Status, which is the most decision-relevant section here.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Read the top row carefully: it scores CagriSema, a two-drug combination containing semaglutide, and it is not a score for cagrilintide as a single agent. The monotherapy row is the one that describes this molecule on its own, and it scores lower not because cagrilintide was never tested alone but because — when it was tested alone — it performed about as well as an approved drug while causing more serious adverse events. No score here can exceed the ceiling imposed by the compound being unapproved everywhere.
Human phase 3 RCT evidence — for a combination product. CagriSema is a fixed once-weekly subcutaneous combination of cagrilintide 2.4 mg and semaglutide 2.4 mg. In REDEFINE 1 (NCT05567796, phase 3a, 68 weeks, n=3,417 adults with obesity or overweight-plus-a-complication and without diabetes), the estimated mean weight change was −20.4% with CagriSema versus −3.0% with placebo (difference −17.3 percentage points, P<0.001), with gastrointestinal adverse events in 79.6% of the combination group versus 39.9% on placebo 4Reference 4RCTCoadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity (REDEFINE 1) — human (RCT, phase 3a, n=3,417; includes a cagrilintide-alone arm)View study →. REDEFINE 2 (NCT05394519, n=1,206, obesity plus type 2 diabetes) gave −13.7% versus −3.4% at 68 weeks 5Reference 5RCTCagrilintide-Semaglutide in Adults with Overweight or Obesity and Type 2 Diabetes (REDEFINE 2) — human (RCT, phase 3)View study →, and a phase 3 East Asian trial (NCT05813925, n=331) reported greater weight loss than semaglutide alone 6Reference 6RCTEfficacy and safety of co-administered cagrilintide and semaglutide versus semaglutide alone in adults from East Asia with overweight or obesity — human (RCT, phase 3)View study →. A 2026 systematic review and meta-analysis of three RCTs (n=3,545) found CagriSema produced 7.47 percentage points more weight loss than semaglutide — but also more administration-site reactions (RR 3.27) and nausea (RR 1.64) 18Reference 18Meta-analysisEfficacy and Safety of Cagrilintide and Cagrisema Versus Semaglutide as Anti-Obesity Medications: A Systematic Review and Meta-Analysis — human (systematic review / meta-analysis of 3 RCTs, n=3,545)View study →. The phase 1b combination study established the additivity in the first place 1Reference 1RCTSafety, tolerability, pharmacokinetics, and pharmacodynamics of concomitant administration of multiple doses of cagrilintide with semaglutide 2·4 mg for weight management: a randomised, controlled, phase 1b trial — human (RCT, phase 1b)View study →.
The arithmetic problem is unavoidable: semaglutide 2.4 mg alone delivers roughly 15% weight loss in this population, so the combination’s advantage over its GLP-1 component — about 7.5 points 18Reference 18Meta-analysisEfficacy and Safety of Cagrilintide and Cagrisema Versus Semaglutide as Anti-Obesity Medications: A Systematic Review and Meta-Analysis — human (systematic review / meta-analysis of 3 RCTs, n=3,545)View study → — is the honest measure of what cagrilintide contributes here, not the 20.4% headline.
Commercial context, offered as such rather than as a clinical finding: Novo Nordisk’s December 2024 topline announcement of REDEFINE 1 was widely reported as falling short of analyst expectations, and the company’s share price fell sharply on the news. That is a financial fact about a forecast, not a clinical one about the drug. A trial can produce one of the largest weight losses ever recorded in obesity pharmacotherapy and still disappoint investors who had priced in more. (Note also that press-released topline numbers and the later peer-reviewed figures can differ because they use different statistical estimands; only the published figures are cited above.)
Gap: no approval anywhere, and this is combination evidence. REDEFINE 1 remains active, not recruiting at this check (extension to late 2026) despite its 68-week publication, and the cardiovascular-outcomes trial REDEFINE 3 (NCT05669755, n=7,101) is active with completion projected for 2027 — so there are no hard-outcome data. Durability past 68 weeks and regain after stopping are unaddressed.
Human RCT evidence, again mostly for the combination. The REIMAGINE phase 3 program tested CagriSema in type 2 diabetes and read out in 2026: superiority to placebo on HbA1c in people managed by diet and exercise (REIMAGINE 1) 8Reference 8RCTEfficacy and safety of once-weekly cagrilintide-semaglutide (CagriSema) in adults with type 2 diabetes inadequately controlled by diet and exercise (REIMAGINE 1) — human (RCT, phase 3)View study →; superiority to semaglutide 2.4 mg on HbA1c in people on metformin ± an SGLT2 inhibitor (REIMAGINE 2, n=2,713) 9Reference 9RCTCagrilintide-semaglutide (CagriSema) versus semaglutide or cagrilintide in people with type 2 diabetes (REIMAGINE 2) — human (RCT, phase 3, n=2,713; includes a cagrilintide-alone arm)View study →; and significant HbA1c reduction as an add-on to basal insulin without excess severe hypoglycemia (REIMAGINE 3) 10Reference 10RCTCagrilintide-semaglutide (CagriSema) as an add-on to basal insulin in adults with type 2 diabetes (REIMAGINE 3) — human (RCT, phase 3)View study →. The earlier phase 2 trial in type 2 diabetes (n=92) showed CagriSema improved glycemic control, including continuous-glucose-monitoring parameters, relative to either agent alone 3Reference 3RCTEfficacy and safety of co-administered once-weekly cagrilintide 2·4 mg with once-weekly semaglutide 2·4 mg in type 2 diabetes: a multicentre, randomised, double-blind, active-controlled, phase 2 trial — human (RCT, phase 2, with a cagrilintide-alone arm)View study →.
REIMAGINE 2 is the most useful trial here for the attribution problem, because it randomized a cagrilintide 2.4 mg monotherapy arm (n=152) alongside CagriSema and semaglutide 9Reference 9RCTCagrilintide-semaglutide (CagriSema) versus semaglutide or cagrilintide in people with type 2 diabetes (REIMAGINE 2) — human (RCT, phase 3, n=2,713; includes a cagrilintide-alone arm)View study →. That design is what makes it possible to say anything at all about the amylin component’s independent contribution — and what most of the program, being combination-only, does not permit.
Gap: no approval for diabetes. Amylin analogues lower post-prandial glucose largely by slowing gastric emptying and suppressing glucagon rather than by driving insulin secretion, so cagrilintide’s independent glycemic effect is modest next to the semaglutide component. Durability beyond about a year is untested.
This is the row that describes the molecule itself, and it is deliberately scored below the combination. The principal dataset is the phase 2 dose-finding RCT (Lau 2021): 57 sites in ten countries, 706 adults with overweight or obesity and without diabetes randomized to once-weekly cagrilintide 0.3–4.5 mg, plus 99 to liraglutide 3.0 mg and 101 to placebo, over 26 weeks. Mean weight reduction was 6.0–10.8% across the cagrilintide doses versus 3.0% for placebo (P<0.001), and cagrilintide 4.5 mg modestly beat daily liraglutide 3.0 mg (10.8% vs 9.0%, P=0.03). Gastrointestinal events occurred in 41–63% of cagrilintide participants versus 32% on placebo 2Reference 2RCTOnce-weekly cagrilintide for weight management in people with overweight and obesity: a multicentre, randomised, double-blind, placebo-controlled and active-controlled, dose-finding phase 2 trial — human (RCT, phase 2, monotherapy)View study →. Randomized monotherapy arms also sit inside the phase 3 trials — n=302 in REDEFINE 1 4Reference 4RCTCoadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity (REDEFINE 1) — human (RCT, phase 3a, n=3,417; includes a cagrilintide-alone arm)View study → and n=152 in REIMAGINE 2 9Reference 9RCTCagrilintide-semaglutide (CagriSema) versus semaglutide or cagrilintide in people with type 2 diabetes (REIMAGINE 2) — human (RCT, phase 3, n=2,713; includes a cagrilintide-alone arm)View study → — and inside the phase 2 diabetes trial (n=30) 3Reference 3RCTEfficacy and safety of co-administered once-weekly cagrilintide 2·4 mg with once-weekly semaglutide 2·4 mg in type 2 diabetes: a multicentre, randomised, double-blind, active-controlled, phase 2 trial — human (RCT, phase 2, with a cagrilintide-alone arm)View study →.
Pooled, the picture is sobering for anyone using it as a standalone agent: the 2026 meta-analysis found cagrilintide monotherapy weight loss comparable to semaglutide, with a higher risk of serious adverse events (RR 1.83, 95% CI 1.03–3.24) 18Reference 18Meta-analysisEfficacy and Safety of Cagrilintide and Cagrisema Versus Semaglutide as Anti-Obesity Medications: A Systematic Review and Meta-Analysis — human (systematic review / meta-analysis of 3 RCTs, n=3,545)View study →. So the honest read on single-agent cagrilintide is roughly as effective as an approved drug you could get from a doctor, apparently less well tolerated, and not approved anywhere.
Gap: no monotherapy indication is being pursued. Novo Nordisk’s phase 3 and commercial program is built around the combination, so long-term standalone efficacy and safety will most likely never be established — this is a permanent evidence gap, not a temporary one. Every gray-market vial is sold for exactly the use the sponsor has chosen not to develop.
Human, but a secondary and post-hoc analysis of a weight-loss trial — not a cardiovascular outcome. A secondary/post-hoc analysis of REDEFINE 1 reported that CagriSema reduced systolic blood pressure by about −10.9 mmHg versus −2.8 mmHg for placebo and diastolic by −5.4 versus −1.7 mmHg at week 68, with more participants reaching blood-pressure targets and reducing antihypertensive medication 7Reference 7RCTCagriSema Reduces Blood Pressure in Adults With Overweight or Obesity: REDEFINE 1 — human (secondary/post-hoc analysis of a phase 3 RCT)View study →. Lipid effects across the program were largely neutral, although the 2026 meta-analysis found LDL-C modestly higher with the combination than with semaglutide alone (mean difference +0.29 mmol/L) 18Reference 18Meta-analysisEfficacy and Safety of Cagrilintide and Cagrisema Versus Semaglutide as Anti-Obesity Medications: A Systematic Review and Meta-Analysis — human (systematic review / meta-analysis of 3 RCTs, n=3,545)View study → — a null-to-adverse signal carried here as found.
All of this is CagriSema, and most of it is plausibly downstream of the weight loss rather than a distinct pharmacological action of the amylin component.
Gap: no cardiovascular outcome data of any kind. Every figure here is a biomarker measured as a secondary endpoint in a weight-loss trial, and the dedicated outcomes trial — REDEFINE 3 (NCT05669755, ~7,101 participants) — was active, not recruiting at this check with completion projected for 2027. Nothing here is attributable to cagrilintide alone.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Amylin receptors AMY1R / AMY3R (calcitonin receptor + RAMP1/RAMP3) | Agonist → satiety, reduced food intake; mouse knockout work shows weight loss depends on brain AMY1R/AMY3R 16Reference 16AnimalCagrilintide lowers bodyweight through brain amylin receptors 1 and 3 — animal (mouse)View study → | Weight lossappetite |
| Calcitonin receptor (CTR) | Non-selective agonist — the “dual” in dual amylin/calcitonin receptor agonist 14Reference 14In vitroAM833 Is a Novel Agonist of Calcitonin Family G Protein-Coupled Receptors: Pharmacological Comparison with Six Selective and Nonselective Agonists — in vitroView study →; cryo-EM describes a bypass binding mode shared across both receptors 15Reference 15In vitroStructural and mechanistic insights into dual activation of cagrilintide in amylin and calcitonin receptors — in vitro (cryo-EM)View study → | Receptor pharmacologyduration of action |
| Dorsal vagal complex / hypothalamic satiety circuits | Activation of central appetite-suppressing neurons (rodent) 16Reference 16AnimalCagrilintide lowers bodyweight through brain amylin receptors 1 and 3 — animal (mouse)View study → | Appetitefood-intake reduction |
| Gastric emptying | Slowed — the classical amylin action, and the source of both the satiety effect and the GI adverse events | Weight lossGI tolerabilityoral-drug absorption |
| GLP-1 receptor | None. Cagrilintide has no GLP-1 receptor activity; the GLP-1 arm of CagriSema is semaglutide | The most common misunderstanding about this compound |
| Complementarity with GLP-1 agonism | Distinct satiety pathways → greater weight loss together than either alone 1, | The CagriSema rationale |
| Fatty-diacid acylation → albumin binding | Resists amyloid fibrillation and prolongs residence time 13Reference 13Development of Cagrilintide, a Long-Acting Amylin Analogue — medicinal chemistry / discoveryView study → | Once-weekly dosing (PK) |
Pharmacokinetics
Route is load-bearing. Cagrilintide is given by once-weekly subcutaneous injection. Like other therapeutic peptides of this size its oral bioavailability is negligible — it is digested rather than absorbed — so any “oral cagrilintide” product is pharmacologically inert regardless of the label.
The engineering problem cagrilintide solves is worth stating, because it explains the whole molecule. Native human amylin is strongly amyloidogenic and very short-acting; the marketed amylin analogue pramlintide requires three injections a day. Cagrilintide was redesigned with a fatty-diacid lipidation that binds albumin, resists fibrillation, and extends duration to a weekly schedule 13,
Dedicated clinical-pharmacology studies found no clinically relevant PK change with renal or hepatic impairment, so no dose adjustment was indicated on that basis 11Reference 11Renal or Hepatic Impairment Does Not Affect Pharmacokinetics, Safety, or Tolerability of Subcutaneous Cagrilintide — human (clinical pharmacology / PK)View study →, and no clinically relevant QTc prolongation at 4.5 mg in a thorough QT study 12Reference 12RCTCagrilintide is not associated with clinically relevant QTc prolongation: A thorough QT study in healthy participants — human (RCT, thorough QT)View study →. Trial dosing is titrated upward specifically to limit gastrointestinal intolerance — the titration is the mitigation for the dose-limiting effect, not a formality. Reconstitution and stability parameters for lyophilized gray-market powder are not independently documented anywhere, because no such product is a characterized pharmaceutical.
Clinical & regulatory status
Cagrilintide is an investigational drug with no marketing approval anywhere in the world as of this check — not approved by the FDA, EMA, TGA or PMDA, not a prescription medicine, and not a dietary supplement. It is Novo Nordisk’s proprietary candidate. A ClinicalTrials.gov search of the cagrilintide intervention set returns 42 registered studies — about 17 phase 1, 5 phase 2 and 20 phase 3 — spanning obesity, type 2 diabetes, cardiovascular outcomes and pediatric obesity, and the overwhelming majority test the CagriSema combination rather than cagrilintide alone.
The temporal distinctions matter here as much as the count. Registered is not completed; completed is not reported; press-released is not published. REDEFINE 2 (NCT05394519) and the East Asian trial (NCT05813925) are completed and published 5,
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 21 | 19(10 recruiting + 8 active-not-recruiting + 1 not-yet-recruiting) | 0(2 withdrawn) | In vitro receptor pharmacology 14, |
Trial counts from the ClinicalTrials.gov “cagrilintide” intervention record set (42 studies). Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status — read this before anything else on the page. Cagrilintide has no marketing approval in any jurisdiction. It is not FDA-approved, not EMA-approved, not TGA- or PMDA-approved, not a prescription drug, and not a dietary supplement. There is no label, no approved indication, no approved dose, and no pharmacy anywhere that can lawfully dispense it. The only lawful way for a person to receive cagrilintide is as a participant in a registered clinical trial. A regulatory filing for the CagriSema combination has been anticipated for some time; anticipated is not approved, and even an approval would be for the combination product, not for single-agent cagrilintide.
This means there is no legitimate source, and that is the spine of this section. Because no approved product exists, there is no diverted-pharmaceutical channel, no compounded-from-approved-drug channel, and no counterfeit-of-a-real-product channel of the kind that complicates semaglutide. Every vial sold as “cagrilintide” to a member of the public is, by definition, unregulated research-chemical material — synthesized by an unaccountable manufacturer, labeled “for research use only / not for human consumption,” and never subject to any regulatory or pharmacopoeial standard. There is no version of buying cagrilintide online that is the trial drug.
The verification problem is structurally worse than for approved drugs. With no legitimate product in existence there is no reference pen, no known appearance, no authorized price, and no pharmacist in the loop — a buyer has no way at all to distinguish genuine cagrilintide from a cheaper peptide, a degraded batch, an underfilled vial, or plain mannitol. The plausible substitutions are not benign: a vial containing semaglutide or another GLP-1 agonist instead of an amylin analogue would produce a broadly similar-feeling appetite effect on an entirely different mechanism, dose-response and safety profile, and the user would have no way to tell. Pramlintide, the older short-acting amylin analogue, is another realistic substitution with a completely different dosing schedule.
How it is supplied (in trials, and on the gray market). In trials cagrilintide is a subcutaneous injection given once weekly, titrated upward under supervision, and in the phase 3 program it is usually co-formulated with semaglutide, not given alone. Gray-market material is typically sold as a lyophilized powder requiring reconstitution with bacteriostatic water, transferring to the buyer the sterile handling, concentration arithmetic and dose measurement that a clinical trial supply chain exists to remove. Non-sterile reconstitution adds infection and endotoxin risk on top of the identity risk, and dosing-error risk is amplified because the therapeutic range is in single-digit milligrams.
Third-party certificates of analysis are not a solution. A COA supplied by, or arranged by, the seller is unverifiable, and testing that shows “a peptide” is not testing that shows this peptide at this purity with acceptable endotoxin.
This page does not recommend, review, rank, or link vendors, and no request will change that. Every efficacy figure here belongs to pharmaceutical-grade cagrilintide administered inside a monitored clinical trial — and most of them belong to it in combination with semaglutide. None of it transfers to a vial of unknown provenance.
Safety
Cagrilintide has an unusually large trial safety database for a gray-market compound — but almost all of it describes CagriSema, the semaglutide combination, not cagrilintide alone, and there is no supervised way to use it outside a trial.
- Gastrointestinal effects are dominant and dose-limiting. Nausea, vomiting, diarrhea and abdominal pain affected roughly 80% of the combination group in phase 3.
- Monotherapy carried more serious adverse events than semaglutide. A wide-confidence-interval signal, but it points the wrong way for standalone use.
- Contraindicated in pregnancy and breastfeeding. Not assessed at all — see the box below.
- Delayed gastric emptying can alter oral drug absorption. A general caution for anything swallowed alongside it, including oral contraceptives.
- Gray-market vials are unverified. Non-sterile reconstitution, unknown identity and purity, and self-mixed dosing errors sit outside every trial figure here.
- No clinically relevant QTc prolongation at 4.5 mg. Renal and hepatic impairment did not meaningfully alter its pharmacokinetics either.
Full Safety & Interactions Detail
Overall posture. Cagrilintide’s human safety data are trial data, and unusually substantial for a compound circulating on the gray market — phase 1 through phase 3, including dedicated QT and organ-impairment studies. They are also still short of what approval requires: the longest published exposure is about 68 weeks, and there is no post-marketing pharmacovigilance for the obvious reason that there is no market. Note too that most of the safety database describes CagriSema, so it reports the safety of cagrilintide plus a full dose of semaglutide, not of cagrilintide alone.
Adverse effects (from human trials). The dominant and dose-limiting effects are gastrointestinal — nausea, vomiting, diarrhea, constipation, abdominal pain — which is the expected consequence of slowed gastric emptying. In REDEFINE 1, GI adverse events affected 79.6% of the CagriSema group versus 39.9% on placebo, and were mostly transient and mild-to-moderate 4Reference 4RCTCoadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity (REDEFINE 1) — human (RCT, phase 3a, n=3,417; includes a cagrilintide-alone arm)View study →; in the phase 2 monotherapy trial they affected 41–63% of cagrilintide participants versus 32% on placebo, primarily nausea 2Reference 2RCTOnce-weekly cagrilintide for weight management in people with overweight and obesity: a multicentre, randomised, double-blind, placebo-controlled and active-controlled, dose-finding phase 2 trial — human (RCT, phase 2, monotherapy)View study →. Injection-site reactions are common and were more frequent with the combination than with semaglutide alone (RR 3.27) 18Reference 18Meta-analysisEfficacy and Safety of Cagrilintide and Cagrisema Versus Semaglutide as Anti-Obesity Medications: A Systematic Review and Meta-Analysis — human (systematic review / meta-analysis of 3 RCTs, n=3,545)View study →.
The monotherapy safety signal is the one people using it alone should read. The 2026 meta-analysis found overall and serious adverse events comparable between CagriSema and semaglutide, but cagrilintide monotherapy carried a higher risk of serious adverse events than semaglutide (RR 1.83, 95% CI 1.03–3.24) 18Reference 18Meta-analysisEfficacy and Safety of Cagrilintide and Cagrisema Versus Semaglutide as Anti-Obesity Medications: A Systematic Review and Meta-Analysis — human (systematic review / meta-analysis of 3 RCTs, n=3,545)View study →. That is a wide confidence interval on a small number of events across three trials, not a settled finding — but it points the wrong way for exactly the use pattern the gray market sells, and it is carried here as found rather than filed as a footnote.
Reassuring where it has been looked for. A thorough QT study found no clinically relevant QTc prolongation at 4.5 mg 12Reference 12RCTCagrilintide is not associated with clinically relevant QTc prolongation: A thorough QT study in healthy participants — human (RCT, thorough QT)View study →, and renal or hepatic impairment did not meaningfully alter its pharmacokinetics, safety or tolerability 11Reference 11Renal or Hepatic Impairment Does Not Affect Pharmacokinetics, Safety, or Tolerability of Subcutaneous Cagrilintide — human (clinical pharmacology / PK)View study →. These are real negatives, and worth as much as the positives.
Interactions. No comprehensive interaction profile is established. A dedicated study examined the combination’s effect on the exposure of oral atorvastatin and warfarin — the relevant mechanism being that delayed gastric emptying can alter the absorption of oral drugs, which is a general caution for anything taken by mouth alongside it, including oral contraceptives and narrow-therapeutic-index medicines. Cagrilintide did not alter semaglutide’s kinetics when co-administered 1Reference 1RCTSafety, tolerability, pharmacokinetics, and pharmacodynamics of concomitant administration of multiple doses of cagrilintide with semaglutide 2·4 mg for weight management: a randomised, controlled, phase 1b trial — human (RCT, phase 1b)View study →. Beyond that, the cautions here are mechanism- and class-based expectations, not assessed findings: additive gastrointestinal effects when stacked with GLP-1 agonists or other appetite suppressants, and additive glucose-lowering — with real hypoglycemia risk — when combined with insulin or insulin secretagogues. As with the GLP-1 class, retained gastric contents are a plausible peri-procedural aspiration concern for anesthesia.
Who should avoid it. In practice, everyone outside a clinical trial — there is no supervised way to use it. Within the cautions a future label would likely carry, extrapolated from the amylin and GLP-1 classes rather than established for cagrilintide: prior pancreatitis, gastroparesis or severe gastrointestinal disease, and pregnancy or lactation. Anyone using insulin should treat unsupervized use as unsafe outright.
Injection-specific risks. Injection-site reactions in trials. For self-sourced product, add non-sterile reconstitution (infection, endotoxin), unverified contents (wrong compound, wrong amount), and dosing error from self-mixed concentrations — risks absent from every trial figure quoted here.
Scope disclosure (honesty, not a claim):
- Human data? Yes, and extensive — phase 1, 2 and 3 RCTs including dedicated QT and organ-impairment studies. But the drug is unapproved, and most of the efficacy and safety data describe the CagriSema combination, not cagrilintide alone.
- Interactions assessed? Only partially. One oral-drug interaction study (atorvastatin/warfarin) and the semaglutide co-administration PK exist; there is no comprehensive profile. Everything else is class/mechanism reasoning.
- Pregnancy/lactation assessed? No. No human reproductive data located for cagrilintide.
- Long-term safety established? No. Longest published exposure ~68 weeks; cardiovascular-outcome data are not expected before 2027.
- Is standalone use characterized? Only partially, and it will likely stay that way — no monotherapy indication is being developed, so long-term single-agent data are unlikely ever to exist.
- Does any of this describe gray-market product? No. Every figure above comes from pharmaceutical-grade drug in a monitored trial.
Never imply safety from silence. Where cagrilintide has not been studied — long-term use, pregnancy, standalone use beyond a year, and the identity and purity of anything sold outside a trial — the correct statement is “not assessed,” not “safe.”
Not assessed, and contraindicated by default. There are no human pregnancy or lactation data for cagrilintide. Intentional weight loss is generally inappropriate in pregnancy, and the ~7–8 day half-life implies a washout measured in weeks. Note also that weight loss can restore fertility unexpectedly, so unintended pregnancy during use is a realistic scenario. Treat as contraindicated in pregnancy and breastfeeding.
Dosage
There is no approved or established human dose for cagrilintide, and none is recommended here. It is an investigational drug with no label, no approved indication, and no lawful self-administration pathway. The figures below are reported as trial data for context only — they are not a protocol, and reproducing them with gray-market material does not reproduce the trial.
In the phase 2 dose-finding trial, once-weekly subcutaneous cagrilintide was tested across 0.3, 0.6, 1.2, 2.4 and 4.5 mg, with weight loss increasing across that range and the 4.5 mg dose performing best 2Reference 2RCTOnce-weekly cagrilintide for weight management in people with overweight and obesity: a multicentre, randomised, double-blind, placebo-controlled and active-controlled, dose-finding phase 2 trial — human (RCT, phase 2, monotherapy)View study →. In the phase 3 program the dose is 2.4 mg once weekly, given as the fixed CagriSema combination with semaglutide 2.4 mg 4,
Two further points make trial doses close to meaningless outside a trial. First, oral products cannot deliver intact peptide (see Pharmacokinetics), so any oral “cagrilintide” is inert whatever the label says. Second, the 2.4 mg figure people quote is the CagriSema dose — it was studied alongside semaglutide, and lifting it out of that context to dose a single agent is not what any phase 3 trial tested. With no reference product, dose figures are in any case meaningless when applied to a vial of unverified concentration and unverified identity. This entry is informational only.
References
- Enebo LB, et al. (2021). Safety, tolerability, pharmacokinetics, and pharmacodynamics of concomitant administration of multiple doses of cagrilintide with semaglutide 2·4 mg for weight management: a randomised, controlled, phase 1b trial — human (RCT, phase 1b). Lancet. https://pubmed.ncbi.nlm.nih.gov/33894838/
- Lau DCW, et al. (2021). Once-weekly cagrilintide for weight management in people with overweight and obesity: a multicentre, randomised, double-blind, placebo-controlled and active-controlled, dose-finding phase 2 trial — human (RCT, phase 2, monotherapy). Lancet. https://pubmed.ncbi.nlm.nih.gov/34798060/
- Frias JP, et al. (2023). Efficacy and safety of co-administered once-weekly cagrilintide 2·4 mg with once-weekly semaglutide 2·4 mg in type 2 diabetes: a multicentre, randomised, double-blind, active-controlled, phase 2 trial — human (RCT, phase 2, with a cagrilintide-alone arm). Lancet. https://pubmed.ncbi.nlm.nih.gov/37364590/
- Garvey WT, et al. (2025). Coadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity (REDEFINE 1) — human (RCT, phase 3a, n=3,417; includes a cagrilintide-alone arm). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/40544433/
- Davies MJ, et al. (2025). Cagrilintide-Semaglutide in Adults with Overweight or Obesity and Type 2 Diabetes (REDEFINE 2) — human (RCT, phase 3). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/40544432/
- Yamauchi T, et al. (2026). Efficacy and safety of co-administered cagrilintide and semaglutide versus semaglutide alone in adults from East Asia with overweight or obesity — human (RCT, phase 3). Lancet Diabetes Endocrinol. https://pubmed.ncbi.nlm.nih.gov/42009015/
- Verma S, et al. (2026). CagriSema Reduces Blood Pressure in Adults With Overweight or Obesity: REDEFINE 1 — human (secondary/post-hoc analysis of a phase 3 RCT). Hypertension. https://pubmed.ncbi.nlm.nih.gov/41328546/
- Aroda VR, et al. (2026). Efficacy and safety of once-weekly cagrilintide-semaglutide (CagriSema) in adults with type 2 diabetes inadequately controlled by diet and exercise (REIMAGINE 1) — human (RCT, phase 3). Lancet Diabetes Endocrinol. https://pubmed.ncbi.nlm.nih.gov/42251860/
- Buse JB, et al. (2026). Cagrilintide-semaglutide (CagriSema) versus semaglutide or cagrilintide in people with type 2 diabetes (REIMAGINE 2) — human (RCT, phase 3, n=2,713; includes a cagrilintide-alone arm). Lancet Diabetes Endocrinol. https://pubmed.ncbi.nlm.nih.gov/42251859/
- Rosenstock J, et al. (2026). Cagrilintide-semaglutide (CagriSema) as an add-on to basal insulin in adults with type 2 diabetes (REIMAGINE 3) — human (RCT, phase 3). Lancet. https://pubmed.ncbi.nlm.nih.gov/42251856/
- Nielsen MJF, et al. (2026). Renal or Hepatic Impairment Does Not Affect Pharmacokinetics, Safety, or Tolerability of Subcutaneous Cagrilintide — human (clinical pharmacology / PK). Clin Pharmacokinet. https://pubmed.ncbi.nlm.nih.gov/42228334/
- Gabe MBN, et al. (2024). Cagrilintide is not associated with clinically relevant QTc prolongation: A thorough QT study in healthy participants — human (RCT, thorough QT). Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/39279639/
- Kruse T, et al. (2021). Development of Cagrilintide, a Long-Acting Amylin Analogue — medicinal chemistry / discovery. J Med Chem. https://pubmed.ncbi.nlm.nih.gov/34288673/
- Fletcher MM, et al. (2021). AM833 Is a Novel Agonist of Calcitonin Family G Protein-Coupled Receptors: Pharmacological Comparison with Six Selective and Nonselective Agonists — in vitro. J Pharmacol Exp Ther. https://pubmed.ncbi.nlm.nih.gov/33727283/
- Gu YM, et al. (2026). Structural and mechanistic insights into dual activation of cagrilintide in amylin and calcitonin receptors — in vitro (cryo-EM). Acta Pharmacol Sin. https://pubmed.ncbi.nlm.nih.gov/40847076/
- Carvas AO, et al. (2025). Cagrilintide lowers bodyweight through brain amylin receptors 1 and 3 — animal (mouse). EBioMedicine. https://pubmed.ncbi.nlm.nih.gov/40609154/
- Larsen AT, et al. (2022). Does receptor balance matter? Comparing the efficacies of the dual amylin and calcitonin receptor agonists cagrilintide and KBP-336 — animal (rat). Biomed Pharmacother. https://pubmed.ncbi.nlm.nih.gov/36242844/
- Ahmed M, et al. (2026). Efficacy and Safety of Cagrilintide and Cagrisema Versus Semaglutide as Anti-Obesity Medications: A Systematic Review and Meta-Analysis — human (systematic review / meta-analysis of 3 RCTs, n=3,545). Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/41834765/
- D’Ascanio AM, et al. (2024). Cagrilintide: A Long-Acting Amylin Analog for the Treatment of Obesity — review. Cardiol Rev. https://pubmed.ncbi.nlm.nih.gov/36883831/
- Cagrilintide lowers bodyweight through brain amylin receptors 1 and 3 (2025). eBioMedicine. https://www.thelancet.com/journals/ebiom/article/PIIS2352-3964(25)00280-4/fulltext
- Lau, D. C. W., Erichsen, L., Francisco, A. M., et al. (2021). Once-weekly cagrilintide for weight management in people with overweight and obesity: a multicentre, randomised, double-blind, placebo-controlled and active-controlled, dose-finding phase 2 trial. The Lancet. https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(21)01751-7/abstract



