
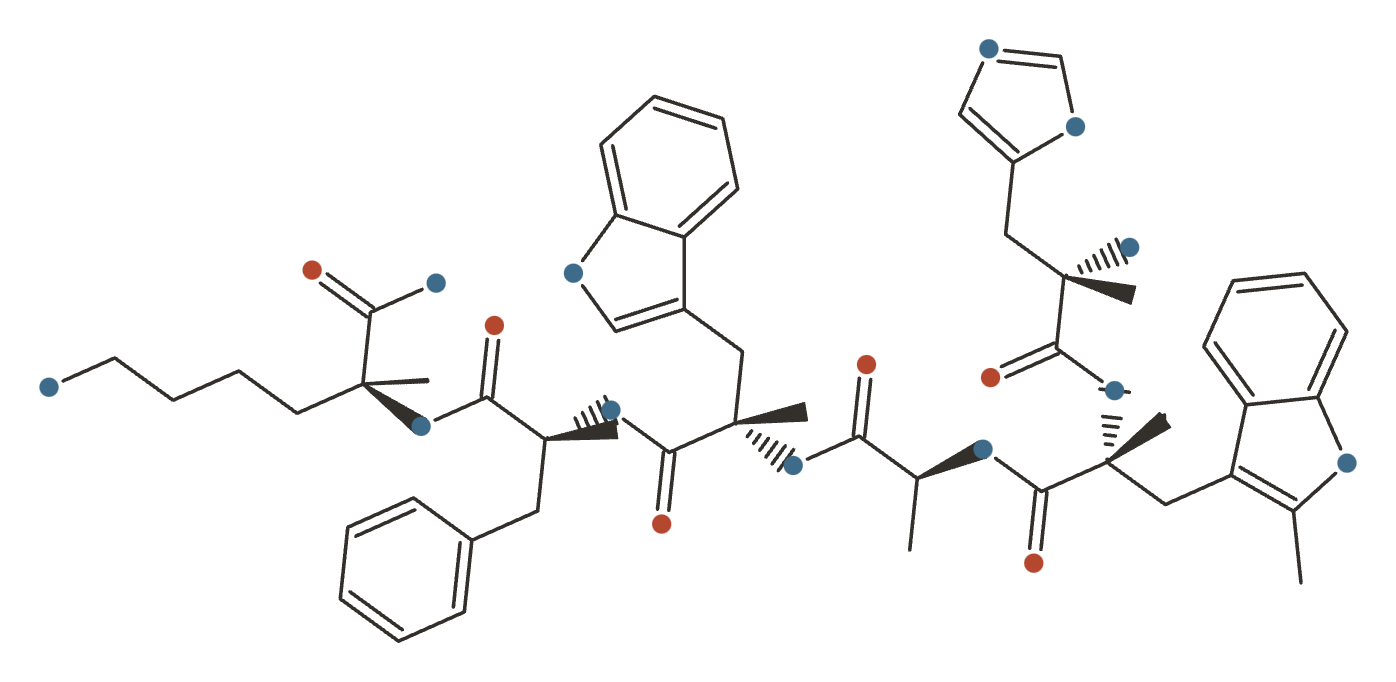
Hexarelin
A synthetic hexapeptide ghrelin-receptor agonist that releases GH potently but desensitizes within weeks; investigated as examorelin, never approved.

Hexarelin at a Glance
Hexarelin is a synthetic hexapeptide ghrelin-receptor agonist and the most potent GH releaser of the peptide secretagogues. Its defining characteristic is what happens next: the response desensitises within weeks of continuous use, as the receptor downregulates, so the initial effect is not sustainable on continuous dosing. It also binds the CD36 receptor in cardiac tissue, which is the basis of a separate line of cardiovascular research independent of growth hormone. It is an unapproved research chemical.
History & Development
Hexarelin releases growth hormone powerfully, and then stops working. The tachyphylaxis is the most thoroughly documented thing about it.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Not established in the sources consulted for this section |
| Origin | Synthetic hexapeptide; ghrelin-receptor (GHS-R1a) agonist |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Investigated as examorelin; never approved |
Discovery
Hexarelin belongs to the growth-hormone-releasing peptide series and is among the most potent GH secretagogues by acute response. It was investigated clinically under the name examorelin.
Like the other GHRPs it is not selective - the GH pulse comes with cortisol and prolactin elevation. It also has a documented cardiac line of research, acting at CD36 in addition to the ghrelin receptor.
Development & ownership
The defining finding is negative, and it comes from the only chronic human study ever run. Twelve healthy elderly subjects received 1.5 µg/kg subcutaneously twice daily for 16 weeks. The GH response desensitised markedly with continued dosing - significantly by week 4, and by roughly 45% at week 16, reversibly.
That result deserves emphasis because it is the kind that rarely exists for compounds in this category: hexarelin was tested chronically, in humans, over months, and the effect faded. This is “tested and did not hold up,” not “never tested.”
Its most active therapeutic research line - cardiac function - is entirely preclinical, resting on work such as pacing-induced cardiomyopathy in dogs.
How it reached the market
Hexarelin was never approved anywhere. It is sold as a research peptide for GH release and muscle gain, on continuous daily schedules - which is precisely the pattern its own 16-week human study shows degrading by nearly half.
What It's Used For
Hexarelin — international non-proprietary name examorelin, development code EP-23905 — is a synthetic hexapeptide (His-D-2-methyl-Trp-Ala-Trp-D-Phe-Lys-NH₂, ~887 Da) that acts as an agonist at the ghrelin / growth-hormone-secretagogue receptor GHS-R1a. It is a ghrelin mimetic, not a GHRH analogue — the same receptor family as GHRP-2, GHRP-6, ipamorelin and MK-677, and a different receptor entirely from sermorelin, CJC-1295 and tesamorelin, with which it is routinely conflated. Unusually for a compound now sold as a gray-market research peptide, hexarelin has a genuine and substantial human literature: it was a real investigational drug, and its ability to release growth hormone in healthy adults, children and GH-deficient patients is documented across many small studies from the 1990s.
The single most important thing here is that the effect does not last. In the one chronic human study ever run — 12 healthy elderly subjects given 1.5 µg/kg subcutaneously twice daily for 16 weeks — the GH response fell by roughly 45% (area under the GH curve 19.1 → 12.3 µg/L·h by week 4, → 10.5 by week 16), and the decline was already statistically significant at week four 13,
The second strand is genuinely interesting and needs its own care. Hexarelin binds CD36, a scavenger receptor expressed in myocardium, macrophages and adipocytes, in addition to GHS-R1a — and cardiac effects have been reported in settings where the GH axis cannot be the mediator: in GH-deficient and hypopituitary humans whose GH response to hexarelin is negligible 7,
That is a legitimate GH-independent mechanism. It is not, however, evidence of clinical benefit: the human cardiac work consists of small acute hemodynamic studies with surrogate endpoints, there has never been a cardiac outcome trial, and the same CD36 activation that drives the metabolic effects also produces dose-dependent coronary vasoconstriction in perfused rat hearts, which the discovering authors proposed as a mechanism of coronary vasospasm 25,
Mechanism is not evidence, and this receptor cuts both ways. Route is load-bearing throughout: measured oral bioavailability in humans is ~0.3% 37Reference 37In vitroHexarelin — evaluation of factors influencing oral bioavailability and ways to improve absorption — human / in vitro (PK)View study →, so hexarelin is an injected compound in every meaningful sense.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Read the low scores here carefully — several of them mean “tested and did not hold up,” not “never tested.” Hexarelin has real negative human data: the GH response desensitizes within weeks 13,
This is hexarelin’s strongest and most human evidence base — and also the application that contains its own refutation.
The acute effect is real and well characterized. In healthy adult men, IV hexarelin releases GH dose-dependently and more potently than GHRH, with marked synergy when the two are given together 1,
The chronic effect is where it falls apart. Twelve healthy elderly subjects received 1.5 µg/kg subcutaneously twice daily for 16 weeks. The area under the GH curve fell from 19.1 µg/L·h at baseline to 13.1 at week 1, 12.3 at week 4 and 10.5 at week 16 — a significant decline by week 4 and a highly significant one by week 16. Four weeks after stopping, it returned to 19.4, statistically indistinguishable from baseline, so the desensitization is partial and reversible 13,
That is the whole therapeutic problem in one study: the pituitary stops responding, and even before it does, the downstream axis the GH pulse is supposed to drive never moves.
Gap: the human data are abundant but are almost entirely acute pharmacodynamic and diagnostic-test data. There is no approved indication and no demonstrated clinical outcome, and the single chronic study is 12 subjects — enough to establish that tachyphylaxis occurs, not enough to characterize it across doses, schedules or populations. Whether an intermittent or lower-dose schedule could avoid desensitization has never been tested.
Small human studies consistently report that a single IV dose of hexarelin (2 µg/kg) produces a short-lived rise in left-ventricular ejection fraction, and — this is the interesting part — that it does so without going through growth hormone.
In healthy men, LVEF rose measurably within 15–30 minutes without change in blood pressure or heart rate, an effect not reproduced by recombinant GH at matched GH levels 6Reference 6Acute cardiovascular and hormonal effects of GH and hexarelin, a synthetic GH-releasing peptide, in humans — human (acute haemodynamic study)View study →.
The cleanest demonstration of GH-independence comes from hypopituitary adults: in seven GH-deficient men, the GH response to hexarelin was negligible (peak 1.9 vs 45.7 µg/L in controls) yet LVEF still rose (50 → 57%), with no change in catecholamines, blood pressure or cardiac output 8Reference 8Cardiac effects of hexarelin in hypopituitary adults — human (acute study, GH-deficient adults)View study →.
A companion study in 7 normal adults, 7 severe GH-deficient patients and 12 patients with dilated cardiomyopathy found the same: LVEF rose significantly in the normal and GH-deficient groups — but not in the dilated-cardiomyopathy group 7Reference 7Clinical trialGrowth hormone-independent cardiotropic activities of growth hormone-releasing peptides in normal subjects, in patients with growth hormone deficiency, and in patients with idiopathic or ischemic dilated cardiomyopathy — human (acute study; null in dilated cardiomyopathy)View study →.
In a controlled study of coronary-artery-disease patients undergoing bypass surgery, hexarelin — but not GHRH, recombinant GH or placebo — acutely improved cardiac index and output 9Reference 9Clinical trialEffects of acute hexarelin administration on cardiac performance in patients with coronary artery disease during by-pass surgery — human (controlled clinical trial)View study →.
A useful contrast: a physiological dose of human ghrelin itself produced no acute cardiac effect in severe GH-deficient patients, distinguishing hexarelin’s action from simple ghrelin-receptor agonism 16Reference 16Clinical trialThere are no acute cardiac effects of a single iv dose of human ghrelin in severe growth hormone deficient patients — human (clinical study; negative control for hexarelin’s effect)View study →.
Gap: every one of these is an acute hemodynamic study with a surrogate endpoint (LVEF), n = 7–24, in a research setting, from a small number of connected groups in Turin. None measured symptoms, exercise capacity, hospitalization or survival, none dosed beyond a single administration, and the effect was absent in the one diseased cardiac population tested — which is precisely the population a cardiac therapy would target. There has never been a hexarelin cardiac outcome trial.
A multi-laboratory rodent literature reports that chronic hexarelin protects the heart, and does so independently of GH. In 24-month-old rats, 21 days of subcutaneous hexarelin produced near-complete recovery of post-ischemic left-ventricular developed pressure (90% of pre-ischemic values vs 37% in controls) and cut creatine-kinase leakage — outperforming GH itself, and, critically, “divorced from any detectable alteration of somatotropic function” as measured by pituitary GH mRNA and plasma IGF-1 17Reference 17AnimalProtectant activity of hexarelin or growth hormone against postischemic ventricular dysfunction in hearts from aged rats — animal (rat)View study →.
Hexarelin improved cardiac function and remodeling after experimental myocardial infarction in rats 18Reference 18AnimalThe growth hormone secretagogue hexarelin improves cardiac function in rats after experimental myocardial infarction — animal (rat)View study →; protected cardiomyocytes from doxorubicin-induced death and from calcium-paradox injury, the latter again where GH did not 19,
One mouse study reported that even a single oral dose given acutely after MI protected chronic cardiac function 24Reference 24AnimalOne dose of oral hexarelin protects chronic cardiac function after myocardial infarction — animal (mouse)View study → — striking, though hard to reconcile with ~0.3% oral bioavailability in humans.
Mechanistically, the myocardial target was identified as CD36, a receptor distinct from pituitary GHS-R1a: a photoactivatable hexarelin derivative labeled an 84-kDa cardiac binding protein whose N-terminal sequence was identical to rat CD36, and the response was absent in CD36-null mice and in CD36-deficient hypertensive rats 25,
Two honest caveats belong with it. First, the functional readout in both CD36 papers was coronary vasoconstriction — hexarelin raised coronary perfusion pressure dose-dependently, and the authors proposed CD36 as a mediator of the coronary vasospasm seen in hypercholesterolemia and atherosclerosis 25,
Gap: entirely animal and in-vitro. No human cardioprotection outcome trial exists, and the acute human inotropy data are the only bridge — small, acute, surrogate, and null in cardiomyopathy. A mechanism this well characterized has had 25 years to produce a clinical trial and has not.
In macrophages and rodents, hexarelin binds the scavenger receptor CD36 and, through a PPARγ-dependent pathway, up-regulates the cholesterol-efflux transporters ABCA1 and ABCG1 and reduces foam-cell formation; treating ApoE-null mice on a lipid-rich diet with hexarelin significantly reduced atherosclerotic lesions, and the response was strongly impaired in PPARγ-heterozygous macrophages 26Reference 26In vitroA growth hormone-releasing peptide that binds scavenger receptor CD36 and ghrelin receptor up-regulates sterol transporters and cholesterol efflux in macrophages through a PPARγ-dependent pathway — in vitro / animal (ApoE-null mouse)View study →. Chronic hexarelin suppressed plaque development in a high-lipid-diet/vitamin-D₃ rat model 28Reference 28AnimalHexarelin suppresses high lipid diet and vitamin D3-induced atherosclerosis in the rat — animal (rat)View study →, and attenuated atherosclerosis in ApoE-knockout mice by inhibiting LOX-1/NF-κB-mediated uptake of oxidized LDL by macrophages 29Reference 29AnimalHexarelin attenuates atherosclerosis via inhibiting LOX-1-NF-κB signaling pathway-mediated macrophage ox-LDL uptake in ApoE−/− mice — animal (mouse)View study →.
Gap: animal and in-vitro only — no human lipid, imaging or cardiovascular-event data of any kind. And the receptor biology genuinely cuts both ways: the same CD36 binding that reduces macrophage lipid uptake produces coronary vasoconstriction in perfused hearts, which the same research group proposed as a vasospasm mechanism in exactly the atherosclerotic setting this application targets 25,
Working through CD36, hexarelin induced a brown-fat-like phenotype in mouse 3T3-L1 white adipocytes and in the epididymal white fat of treated mice — depletion of intracellular lipid, dense mitochondrial cristae formation, raised cytochrome-c-oxidase activity, and up-regulation of the thermogenic markers PGC-1α and UCP-1. The in-vivo effect was lost in CD36-null mice, tying it to the scavenger receptor rather than to GH 30Reference 30In vitroA growth hormone-releasing peptide promotes mitochondrial biogenesis and a fat burning-like phenotype through scavenger receptor CD36 in white adipocytes — in vitro / animal (mouse)View study →.
In non-obese insulin-resistant MKR mice, hexarelin improved glucose and insulin tolerance and lowered plasma and liver triglycerides while shifting body composition toward lean mass 31Reference 31AnimalHexarelin, a growth hormone secretagogue, improves lipid metabolic aberrations in nonobese insulin-resistant male MKR mice — animal (mouse)View study →.
A related study found hexarelin protected rodent pancreatic β-cell function against streptozotocin cytotoxicity via mitochondrial anti-apoptotic pathways 32Reference 32In vitroHexarelin protects rodent pancreatic β-cells function from cytotoxic effects of streptozotocin involving mitochondrial signalling pathways — animal (rat) / in vitroView study →.
Gap: animal and in-vitro only — there is no human metabolic, glycemic or fat-loss trial. This mechanism is the entire scientific basis for community “fat-loss” marketing, and the one human study that actually measured the outcome found total body fat unchanged after 16 weeks of twice-daily dosing 14Reference 14Clinical trialGrowth hormone status during long-term hexarelin therapy — human (clinical trial, 16 weeks; null for IGF-1, body composition and BMD)View study →. A mouse adipocyte phenotype is not a human fat-loss result, and here the human result already points the other way.
In rats, hexarelin (alongside the related GH secretagogue JMV2894) protected skeletal muscle from mitochondrial damage in a cisplatin-induced cachexia model, preserving mitochondrial biogenesis markers (PGC-1α, NRF-1, TFAM, mtDNA) and limiting autophagy and ROS markers 33Reference 33AnimalGrowth hormone secretagogues hexarelin and JMV2894 protect skeletal muscle from mitochondrial damages in a rat model of cisplatin-induced cachexia — animal (rat)View study →.
In aged dogs, 16 weeks of hexarelin produced changes in the somatotropic axis and muscle morphology 34Reference 34Sixteen weeks of hexarelin therapy in aged dogs: effects on the somatotropic axis, muscle morphology, and bone metabolism — animal (dog)View study →.
GHRP-class peptides were also reported to alleviate cardiac cachexia in heart-failure rats — but that study pooled GHRP-1, -2, -6 and hexarelin and reported results for the class, so it is not hexarelin-specific evidence 21Reference 21AnimalGH-releasing peptides improve cardiac dysfunction and cachexia and suppress stress-related hormones and cardiomyocyte apoptosis in rats with heart failure — animal (rat; pooled GHRP-1/-2/-6 and hexarelin, class-level result)View study →.
Gap: animal only, and thin even there — one rat cachexia model, one dog study, and a pooled-GHRP result. There is no human cachexia, sarcopenia or muscle-building trial. The bodybuilding use has no controlled human evidence at all, and the only chronic human study to measure lean body mass found no change 14Reference 14Clinical trialGrowth hormone status during long-term hexarelin therapy — human (clinical trial, 16 weeks; null for IGF-1, body composition and BMD)View study →.
This row is scored low because of human data, not for lack of it.
The animal signal is genuine: in gonadectomized (osteopenic) male rats, 30 days of hexarelin prevented the androgen-deficiency-driven rise in bone-resorption markers and the fall in bone mineral density at the femur and lumbar vertebrae, with evidence that it inhibits resorption through a route beyond its GH-releasing action 35Reference 35AnimalHexarelin, a growth hormone-releasing peptide, counteracts bone loss in gonadectomized male rats — animal (rat)View study →. Aged dogs treated for 16 weeks showed changes in bone metabolism alongside somatotropic and muscle effects 34Reference 34Sixteen weeks of hexarelin therapy in aged dogs: effects on the somatotropic axis, muscle morphology, and bone metabolism — animal (dog)View study →.
It did not translate. In the only long-term human study — 12 healthy elderly subjects, 1.5 µg/kg subcutaneously twice daily for 16 weeks — bone mineral density did not change (nor did total body fat or lean body mass). Of the several bone formation and resorption markers measured, only the C-terminal propeptide of type I collagen moved at all 14Reference 14Clinical trialGrowth hormone status during long-term hexarelin therapy — human (clinical trial, 16 weeks; null for IGF-1, body composition and BMD)View study →.
Gap: a well-evidenced human negative that outweighs the rodent data for translational purposes. The honest caveats are that the human study was small (n=12), ran only 16 weeks — short for a BMD endpoint — and was conducted in healthy elderly subjects rather than an osteoporotic population, and that GH-response tachyphylaxis over that same window may itself explain the null. No osteoporosis trial has ever been run.
The evidence here is a single animal study. In golden hamsters subjected to optic-nerve transection, daily intraperitoneal hexarelin for five days dose-dependently increased retinal ganglion cell survival at seven days — 51.2% in saline controls versus 62.4%, 68.5% and 74.6% at 25, 50 and 100 µg/kg, with twice-daily dosing raising survival further 36Reference 36Hexarelin promotes the survival of retinal ganglion cells after optic nerve transection — animal (hamster)View study →. The authors attribute this to the known anti-apoptotic signaling of GHS-R1a agonism.
Gap: one model, one laboratory, one species, no replication and no human neurological data of any kind. Community claims of neuroprotective or cognitive benefit have nothing else behind them, and are not scored here.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| GHS-R1a (ghrelin receptor), pituitary and hypothalamus | Agonist → acute pulsatile GH release; not selective — also raises ACTH, cortisol and prolactin 12, | Acute GH release; endocrine testing |
| GHS-R1a desensitization | GH response falls ~45% over 16 weeks (significant by week 4); partial and fully reversible after washout 13, | The limiting fact for every chronic use |
| GH → hepatic IGF-1 axis | Does not engage on a twice-daily schedule — IGF-1 and IGFBP-3 unchanged over 20 weeks in humans 14Reference 14Clinical trialGrowth hormone status during long-term hexarelin therapy — human (clinical trial, 16 weeks; null for IGF-1, body composition and BMD)View study → | Body composition; bone; anti-aging claims |
| Hypothalamic somatostatin / GHRH balance | Partial antagonism of somatostatin tone; marked synergy with GHRH 1, | Potency above GHRH; stacking rationale |
| CD36 scavenger receptor (myocardium) | Distinct 84-kDa cardiac binding site; GH-independent cardiac activity — and dose-dependent coronary vasoconstriction 25, | Cardiac effects — both the benefit claim and a liability |
| CD36 / PPARγ / LXRα (macrophages) | ↑ ABCA1/ABCG1 sterol transporters, ↑ cholesterol efflux, ↓ foam-cell formation (mouse) 26Reference 26In vitroA growth hormone-releasing peptide that binds scavenger receptor CD36 and ghrelin receptor up-regulates sterol transporters and cholesterol efflux in macrophages through a PPARγ-dependent pathway — in vitro / animal (ApoE-null mouse)View study → | Anti-atherosclerosis (preclinical) |
| CD36 / mitochondrial biogenesis (PGC-1α, UCP-1) in adipocytes | Brown-fat-like thermogenic phenotype; lost in CD36-null mice 30Reference 30In vitroA growth hormone-releasing peptide promotes mitochondrial biogenesis and a fat burning-like phenotype through scavenger receptor CD36 in white adipocytes — in vitro / animal (mouse)View study → | Metabolic / fat-loss (preclinical only) |
| Cardiomyocyte anti-apoptotic signaling | ↓ apoptosis from doxorubicin and calcium-paradox injury; ↓ fibrosis (rodent, in vitro) 19, | Cardioprotection (preclinical) |
Pharmacokinetics
Hexarelin is a small, relatively protease-resistant hexapeptide, but like essentially all peptides it is inactive by mouth: measured oral bioavailability in humans is ~0.3%, limited by degradation (deamidation at the lysine by intestinal and pancreatic proteases) and poor permeability 37Reference 37In vitroHexarelin — evaluation of factors influencing oral bioavailability and ways to improve absorption — human / in vitro (PK)View study →. That single figure reframes any oral product — an oral “hexarelin” capsule cannot deliver a meaningful amount of intact peptide regardless of what the label claims. It has been given intravenously, subcutaneously and intranasally in research; subcutaneous bioavailability in rats is ~64% 38Reference 38AnimalKinetics and disposition of hexarelin, a peptidic growth hormone secretagogue, in rats — animal (rat, PK)View study →.
Plasma half-life is short: roughly 75 minutes in rats after IV dosing 38Reference 38AnimalKinetics and disposition of hexarelin, a peptidic growth hormone secretagogue, in rats — animal (rat, PK)View study → and ~2 hours in dogs 39Reference 39Radioimmunoassay for hexarelin, a peptidic growth hormone secretagogue, and its pharmacokinetic studies — animal (dog, PK)View study →, with biliary excretion the primary elimination route and a high fraction excreted unchanged. No validated human terminal half-life has been published in the indexed literature — the human studies measured hormone responses, not peptide disposition, which is a real gap for a compound with this much human exposure. Doping-control work has mapped the exopeptidase- and amidase-generated urinary metabolites used to detect it 40Reference 40Metabolism of growth hormone releasing peptides — analytical / doping controlView study →, and a 2025 analysis identified hexarelin/examorelin as a metabolite of the related secretagogue alexamorelin — a distinct compound that should not be conflated with hexarelin despite the shared detection signature 42Reference 42Identification of alexamorelin consumption biomarkers using human hepatocyte incubations and high-resolution mass spectrometry — analytical / doping control (identifies hexarelin as an alexamorelin metabolite)View study →.
There is no established human dosing regimen for any therapeutic use. Research studies used roughly 0.25–2 µg/kg IV for GH-stimulation testing and 1.5 µg/kg SC twice daily in the 16-week chronic study 14Reference 14Clinical trialGrowth hormone status during long-term hexarelin therapy — human (clinical trial, 16 weeks; null for IGF-1, body composition and BMD)View study →. Reconstitution and stability parameters for gray-market lyophilized product are vendor-level claims, not independently documented.
Clinical & regulatory status
Hexarelin is an unapproved, abandoned investigational drug. Under the name examorelin (code EP-23905) it was studied extensively in humans through the 1990s and early 2000s as a growth-hormone secretagogue and a diagnostic agent, but it was never approved by the FDA, EMA, TGA or any other regulator, for any indication, in any country, and development did not continue.
The discontinuation is best treated as an event with a documented consequence but an undocumented rationale. What is verifiable is that the human program stopped: the clinical literature effectively ends in the early 2000s, no approval was ever granted, and no sponsor has taken it forward since. No primary source states why the program was halted. The explanation offered throughout the secondary literature — that GH-response tachyphylaxis 13,
It is not a dietary supplement and cannot lawfully be sold for human consumption; it circulates only as a gray-market “research chemical.” It is prohibited in sport at all times by WADA under class S2 (growth hormone, its fragments and releasing factors), which is why a disproportionate share of the recent hexarelin literature is anti-doping metabolite work 40,
Because the human program predates modern trial registration, searches of ClinicalTrials.gov for hexarelin, examorelin, EP-23905 and alexamorelin return zero registered studies — verified against the registry API in this pass. The human evidence lives entirely in the pre-2005 endocrinology literature, not in any registry, and the count below reflects that.
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 0registered (pre-registry human pharmacology only) | 0 | 0registered — program abandoned unregistered | ~150+animal / in-vitro (PubMed) |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. Hexarelin has never been approved for human use in any jurisdiction. It is not a medicine, not a recognized dietary supplement in the US, UK, EU or Australia, and carries no marketing authorization anywhere. Its development history is not a credential: a sponsor took it into human investigation as examorelin, generated a substantial acute pharmacology dataset, and stopped. It is not a scheduled or controlled substance in the US, but “not scheduled” is not “approved” — marketing it for human consumption is unlawful in most Western jurisdictions, and it is sold instead as a research chemical labeled “not for human consumption.” In sport it is banned at all times as a growth-hormone secretagogue (WADA Prohibited List, class S2), and it is a routine target in doping-control assays 40,
How it’s supplied & administered. Gray-market hexarelin ships as a lyophilized (freeze-dried) powder in a multi-dose vial, which the buyer reconstitutes with bacteriostatic or sterile water. Because oral bioavailability is ~0.3% 37Reference 37In vitroHexarelin — evaluation of factors influencing oral bioavailability and ways to improve absorption — human / in vitro (PK)View study →, it must be given parenterally — research used intravenous and subcutaneous dosing, and community use is subcutaneous injection. Intranasal delivery was explored in research and is inefficient. Lyophilized powder is generally stored refrigerated or frozen and protected from light; reconstituted solution is unstable and short-lived. The short half-life means dosing produces a transient pulse rather than sustained elevation — and repeated pulsing is exactly the pattern shown to induce desensitization 13,
Sourcing reality (this is a safety issue, not a footnote). Every gray-market vial comes from an unregulated supplier with no manufacturing oversight. There is no assurance of identity, correct sequence, peptide content, freedom from synthesis-related impurities, or absence of bacterial endotoxin — the last of which matters acutely for an injected product, where contamination can cause fever, injection-site reactions or systemic illness. Mislabeling, under- and over-filling, and outright substitution are documented problems across the research-peptide market. A specific hazard for this compound: hexarelin, GHRP-2 and GHRP-6 are close analogues that are routinely conflated in vendor copy and in the secondary literature, so both the product in the vial and the studies cited to justify it may not be the compound named on the label. Third-party certificates of analysis — independent identity and purity testing by mass spectrometry or HPLC, plus endotoxin testing — are the minimum needed to interpret the risk, and even those are only as trustworthy as the party commissioning them. This page does not recommend or link vendors; the honest position is that gray-market peptide identity and purity cannot be assumed.
Safety
Hexarelin has genuine cardiac receptor activity and no cardiac safety data — the combination that makes it the least self-administrable of the GH secretagogues. Chronic human exposure has been tested exactly once, for 16 weeks in twelve people.
- Real cardiovascular activity, unstudied in chronic use. Dose-dependent coronary vasoconstriction in perfused animal hearts, which the investigators linked to coronary vasospasm.
- Not GH-selective. ACTH, cortisol and prolactin rise acutely alongside GH, and neither elevation has been characterized long term.
- Several groups should avoid it. Cardiovascular disease, active or prior malignancy, diabetes or impaired glucose tolerance, children and adolescents, and anyone pregnant or breastfeeding.
- Nocturnal dosing reduced deep sleep. Directly counterproductive for anyone dosing on the “GH is released in slow-wave sleep” rationale.
- Tachyphylaxis is the practical ceiling. The GH response fades by about week 4 while the cortisol and prolactin rise does not.
- Unregulated injected product. Injection-site reactions, non-sterile technique, endotoxin exposure and self-reconstitution dosing error.
Full Safety & Interactions Detail
Overall posture. Hexarelin’s human safety data come almost entirely from short-term GH-secretion and acute-cardiac studies, in which it was administered under research supervision without a reported serious-adverse-event signal. Chronic human exposure has been tested exactly once, for 16 weeks in 12 healthy elderly subjects 14Reference 14Clinical trialGrowth hormone status during long-term hexarelin therapy — human (clinical trial, 16 weeks; null for IGF-1, body composition and BMD)View study →. That is the entire chronic human safety database for this compound, and it is far too small to characterize risk. Note the asymmetry it creates: the same study that provides the only chronic safety reassurance also found the compound did essentially nothing to the GH–IGF-1 axis.
Hormonal spillover. Hexarelin is not GH-selective — this is its clearest pharmacological difference from ipamorelin. It acutely raises ACTH, cortisol and prolactin alongside GH, both on daytime subcutaneous schedules 12Reference 12RCTImpact of two or three daily subcutaneous injections of hexarelin, a synthetic growth hormone (GH) secretagogue, on 24-h GH, prolactin, adrenocorticotropin and cortisol secretion in humans — human (randomised clinical trial)View study → and when dosed during sleep 15Reference 15Clinical trialHexarelin decreases slow-wave sleep and stimulates the secretion of GH, ACTH, cortisol and prolactin during sleep in healthy volunteers — human (controlled clinical trial)View study →. Chronically elevated cortisol and prolactin are undesirable in their own right, and neither has been characterized over long-term use.
Sleep. Repeated nocturnal dosing reduced slow-wave (deep) sleep in healthy volunteers while raising GH, ACTH, cortisol and prolactin 15Reference 15Clinical trialHexarelin decreases slow-wave sleep and stimulates the secretion of GH, ACTH, cortisol and prolactin during sleep in healthy volunteers — human (controlled clinical trial)View study → — a directly counterproductive effect for anyone using it on the “GH is released during deep sleep” rationale.
Cardiovascular. Hexarelin has genuine, receptor-mediated cardiovascular activity: an acute rise in ejection fraction in humans 6,
Glucose and insulin. As a class effect of GH secretagogues, GH elevation can reduce insulin sensitivity and raise blood glucose — flagged in the GHS safety literature 41Reference 41ReviewThe safety and efficacy of growth hormone secretagogues — reviewView study →. This is class/mechanism reasoning, not a hexarelin trial finding, and it is worth noting that on the one chronic schedule tested, IGF-1 never rose at all 14Reference 14Clinical trialGrowth hormone status during long-term hexarelin therapy — human (clinical trial, 16 weeks; null for IGF-1, body composition and BMD)View study →.
Tachyphylaxis as a practical limiter. The combination of a GH response that fades by week 4 13,
Route-specific risks. Injection-site reactions; infection from non-sterile technique; endotoxin exposure from unregulated product; and dosing error from self-reconstituted concentrations. These are structural to how the compound is obtained and used.
Interactions. No formal human drug-interaction studies exist. Mechanistic cautions only: additive GH stimulation when stacked with other secretagogues or with GHRH analogues (the synergy with GHRH is documented 1,
Who should avoid it. Anyone pregnant, breastfeeding or trying to conceive; children and adolescents; anyone with active or prior malignancy, given GH/IGF-1 proliferative signaling; anyone with diabetes or impaired glucose tolerance; anyone with cardiovascular disease, given the coronary vasoconstriction signal; competitive athletes (banned at all times); and anyone unwilling to accept an unapproved product of unverified identity and purity.
Scope disclosure (honesty, not a claim):
- Human data? Yes for acute pharmacology — GH release, hormonal profile, acute cardiac contractility, short-term tolerability. None for therapeutic efficacy in any indication, and chronic human exposure amounts to one 16-week study in 12 subjects 14Reference 14Clinical trialGrowth hormone status during long-term hexarelin therapy — human (clinical trial, 16 weeks; null for IGF-1, body composition and BMD)View study →.
- Interactions assessed? No. Only class and mechanism cautions (GH secretagogue stacking, somatostatin analogues, glucose-lowering agents), which are inferred, not tested.
- Pregnancy/lactation assessed? No — no human or animal reproductive data located.
- Long-term safety established? No. Human dosing beyond 16 weeks has never been studied, and no cancer-incidence or mortality data exist. Absence of reports is not evidence of safety.
Never imply safety from silence. Where hexarelin has not been studied — chronic use, dose escalation, cardiac safety, interactions, pregnancy, gray-market product purity — the correct statement is “not assessed,” not “safe.” And a clean short-term tolerability record is not evidence that the compound works: the one study that dosed it for 16 weeks found the GH response fading and nothing downstream changing.
Not assessed / not established. There are no human pregnancy or lactation data for hexarelin, no regulatory label, and no reproductive-toxicity data located in the accessible literature. Treat as contraindicated by default in pregnancy and breastfeeding.
Dosage
There is no established human therapeutic dose for hexarelin, and none is recommended here. It has never been approved for any indication in any country, so there is no label, no titration schedule and no maintenance regimen to report. Every figure below is data reported for context, not a personal recommendation.
Research dosing fell into two patterns. For GH-stimulation testing, roughly 0.25–2 µg/kg intravenously as a single dose, which reliably produces a GH pulse 1,
Gray-market practice — microgram-per-kilogram subcutaneous injections, often timed around sleep or training and frequently stacked with a GHRH analogue — derives from vendor copy and community convention, not from any human dose-finding study, and no protocol addresses the desensitization problem. Oral products cannot deliver intact peptide (~0.3% bioavailability, see Pharmacokinetics), so any oral dose is pharmacologically inert regardless of the number on the label. This entry is informational only.
References
- Massoud AF, Hindmarsh PC, Brook CG. (1996). Hexarelin-induced growth hormone, cortisol, and prolactin release: a dose-response study — human (clinical trial). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/8954038/
- Massoud AF, Hindmarsh PC, Matthews DR, Brook CG. (1996). The effect of repeated administration of hexarelin, a growth hormone releasing peptide, and growth hormone releasing hormone on growth hormone responsivity — human (clinical trial). Clinical Endocrinology (Oxford). https://pubmed.ncbi.nlm.nih.gov/8762732/
- Loche S, Cambiaso P, Merola B, et al. (1995). The effect of hexarelin on growth hormone (GH) secretion in patients with GH deficiency — human (clinical trial). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/7673411/
- Tolis G, Karydis I, Markousis V, et al. (1997). Growth hormone release by the novel GH releasing peptide hexarelin in patients with homozygous beta-thalassemia — human (clinical study). Journal of Pediatric Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/9364340/
- Loche S, Colao A, Cappa M, et al. (1997). The growth hormone response to hexarelin in children: reproducibility and effect of sex steroids — human (children). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/9062497/
- Bisi G, Podio V, Valetto MR, et al. (1999). Acute cardiovascular and hormonal effects of GH and hexarelin, a synthetic GH-releasing peptide, in humans — human (acute haemodynamic study). Journal of Endocrinological Investigation. https://pubmed.ncbi.nlm.nih.gov/10342360/
- Broglio F, Benso A, Valetto MR, et al. (2001). Growth hormone-independent cardiotropic activities of growth hormone-releasing peptides in normal subjects, in patients with growth hormone deficiency, and in patients with idiopathic or ischemic dilated cardiomyopathy — human (acute study; null in dilated cardiomyopathy). Endocrine. https://pubmed.ncbi.nlm.nih.gov/11322491/
- Bisi G, Podio V, Valetto MR, et al. (1999). Cardiac effects of hexarelin in hypopituitary adults — human (acute study, GH-deficient adults). European Journal of Pharmacology. https://pubmed.ncbi.nlm.nih.gov/10528131/
- Broglio F, Guarracino F, Benso A, et al. (2002). Effects of acute hexarelin administration on cardiac performance in patients with coronary artery disease during by-pass surgery — human (controlled clinical trial). European Journal of Pharmacology. https://pubmed.ncbi.nlm.nih.gov/12144941/
- Arvat E, Camanni F, Ghigo E. (1997). Age-related growth hormone-releasing activity of growth hormone secretagogues in humans — review. Acta Paediatrica Supplement. https://pubmed.ncbi.nlm.nih.gov/9401552/
- Rahim A, O’Neill P, Shalet SM. (1998). The effect of body composition on hexarelin-induced growth hormone release in normal elderly subjects — human. Clinical Endocrinology (Oxford). https://pubmed.ncbi.nlm.nih.gov/10197083/
- Maccario M, Veldhuis JD, Broglio F, et al. (2002). Impact of two or three daily subcutaneous injections of hexarelin, a synthetic growth hormone (GH) secretagogue, on 24-h GH, prolactin, adrenocorticotropin and cortisol secretion in humans — human (randomised clinical trial). European Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/11888836/
- Rahim A, Shalet SM. (1998). Does desensitization to hexarelin occur? — human (clinical trial; same 12-subject 16-week dataset as reference 14). Growth Hormone & IGF Research. https://pubmed.ncbi.nlm.nih.gov/10990150/
- Rahim A, O’Neill PA, Shalet SM. (1998). Growth hormone status during long-term hexarelin therapy — human (clinical trial, 16 weeks; null for IGF-1, body composition and BMD). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/9589671/
- Frieboes RM, Antonijevic IA, Held K, et al. (2004). Hexarelin decreases slow-wave sleep and stimulates the secretion of GH, ACTH, cortisol and prolactin during sleep in healthy volunteers — human (controlled clinical trial). Psychoneuroendocrinology. https://pubmed.ncbi.nlm.nih.gov/15177700/
- Janssen JA, Poldermans D, Hofland LJ, et al. (2004). There are no acute cardiac effects of a single iv dose of human ghrelin in severe growth hormone deficient patients — human (clinical study; negative control for hexarelin’s effect). Journal of Endocrinological Investigation. https://pubmed.ncbi.nlm.nih.gov/15505990/
- Rossoni G, De Gennaro Colonna V, Bernareggi M, et al. (1998). Protectant activity of hexarelin or growth hormone against postischemic ventricular dysfunction in hearts from aged rats — animal (rat). Journal of Cardiovascular Pharmacology. https://pubmed.ncbi.nlm.nih.gov/9700988/
- Tivesten A, Bollano E, Caidahl K, et al. (2000). The growth hormone secretagogue hexarelin improves cardiac function in rats after experimental myocardial infarction — animal (rat). Endocrinology. https://pubmed.ncbi.nlm.nih.gov/10614623/
- Filigheddu N, Fubini A, Baldanzi G, et al. (2001). Hexarelin protects H9c2 cardiomyocytes from doxorubicin-induced cell death — in vitro. Endocrine. https://pubmed.ncbi.nlm.nih.gov/11322493/
- Torsello A, Rossoni G, Locatelli V, et al. (2001). Hexarelin, but not growth hormone, protects heart from damage induced in vitro by calcium deprivation replenishment — animal (rat, ex vivo). Endocrine. https://pubmed.ncbi.nlm.nih.gov/11322492/
- Xu XB, Pang JJ, Cao JM, et al. (2005). GH-releasing peptides improve cardiac dysfunction and cachexia and suppress stress-related hormones and cardiomyocyte apoptosis in rats with heart failure — animal (rat; pooled GHRP-1/-2/-6 and hexarelin, class-level result). American Journal of Physiology — Heart and Circulatory Physiology. https://pubmed.ncbi.nlm.nih.gov/15951341/
- Xu X, Ding F, Pang J, et al. (2012). Chronic administration of hexarelin attenuates cardiac fibrosis in the spontaneously hypertensive rat — animal (rat). American Journal of Physiology — Heart and Circulatory Physiology. https://pubmed.ncbi.nlm.nih.gov/22842067/
- McDonald H, Peart J, Kurniawan ND, et al. (2020). Hexarelin targets neuroinflammatory pathways to preserve cardiac morphology and function in a mouse model of myocardial ischemia-reperfusion — animal (mouse). Biomedicine & Pharmacotherapy. https://pubmed.ncbi.nlm.nih.gov/32403043/
- Mao Y, Tokudome T, Kishimoto I, et al. (2014). One dose of oral hexarelin protects chronic cardiac function after myocardial infarction — animal (mouse). Peptides. https://pubmed.ncbi.nlm.nih.gov/24747279/
- Bodart V, Bouchard JF, McNicoll N, et al. (1999). Identification and characterization of a new growth hormone-releasing peptide receptor in the heart — animal (rat; receptor identification and coronary vasoconstriction). Circulation Research. https://pubmed.ncbi.nlm.nih.gov/10532947/
- Avallone R, Demers A, Rodrigue-Way A, et al. (2006). A growth hormone-releasing peptide that binds scavenger receptor CD36 and ghrelin receptor up-regulates sterol transporters and cholesterol efflux in macrophages through a PPARγ-dependent pathway — in vitro / animal (ApoE-null mouse). Molecular Endocrinology. https://pubmed.ncbi.nlm.nih.gov/16959872/
- Bodart V, Febbraio M, Demers A, et al. (2002). CD36 mediates the cardiovascular action of growth hormone-releasing peptides in the heart — animal (rat/mouse; coronary vasoconstriction, proposed vasospasm mechanism). Circulation Research. https://pubmed.ncbi.nlm.nih.gov/11988484/
- Pang J, Xu Q, Xu X, et al. (2010). Hexarelin suppresses high lipid diet and vitamin D3-induced atherosclerosis in the rat — animal (rat). Peptides. https://pubmed.ncbi.nlm.nih.gov/19931584/
- Cheng XL, Ding F, Wang DP, et al. (2019). Hexarelin attenuates atherosclerosis via inhibiting LOX-1-NF-κB signaling pathway-mediated macrophage ox-LDL uptake in ApoE−/− mice — animal (mouse). Peptides. https://pubmed.ncbi.nlm.nih.gov/31386895/
- Rodrigue-Way A, Demers A, Ong H, Tremblay A. (2007). A growth hormone-releasing peptide promotes mitochondrial biogenesis and a fat burning-like phenotype through scavenger receptor CD36 in white adipocytes — in vitro / animal (mouse). Endocrinology. https://pubmed.ncbi.nlm.nih.gov/17138655/
- Mosa R, Huang L, Wu Y, et al. (2017). Hexarelin, a growth hormone secretagogue, improves lipid metabolic aberrations in nonobese insulin-resistant male MKR mice — animal (mouse). Endocrinology. https://pubmed.ncbi.nlm.nih.gov/28977588/
- Zhao Y, Zhang X, Chen J, Lin C, et al. (2016). Hexarelin protects rodent pancreatic β-cells function from cytotoxic effects of streptozotocin involving mitochondrial signalling pathways — animal (rat) / in vitro. PLoS One. https://pubmed.ncbi.nlm.nih.gov/26918825/
- Sirago G, Conte E, Fracasso F, et al. (2017). Growth hormone secretagogues hexarelin and JMV2894 protect skeletal muscle from mitochondrial damages in a rat model of cisplatin-induced cachexia — animal (rat). Scientific Reports. https://pubmed.ncbi.nlm.nih.gov/29026190/
- Cella SG, Cerri CG, Daniel S, et al. (1996). Sixteen weeks of hexarelin therapy in aged dogs: effects on the somatotropic axis, muscle morphology, and bone metabolism — animal (dog). Journals of Gerontology Series A. https://pubmed.ncbi.nlm.nih.gov/8914494/
- Sibilia V, Cocchi D, Pagani F, et al. (1999). Hexarelin, a growth hormone-releasing peptide, counteracts bone loss in gonadectomized male rats — animal (rat). Growth Hormone & IGF Research. https://pubmed.ncbi.nlm.nih.gov/10512687/
- Chow KBS. (2026). Hexarelin promotes the survival of retinal ganglion cells after optic nerve transection — animal (hamster). Indian Journal of Pharmacology. https://pubmed.ncbi.nlm.nih.gov/41766237/
- Westberg C, Benkestock K, Fatouros A, et al. (2001). Hexarelin — evaluation of factors influencing oral bioavailability and ways to improve absorption — human / in vitro (PK). Journal of Pharmacy and Pharmacology. https://pubmed.ncbi.nlm.nih.gov/11578108/
- Roumi M, Marleau S, Souich P, et al. (2000). Kinetics and disposition of hexarelin, a peptidic growth hormone secretagogue, in rats — animal (rat, PK). Drug Metabolism and Disposition. https://pubmed.ncbi.nlm.nih.gov/10611139/
- Roumi M, Kwong E, Deghenghi R, et al. (1995). Radioimmunoassay for hexarelin, a peptidic growth hormone secretagogue, and its pharmacokinetic studies — animal (dog, PK). Peptides. https://pubmed.ncbi.nlm.nih.gov/8545255/
- Thomas A, Delahaut P, Krug O, et al. (2012). Metabolism of growth hormone releasing peptides — analytical / doping control. Analytical Chemistry. https://pubmed.ncbi.nlm.nih.gov/23101768/
- Sigalos JT, Pastuszak AW. (2018). The safety and efficacy of growth hormone secretagogues — review. Sexual Medicine Reviews. https://pubmed.ncbi.nlm.nih.gov/28400207/
- Pobee E, Daziani G, Gameli PS, et al. (2025). Identification of alexamorelin consumption biomarkers using human hepatocyte incubations and high-resolution mass spectrometry — analytical / doping control (identifies hexarelin as an alexamorelin metabolite). Journal of Analytical Toxicology. https://pubmed.ncbi.nlm.nih.gov/40465419/
- Mao Y, Tokudome T, Kishimoto I. (2014). The cardiovascular action of hexarelin — review. Journal of Geriatric Cardiology. https://pubmed.ncbi.nlm.nih.gov/25278975/



