
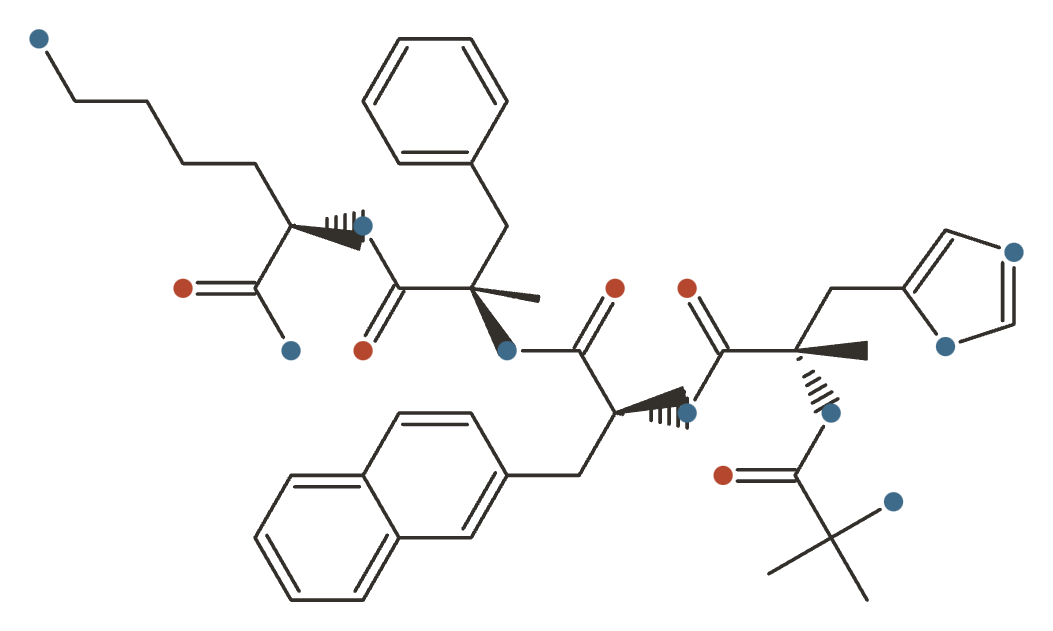
Ipamorelin
A selective pentapeptide GH secretagogue that reached Phase 2 for gastrointestinal motility, missed its endpoint, and was never approved.

Ipamorelin at a Glance
Ipamorelin is a pentapeptide ghrelin-receptor agonist, and the selective member of the growth-hormone secretagogue family: it triggers a GH pulse with little of the cortisol, prolactin or appetite stimulation that the older peptides in this class produce. That clean profile is why it became the most popular GH secretagogue on the research-peptide market. Its actual clinical development went a different way — it reached phase 2 for postoperative gastrointestinal motility and missed its endpoint, and was not pursued for growth hormone at all. It is an unapproved research chemical.
History & Development
Ipamorelin is the most popular growth-hormone secretagogue on the research-peptide market, and its actual clinical development had nothing to do with growth hormone. It was tested as a gut motility drug, and it missed.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Clinical development conducted by Helsinn |
| Origin | Synthetic pentapeptide; selective agonist at the ghrelin receptor (GHS-R1a) |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Discontinued - reached Phase 2 for gastrointestinal motility, missed its endpoint; never approved |
Discovery
Ipamorelin is a pentapeptide - five amino acids - that activates the ghrelin receptor to trigger growth-hormone release from the pituitary. What distinguished it from the earlier secretagogues is selectivity: it releases growth hormone without the rises in cortisol, prolactin and ACTH that the GHRP series produce. That clean profile is the reason it displaced them in popularity.
Development & ownership
The clinical programme was run by Helsinn, and the indication was not what its retail market assumes. Ghrelin-receptor agonism stimulates gastric motility, so ipamorelin was developed for postoperative ileus - the temporary gut paralysis that follows abdominal surgery.
Phase 2 trials gave 0.03 mg/kg intravenously twice daily for up to seven days in a hospital setting, in a programme including a 114-patient trial. It missed its endpoint, and development ended there.
Two things follow from that record and both bear on how the compound is used now. The trials established short-term tolerability under monitoring - not the safety of chronic use. And the studied route was intravenous over days, whereas the community route is subcutaneous self-injection over months, which no trial has evaluated.
How it reached the market
Ipamorelin was never approved for any indication, anywhere. It reached consumers the way most of this category does: development stopped, the molecule left pharmaceutical channels, and it is now sold as a research peptide for growth-hormone release, muscle gain and anti-ageing - none of which it was ever trialled for. It is prohibited in sport at all times.
What It's Used For
Ipamorelin is a synthetic pentapeptide — Aib-His-D-2-Nal-D-Phe-Lys-NH₂ (C₃₈H₄₉N₉O₅, ~712 Da) — that acts as an agonist at the ghrelin / growth-hormone-secretagogue receptor GHS-R1a, triggering a pulse of growth hormone (GH) from the pituitary. Its defining property, established in the original 1998 characterization, is selectivity: it releases GH with potency comparable to the earlier GHRPs but without meaningfully raising ACTH, cortisol or prolactin — the off-target hormone rise that dogged GHRP-2 and GHRP-6 1Reference 1In vitroIpamorelin, the first selective growth hormone secretagogue — in vitro / animal (rat)View study →.
Mechanistically it is a ghrelin mimetic, not a GHRH analogue: sermorelin, CJC-1295 and tesamorelin work through a different receptor, and the two classes are frequently conflated. Unusually for a compound now sold as a gray-market research peptide, ipamorelin was taken a long way into formal drug development — originating at Novo Nordisk as NNC 26-0161 and later advanced by Helsinn Therapeutics — and it carries a published human PK/PD study 2Reference 2Clinical trialPharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers — human (PK/PD, healthy men)View study → plus two completed Phase 2 randomized controlled trials in gastrointestinal indications. That is far more human data than most peptides on this hub, and the honest headline is that it did not work: the published Phase 2 trial missed its primary endpoint and the program was discontinued 3Reference 3RCTProspective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients — human (Phase 2 RCT, NCT00672074)View study →.
Route is load-bearing — oral bioavailability is negligible, the trials infused it intravenously, and community use is subcutaneous injection.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. For this compound the score is deliberately not driven by raw publication count — most ipamorelin papers trace to the originating program or are anti-doping analytical-method papers, so more hits ≠ more independent evidence. Note also that a completed human trial can lower a score: the GI-motility row is ranked on a well-run RCT that found no effect. Each application links down to its write-up.
This is the one application with direct human data. In a dose-escalation PK/PD study, eight healthy male volunteers per dose level received 15-minute intravenous infusions across five rates (4.21–140.45 nmol/kg); ipamorelin produced a single episode of GH release peaking at ~0.67 h and declining exponentially to negligible levels at every dose, modeled with an indirect-response population fit 2Reference 2Clinical trialPharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers — human (PK/PD, healthy men)View study →.
The underlying pharmacology is well replicated in rats and rat tissue: in primary rat pituitary cells ipamorelin released GH with potency and efficacy similar to GHRP-6, acting through a GHRP-like (ghrelin) receptor rather than the GHRH receptor, and in vivo it did so without raising ACTH or cortisol above GHRH-stimulated levels 1Reference 1In vitroIpamorelin, the first selective growth hormone secretagogue — in vitro / animal (rat)View study →.
That selectivity — GH without the stress-hormone rise — is the compound’s genuine contribution and the reason it was developed. Note the ceiling carefully: the human evidence is a hormone concentration, not a clinical outcome. No trial has shown that this GH pulse produces any benefit in muscle, fat, recovery, bone or aging.
Gap: human data prove GH is released; no human clinical-outcome trial links that pulse to any health, body-composition or performance endpoint.
Ipamorelin has a coherent skeletal signal — in rodents only. In adult female rats, 12 weeks of continuous subcutaneous ipamorelin (0.5 mg/kg/day by osmotic minipump) increased bone mineral content measured by DXA and pQCT, comparably to GHRP-6 5Reference 5AnimalThe GH secretagogues ipamorelin and GH-releasing peptide-6 increase bone mineral content in adult female rats — animal (rat)View study →.
In a separate rat study, subcutaneous ipamorelin dose-dependently increased the longitudinal bone-growth rate of the proximal tibia (roughly 42 → 52 µm/day) — notably without a rise in total IGF-1, which complicates the simple “GH → IGF-1 → growth” story 6Reference 6AnimalIpamorelin, a new growth-hormone-releasing peptide, induces longitudinal bone growth in rats — animal (rat)View study →.
In an adult-rat glucocorticoid model, co-administered ipamorelin counteracted the steroid-induced fall in periosteal bone-formation rate and muscle strength 7Reference 7AnimalThe growth hormone secretagogue ipamorelin counteracts glucocorticoid-induced decrease in bone formation of adult rats — animal (rat)View study →, consistent with a broader anti-catabolic effect on nitrogen balance seen in steroid-treated rats 4Reference 4AnimalGrowth hormone and growth hormone secretagogue effects on nitrogen balance and urea synthesis in steroid treated rats — animal (rat)View study →.
These results are internally consistent and mechanistically sensible, but they cluster in a small set of studies from essentially one research program, and none has been repeated in humans.
Gap: entirely rat data, largely one program. No human bone, osteoporosis or sarcopenia trial exists — a single one would move this row substantially.
This is the application ipamorelin was actually developed and tested for in humans, and it is the reason the page ends where it does. The rationale was solid preclinical prokinetic pharmacology: in a rat model of post-operative ileus, ipamorelin accelerated gastric emptying and gastrointestinal transit 11Reference 11AnimalEfficacy of ipamorelin, a novel ghrelin mimetic, in a rodent model of postoperative ileus — animal (rat)View study →, a result extended in a second rodent gastric-dysmotility model 12Reference 12AnimalEfficacy of ipamorelin, a ghrelin mimetic, on gastric dysmotility in a rodent model of postoperative ileus — animal (rat)View study →; and in isolated ferret ileum ipamorelin inhibited electrical-field-stimulation-evoked contractions (54.4% inhibition, IC₅₀ 11.7 µM) while reducing cisplatin-induced weight loss in vivo 13Reference 13The growth hormone secretagogue receptor 1a agonists, anamorelin and ipamorelin, inhibit cisplatin-induced weight loss in ferrets — animal (ferret) / ex vivoView study →.
Helsinn Therapeutics ran two Phase 2 RCTs. The published one — NCT00672074, a multicenter, double-blind, placebo-controlled trial in adults undergoing open or laparoscopic bowel resection, 117 enrolled and 114 in the safety/modified-intent-to-treat population, IV 0.03 mg/kg twice daily from post-operative day 1 to day 7 or discharge — found ipamorelin well tolerated but not effective: median time to first tolerated solid meal was 25.3 h on ipamorelin vs 32.6 h on placebo, p = 0.15, with no significant differences on secondary endpoints either 3Reference 3RCTProspective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients — human (Phase 2 RCT, NCT00672074)View study →.
A larger second Phase 2, NCT01280344 (recovery of gastrointestinal function, n=320, Helsinn), completed in May 2014; per the ClinicalTrials.gov record it has no results posted, and no outcome publication was located in this pass. No further development followed.
Gap: the human answer here is negative, not absent. The unresolved piece is NCT01280344 — a 320-patient completed trial whose results have never been posted or published, which is itself a reporting gap worth naming.
This is what ipamorelin is actually sold for, and it is the least supported thing on the page. There is no human trial of ipamorelin for muscle gain, fat loss, recovery, injury healing or aging. The entire rationale is inferential: it raises GH (true, and human-confirmed 1,
A 2020 review of GH secretagogues in hypogonadal men lists ipamorelin among candidate agents while explicitly noting that clinical efficacy data are lacking 9Reference 9ReviewBeyond the androgen receptor: the role of growth hormone secretagogues in the modern management of body composition in hypogonadal males — reviewView study →, and a 2026 review of performance-enhancing GH-axis peptides places it squarely in the self-administration/gray-market category, with the clinical-evidence gap as its organizing theme 10Reference 10ReviewThe emerging landscape of performance-enhancing peptides modulating the GH-IGF1 axis: bridging the gap between clinical evidence and patient self-administration — reviewView study →.
Community and vendor claims for this application are not evidence and are not scored here.
Gap: zero human efficacy data of any kind. The claim rests on GH-pulse inference, and the available rodent data point toward increased adiposity rather than fat loss.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| GHS-R1a (ghrelin / GH-secretagogue receptor), pituitary somatotrophs | Agonist → pulsatile GH release; selective — no meaningful ACTH, cortisol or prolactin rise (rat) 1Reference 1In vitroIpamorelin, the first selective growth hormone secretagogue — in vitro / animal (rat)View study → | All applications |
| GH → hepatic IGF-1 axis | GH pulse in humans 2Reference 2Clinical trialPharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers — human (PK/PD, healthy men)View study →; note the rat longitudinal-growth effect occurred without a rise in total IGF-1 6Reference 6AnimalIpamorelin, a new growth-hormone-releasing peptide, induces longitudinal bone growth in rats — animal (rat)View study → | Bonebody composition |
| GHS-R1a in gut smooth muscle / enteric pathways | Prokinetic — accelerates gastric emptying and transit (rat) 11, | GI motility — tested in humansnegative |
| Bone formation / periosteal remodeling | ↑ bone mineral content and longitudinal growth rate; counteracts glucocorticoid-induced suppression (rat) 5, | Bone (animal-only) |
| Nitrogen balance / anti-catabolism | Improves nitrogen balance in steroid-treated rats 4Reference 4AnimalGrowth hormone and growth hormone secretagogue effects on nitrogen balance and urea synthesis in steroid treated rats — animal (rat)View study → | Muscle-preservation rationale (animal-only) |
| Appetite / adiposity (GH-independent) | ↑ food intake, leptin and relative fat mass (mouse) 8Reference 8AnimalGrowth hormone (GH)-independent stimulation of adiposity by GH secretagogues — animal (mouse)View study →; reduces cisplatin-induced weight loss (ferret) 13Reference 13The growth hormone secretagogue receptor 1a agonists, anamorelin and ipamorelin, inhibit cisplatin-induced weight loss in ferrets — animal (ferret) / ex vivoView study → | Body composition — counter-signal to the fat-loss claim |
Pharmacokinetics
Ipamorelin is a peptide, so oral bioavailability is negligible — it is not absorbed intact from the gut, which is why every study and every community protocol uses a parenteral route. Any oral “ipamorelin” product is pharmacologically inert regardless of the label. Human PK is characterized: in healthy male volunteers given 15-minute IV infusions, exposure was dose-proportional with a short terminal half-life of ~2 hours, clearance of ~0.078 L/h/kg and a steady-state volume of distribution of ~0.22 L/kg 2Reference 2Clinical trialPharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers — human (PK/PD, healthy men)View study →. In rats, systemic plasma clearance was roughly five-fold lower than GHRP-6, the peptide was excreted mainly intact in urine (rather than via the biliary route used by GHRP-6), and intranasal delivery achieved only modest bioavailability 14Reference 14AnimalPharmacokinetic evaluation of ipamorelin and other peptidyl growth hormone secretagogues with emphasis on nasal absorption — animal (rat, PK)View study →. The Phase 2 trials dosed it as an intravenous infusion (0.03 mg/kg twice daily) 3Reference 3RCTProspective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients — human (Phase 2 RCT, NCT00672074)View study →; gray-market use is subcutaneous injection of reconstituted lyophilized powder — a route for which no human PK has been published. The short half-life is decision-relevant: any GH effect is a brief pulse, not sustained elevation, which is precisely what the human PK/PD data show 2Reference 2Clinical trialPharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers — human (PK/PD, healthy men)View study →. Reconstitution and stability parameters for gray-market lyophilized product are vendor-level claims, not independently documented.
Clinical & regulatory status
Ipamorelin is not approved anywhere, for any indication — not by the FDA, EMA, TGA or any other regulator — and it holds no orphan or expedited designation. It was a genuine pharmaceutical development candidate: originated at Novo Nordisk as NNC 26-0161, later advanced by Helsinn Therapeutics for gastrointestinal motility disorders, and taken through Phase 2 before being discontinued. Two Helsinn Phase 2 trials are registered and completed on ClinicalTrials.gov: NCT00672074 (post-operative ileus; 117 enrolled, completed December 2009) and NCT01280344 (recovery of gastrointestinal function; 320 enrolled, completed May 2014). Neither has results posted on the registry. The published NCT00672074 outcome was a null result — well tolerated, but no significant benefit over placebo on the key or secondary efficacy endpoints 3Reference 3RCTProspective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients — human (Phase 2 RCT, NCT00672074)View study → — and no further development followed. Today ipamorelin circulates only as an unapproved research chemical sold “for research use only / not for human consumption,” and as a growth-hormone secretagogue it is prohibited in sport at all times under WADA class S2. The preclinical count below reflects what is findable and verifiable in PubMed in this pass; a substantial slice of the ipamorelin literature is anti-doping analytical-method work rather than efficacy research.
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 2Phase 2 (both GI; 1 published, negative) + 1 human PK/PD | 0 | 0registered — program discontinued post-Phase 2 | ~20+(PubMed) |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. Ipamorelin has never been approved for human use in any jurisdiction. It is not a medicine, not a recognized dietary supplement in the US, UK, EU or Australia, and it carries no marketing authorization anywhere. Its development history is the opposite of validation: a pharmaceutical sponsor took it through two Phase 2 trials, the published one missed its primary endpoint, and the program stopped 3Reference 3RCTProspective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients — human (Phase 2 RCT, NCT00672074)View study →. It is not a scheduled/controlled substance in the US, but “not scheduled” is not “approved” — marketing it for human consumption is unlawful in most Western jurisdictions, and it is sold instead as a research chemical labeled “not for human consumption.” In sport it is banned at all times as a growth-hormone secretagogue (WADA Prohibited List, class S2), and it is a routine target in doping-control assays.
How it’s supplied & administered. Gray-market ipamorelin ships as a lyophilized (freeze-dried) powder in a multi-dose vial, which the buyer reconstitutes with bacteriostatic or sterile water. Because it is a peptide with negligible oral bioavailability it must be given parenterally: the clinical trials used intravenous infusion, and community use is subcutaneous injection. Lyophilized powder is generally stored refrigerated or frozen and protected from light; reconstituted solution is unstable and short-lived. The ~2-hour half-life means it is dosed for a transient GH pulse rather than sustained elevation — which is why community protocols involve repeated injections, a pattern no trial has ever evaluated.
Sourcing reality (this is a safety issue, not a footnote). Every gray-market vial comes from an unregulated supplier with no manufacturing oversight. There is no assurance of identity, correct sequence, peptide content, freedom from synthesis-related impurities, or absence of bacterial endotoxin — the last of which matters acutely for an injected product, where contamination can cause fever, injection-site reactions or systemic illness. Mislabeling, under- and over-filling, and outright substitution are documented problems across the research-peptide market generally. Third-party certificates of analysis — independent identity and purity testing by mass spectrometry/HPLC plus endotoxin testing — are the minimum needed to interpret the risk, and even those are only as trustworthy as the party commissioning them. This page does not recommend or link vendors; the honest position is that gray-market peptide identity and purity cannot be assumed.
Safety
Ipamorelin has something most research peptides lack — a real short-term human tolerability record from a controlled trial. But that record covers seven monitored days of intravenous dosing in hospital, and the chronic subcutaneous self-injection people actually do has never been studied at all.
- Well tolerated in its Phase 2 trial. Adverse events were lower than placebo across up to seven days of twice-daily IV dosing in 114 patients.
- Selectivity holds. It releases GH without the ACTH, cortisol and prolactin rise seen with GHRP-2 and GHRP-6.
- Several groups should avoid it. Active or prior malignancy, diabetes or impaired glucose tolerance without supervision, children and adolescents, and anyone pregnant or breastfeeding.
- Long-term safety is unassessed. Total trial exposure was seven days; the community route has no published human pharmacokinetics.
- Class effects are inferred, not measured. IGF-1 elevation, insulin sensitivity and fluid balance follow from the GH axis rather than from ipamorelin findings.
- Unregulated injected product. Injection-site reactions, non-sterile technique, endotoxin exposure and self-reconstitution dosing error.
Full Safety & Interactions Detail
Overall posture. Ipamorelin’s short-term human safety profile is, unusually for a research peptide, backed by actual trial data: in the post-operative-ileus RCT (114 patients in the safety population), it was well tolerated, with treatment-emergent adverse events lower than placebo (87.5% vs 94.8%) across up to seven days of twice-daily IV dosing in a hospital setting 3Reference 3RCTProspective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients — human (Phase 2 RCT, NCT00672074)View study →. That is genuinely reassuring for acute, supervised, intravenous use — and it says nothing about chronic, self-injected, subcutaneous use at community doses, which no study has assessed. Do not let seven monitored days stand in for open-ended self-administration.
Class-level expectations (mechanism, not findings). As a GH secretagogue, ipamorelin would be expected to raise IGF-1, and the GH class carries recognized effects on insulin sensitivity and glucose handling and on fluid balance (edema, arthralgia and carpal-tunnel-type symptoms are characteristic of GH excess). These are inferred from the mechanism and the behavior of the GH axis, not demonstrated ipamorelin trial findings, and are labeled as such. The one direct counter-signal worth naming is the rodent finding that GH secretagogues can increase appetite and relative fat mass by a GH-independent route 8Reference 8AnimalGrowth hormone (GH)-independent stimulation of adiposity by GH secretagogues — animal (mouse)View study → — the opposite of the intended effect for anyone using it for body composition.
Route-specific risks. For gray-market use the dominant hazards are not classical drug toxicity but delivery and product risks: injection-site reactions, infection from non-sterile technique, endotoxin exposure from unregulated product, and dosing error from self-reconstituted concentrations. These risks are structural to how the compound is obtained and used, and they exist independently of the peptide’s own pharmacology.
Interactions. No formal human drug-interaction studies exist. Mechanistic cautions only: agents affecting glucose control (insulin, other antidiabetic drugs) because of the GH axis’s effect on insulin sensitivity, and additive GH stimulation when stacked with other secretagogues or GHRH analogues (the common community “GHRH + GHRP” pattern). Both are class reasoning, not assessed interactions.
Who should avoid it. Anyone pregnant, breastfeeding or trying to conceive; children and adolescents (an unstudied compound acting on the growth axis during growth); anyone with active or prior malignancy, given GH/IGF-1’s proliferative signaling; anyone with diabetes or impaired glucose tolerance without medical supervision; competitive athletes (banned at all times); and anyone unwilling to accept an unapproved product of unverified identity and purity.
Scope disclosure (honesty, not a claim):
- Human data? Yes, but narrow and mostly negative — one human PK/PD study in healthy men 2Reference 2Clinical trialPharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers — human (PK/PD, healthy men)View study → and two Phase 2 GI-motility RCTs, the published one null 3Reference 3RCTProspective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients — human (Phase 2 RCT, NCT00672074)View study →. There are no human data for the muscle, fat-loss, recovery or anti-aging uses it is actually sold for.
- Interactions assessed? No. Only class/mechanism cautions (glucose-lowering agents; stacking with other GH secretagogues or GHRH analogues), which are inferred, not tested.
- Pregnancy/lactation assessed? No — no human or animal reproductive data located.
- Long-term safety established? No. Total trial exposure was up to seven days of monitored IV dosing. The chronic subcutaneous self-administration pattern used in the community is entirely unstudied.
Never imply safety from silence. Where ipamorelin has not been studied — chronic use, the subcutaneous route, interactions, pregnancy, gray-market product purity — the correct statement is “not assessed,” not “safe.” Equally, a clean short-term tolerability record is not evidence that the compound works: the same trial that found it well tolerated found it no better than placebo.
Not assessed / not established. There are no human pregnancy or lactation data and no reproductive-toxicity data specific to ipamorelin in the accessible literature. Treat as contraindicated by default in pregnancy and breastfeeding.
Dosage
There is no established human therapeutic dose for ipamorelin, and none is recommended here. It has never been approved for any indication in any country, so there is no label, no titration schedule and no maintenance regimen to report. Every figure below is data reported for context, not a personal recommendation.
The only validated human dosing comes from the Phase 2 program, where ipamorelin was given as an intravenous infusion of 0.03 mg/kg twice daily for up to seven days following bowel-resection surgery — and at that dose, in that setting, it did not beat placebo 3Reference 3RCTProspective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients — human (Phase 2 RCT, NCT00672074)View study →. The human PK/PD study used single 15-minute IV infusions across a 4.21–140.45 nmol/kg range and found a GH pulse at every dose level, with a ~2-hour terminal half-life 2Reference 2Clinical trialPharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers — human (PK/PD, healthy men)View study →. Gray-market practice — microgram-to-milligram subcutaneous injections, often timed around sleep or training and frequently stacked with a GHRH analogue — derives from vendor copy and community convention, not from any human dose-finding study, and the subcutaneous route has no published human pharmacokinetics at all. Oral products cannot deliver intact peptide (see Pharmacokinetics). This entry is informational only.
References
- Raun K, Hansen BS, Johansen NL, et al. (1998). Ipamorelin, the first selective growth hormone secretagogue — in vitro / animal (rat). European Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/9849822/
- Gobburu JV, Agersø H, Jusko WJ, Ynddal L. (1999). Pharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers — human (PK/PD, healthy men). Pharmaceutical Research. https://pubmed.ncbi.nlm.nih.gov/10496658/
- Beck DE, Sweeney WB, McCarter MD; Ipamorelin 201 Study Group. (2014). Prospective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients — human (Phase 2 RCT, NCT00672074). International Journal of Colorectal Disease. https://pubmed.ncbi.nlm.nih.gov/25331030/
- Aagaard NK, Grøfte T, Greisen J, et al. (2009). Growth hormone and growth hormone secretagogue effects on nitrogen balance and urea synthesis in steroid treated rats — animal (rat). Growth Hormone & IGF Research. https://pubmed.ncbi.nlm.nih.gov/19231263/
- Svensson J, Lall S, Dickson SL, et al. (2000). The GH secretagogues ipamorelin and GH-releasing peptide-6 increase bone mineral content in adult female rats — animal (rat). Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/10828840/
- Johansen PB, Nowak J, Skjaerbaek C, et al. (1999). Ipamorelin, a new growth-hormone-releasing peptide, induces longitudinal bone growth in rats — animal (rat). Growth Hormone & IGF Research. https://pubmed.ncbi.nlm.nih.gov/10373343/
- Andersen NB, Malmlöf K, Johansen PB, et al. (2001). The growth hormone secretagogue ipamorelin counteracts glucocorticoid-induced decrease in bone formation of adult rats — animal (rat). Growth Hormone & IGF Research. https://pubmed.ncbi.nlm.nih.gov/11735244/
- Lall S, Tung LY, Ohlsson C, et al. (2001). Growth hormone (GH)-independent stimulation of adiposity by GH secretagogues — animal (mouse). Biochemical and Biophysical Research Communications. https://pubmed.ncbi.nlm.nih.gov/11162489/
- Sinha DK, Balasubramanian A, Tatem AJ, et al. (2020). Beyond the androgen receptor: the role of growth hormone secretagogues in the modern management of body composition in hypogonadal males — review. Translational Andrology and Urology. https://pubmed.ncbi.nlm.nih.gov/32257855/
- Dominikowski A, et al. (2026). The emerging landscape of performance-enhancing peptides modulating the GH-IGF1 axis: bridging the gap between clinical evidence and patient self-administration — review. Frontiers in Endocrinology. https://pubmed.ncbi.nlm.nih.gov/42395176/
- Venkova K, Mann W, Nelson R, Greenwood-Van Meerveld B. (2009). Efficacy of ipamorelin, a novel ghrelin mimetic, in a rodent model of postoperative ileus — animal (rat). Journal of Pharmacology and Experimental Therapeutics. https://pubmed.ncbi.nlm.nih.gov/19289567/
- Greenwood-Van Meerveld B, Tyler K, Mohammadi E, et al. (2012). Efficacy of ipamorelin, a ghrelin mimetic, on gastric dysmotility in a rodent model of postoperative ileus — animal (rat). Journal of Experimental Pharmacology. https://pubmed.ncbi.nlm.nih.gov/27186127/
- Lu Z, Ngan MP, Liu JYH, et al. (2024). The growth hormone secretagogue receptor 1a agonists, anamorelin and ipamorelin, inhibit cisplatin-induced weight loss in ferrets — animal (ferret) / ex vivo. Physiology & Behavior. https://pubmed.ncbi.nlm.nih.gov/39043357/
- Johansen PB, Hansen KT, Andersen JV, et al. (1998). Pharmacokinetic evaluation of ipamorelin and other peptidyl growth hormone secretagogues with emphasis on nasal absorption — animal (rat, PK). Xenobiotica. https://pubmed.ncbi.nlm.nih.gov/9879640/



