
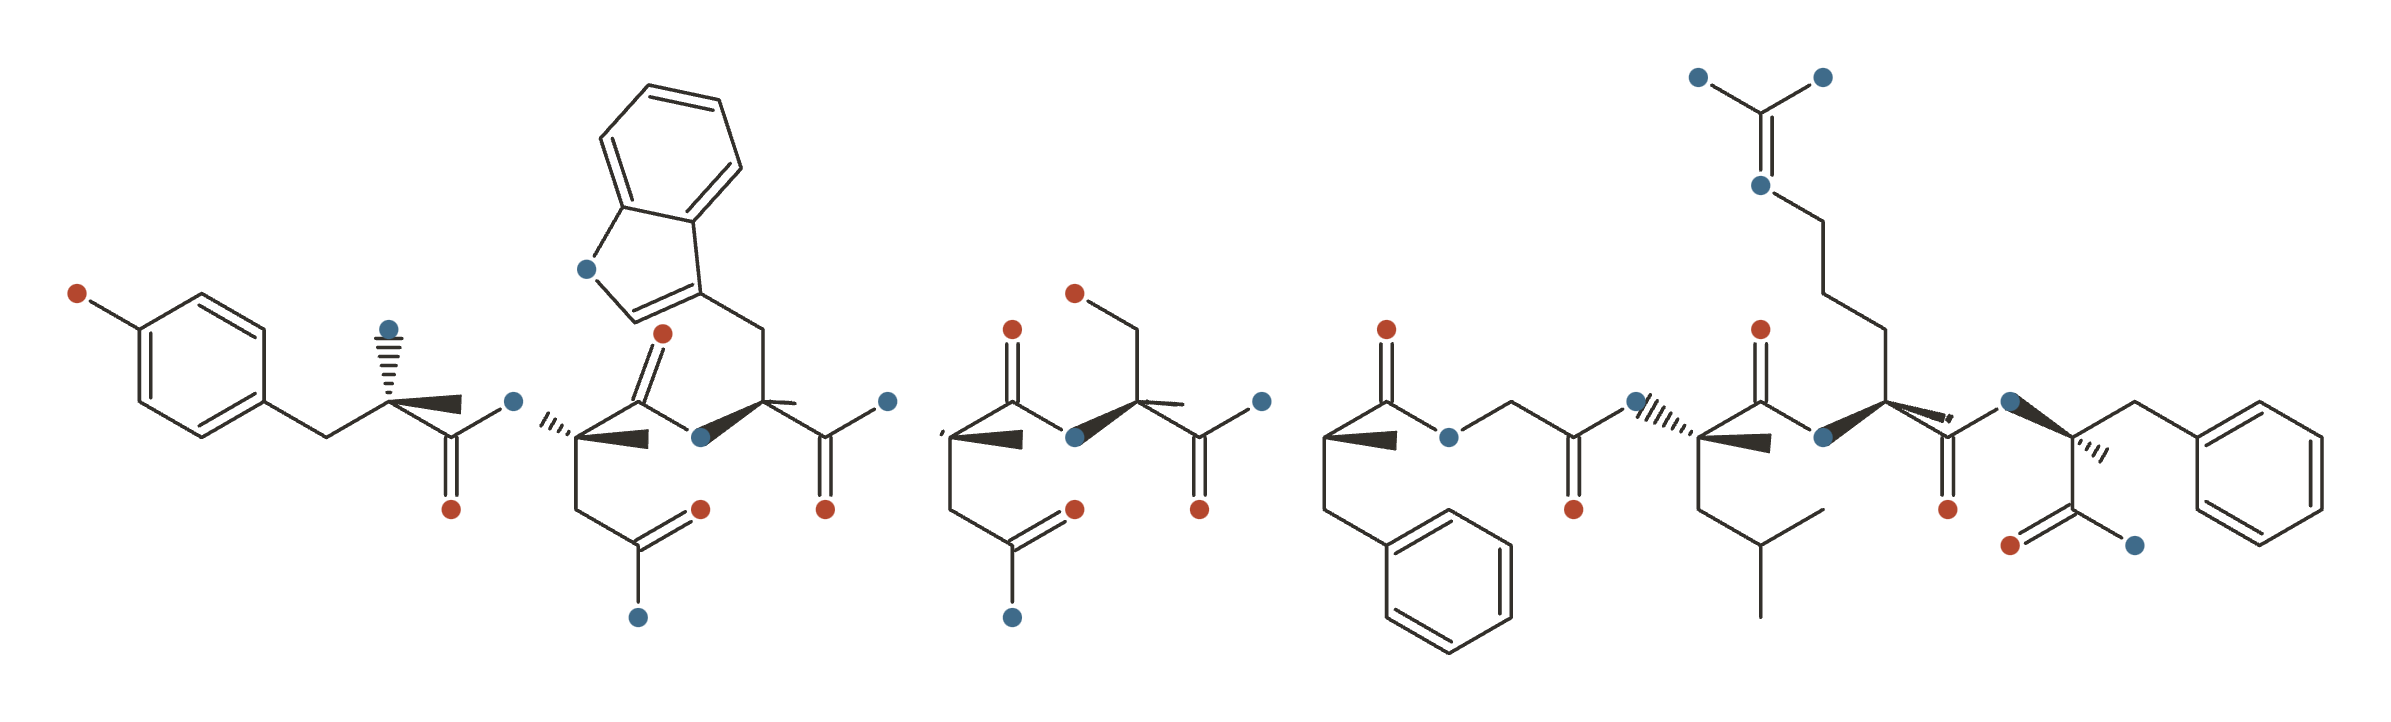
Kisspeptin-10
The 10-amino-acid fragment of kisspeptin — a KISS1R agonist that triggers GnRH release and an LH surge, studied in humans only as an intravenous probe.

Kisspeptin-10 at a Glance
Kisspeptin-10 is the shortest active fragment of kisspeptin, the peptide that sits upstream of the entire reproductive hormone cascade — it acts on GnRH neurons to trigger the pulse that produces an LH surge. Its discovery reframed how puberty and fertility are understood, since loss of kisspeptin signalling prevents puberty entirely. It is investigational, studied in fertility medicine and as a diagnostic, and it is not approved.
History & Development
Kisspeptin is the switch that starts puberty. It was found through the genetics of people in whom that switch never flipped.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Not established in the sources consulted for this section |
| Origin | Synthetic decapeptide - the C-terminal fragment (112-121) of the KISS1 gene product, endogenous ligand of the KISS1R (GPR54) receptor |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Investigational - academic human studies only; not approved anywhere |
Discovery
Kisspeptin sits one level above GnRH. It acts on KISS1R-expressing neurons in the hypothalamus, which in turn drive GnRH release - so kisspeptin is the upstream trigger for the entire reproductive cascade, and its discovery reorganised how the axis is understood.
Kisspeptin-10 is the ten-amino-acid C-terminal fragment of the larger KISS1 product, retaining full receptor activity. Its gene name is a curiosity worth knowing: KISS1 was named for Hershey’s Kisses, after the Pennsylvania laboratory where it was first identified as a metastasis-suppressor gene - years before anyone connected it to reproduction.
Development & ownership
Kisspeptin-10 has no corporate development programme, and that shapes its whole record. What exists is academic: short, monitored intravenous studies in university units, administered to healthy men, to boys through puberty, and in reproductive disorders.
That work is unusually good for a compound sold on the grey market - real, replicated, published human data, rather than rodent extrapolation. A ClinicalTrials.gov query in July 2026 returned 25 interventional kisspeptin studies, 18 specifying kisspeptin-10 or kisspeptin 112-121, of which 12 had completed.
The gap between that literature and the retail product is the route and duration. Every human study is a short intravenous bolus or infusion under monitoring; nothing supports repeated subcutaneous self-administration, which is how it is sold.
How it reached the market
No kisspeptin peptide holds marketing authorisation from the FDA, EMA, TGA or PMDA for any indication. Kisspeptin-10 reaches consumers as an unapproved research chemical, marketed for testosterone and libido on the strength of academic studies that measured hormone pulses over hours, not outcomes over months.
What It's Used For
Kisspeptin-10 is the C-terminal decapeptide of kisspeptin — YNWNSFGLRF-NH₂, residues 112–121 of the KISS1 gene product (also written metastin 45–54) — and it is the shortest fragment that retains full activity at the kisspeptin receptor KISS1R (GPR54) 10Reference 10In vitroLC-MS/MS quantification of kisspeptin-10 (NSC 741805), characterization of its decomposition product and pharmacokinetics — animal (rat PK) / in vitroView study →.
It works upstream of the reproductive axis: it stimulates hypothalamic GnRH neurons to release their own GnRH, which drives pituitary luteinizing hormone (LH) and follicle-stimulating hormone (FSH), which in turn drive gonadal testosterone or estradiol. It is not a GnRH agonist, and that distinction matters — it is one receptor further up the chain, which is exactly why researchers use it.
Two facts reframe everything here. The first is that, unusually for a compound sold on the peptide gray market, kisspeptin-10 has real, replicated, published human data — administered to healthy men, boys through puberty, men with type 2 diabetes, women with amenorrhea and women with PCOS, by academic endocrinology groups in the UK, US and Pakistan. That is a far stronger human base than most of this hub. But all of it is acute physiology: hormone concentrations measured over hours. Not one kisspeptin-10 study has a clinical endpoint — no fertility outcome, no symptom score, no body-composition measure — and no kisspeptin peptide is approved by any regulator anywhere.
The second is a fragment problem, and it is the single most-abused thing about this compound. The famous kisspeptin headlines — triggering egg maturation in IVF with a lower risk of ovarian hyperstimulation syndrome, treating hypothalamic amenorrhea, the fMRI trials on sexual desire — were run with kisspeptin-54, a longer molecule with roughly eight times the circulating half-life that reaches GnRH neurons behind the blood–brain barrier after peripheral dosing when kisspeptin-10 does not 9,
Those results are frequently recycled as marketing for kisspeptin-10. They do not transfer. Route is load-bearing on top of that: kisspeptin-10’s bloodstream half-life is about four minutes, essentially all published human work used intravenous bolus or infusion, and the subcutaneous self-injection the gray market sells is not the route the evidence was generated on.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Two calibration notes specific to this compound. First, these scores sit higher than most preclinical-only peptides on this hub because the human studies are real — but they are capped well below approval-grade because every endpoint is a hormone concentration, every sample size is single- or double-digit, and none of it is phase 3. Second, the strongest kisspeptin clinical program — the IVF oocyte-maturation trigger — is deliberately absent from this table, because it used kisspeptin-54. It is written up in toggle 5 as context, unscored.
This is the core kisspeptin-10 human finding, and it replicates across independent groups. In the defining study, intravenous bolus kisspeptin-10 (0.01–3.0 µg/kg) in healthy men produced a rapid, dose-dependent LH rise, maximal at 1 µg/kg; continuous infusion at 1.5 µg/kg/h raised LH pulse frequency and pulse size, and higher-rate infusion raised testosterone 1Reference 1Clinical trialKisspeptin-10 is a potent stimulator of LH and increases pulse frequency in men — human (clinical trial)View study →.
The same acute response held in five hypotestosteronemic men with type 2 diabetes and seven age-matched controls — a 0.3 µg/kg IV bolus roughly doubled LH in both groups, and infusion raised testosterone 2Reference 2Clinical trialExploring the pathophysiology of hypogonadism in men with type 2 diabetes: kisspeptin-10 stimulates serum testosterone and LH secretion — human (clinical study)View study →.
In healthy men across three age bands, a 1 µg/kg IV bolus significantly raised LH in every group, but raised testosterone only in the youngest — implicating declining Leydig-cell responsiveness rather than central failure with age 3Reference 3Age-dependent changes in the reproductive axis responsiveness to kisspeptin-10 administration in healthy men — humanView study →.
Most recently, a 24-hour continuous IV infusion at 12.5 µg/kg/h in three healthy men drove LH five- to eightfold above baseline within 12–20 hours, after which it declined 13–47% while the infusion continued — early desensitization, measured directly 4Reference 4Dynamic modulation of LH secretion by continuous kisspeptin infusion in healthy men — human (n=3, 24-h IV infusion)View study →.
Every one of these is human, and every one used intravenous administration under clinical monitoring. Every endpoint is a circulating hormone level. Sample sizes run from three to a few dozen.
Gap: No human trial links kisspeptin-10 to any clinical endpoint — not fertility, not symptoms, not body composition. There is no dose-finding study for a therapeutic outcome because there is no therapeutic outcome under study. Marketed subcutaneous “testosterone-boost” protocols have no controlled evidence at all and run against the peptide’s ~4-minute half-life.
Because a kisspeptin-10 bolus produces a fast, clean, GnRH-mediated LH pulse and then clears, it is being tested as a diagnostic probe rather than a treatment — the application where the short half-life is a feature. In healthy boys grouped by Tanner stage (n=5 per stage) plus adult men, an IV kisspeptin-10 bolus produced no significant LH response at Tanner I–III, a testosterone response at Tanner IV, and a full LH and testosterone response at Tanner V — a human demonstration that KISS1R responsiveness emerges through puberty 5Reference 5Changes in the responsiveness of the hypothalamic-pituitary-gonadal axis to kisspeptin-10 administration during pubertal transition in boys — humanView study →.
The aging study used the same bolus design to separate central from gonadal responsiveness 3Reference 3Age-dependent changes in the reproductive axis responsiveness to kisspeptin-10 administration in healthy men — humanView study →.
Registered trials extend this: NCT07224490 (phase 1, n=40, recruiting) is explicitly designed to quantify GnRH-neuron function in health and disease using kisspeptin 112-121, and NCT01438073 (phase 1, n=96, completed) used it alongside GnRH to dissect kisspeptin signaling. A completed 14-participant study of kisspeptin-10 and insulin secretion in men (NCT03771326) extends the probe idea beyond reproduction — note that this record is registry-tagged “Phase 3”, which is an artifact of registration practice, not a real phase-3 program.
Gap: Human but exploratory. Single-center physiology studies, no standardized assay, no reference ranges, no diagnostic qualification by any regulator. This is not an established clinical test.
Small human studies show kisspeptin-10 can re-engage a suppressed reproductive axis in women. In two women with cabergoline-resistant microprolactinomas and chronic hyperprolactinemic amenorrhea, a 12-hour IV kisspeptin-10 infusion at 1.5 µg/kg/h significantly raised LH and FSH, increased LH pulses, and raised estradiol, testosterone and inhibin B 6Reference 6Hypothalamic-pituitary-ovarian axis reactivation by kisspeptin-10 in hyperprolactinemic women with chronic amenorrhea — human (n=2, exploratory)View study →.
In women with PCOS (n=8 treated, n=7 untreated), a 7-hour IV kisspeptin-10 infusion at 4 µg/kg/h still produced its stimulatory LH response after seven days of a neurokinin-3-receptor antagonist, mapping the NKB–kisspeptin interaction in the disorder 7Reference 7RCTKisspeptin and neurokinin B interactions in modulating gonadotropin secretion in women with polycystic ovary syndrome — human (randomised crossover)View study →.
Both are genuinely human and genuinely informative about mechanism.
They are also tiny — one has an n of two — and neither measured a therapeutic outcome. The substantive female therapeutic program in this space, including the hypothalamic-amenorrhea dose-ranging work, used kisspeptin-54 14Reference 14Increasing LH pulsatility in women with hypothalamic amenorrhoea using intravenous infusion of kisspeptin-54 — human (n=5; kisspeptin-54)View study →, and even there chronic dosing caused tachyphylaxis, which was the limiting finding.
Gap: Extremely small n, no clinical endpoint, no kisspeptin-10 therapeutic trial in women. Two subcutaneous kisspeptin 112-121 trials are now recruiting in this space — NCT07224438 (phase 2, n=20, hypothalamic amenorrhea) and NCT05896293 (phase 2, n=36, idiopathic hypogonadotropic hypogonadism) — which would be the first real test.
KISS1R is expressed on oxytocin neurons, which makes kisspeptin a candidate probe of the oxytocin system as well as the reproductive one. In 12 healthy adults (half female), an IV bolus of kisspeptin-112-121 (0.24 nmol/kg — this is kisspeptin-10 under its residue-numbering name) raised serum oxytocin by 18.8% at 10 minutes, with a much larger rise in men than women (31.9% vs 5.7%), supporting it as a candidate provocative test for oxytocin deficiency in males 8Reference 8Sex-dependent increases in oxytocin levels in response to intravenous kisspeptin in humans — human (n=12)View study →.
The study was registered under NCT00914823 (phase 1, completed).
Gap: One small human study, no replication, no validated cut-offs, no diagnostic qualification. A promising research tool, not a clinical test — and the female response was small enough that the authors limited their claim to men.
5. IVF Oocyte-Maturation Trigger — a Kisspeptin-54 Result
This is the strongest clinical program in the kisspeptin field, it is genuinely interesting, and it is not kisspeptin-10 — so it is not scored above. Reproduced here because it is the evidence most often mis-sold as belonging to this molecule.
The rationale is real: kisspeptin triggers an endogenous LH surge that is shorter than the sustained stimulus from hCG, which is the standard IVF trigger and the driver of ovarian hyperstimulation syndrome (OHSS). In the first study, 53 women undergoing IVF received a single subcutaneous injection of kisspeptin-54 (1.6–12.8 nmol/kg) after standard FSH/GnRH-antagonist stimulation, and eggs were retrieved 36 hours later with maturation as the primary outcome 12Reference 12In vitroKisspeptin-54 triggers egg maturation in women undergoing in vitro fertilization — human (n=53; kisspeptin-54, subcutaneous)View study →.
A follow-up phase 2, multi-dose, open-label randomized trial in 60 women at high risk of OHSS tested the same trigger with adaptive dose allocation 13Reference 13RCTEfficacy of kisspeptin-54 to trigger oocyte maturation in women at high risk of ovarian hyperstimulation syndrome during IVF — human (phase 2 randomised, n=60; kisspeptin-54)View study →.
Related work established kisspeptin-54’s dose-dependent stimulation of LH pulsatility in hypothalamic amenorrhea 14Reference 14Increasing LH pulsatility in women with hypothalamic amenorrhoea using intravenous infusion of kisspeptin-54 — human (n=5; kisspeptin-54)View study → and its acute HPG-axis effect in men 11Reference 11RCTKisspeptin-54 stimulates the hypothalamic-pituitary gonadal axis in human males — human (RCT, crossover; kisspeptin-54)View study →.
Gap — and this is the honest read: the program peaked at phase 2, in dozens of women at a single London center. No phase 3 trial, no regulatory filing, and no approval anywhere followed; development effort has largely shifted to longer-acting KISS1R analogues such as MVT-602 17,
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| KISS1R (GPR54), Gq-coupled | Agonism on hypothalamic GnRH neurons → GnRH release | All applications |
| Pituitary gonadotropes (via GnRH) | ↑ LH and FSH; ↑ LH pulse frequency and pulse size | Male stimulationamenorrheadiagnostic probe |
| Gonad (downstream) | ↑ testosterone in men; ↑ estradiol and inhibin B in women | Male stimulationamenorrhea |
| Oxytocin neurons (KISS1R-expressing) | ↑ oxytocin release, markedly larger in men | Oxytocin-deficiency probe |
| Receptor desensitization | High bolus or continuous exposure → blunted / declining LH response | Dosing logic; argues against continuous use |
| Blood–brain barrier access | Peripheral kisspeptin-10 fails to activate GnRH neurons behind the BBB (mouse); kisspeptin-54 succeeds | Explains why KP-54 results do not transfer |
| Neurokinin B (NKB) pathway | Kisspeptin response persists under NK3-receptor blockade in PCOS | Mechanistic mapping only |
| KISS1 as metastin | Original identification as a metastasis-suppressor gene product | Historical; oncology analogues (TAK-448/683) |
Pharmacokinetics
The defining pharmacokinetic fact about kisspeptin-10 is how fast it disappears. In a validated LC-MS/MS study in rats it degraded with plasma decomposition half-lives of roughly 1.7–6.8 minutes depending on temperature, was undetectable about 30 minutes after an IV bolus, and broke down primarily by loss of the N-terminal tyrosine 10Reference 10In vitroLC-MS/MS quantification of kisspeptin-10 (NSC 741805), characterization of its decomposition product and pharmacokinetics — animal (rat PK) / in vitroView study →. A direct head-to-head in mice put its bloodstream half-life at ~4 minutes against ~32 minutes for kisspeptin-54 — and, critically, showed that repeated kisspeptin-10 injections still failed to reproduce the sustained LH release of a single kisspeptin-54 dose, because only kisspeptin-54 reached GnRH neurons behind the blood–brain barrier after peripheral administration 9Reference 9AnimalMechanistic insights into the more potent effect of KP-54 compared to KP-10 in vivo — animal (mouse; PK and BBB access)View study →. No precise human half-life figure for kisspeptin-10 is established in the accessible literature; the human record is consistent with minutes.
Route is therefore the whole story. Essentially all published human kisspeptin-10 work is intravenous — bolus for a single clean LH pulse, or timed infusion when sustained exposure is needed — precisely because no simpler route can hold exposure up. Oral dosing is not a possibility: a decapeptide is digested, not absorbed. Subcutaneous kisspeptin-10 is not fantasy — three registered phase 2 trials are testing pulsatile subcutaneous delivery by pump in hypogonadotropic hypogonadism and hypothalamic amenorrhea (NCT04648969, completed, n=18; NCT05896293 and NCT07224438, recruiting) — but pulsatile pump delivery under trial conditions is a different thing from a once-daily self-injection, and none of those trials has reported. The published human intranasal kisspeptin data used kisspeptin-54, not kisspeptin-10 19Reference 19RCTIntranasal kisspeptin administration rapidly stimulates gonadotropin release in humans — human (randomised crossover; kisspeptin-54)View study →. As lyophilized powder it requires reconstitution and is unstable in solution, so cold handling and timing are genuinely consequential rather than nominal.
The practical conclusion: a compound that had to be infused intravenously to produce its published effects does not support oral or casual subcutaneous protocols, and any claim built on one should be read against the four-minute number.
Clinical & regulatory status
Kisspeptin-10 is an unapproved research chemical. No kisspeptin peptide — kisspeptin-10, kisspeptin-54, or any analogue — holds marketing authorization from the FDA, EMA, TGA or PMDA for any indication, and none has been submitted for one. Material sold online as “kisspeptin-10” is gray-market, typically labeled “for research use only / not for human consumption”, with no manufacturing oversight.
Registered-trial activity is real but modest and academic. A ClinicalTrials.gov query in July 2026 returns 25 interventional kisspeptin studies overall, of which 18 specify kisspeptin-10 / kisspeptin 112-121 — 12 completed, 3 recruiting, 2 withdrawn, 1 terminated. These are phase 1 and phase 2 physiology and proof-of-concept studies at a handful of academic centers (Boston, London, Edinburgh), enrolling tens of participants; the largest, NCT00914823, is a long-running phase 1 administration program with 256 participants. The kisspeptin-54 IVF-trigger program also stopped at phase 2 13Reference 13RCTEfficacy of kisspeptin-54 to trigger oocyte maturation in women at high risk of ovarian hyperstimulation syndrome during IVF — human (phase 2 randomised, n=60; kisspeptin-54)View study →. Commercial development has moved to analogues rather than the native fragments — MVT-602, a long-acting KISS1R agonist 17,
| Completed | Ongoing | Terminated / Withdrawn | Preclinical |
|---|---|---|---|
| 12(kisspeptin-10-specific) | 3recruiting | 3 | Extensive(rodent, ovine, primate) |
Trial counts are ClinicalTrials.gov interventional records naming kisspeptin-10 or kisspeptin 112-121, queried July 2026. The wider kisspeptin field (25 interventional records) is dominated by kisspeptin-54 and analogues.
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. Kisspeptin-10 is not approved as a drug or as a dietary supplement anywhere — not by the FDA, EMA, TGA or PMDA — for any indication. There is no approval document to cite because none exists; the compound lives entirely in academic research and on the gray market. Kisspeptin peptides are in registered clinical trials, but investigational use under an IND is not marketing authorization, and it never converts into one by itself. It is not a scheduled or controlled substance in the US, but “not scheduled” is not “approved”: selling it for human consumption is unlawful in most Western jurisdictions, which is why every vendor labels it “not for human consumption”.
How it’s supplied and administered. Kisspeptin-10 is sold as a lyophilized powder requiring reconstitution, typically in bacteriostatic water, before injection. In legitimate human research it is given intravenously — bolus or timed infusion — because its plasma half-life is roughly four minutes and it degrades quickly in solution, so exposure cannot be sustained any other way. The route the gray market sells (subcutaneous self-injection, usually once daily) is not the route the human evidence was generated on, and that mismatch is not a technicality: the mouse comparison shows that even repeated injections of kisspeptin-10 failed to reproduce a single kisspeptin-54 dose’s sustained LH release 9Reference 9AnimalMechanistic insights into the more potent effect of KP-54 compared to KP-10 in vivo — animal (mouse; PK and BBB access)View study →. Pulsatile subcutaneous delivery by pump is under trial in specific patient groups, and an intranasal route exists — for kisspeptin-54 19Reference 19RCTIntranasal kisspeptin administration rapidly stimulates gonadotropin release in humans — human (randomised crossover; kisspeptin-54)View study →. Reconstituted peptide is unstable and needs cold storage.
Sourcing reality (this is a safety issue, not a footnote). Because there is no approved product, every consumer source is an unregulated vendor with no manufacturing oversight. Identity and sequence (kisspeptin-10 vs -13 vs -14 vs -54 are all sold, and are not interchangeable), peptide content versus label, purity, and bacterial endotoxin are all unverifiable for an injected product. A mislabeled or contaminated vial adds infection and immunogenicity risk on top of the pharmacology, and dosing in micrograms per kilogram from self-reconstituted powder makes concentration errors easy. Third-party certificates of analysis — independent HPLC identity/purity and endotoxin testing — are the only partial mitigation, and even those can be falsified. This page does not recommend or link vendors. Anyone handling kisspeptin-10 outside a clinical trial is handling an unapproved injectable of unverified quality.
Safety
Kisspeptin-10 is an unapproved research peptide that has only ever been given to people as a short, monitored intravenous probe — so the honest headline is not that it is safe but that almost nothing about consumer-style use has been assessed. It acts directly on the reproductive axis, and every consumer vial comes from an unregulated source.
- Unapproved injectable from unregulated vendors. Identity, purity and endotoxin are unverifiable, adding infection and immunogenicity risk.
- Contraindicated in pregnancy, breastfeeding and while trying to conceive. See the box below.
- Acts directly on the reproductive axis. Avoid with hormone-sensitive conditions; the adolescent data are a research probe, not a use case.
- Desensitization is measured, not theoretical. High boluses and continuous infusion both blunt the LH response.
- Interactions not assessed. GnRH agents, hormone therapy and dopamine agonists are mechanistic flags only, with no drug–drug data.
Full Safety & Interactions Detail
Overall posture. In the small acute human studies conducted so far, intravenous kisspeptin-10 has generally been well tolerated, with no consistent adverse-event signal reported at the doses used 1,
The clearest pharmacological caveat is desensitization. This is measured, not theoretical: the highest bolus dose produced a smaller LH response than a lower one 1Reference 1Clinical trialKisspeptin-10 is a potent stimulator of LH and increases pulse frequency in men — human (clinical trial)View study →, a 24-hour continuous infusion produced LH that peaked and then fell 13–47% while dosing continued 4Reference 4Dynamic modulation of LH secretion by continuous kisspeptin infusion in healthy men — human (n=3, 24-h IV infusion)View study →, and for kisspeptin-54 chronic twice-daily dosing abolished the response within days 14Reference 14Increasing LH pulsatility in women with hypothalamic amenorrhoea using intravenous infusion of kisspeptin-54 — human (n=5; kisspeptin-54)View study →. Whatever else this means, it directly undercuts the “more, or continuously, is better” logic behind consumer dosing schedules.
Interactions. Not assessed — there are no controlled human drug-interaction studies. On mechanism alone (labeled as inference, not a finding), anything acting on the GnRH/LH axis is worth flagging: GnRH agonists and antagonists, testosterone or estrogen therapy, fertility protocols, and dopamine agonists (the hyperprolactinemia setting 6Reference 6Hypothalamic-pituitary-ovarian axis reactivation by kisspeptin-10 in hyperprolactinemic women with chronic amenorrhea — human (n=2, exploratory)View study →). These are class-level expectations, not measured drug–drug data.
Who should avoid it. Anyone pregnant, breastfeeding, or trying to conceive outside medical supervision; anyone with a hormone-sensitive condition; adolescents (the puberty data are a research probe, not a use case); and anyone unable to verify product sterility and identity — which is effectively all consumer use. As an injected unapproved peptide it also carries the usual injection risks: injection-site reactions, non-sterile technique, and endotoxin exposure from unregulated product.
Scope disclosure (honesty, not a claim):
- Human data? Yes — genuinely, and more than most peptides on this hub. But limited and specific: several small intravenous studies of hormone response in men, and exploratory studies in women. No clinical-endpoint trial of kisspeptin-10 exists, and none by oral or routine subcutaneous routes.
- Interactions assessed? No. Only mechanism/class-level cautions, and those are inferred, not tested.
- Pregnancy/lactation assessed? No — not established; avoid on mechanistic grounds.
- Long-term safety established? No. All human exposure has been short-term and acute. Absence of reported harm across hours of monitored infusion is not evidence of safety over months of self-injection.
Never imply safety from silence. Where kisspeptin-10 has not been studied — interactions, pregnancy, repeated subcutaneous use, long-term exposure, gray-market purity — the correct statement is “not assessed,” not “safe.”
Not assessed / not established. Kisspeptin is central to reproductive and placental physiology, so exogenous administration is inherently relevant here and cannot be assumed benign; there is no human safety finding, no animal reproductive-toxicity dataset in the accessible literature, and no label statement permitting use. Treat as contraindicated by default.
Dosage
There is no established human dose for kisspeptin-10, and none is recommended here. It is not an approved supplement or drug anywhere, no dose has ever been ranged against a clinical outcome, and every figure below is data reported for context, not a personal recommendation.
The published human regimens are intravenous and were run under clinical monitoring. Boluses spanned 0.01–3.0 µg/kg, with the maximal LH response at about 1 µg/kg 1,
There is no validated subcutaneous dose, and this matters more here than on most pages: with a ~4-minute half-life, the pharmacokinetics that make an IV infusion work do not carry over to a daily subcutaneous injection, and the one direct comparison available found repeated injection insufficient to reproduce sustained LH release 9Reference 9AnimalMechanistic insights into the more potent effect of KP-54 compared to KP-10 in vivo — animal (mouse; PK and BBB access)View study →. Oral dosing cannot deliver intact peptide at all. Vendor protocols circulating for “testosterone optimization” derive from marketing copy and community practice, not from dose-finding, and the desensitization data 1,
References
- George JT, et al. (2011). Kisspeptin-10 is a potent stimulator of LH and increases pulse frequency in men — human (clinical trial). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/21632807/
- George JT, et al. (2013). Exploring the pathophysiology of hypogonadism in men with type 2 diabetes: kisspeptin-10 stimulates serum testosterone and LH secretion — human (clinical study). Clinical Endocrinology (Oxford). https://pubmed.ncbi.nlm.nih.gov/23153270/
- Ullah H, et al. (2019). Age-dependent changes in the reproductive axis responsiveness to kisspeptin-10 administration in healthy men — human. Andrologia. https://pubmed.ncbi.nlm.nih.gov/30590872/
- Naveed A, et al. (2026). Dynamic modulation of LH secretion by continuous kisspeptin infusion in healthy men — human (n=3, 24-h IV infusion). Hormones (Athens). https://pubmed.ncbi.nlm.nih.gov/42230485/
- Nabi G, et al. (2018). Changes in the responsiveness of the hypothalamic-pituitary-gonadal axis to kisspeptin-10 administration during pubertal transition in boys — human. International Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/30046307/
- Millar RP, et al. (2017). Hypothalamic-pituitary-ovarian axis reactivation by kisspeptin-10 in hyperprolactinemic women with chronic amenorrhea — human (n=2, exploratory). Journal of the Endocrine Society. https://pubmed.ncbi.nlm.nih.gov/29264460/
- Skorupskaite K, et al. (2020). Kisspeptin and neurokinin B interactions in modulating gonadotropin secretion in women with polycystic ovary syndrome — human (randomised crossover). Human Reproduction. https://pubmed.ncbi.nlm.nih.gov/32510130/
- Galbiati F, et al. (2025). Sex-dependent increases in oxytocin levels in response to intravenous kisspeptin in humans — human (n=12). European Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/39965102/
- d’Anglemont de Tassigny X, et al. (2017). Mechanistic insights into the more potent effect of KP-54 compared to KP-10 in vivo — animal (mouse; PK and BBB access). PLoS One. https://pubmed.ncbi.nlm.nih.gov/28464043/
- Liu Z, et al. (2013). LC-MS/MS quantification of kisspeptin-10 (NSC 741805), characterization of its decomposition product and pharmacokinetics — animal (rat PK) / in vitro. Journal of Chromatography B. https://pubmed.ncbi.nlm.nih.gov/23524040/
- Dhillo WS, et al. (2005). Kisspeptin-54 stimulates the hypothalamic-pituitary gonadal axis in human males — human (RCT, crossover; kisspeptin-54). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/16174713/
- Jayasena CN, et al. (2014). Kisspeptin-54 triggers egg maturation in women undergoing in vitro fertilization — human (n=53; kisspeptin-54, subcutaneous). Journal of Clinical Investigation. https://pubmed.ncbi.nlm.nih.gov/25036713/
- Abbara A, et al. (2015). Efficacy of kisspeptin-54 to trigger oocyte maturation in women at high risk of ovarian hyperstimulation syndrome during IVF — human (phase 2 randomised, n=60; kisspeptin-54). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/26192876/
- Jayasena CN, et al. (2014). Increasing LH pulsatility in women with hypothalamic amenorrhoea using intravenous infusion of kisspeptin-54 — human (n=5; kisspeptin-54). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/24517142/
- Thurston L, et al. (2022). Effects of kisspeptin administration in women with hypoactive sexual desire disorder — human (RCT; kisspeptin-54). JAMA Network Open. https://pubmed.ncbi.nlm.nih.gov/36287566/
- Mills EG, et al. (2023). Effects of kisspeptin on sexual brain processing and penile tumescence in men with hypoactive sexual desire disorder — human (RCT; kisspeptin-54). JAMA Network Open. https://pubmed.ncbi.nlm.nih.gov/36735255/
- Abbara A, et al. (2020). Kisspeptin receptor agonist has therapeutic potential for female reproductive disorders — human + in vitro (MVT-602). Journal of Clinical Investigation. https://pubmed.ncbi.nlm.nih.gov/33196464/
- Abbara A, et al. (2024). Endocrine profile of the kisspeptin receptor agonist MVT-602 in healthy premenopausal women with and without ovarian stimulation — human (RCT; MVT-602). Fertility and Sterility. https://pubmed.ncbi.nlm.nih.gov/37925096/
- Mills EG, et al. (2025). Intranasal kisspeptin administration rapidly stimulates gonadotropin release in humans — human (randomised crossover; kisspeptin-54). EBioMedicine. https://pubmed.ncbi.nlm.nih.gov/40215751/
- Velmurugan H, et al. (2025). Kisspeptin and its current clinical status — a systematic review. Current Medicinal Chemistry. https://pubmed.ncbi.nlm.nih.gov/38265397/



