
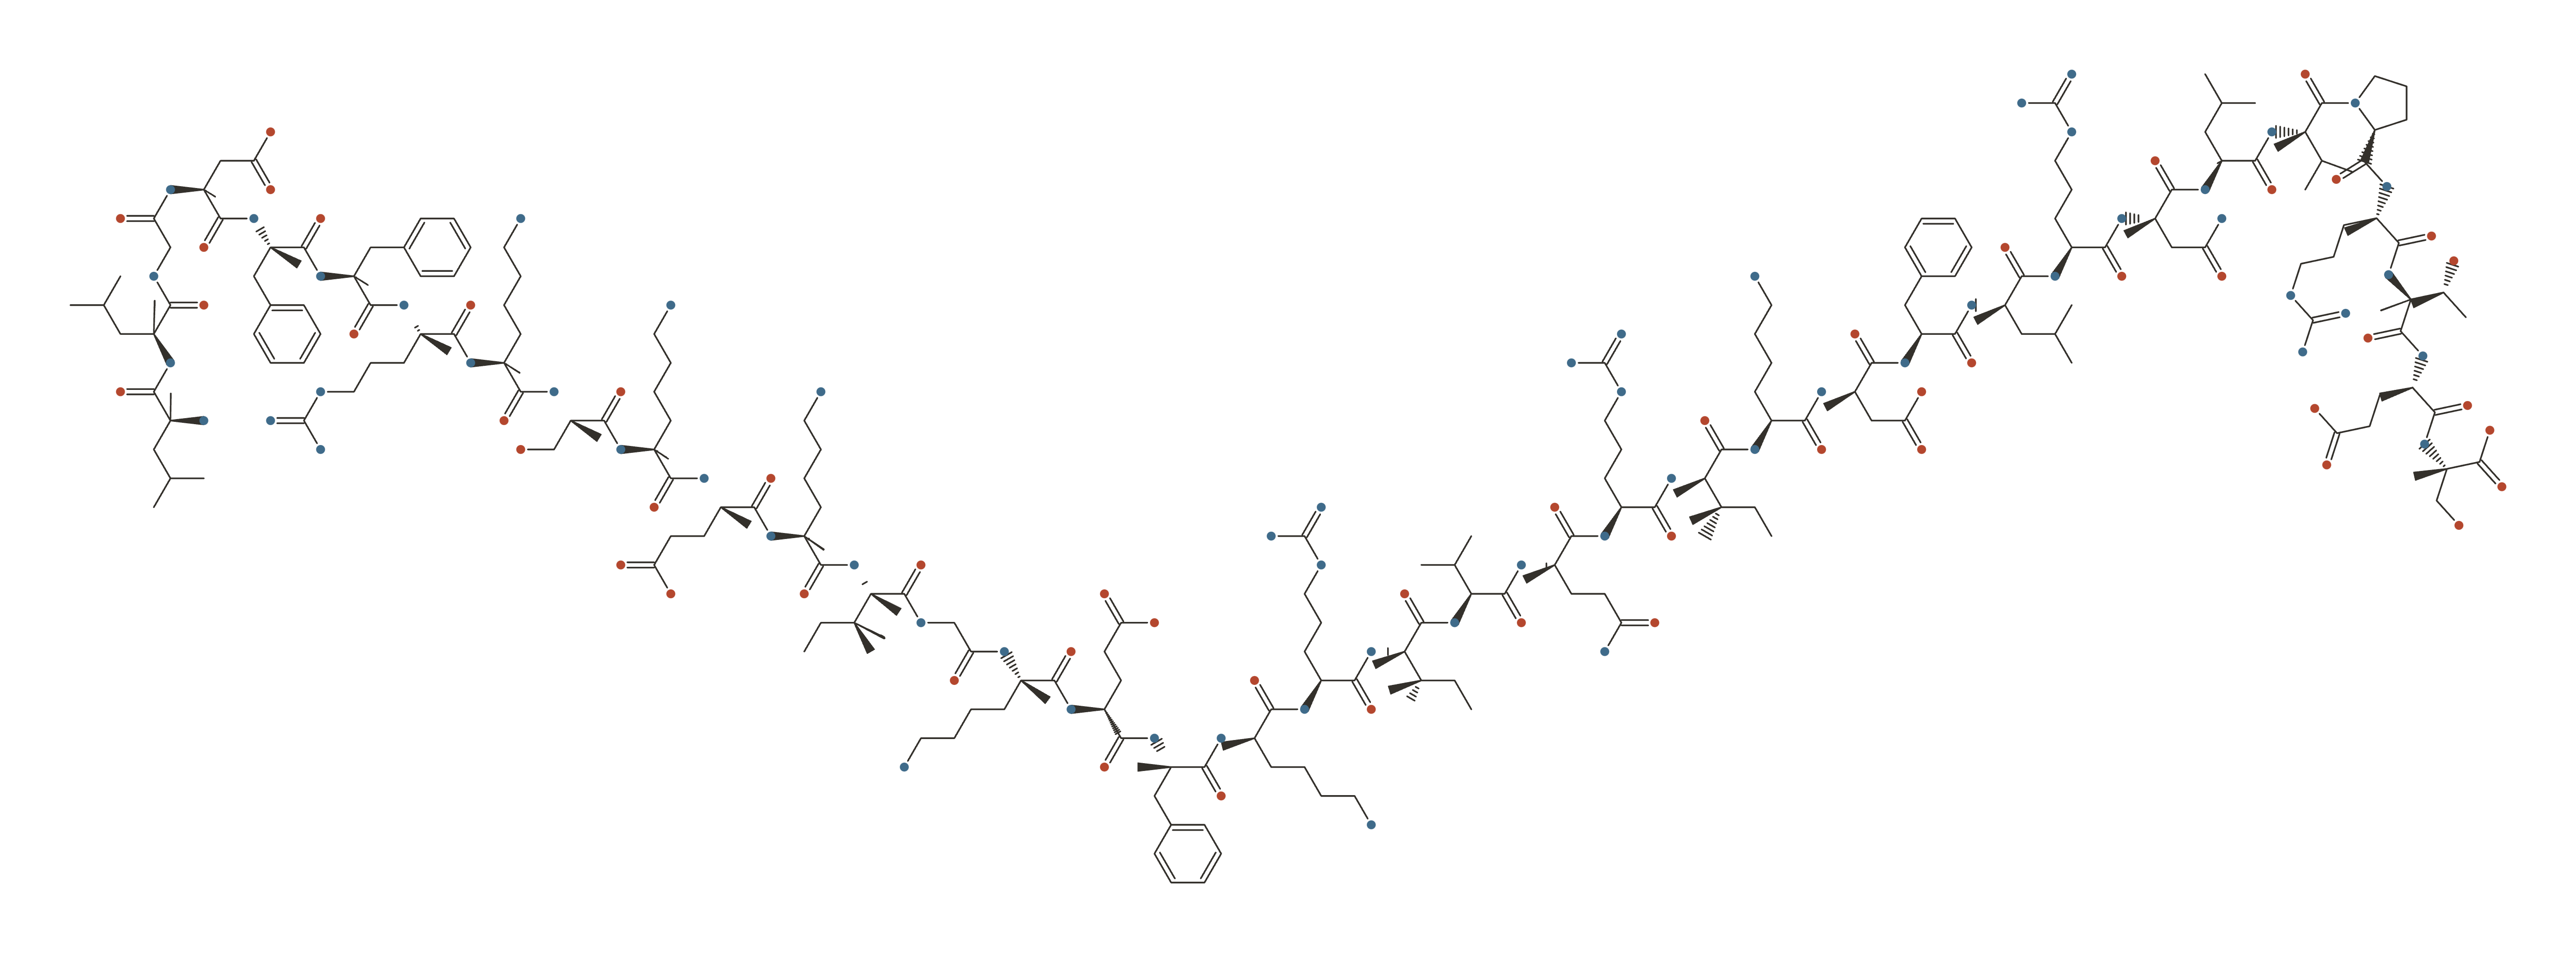
LL-37
The only human cathelicidin, a host-defense peptide studied topically for wound healing.

LL-37 at a Glance
LL-37 is the only cathelicidin humans make — a 37-amino-acid host-defence peptide released by immune cells and skin, where it kills bacteria directly and coordinates the wound-healing response. That dual role, antimicrobial and reparative at once, is what makes it interesting: it is part of innate immunity rather than a designed drug. It has been studied topically for wound healing and remains investigational, with no approved product.
History & Development
LL-37 is the only cathelicidin humans make - part of the innate immune system rather than a designed drug, and its own chemistry argues against the way it is sold.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Not established in the sources consulted for this section |
| Origin | Endogenous human host-defence peptide - the active fragment of hCAP-18, product of the CAMP gene |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Investigational - studied topically in venous leg ulcers; never approved |
Discovery
Cathelicidins are antimicrobial peptides of innate immunity, and humans have exactly one: LL-37, cleaved from the precursor hCAP-18. It kills bacteria by disrupting membranes, and it also modulates immune signalling and promotes wound repair - a defence molecule and a repair signal at once.
Because it is endogenous and broad-spectrum, it attracted interest as an antimicrobial that bacteria might struggle to resist.
Development & ownership
Human study has been topical, and specifically in venous leg ulcers, where randomised trials used LL-37 solution at 0.5-3.2 mg/mL twice weekly. The dose-response is the notable result: 0.5 mg/mL performed best, and the highest dose was no better - a non-monotonic pattern, which is characteristic of membrane-active peptides that become cytotoxic to host cells as concentration rises.
Two physiological facts argue directly against systemic use, and they are the two most useful facts about it. LL-37’s activity is inhibited by physiological salt concentrations, and it is inhibited by serum lipoproteins. Blood is salty and full of lipoproteins - so the environment a systemic dose would enter is the one in which this peptide works least well. As a small linear peptide it is also rapidly degraded by proteases.
That is why the human work is topical: applied to a wound surface, it acts where it can still act.
How it reached the market
LL-37 is sold as an injectable antimicrobial and anti-inflammatory. That route contradicts both its studied use and its own biochemistry - the only human trials are topical, and salt and serum inhibit it in exactly the compartment an injection delivers it to.
What It's Used For
LL-37 is the only cathelicidin made by humans — a 37-residue, cationic, amphipathic α-helical host-defense peptide (it takes its name from the two leading Leucines and its 37 residues) cleaved by proteases from the C-terminus of its precursor protein hCAP18 (the product of the CAMP gene) 1,
It is stored in neutrophil granules and produced by epithelial cells of the skin, gut, and airway, where it acts both as a broad-spectrum antimicrobial and, more importantly for its therapeutic interest, as an immune-signaling molecule — chemoattracting immune cells, neutralizing bacterial endotoxin, promoting angiogenesis, and driving wound closure 1,
The honest evidence posture is preclinical-dominant with a genuine but thin and mixed human wound-healing signal: LL-37 is one of the few peptides in this collection with dedicated human randomized trials, but they are all topical, small, and contradictory — two positive early trials (venous leg ulcer, diabetic foot ulcer) against one null Phase IIb 2,
Route is decisive: as a small peptide LL-37 is rapidly degraded by proteases and inactivated by serum and physiological salt, so the injected/systemic “immune-boosting” form sold online has essentially no basis — its own biology argues against it working that way 1,
It also has a double-edged nature: the same peptide implicated in host defense is a self-antigen and pro-inflammatory driver in psoriasis and lupus, and a tumor-promoter in several cancers — so “more LL-37” is not self-evidently good 10,
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. For LL-37 the ceiling is set by the fact that the human data are topical, small, and mixed and the mechanism is largely in-vitro/animal — so even the top row sits mid-scale, with the human gap and the route caveat stated out loud. Each application links down to its write-up.
This is LL-37’s best-evidenced use and the only one with dedicated human trials — all topical, and the record is genuinely mixed. A first-in-human dose-ranging RCT in hard-to-heal venous leg ulcers (n=34, twice-weekly LL-37 at 0.5/1.6/3.2 mg/mL vs placebo) reported healing-rate constants roughly six- and three-fold higher than placebo at the two lower doses (the highest dose was no better than placebo — a non-monotonic dose response), with no safety concerns 2Reference 2RCTTreatment with LL-37 is safe and effective in enhancing healing of hard-to-heal venous leg ulcers: a randomized, placebo-controlled clinical trial — RCT (human, topical)View study →.
But the pivotal Phase IIb “HEAL LL-37” trial (n=148, with compression) found no significant healing benefit in the overall population; only a post hoc subgroup of large (≥10 cm²) ulcers showed improvement, an observation that needs a properly powered confirmatory trial 3Reference 3RCTEvaluation of LL-37 in healing of hard-to-heal venous leg ulcers: a multicentric prospective randomized placebo-controlled clinical trial — RCT (human, topical; null overall)View study →.
Separately, a small diabetic foot ulcer RCT (n=40, LL-37 cream twice weekly for 4 weeks) found consistently greater granulation-tissue index in the LL-37 arm, though it did not reduce inflammatory cytokines or bacterial colonization as hypothesized 4Reference 4RCTEfficacy of LL-37 cream in enhancing healing of diabetic foot ulcer: a randomized double-blind controlled trial — RCT (human, topical)View study →.
The mechanistic basis — angiogenesis, keratinocyte migration, and re-epithelialization — is supported by endothelial and rodent work 8,
Gap: the only positive human results are small and topical; the single adequately-powered trial (Phase IIb VLU) was null overall, with benefit surviving only in an unconfirmed subgroup. There is no human data for any systemic/injected route.
LL-37 kills a broad range of Gram-positive and Gram-negative bacteria, fungi, and some enveloped viruses by disrupting microbial membranes, and this direct activity is extensively characterized in vitro 1,
It also has anti-infective activity in animals — for example protecting rats from lethal Gram-negative sepsis 16Reference 16AnimalLL-37 protects rats against lethal sepsis caused by gram-negative bacteria — rat/in vivoView study →.
The decisive limitation is pharmacological, not conceptual: LL-37’s antibacterial potency is strongly attenuated by physiological salt concentrations, divalent cations, and serum proteins, so its killing seen in dilute buffer often does not translate to body fluids — a central reason much drug-development effort focuses on engineered, salt-resistant fragments and analogues (e.g. KR-12, SAAP-148) rather than native LL-37 1,
Vitamin D is the natural inducer of endogenous LL-37, and boosting endogenous production (rather than dosing the peptide) is a distinct anti-infective strategy 17,
Gap: broad in-vitro potency and rat data, but native LL-37 is salt- and serum-inactivated, and there is no human trial of administered LL-37 as an anti-infective. This is a mechanism looking for a delivery solution.
Beyond direct killing, LL-37 binds and neutralizes bacterial endotoxin (LPS) and lipoteichoic acid, blunting macrophage over-activation — an “anti-sepsis” immunomodulatory action first characterized in human cells and monocytes in vitro 5Reference 5In vitroThe human antimicrobial peptide LL-37 is a multifunctional modulator of innate immune responses — in vitroView study →.
In vivo, LL-37 protected rats against lethal Gram-negative sepsis across several challenge models 16Reference 16AnimalLL-37 protects rats against lethal sepsis caused by gram-negative bacteria — rat/in vivoView study →.
Crucially, the picture is context-dependent: in other settings LL-37 is *pro-*inflammatory and has been reported to exacerbate sepsis-induced acute lung injury, so its net effect depends on concentration, tissue, and the inflammatory milieu 10,
Gap: Lps-neutralization is well shown in vitro and LL-37 is protective in a rat sepsis model, but the biology is double-edged (pro- vs anti-inflammatory) and there is no human interventional trial. Animal + in-vitro only.
LL-37 has a distinct, potent action against bacterial biofilms that is separate from its direct killing: at concentrations below the minimum inhibitory concentration it prevents Pseudomonas aeruginosa biofilm formation and promotes dispersal, by down-regulating quorum-sensing systems and twitching motility 6Reference 6In vitroHuman host defense peptide LL-37 prevents bacterial biofilm formation — in vitroView study →.
This has been reproduced and extended across multiple organisms and reviewed in depth 7Reference 7ReviewAntibiofilm properties of cathelicidin LL-37: an in-depth reviewView study →.
Derived/engineered peptides based on LL-37 have shown anti-biofilm effect in animal infection models 7Reference 7ReviewAntibiofilm properties of cathelicidin LL-37: an in-depth reviewView study →.
Gap: the anti-biofilm data are compelling but in vitro (with some animal work on derivatives); there is no human trial, and native LL-37 carries the same salt/serum-inactivation limitation on delivery.
LL-37 is produced by colonic epithelium and has tissue-repair and antimicrobial roles in the gut, prompting interest in inflammatory bowel disease 11,
In mouse colitis models, exogenous cathelicidin (including delivery approaches) reduced inflammation and promoted mucosal healing 11Reference 11ReviewThe roles of cathelicidin LL-37 in inflammatory bowel disease — reviewView study →.
In humans the data are observational biomarker studies: circulating and mucosal cathelicidin levels correlate with mucosal disease activity in ulcerative colitis and with stricture risk in Crohn’s disease 19Reference 19ObservationalCirculating cathelicidin levels correlate with mucosal disease activity in ulcerative colitis, risk of intestinal stricture in Crohn’s disease, and clinical prognosis in IBD — human (biomarker cohort)View study → — informative about biology, but not a test of LL-37 as a treatment.
Gap: therapeutic effect is mouse-only; human data are correlational biomarker studies, not interventional. No trial of administered LL-37 for IBD.
LL-37’s ability to recruit and activate immune cells motivated a first-in-human trial of intratumoral LL-37 injection in metastatic melanoma (MD Anderson, NCT02225366, Phase 1/2) to test whether it could stimulate an anti-tumor immune response [T2]. The trial completed with results posted on ClinicalTrials.gov, but it enrolled only 4 patients and was a dose-finding study — its primary endpoint was determining a toxicity-based optimal biological dose of LL-37, with anti-tumor immune response as a secondary endpoint [T2]. At n=4 it is far too small to establish efficacy. This application is also the clearest example of LL-37’s double-edged biology: in ovarian, lung, breast, and skin cancers LL-37 is frequently over-expressed and tumor-promoting — driving proliferation, migration, invasion, and angiogenesis — so systemic elevation could plausibly help some tumors grow 13,
Gap: the one human trial is tiny (n=4) and dose-finding (toxicity-based primary endpoint), so despite having posted results it cannot establish efficacy; the underlying biology is genuinely bidirectional (pro- vs anti-tumor by cancer type), making net therapeutic direction unknown.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Microbial membranes (electrostatic + amphipathic insertion) | permeabilization / lysis | antimicrobialanti-fungal |
| Bacterial LPS / lipoteichoic acid | binds & neutralizes endotoxin → ↓ macrophage over-activation | anti-endotoxinsepsis |
| Quorum sensing & twitching motility (P. aeruginosa) | ↓ (prevents biofilm at sub-MIC) | anti-biofilm |
| Formyl-peptide receptor FPR2/FPRL1 (on endothelium, leukocytes) | ↑ chemotaxis, ↑ angiogenesis | wound healingimmune recruitment |
| Angiogenesis via PGE2–EP3 / COX signaling | ↑ (aspirin-inhibitable in vivo) | wound healingtumor vasculature |
| Self-DNA/RNA complexing → TLR9/TLR7 activation in pDCs | ↑ type-I interferon (breaks self-tolerance) | psoriasislupus autoimmunity (adverse) |
| Wnt/β-catenin, growth-factor receptor transactivation | ↑ proliferation/migration | wound healing (benefit) & tumor growth (harm) |
| Apoptosis of host epithelial cells (serum-sensitized) | ↑ at higher concentrations | context-dependent cytotoxicity |
Pharmacokinetics
Route and stability are the most decision-relevant facts for LL-37. Endogenously it is released from hCAP18 by proteolysis (proteinase-3 in neutrophils, kallikreins in skin) and acts locally at epithelial and wound surfaces 1Reference 1ReviewLL-37, the only human member of the cathelicidin family of antimicrobial peptides — reviewView study →. As a small linear peptide it is highly susceptible to proteolytic degradation and its antimicrobial activity is markedly inhibited by physiological salt, divalent cations, and serum components — LL-37 partitions onto serum lipoproteins (e.g. apolipoprotein A-I), which both limits its free active concentration and can sensitize host cells to its cytotoxic effects 1,
Clinical & regulatory status
LL-37 is not an approved drug or dietary supplement anywhere, and the injected/systemic “research peptide” form is an unapproved research chemical (“for research use only / not for human consumption”) sold by unregulated vendors. It is not a scheduled/controlled substance. The most developed clinical program was topical LL-37 for venous leg ulcers, taken through a Phase I/II first-in-man study 2Reference 2RCTTreatment with LL-37 is safe and effective in enhancing healing of hard-to-heal venous leg ulcers: a randomized, placebo-controlled clinical trial — RCT (human, topical)View study → and a Phase IIb trial 3Reference 3RCTEvaluation of LL-37 in healing of hard-to-heal venous leg ulcers: a multicentric prospective randomized placebo-controlled clinical trial — RCT (human, topical; null overall)View study → (developed as a topical drug candidate, sometimes designated LL-37/“LL18-0409” by its developer) — but the Phase IIb was null in the overall population, and no marketing approval has followed. A separate small diabetic-foot-ulcer cream RCT was positive on granulation 4Reference 4RCTEfficacy of LL-37 cream in enhancing healing of diabetic foot ulcer: a randomized double-blind controlled trial — RCT (human, topical)View study →, and a first-in-human intratumoral melanoma Phase 1/2 (n=4) completed with results posted but was dose-finding, not powered for efficacy [T2]. The large majority of registered “LL-37” studies on ClinicalTrials.gov do not administer the peptide at all — they measure endogenous LL-37 as a biomarker (in saliva, gingival crevicular fluid, or serum, often alongside vitamin D), which is a different kind of study and not evidence of LL-37 as a therapeutic [T1, T3].
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 3human topical wound RCTs (VLU first-in-man, positive 2Reference 2RCTTreatment with LL-37 is safe and effective in enhancing healing of hard-to-heal venous leg ulcers: a randomized, placebo-controlled clinical trial — RCT (human, topical)View study →; VLU Phase IIb, null overall 3Reference 3RCTEvaluation of LL-37 in healing of hard-to-heal venous leg ulcers: a multicentric prospective randomized placebo-controlled clinical trial — RCT (human, topical; null overall)View study →; DFU cream, positive granulation 4Reference 4RCTEfficacy of LL-37 cream in enhancing healing of diabetic foot ulcer: a randomized double-blind controlled trial — RCT (human, topical)View study →) + intratumoral melanoma Phase 1/2 (n=4, dose-finding, results posted [T2]) | none administering LL-37 identified (numerous biomarker studies ongoing) | none of the administered-LL-37 trials identified as terminated | Hundreds of in-vitro / rodent studies (antimicrobial, anti-biofilm, sepsis, angiogenesis, IBD, cancer, autoimmunity) |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status — not an approved drug or supplement anywhere; injectable form is an unapproved research chemical. LL-37 has no marketing approval from the FDA, EMA, TGA, or any other major regulator, for any indication, and there is no drug or dietary-supplement monograph for it. Its most advanced legitimate development was as a topical drug candidate for venous leg ulcers, which was taken through a first-in-man study and a Phase IIb trial; the Phase IIb was null in the overall population and no approval followed. The injected/systemic “research peptide” LL-37 sold online is an unapproved research chemical, marketed “for research use only / not for human consumption,” with no regulatory oversight. LL-37 is not a DEA-controlled substance and is not, in itself, on the WADA Prohibited List — but anyone subject to anti-doping testing should verify current status, and the sourcing/safety issues below apply regardless.
How it’s supplied & administered. In legitimate research and the clinical trials, LL-37 has been used topically (as a solution or cream applied to ulcers) or, in the single oncology study, by direct intratumoral injection — never as a systemic therapeutic. The gray-market product is a lyophilized (freeze-dried) powder in vials, requiring reconstitution (typically with bacteriostatic or sterile water) and sold for subcutaneous or intramuscular injection. This is the central pharmacological problem with the injectable form: LL-37 is rapidly degraded by proteases and inactivated by the salt and serum proteins in blood, so a systemically injected dose is unlikely to reach or sustain an active free concentration — its own biology argues against the marketed route. Reconstituted peptide requires refrigeration and light protection; the powder is stored cold.
Sourcing reality (this is a safety issue, not a footnote). Essentially all injectable LL-37 comes from unregulated vendors with no manufacturing oversight. Independent testing of gray-market peptides repeatedly finds mislabeled content, under- or over-dosing, degraded peptide, and contaminants. For an injected product the specific hazards are bacterial endotoxin, microbial contamination, and residual synthesis reagents — none assessable without a genuine third-party certificate of analysis (COA) with HPLC purity and endotoxin testing. There is a particular irony worth stating: LL-37’s best-known activity is neutralizing endotoxin, but an impure vendor product injected systemically could itself carry endotoxin. Reconstitution and self-injection by non-clinicians add sterility and dosing-error risk. This page does not recommend, rank, or link any vendor; purity and identity are unverifiable in the research-chemical market.
Safety
Being a natural human peptide does not make extra LL-37 safe. Its biology is double-edged — host defense in one context, autoimmune driver and tumor promoter in another — and every scrap of human safety data is topical, so the injectable form is unstudied in the direction that matters.
- Well tolerated topically. The venous-leg-ulcer and diabetic-foot-ulcer trials raised no local safety concerns at the doses used.
- Can worsen autoimmune and inflammatory disease. A recognized autoantigen and pathogenic driver in psoriasis and lupus, and implicated in rosacea and rheumatoid arthritis.
- Tumor-promoting in several cancers. Over-expressed and pro-invasive in ovarian, lung, breast and skin cancer — a hazard for anyone with active or high-risk malignancy.
- Avoid in pregnancy and breastfeeding. Not assessed — see the box below.
- The injectable form is unstudied and unregulated. Gray-market vials carry endotoxin, contamination and dosing-error risk on top of uncharacterized pharmacology.
- The dose-response is non-monotonic. In the dose-ranging ulcer trial the highest concentration was no better than placebo while lower doses worked.
Full Safety & Interactions Detail
Overall posture. LL-37’s safety profile is dominated by two facts that set it apart from a “benign endogenous peptide” framing. First, it is context-dependent and double-edged: the same peptide that supports host defense is a pathogenic driver in inflammatory and autoimmune disease and a tumor promoter in several cancers. Second, all human safety data are topical and limited; the systemic/injectable route is entirely unstudied in humans, and the peptide’s serum inactivation and host-cell cytotoxicity make systemic dosing both implausible and uncharacterized. The topical trials reported the peptide was well tolerated locally with no safety signal at the doses used 2,
Adverse effects. Topical: generally well tolerated in the ulcer trials; local application did not raise safety concerns 2,
- Autoimmune / inflammatory disease. LL-37 complexes with self-DNA and self-RNA and activates plasmacytoid dendritic cells via TLR9/TLR7, driving type-I interferon and breaking self-tolerance — it is a recognized autoantigen and pathogenic driver in psoriasis and systemic lupus erythematosus, and is implicated in rosacea and rheumatoid arthritis 10,
14Reference 10ReviewLittle peptide, big effects: the role of LL-37 in inflammation and autoimmune disease — reviewView study →Reference 14ReviewRoles and mechanisms of human cathelicidin LL-37 in cancer — reviewView study → . Raising systemic LL-37 is therefore not self-evidently benign, especially in anyone predisposed to these conditions. - Cancer. In ovarian, lung, breast, and skin cancers LL-37 is frequently over-expressed and tumor-promoting (proliferation, migration, invasion, angiogenesis) 13,
14, — a theoretical hazard for systemic elevation.15Reference 13In vitroMyeloid cell-derived LL-37 promotes lung cancer growth by activating Wnt/β-catenin signaling — in vitro / animal / human tissueView study →Reference 14ReviewRoles and mechanisms of human cathelicidin LL-37 in cancer — reviewView study →Reference 15ReviewThe role of cathelicidin LL-37 in cancer development — reviewView study → - Host-cell cytotoxicity. At higher concentrations, and sensitized by serum, LL-37 can induce apoptosis of host epithelial cells 20Reference 20In vitroApoptosis of airway epithelial cells: human serum-sensitive induction by the cathelicidin LL-37 — in vitroView study →.
Dose-limiting effect. None formally established in humans (no systemic dose-finding trial). Notably, in the venous-ulcer dose-ranging trial the highest dose (3.2 mg/mL) was no better than placebo while lower doses worked — a non-monotonic dose-response consistent with higher concentrations tipping toward host-cytotoxic/pro-inflammatory effects 2Reference 2RCTTreatment with LL-37 is safe and effective in enhancing healing of hard-to-heal venous leg ulcers: a randomized, placebo-controlled clinical trial — RCT (human, topical)View study →.
Interactions. No human interaction studies. Mechanistic flags: LL-37’s pro-angiogenic action is COX/PGE2-dependent and inhibitable by aspirin in vivo 8Reference 8In vitroCathelicidin LL-37 induces angiogenesis via PGE2-EP3 signaling in endothelial cells, in vivo inhibition by aspirin — in vitro / in vivoView study →, so NSAIDs could blunt a wound-healing effect; and its biology intersects with vitamin D, the natural inducer of endogenous LL-37 17,
Injection-specific risks. For the research-peptide route: non-sterile technique, contamination/endotoxin from impure product, injection-site reaction/infection, and dosing error — often larger real-world hazards than the peptide’s own pharmacology.
Who should avoid it (systemic form). Anyone with psoriasis, lupus, rosacea, rheumatoid arthritis, or another autoimmune/inflammatory condition (LL-37 can worsen these); anyone with active or high-risk malignancy (tumor-promotion concern); pregnant or breastfeeding individuals; and anyone considering the injectable form outside a supervised clinical trial. The conservative position is that the systemic/injectable form should not be self-administered given the absence of human data and the plausible harm directions.
Scope disclosure (not a claim):
- Human data? Topical only, and mixed — three topical wound RCTs (two small positive, one Phase IIb null overall) plus a 4-patient intratumoral melanoma dose-finding study (results posted, but n=4 and toxicity-based primary endpoint — not an efficacy read-out). No human study of the injectable/systemic form.
- Interactions assessed? No in humans; only mechanistic flags (aspirin/NSAIDs via COX–PGE2; vitamin D as the endogenous inducer).
- Pregnancy/lactation assessed? No — not established; avoid the systemic form.
- Long-term safety established? No. No long-term human data for administered LL-37 by any route; the topical trials were weeks long. Do not infer systemic safety from the fact that LL-37 is endogenous — the context-dependent pro-inflammatory and pro-tumor biology is the reason.
Never imply safety from silence. LL-37 being a natural human peptide does not make dosing extra LL-37 safe — its own biology is double-edged, and the systemic route is unstudied. For that route the honest statement is “not assessed.”
Not assessed / not established. There are no human pregnancy or lactation data for administered LL-37 and no adequate reproductive-safety studies; the injectable/systemic form should be avoided in pregnancy and breastfeeding.
Dosage
There is no established human dose for LL-37, and none is recommended here. It is not an approved supplement or drug, and every figure below is trial data reported for context, not a personal recommendation — do not read it as a protocol.
All human dosing to date has been topical. In the first-in-human venous-leg-ulcer dose-ranging RCT, LL-37 solution was applied twice weekly at 0.5, 1.6, or 3.2 mg/mL; the lowest dose (0.5 mg/mL) performed best and the highest (3.2 mg/mL) was no better than placebo — a non-monotonic response, so “more” was not better 2Reference 2RCTTreatment with LL-37 is safe and effective in enhancing healing of hard-to-heal venous leg ulcers: a randomized, placebo-controlled clinical trial — RCT (human, topical)View study →. The Phase IIb venous-ulcer trial (with compression) found no overall benefit at the doses tested 3Reference 3RCTEvaluation of LL-37 in healing of hard-to-heal venous leg ulcers: a multicentric prospective randomized placebo-controlled clinical trial — RCT (human, topical; null overall)View study →. A diabetic-foot-ulcer trial applied an LL-37 cream twice weekly for 4 weeks 4Reference 4RCTEfficacy of LL-37 cream in enhancing healing of diabetic foot ulcer: a randomized double-blind controlled trial — RCT (human, topical)View study →. The single oncology study used intratumoral injection in a 4-patient dose-finding design whose entire purpose was to identify a toxicity-based optimal biological dose — i.e. no established dose existed to begin with [T2].
There is no validated systemic or injectable human dose. The gray-market “research peptide” circulates as a lyophilized powder with vendor-suggested reconstitution and injection amounts, but these are not derived from any human trial, and — given LL-37’s serum/salt inactivation and its double-edged biology — the systemic route has neither an efficacy nor a safety basis (see Sourcing, Route & Legal Status and Safety). This entry is informational only.
References
- Dürr UHN, Sudheendra US, Ramamoorthy A (2006). LL-37, the only human member of the cathelicidin family of antimicrobial peptides — review. Biochim Biophys Acta. https://pubmed.ncbi.nlm.nih.gov/16716248/
- Grönberg A, Mahlapuu M, Ståhle M, Whately-Smith C, Rollman O (2014). Treatment with LL-37 is safe and effective in enhancing healing of hard-to-heal venous leg ulcers: a randomized, placebo-controlled clinical trial — RCT (human, topical). Wound Repair Regen. https://pubmed.ncbi.nlm.nih.gov/25041740/
- Mahlapuu M, Sidorowicz A, Mikosinski J, et al. (2021). Evaluation of LL-37 in healing of hard-to-heal venous leg ulcers: a multicentric prospective randomized placebo-controlled clinical trial — RCT (human, topical; null overall). Wound Repair Regen. https://pubmed.ncbi.nlm.nih.gov/34687253/
- Miranda E, Bramono K, Yunir E, et al. (2023). Efficacy of LL-37 cream in enhancing healing of diabetic foot ulcer: a randomized double-blind controlled trial — RCT (human, topical). Arch Dermatol Res. https://pubmed.ncbi.nlm.nih.gov/37480520/
- Scott MG, Davidson DJ, Gold MR, Bowdish D, Hancock REW (2002). The human antimicrobial peptide LL-37 is a multifunctional modulator of innate immune responses — in vitro. J Immunol. https://pubmed.ncbi.nlm.nih.gov/12244186/
- Overhage J, Campisano A, Bains M, et al. (2008). Human host defense peptide LL-37 prevents bacterial biofilm formation — in vitro. Infect Immun. https://pubmed.ncbi.nlm.nih.gov/18591225/
- Memariani H, Memariani M (2023). Antibiofilm properties of cathelicidin LL-37: an in-depth review. World J Microbiol Biotechnol. https://pubmed.ncbi.nlm.nih.gov/36781570/
- Salvado MD, Di Gennaro A, Lindbom L, Agerberth B, Haeggström JZ (2013). Cathelicidin LL-37 induces angiogenesis via PGE2-EP3 signaling in endothelial cells, in vivo inhibition by aspirin — in vitro / in vivo. Arterioscler Thromb Vasc Biol. https://pubmed.ncbi.nlm.nih.gov/23766266/
- Koczulla R, von Degenfeld G, Kupatt C, et al. (2003). An angiogenic role for the human peptide antibiotic LL-37/hCAP-18 — in vitro / animal. J Clin Invest. https://pubmed.ncbi.nlm.nih.gov/12782669/
- Kahlenberg JM, Kaplan MJ (2013). Little peptide, big effects: the role of LL-37 in inflammation and autoimmune disease — review. J Immunol. https://pubmed.ncbi.nlm.nih.gov/24185823/
- Sun L, Wang W, Xiao W, Yang H (2016). The roles of cathelicidin LL-37 in inflammatory bowel disease — review. Inflamm Bowel Dis. https://pubmed.ncbi.nlm.nih.gov/27135484/
- Bhattacharjya S, Zhang Z, Ramamoorthy A (2024). LL-37: structures, antimicrobial activity, and influence on amyloid-related diseases — review. Biomolecules. https://pubmed.ncbi.nlm.nih.gov/38540740/
- Ji P, Zhou Y, Yang Y, et al. (2019). Myeloid cell-derived LL-37 promotes lung cancer growth by activating Wnt/β-catenin signaling — in vitro / animal / human tissue. Theranostics. https://pubmed.ncbi.nlm.nih.gov/31149039/
- Chen X, Zou X, Qi G, et al. (2018). Roles and mechanisms of human cathelicidin LL-37 in cancer — review. Cell Physiol Biochem. https://pubmed.ncbi.nlm.nih.gov/29843147/
- Piktel E, Niemirowicz K, Wnorowska U, et al. (2016). The role of cathelicidin LL-37 in cancer development — review. Arch Immunol Ther Exp (Warsz). https://pubmed.ncbi.nlm.nih.gov/26395996/
- Cirioni O, Giacometti A, Ghiselli R, et al. (2006). LL-37 protects rats against lethal sepsis caused by gram-negative bacteria — rat/in vivo. Antimicrob Agents Chemother. https://pubmed.ncbi.nlm.nih.gov/16641434/
- Martineau AR, Wilkinson KA, Newton SM, et al. (2007). IFN-γ- and TNF-independent vitamin D-inducible human suppression of mycobacteria: the role of cathelicidin LL-37 — in vitro (human cells). J Immunol. https://pubmed.ncbi.nlm.nih.gov/17513768/
- van der Does AM, Bergman P, Agerberth B, Lindbom L (2012). Induction of the human cathelicidin LL-37 as a novel treatment against bacterial infections — review. J Leukoc Biol. https://pubmed.ncbi.nlm.nih.gov/22701042/
- Tran DHY, Wang J, Ha C, et al. (2017). Circulating cathelicidin levels correlate with mucosal disease activity in ulcerative colitis, risk of intestinal stricture in Crohn’s disease, and clinical prognosis in IBD — human (biomarker cohort). BMC Gastroenterol. https://pubmed.ncbi.nlm.nih.gov/28494754/
- Lau YE, Bowdish DME, Cosseau C, Hancock REW, Davidson DJ (2006). Apoptosis of airway epithelial cells: human serum-sensitive induction by the cathelicidin LL-37 — in vitro. Am J Respir Cell Mol Biol. https://pubmed.ncbi.nlm.nih.gov/16340000/
- Memariani H, Memariani M (2023). Antifungal properties of cathelicidin LL-37: current knowledge and future research directions — review. World J Microbiol Biotechnol. https://pubmed.ncbi.nlm.nih.gov/38057654/
- Miao S, Liu H, Yang Q, et al. (2024). Cathelicidin peptide LL-37: a multifunctional peptide involved in heart disease — review. Pharmacol Res. https://pubmed.ncbi.nlm.nih.gov/39615616/
Registered trials (ClinicalTrials.gov)
- T1. NCT04098562 — Efficacy of LL-37 Cream on aerobic bacteria colonization and inflammation in diabetic foot ulcer (Phase 2, n=40; results published as Miranda 2023 4Reference 4RCTEfficacy of LL-37 cream in enhancing healing of diabetic foot ulcer: a randomized double-blind controlled trial — RCT (human, topical)View study →). https://clinicaltrials.gov/study/NCT04098562
- T2. NCT02225366 — Induction of antitumor response in melanoma patients using the antimicrobial peptide LL37 (intratumoral, Phase 1/2, n=4, completed, results posted on ClinicalTrials.gov; dose-finding — primary endpoint was a toxicity-based optimal biological dose, anti-tumour immune response secondary; MD Anderson Cancer Center). https://clinicaltrials.gov/study/NCT02225366
- T3. Representative biomarker studies measuring endogenous LL-37 (not administering it): NCT03923218, NCT04861493 (gingival crevicular fluid / saliva vs vitamin D). https://clinicaltrials.gov/study/NCT03923218



