
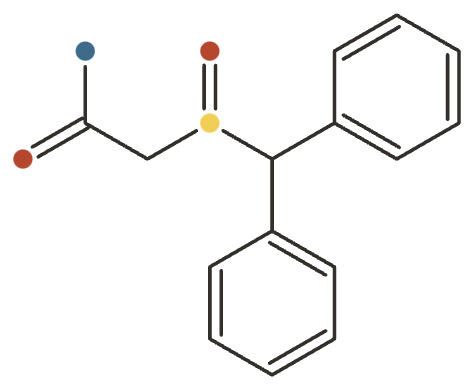
Modafinil
A prescription wakefulness-promoting agent (eugeroic) for narcolepsy, shift-work sleep disorder and residual sleepiness in treated sleep apnoea — widely used off-label for focus.

Modafinil at a Glance
Modafinil is a synthetic benzhydryl-sulfinyl eugeroic — a wakefulness-promoting agent — approved for excessive sleepiness in narcolepsy, obstructive sleep apnoea and shift-work sleep disorder. It is a prescription-only medicine, not a supplement, and what follows is informational rather than a guide to obtaining it.
It has no dietary source. It emerged from work on adrafinil, a wakefulness compound developed in France in the 1970s by Lafon Laboratories; adrafinil is a prodrug that the body converts into modafinil (the active part) plus inactive modafinilic acid. Once researchers recognised the metabolite carried the activity, they developed it directly, and it reached market as Provigil. The longer-acting R-enantiomer was later marketed separately as armodafinil (Nuvigil).
The framing that makes the evidence legible: modafinil counteracts a sleepiness deficit; it does not add cognitive capacity to a rested brain. That single distinction separates its strong evidence from its weak evidence. Where someone is pathologically or situationally sleepy, it works well and reliably. Where someone is already rested, the gains are small, task-specific, and sometimes come at the cost of accuracy.
The honest bottom line: excellent for the approved sleep-disorder indications, genuinely useful during acute sleep deprivation, and considerably oversold as a study drug. It also carries two risks that get lost in the “safer than amphetamine” framing — rare but serious skin reactions, and a signal for congenital malformations in pregnancy.
What It’s Used For
Ranked by how well the evidence actually holds up:
- Narcolepsy — the strongest indication, from a 9-RCT meta-analysis. Note it does not reduce cataplexy.
- Shift-work sleep disorder — a pivotal NEJM trial; real but modest, and most treated workers remained sleepy.
- Residual sleepiness in treated sleep apnoea — an adjunct to CPAP, never a substitute for it.
- Sleep-deprivation alertness — the best-replicated “cognitive” use, and it is restoration rather than enhancement.
- Depression, as an adjunct — a modest signal, mainly for the fatigue dimension of bipolar depression.
- Cognitive enhancement in healthy adults — the popular off-label use, and much weaker than its reputation.
Two claims deserve to be named as off-label and not established, because older write-ups here listed them as though they were indications: ADHD (positive paediatric trials exist, but it is not first-line, and the FDA declined approval after serious rash cases) and chronic fatigue syndrome. Two more are honest failures worth knowing: cancer-related fatigue was negative in a Phase III trial except in the most severely fatigued, and cocaine dependence was null in meta-analysis.
New to this class of compound? Start with What Are Nootropics?.
How It Works
Modafinil promotes wakefulness without the profile of an amphetamine, but the mechanistic gap between them is narrower than the marketing implies.
It inhibits dopamine reuptake at the dopamine transporter, and human PET imaging confirmed that it occupies DAT and raises extracellular dopamine in the living brain at therapeutic doses 16Reference 16Effects of modafinil on dopamine and dopamine transporters in the male human brainView study →. That finding mattered clinically, because it established that modafinil shares a pathway with classic stimulants even though it does not share their subjective punch or their abuse profile. It also inhibits the norepinephrine transporter, raising cortical catecholamines.
Above the transporter level, it acts on the brain’s actual wake circuitry: modafinil activates hypothalamic arousal regions, including orexin/hypocretin and histaminergic neurons in the tuberomammillary nucleus 17Reference 17Hypothalamic arousal regions are activated during modafinil-induced wakefulness — animal studyView study →. This is what makes it a eugeroic rather than a general stimulant — it engages the systems that normally hold you awake, instead of simply flooding the synapse.
The net effect is a shift toward excitation (increased glutamate, decreased GABA) in cortex and thalamus, sustained over many hours by the long half-life.
Pharmacology & Research
Modafinil is a synthetic benzhydryl-sulfinyl eugeroic (wakefulness-promoting agent) — the active R/S metabolite of the older prodrug adrafinil — approved for excessive sleepiness in narcolepsy, obstructive sleep apnoea and shift-work sleep disorder. Its evidence base is genuinely strong for one thing: restoring alertness in people who are pathologically or situationally sleepy. The picture is much weaker for the reason most people buy it off-label — “smarter” cognition in rested, healthy adults — where effects are small, task-dependent, and easy to overstate. Because there is no intravenous formulation its absolute bioavailability is unknown, but oral absorption is high and the ~13–15 h half-life is what makes it a once-daily morning drug. Throughout, keep the eugeroic framing in mind: modafinil reliably counteracts a sleepiness deficit; it does not reliably add cognitive capacity on top of an already-rested baseline.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
A systematic review and meta-analysis of 9 RCTs (n≈1,054) found modafinil significantly reduced excessive daytime sleepiness versus placebo: Epworth Sleepiness Scale weighted mean difference −2.73 points (95% CI −3.39 to −2.08), with parallel gains on objective Multiple Sleep Latency and Maintenance of Wakefulness tests, plus improved quality of life 1Reference 1Meta-analysisModafinil for narcolepsy: systematic review and meta-analysisView study →.
American Academy of Sleep Medicine guidance lists modafinil among recommended agents for the central hypersomnolence disorders 2Reference 2Meta-analysisTreatment of central disorders of hypersomnolence: an American Academy of Sleep Medicine systematic review, meta-analysis, and GRADE assessmentView study →.
Note the ceiling: modafinil did not reduce cataplexy attacks 1Reference 1Meta-analysisModafinil for narcolepsy: systematic review and meta-analysisView study → — that symptom needs different treatment.
Gap: Benefit is for the sleepiness of a diagnosed disorder; effects on alertness are consistent but comparative (versus newer agents such as solriamfetol/pitolisant) matter for choice.
The pivotal 3-month, double-blind RCT (n=209) randomised night-shift workers to 200 mg modafinil or placebo before each shift. Modafinil produced a statistically significant but modest improvement in nighttime sleep latency and in clinician-rated global functioning, and reduced (without eliminating) lapses of attention during the commute home 3Reference 3RCTModafinil for excessive sleepiness associated with shift-work sleep disorder — randomised controlled trialView study →.
Many treated patients remained excessively sleepy — the drug narrows the deficit rather than closing it.
Gap: Real but small effect; behavioural measures (scheduled naps, light exposure, limiting shift rotation) remain first-line and modafinil is an add-on.
Meta-analyses of RCTs show modafinil and armodafinil improve residual excessive sleepiness (Epworth and Maintenance of Wakefulness measures) in OSA patients who remain sleepy despite adequate CPAP therapy 4Reference 4Meta-analysisEffects of modafinil and armodafinil in patients with obstructive sleep apnea: a meta-analysis of randomized controlled trialsView study →, and a 2025 network meta-analysis of wake-promoting agents ranks it among effective options for this indication 5Reference 5Meta-analysisComparative efficacy and safety of multiple wake-promoting agents for the treatment of residual excessive daytime sleepiness — network meta-analysisView study →.
Gap: It treats the symptom of residual sleepiness and must not be used as a substitute for CPAP — it does nothing for the underlying airway obstruction or cardiovascular risk. Regulators have restricted the OSA indication in some regions over benefit–risk concerns.
In acutely sleep-deprived healthy adults (the military/shift context modafinil was studied for), RCTs consistently show it sustains vigilance, reaction time and subjective alertness better than placebo, comparable to amphetamine but with a smoother profile 6Reference 6ReviewEffects of modafinil on cognitive performance and alertness during sleep deprivation — reviewView study →. This is the best-replicated “cognitive” use — but it is restoring performance eroded by sleep loss, not enhancing a rested baseline.
Gap: Benefits are largest when the deficit is largest; as rest is restored the advantage shrinks, and it does not substitute for sleep.
Meta-analyses of adjunctive modafinil/armodafinil report a modest improvement in response and remission when added to standard antidepressants, with the clearest signal in bipolar depression (5 RCTs, ~1,587 patients) 10Reference 10Meta-analysisEfficacy and tolerability of adjunctive modafinil/armodafinil in bipolar depression: a meta-analysis of randomized controlled trialsView study → and a broader unipolar-plus-bipolar analysis also favouring augmentation, particularly for the fatigue and sleepiness dimensions of depression 11Reference 11Meta-analysisModafinil augmentation therapy in unipolar and bipolar depression: a systematic review and meta-analysisView study →.
Gap: Effect sizes are small, it is an add-on rather than a primary antidepressant, and use in bipolar disorder carries a theoretical mood-switch caution.
This is the popular off-label use, and the evidence is mixed. A systematic review concluded modafinil can improve performance on complex, higher-order executive tasks in non-sleep-deprived people while showing little benefit on simple tasks 7Reference 7Systematic reviewModafinil for cognitive neuroenhancement in healthy non-sleep-deprived subjects: a systematic reviewView study →.
A later series of meta-analyses (k=14 modafinil studies) found effects that were small, inconsistent across cognitive domains, and in some cases came with a speed–accuracy trade-off 8Reference 8Meta-analysisHow effective are pharmaceuticals for cognitive enhancement in healthy adults? A series of meta-analysesView study →.
A controlled RCT found attentional gains only at doses that did not cause hyperarousal 9Reference 9RCTModafinil improves attentional performance in healthy, non-sleep deprived humans at doses not inducing hyperarousal across species — randomised controlled trialView study →.
Gap: No reliable across-the-board “smart drug” effect in rested people — benefits are task-specific, small, and partly explained by increased motivation/wakefulness rather than raw cognitive capacity.
Placebo-controlled paediatric RCTs showed modafinil improved ADHD rating-scale scores, but it is not a first-line ADHD medication and network meta-analyses of ADHD pharmacotherapy do not position it alongside stimulants/atomoxetine for routine use 12Reference 12Meta-analysisComparative efficacy and tolerability of medications for attention-deficit hyperactivity disorder: a systematic review and network meta-analysisView study →. The FDA declined approval for paediatric ADHD after cases of serious rash including Stevens–Johnson syndrome emerged in trials.
Gap: Efficacy signal exists but is outweighed by the skin-reaction risk in children and the availability of better-established agents; off-label only.
Despite a plausible dopaminergic rationale, a systematic review and meta-analysis of RCTs found modafinil did not significantly increase cocaine abstinence overall 13Reference 13Meta-analysisModafinil treatment of cocaine dependence: a systematic review and meta-analysisView study →, consistent with the large NIDA multi-site RCT (n=210) that showed no significant difference versus placebo in cocaine non-use days for the total sample 14Reference 14RCTModafinil for the treatment of cocaine dependence — randomised controlled trialView study →. Some analyses hint at benefit in specific subgroups (e.g. those without co-occurring alcohol dependence).
Gap: Overall null; not an approved or reliable treatment for stimulant use disorder.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Dopamine transporter (DAT) | Blocks reuptake → ↑ synaptic dopamine (confirmed in human brain by PET) 16Reference 16Effects of modafinil on dopamine and dopamine transporters in the male human brainView study → | Wakefulnessalertnessabuse-liability questions |
| Norepinephrine transporter (NET) | Reuptake inhibition → ↑ cortical catecholamines | Alertnessattention |
| Hypothalamic wake circuitry (orexin/hypocretin & histamine neurons; TMN) | Activates arousal-promoting regions 17Reference 17Hypothalamic arousal regions are activated during modafinil-induced wakefulness — animal studyView study → | Sleep–wake regulationeugeroic action |
| Glutamate ↑ / GABA ↓ (indirect) | Net excitatory shift in cortex/thalamus | Sustained wakefulness |
Human PET work established that modafinil occupies the dopamine transporter and raises extracellular dopamine at therapeutic doses 16Reference 16Effects of modafinil on dopamine and dopamine transporters in the male human brainView study → — clinically important because it reframed the drug as sharing a mechanistic pathway (though not the profile) with classic stimulants. Its wakefulness effect maps onto activation of hypothalamic arousal regions 17Reference 17Hypothalamic arousal regions are activated during modafinil-induced wakefulness — animal studyView study →.
Pharmacokinetics
Oral absorption is high (no intravenous form exists, so absolute bioavailability is formally unknown); peak plasma at ~2–4 h, delayed but not reduced by food. Racemic modafinil has a terminal half-life of roughly 13–15 h, supporting once-daily morning dosing; the R-enantiomer (armodafinil) is longer-lived, which is why it is marketed separately. Clearance is mainly hepatic — amide hydrolysis to the inactive modafinilic acid plus CYP-mediated routes. Critically, modafinil is a CYP3A4 inducer and a CYP2C19 inhibitor: induction of CYP3A4 lowers plasma levels of ethinyl-estradiol, which is the mechanism behind reduced hormonal-contraceptive efficacy 18Reference 18RCTEffect of modafinil on the pharmacokinetics of ethinyl estradiol and triazolam in healthy volunteers — randomised controlled trialView study →.
Clinical trials
Modafinil has an extensive completed-trial record across its approved sleep indications and numerous off-label areas (cognition, depression, ADHD, substance use, cancer/MS fatigue); as an off-patent molecule, industry-sponsored new trials have slowed, with more recent activity centred on comparative/network meta-analyses and newer wake-promoting competitors.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| 100+ | Few(mostly investigator-led / comparative) | Several | Extensive |
Last checked: August 2026.
Dietary Sources
Not applicable — modafinil is a fully synthetic pharmaceutical, not a nutrient. It does not occur in food or in the human body, and has no dietary source, no recommended intake, and no deficiency state.
How it’s made and where it came from: modafinil emerged from research on adrafinil, a wakefulness-promoting compound developed in France in the 1970s at Lafon Laboratories. Adrafinil is a prodrug — once absorbed it is metabolised to modafinil (the active fraction) plus inactive modafinilic acid. Recognising that modafinil carried the activity, the developers advanced the metabolite itself, which reached market as Provigil (Cephalon). The single longer-acting R-enantiomer was later marketed as armodafinil (Nuvigil). All three are manufactured synthetically; there is no plant or food origin.
Dosage
These are doses used in clinical prescribing, not a personal recommendation. Modafinil is a prescription-only medicine and dosing is a clinician’s decision.
- Standard clinical dose: 200 mg once daily, taken in the morning (for shift work, about an hour before the shift). Because of the ~13–15 h half-life, later dosing causes insomnia.
- Range: 100–400 mg/day. Trials show 400 mg offers little additional benefit over 200 mg while increasing side effects, so 200 mg is the usual target; 100 mg is used for dose-sensitive or older patients.
- Armodafinil (the R-enantiomer) is dosed lower, 150–250 mg, because it is longer-acting.
- No RDA, AI or Upper Limit exists — this is not a nutrient. “Intake” here means a prescribed dose individualised by a clinician, not a supplement serving.
- Food: can be taken with or without; food delays but does not reduce absorption.
Safety
Modafinil is generally better tolerated than amphetamine-type stimulants, but it is a scheduled prescription medicine with real risks — and two of them are routinely left out of the “safer stimulant” framing.
- Headache is the most common effect, along with insomnia, anxiety, nausea, dry mouth and reduced appetite. Headache and insomnia are the usual reasons to lower the dose or take it earlier.
- Rare but serious skin and hypersensitivity reactions — Stevens–Johnson syndrome, toxic epidermal necrolysis and DRESS. Any rash warrants stopping immediately and seeking medical review.
- Reduces hormonal contraceptive efficacy by inducing CYP3A4 and lowering ethinyl-estradiol — during use and for about a month after stopping 18Reference 18RCTEffect of modafinil on the pharmacokinetics of ethinyl estradiol and triazolam in healthy volunteers — randomised controlled trialView study →.
- Avoid in pregnancy. Registry and cohort data raised a congenital-malformation signal, prompting regulatory warnings.
- CYP2C19 inhibition can raise levels of some SSRIs, tricyclics, diazepam, phenytoin and omeprazole.
- Cardiovascular and psychiatric caution. Modest rises in heart rate and blood pressure; anxiety, agitation and rarely mania or psychosis in predisposed people.
Full Safety & Interactions Detail
- Common adverse effects: headache (the most frequent), insomnia, anxiety/nervousness, nausea, dry mouth, reduced appetite, dizziness. Headache and insomnia are the usual dose-limiting effects.
- Rare but serious: severe skin and hypersensitivity reactions — Stevens–Johnson syndrome, toxic epidermal necrolysis and DRESS — have been reported, and led the FDA to decline a paediatric ADHD indication. Psychiatric effects (anxiety, agitation, rarely mania or psychosis, especially in predisposed individuals) can occur.
- Cardiovascular: modest increases in heart rate and blood pressure; caution in uncontrolled hypertension, arrhythmia, or a history of left-ventricular hypertrophy or mitral-valve prolapse with prior stimulant use.
Interactions by class:
- Hormonal contraceptives — modafinil induces CYP3A4 and lowers ethinyl-estradiol levels, reducing contraceptive efficacy; alternative or additional contraception is advised during use and for about a month after stopping 18Reference 18RCTEffect of modafinil on the pharmacokinetics of ethinyl estradiol and triazolam in healthy volunteers — randomised controlled trialView study →.
- CYP2C19 substrates (some SSRIs, tricyclics, diazepam, phenytoin, omeprazole) — modafinil inhibits CYP2C19, potentially raising their levels.
- CYP3A4 substrates (ciclosporin, some statins, midazolam) may fall via induction.
- Warfarin — monitor INR when starting or stopping.
- Other stimulants and psychotropics (SSRIs, SNRIs, tricyclics, MAOIs) — combining increases the risk of overstimulation and blood-pressure effects; combination with MAOIs is generally avoided.
Who should be cautious: anyone with cardiovascular disease, a psychiatric history (anxiety, bipolar disorder, psychosis), or hepatic impairment (dose reduction is needed in severe liver disease). Modafinil has recognised misuse and dependence potential — lower than classic stimulants, but not absent — and obtaining it off-label without a prescription removes exactly the medical oversight its risk profile requires.
Scope disclosure. Interactions assessed? Yes — CYP3A4 induction (contraceptives, ciclosporin, statins), CYP2C19 inhibition (SSRIs, TCAs, diazepam, phenytoin), warfarin, and co-stimulant/psychotropic combinations reviewed. Pregnancy/lactation assessed? Yes — a congenital-malformation signal with regulatory advice to avoid; lactation data limited. Upper limit established? No UL — not a nutrient; 400 mg/day is the practical clinical ceiling with no efficacy gain over 200 mg. Where data are thin — long-term off-label use in healthy people, lactation — the honest answer is “not adequately studied,” not “safe.”
Avoid unless clearly necessary and directed by a clinician. Pregnancy-registry and cohort data have raised concern about an increased risk of congenital malformations with in-utero modafinil or armodafinil exposure, prompting regulatory warnings (EMA and others) against use in pregnancy. Modafinil also reduces the reliability of hormonal contraception, so effective non-hormonal contraception matters for anyone who could become pregnant. Excretion into breast milk is not well characterised, so caution is advised during breastfeeding.
Related molecules. Armodafinil is the longer-acting R-enantiomer (Nuvigil) — a distinct molecule, not a form of modafinil. Adrafinil is the prodrug the body converts into modafinil, and the historical parent of the whole family; modafinilic acid is the inactive co-metabolite. For context in sleep-disorder treatment, the comparator agents are methylphenidate and amphetamine among the classic stimulants, and solriamfetol and pitolisant among the newer eugeroics.
Modafinil is generally used on its own under medical supervision. Stacking it with other stimulants raises side-effect risk without an established benefit.
References
- Golicki D, Bala MM, Niewada M, Wierzbicka A. (2010). Modafinil for narcolepsy: systematic review and meta-analysis. Medical Science Monitor, 16(8), RA177-86. https://pubmed.ncbi.nlm.nih.gov/20671626/
- Maski K, Trotti LM, Kotagal S, et al. (2021). Treatment of central disorders of hypersomnolence: an American Academy of Sleep Medicine systematic review, meta-analysis, and GRADE assessment. Journal of Clinical Sleep Medicine, 17(9), 1895-1945. https://pubmed.ncbi.nlm.nih.gov/34743790/
- Czeisler CA, Walsh JK, Roth T, et al. (2005). Modafinil for excessive sleepiness associated with shift-work sleep disorder — randomised controlled trial. New England Journal of Medicine, 353(5), 476-486. https://pubmed.ncbi.nlm.nih.gov/16079371/
- Kuan YC, Wu D, Huang KW, et al. (2016). Effects of modafinil and armodafinil in patients with obstructive sleep apnea: a meta-analysis of randomized controlled trials. Clinical Therapeutics, 38(4), 874-888. https://pubmed.ncbi.nlm.nih.gov/26923035/
- Tanayapong P, et al. (2025). Comparative efficacy and safety of multiple wake-promoting agents for the treatment of residual excessive daytime sleepiness — network meta-analysis. CNS Drugs, 39. https://pubmed.ncbi.nlm.nih.gov/40208562/
- Wesensten NJ. (2006). Effects of modafinil on cognitive performance and alertness during sleep deprivation — review. Current Pharmaceutical Design, 12(20), 2457-2471. https://pubmed.ncbi.nlm.nih.gov/16842170/
- Battleday RM, Brem AK. (2015). Modafinil for cognitive neuroenhancement in healthy non-sleep-deprived subjects: a systematic review. European Neuropsychopharmacology, 25(11), 1865-1881. https://pubmed.ncbi.nlm.nih.gov/26381811/
- Roberts CA, Jones A, Sumnall H, Gage SH, Montgomery C. (2020). How effective are pharmaceuticals for cognitive enhancement in healthy adults? A series of meta-analyses. European Neuropsychopharmacology, 38, 40-62. https://pubmed.ncbi.nlm.nih.gov/32709551/
- Cope ZA, Minassian A, Kreitner D, et al. (2017). Modafinil improves attentional performance in healthy, non-sleep deprived humans at doses not inducing hyperarousal across species — randomised controlled trial. Neuropharmacology, 125, 254-262. https://pubmed.ncbi.nlm.nih.gov/28774856/
- Nunez NA, Singh B, Romo-Nava F, et al. (2020). Efficacy and tolerability of adjunctive modafinil/armodafinil in bipolar depression: a meta-analysis of randomized controlled trials. Bipolar Disorders, 22(2), 109-120. https://pubmed.ncbi.nlm.nih.gov/31643130/
- Goss AJ, Kaser M, Costafreda SG, Sahakian BJ, Fu CH. (2013). Modafinil augmentation therapy in unipolar and bipolar depression: a systematic review and meta-analysis. Journal of Clinical Psychiatry, 74(11), 1101-1107. https://pubmed.ncbi.nlm.nih.gov/24330897/
- Cortese S, Adamo N, Del Giovane C, et al. (2018). Comparative efficacy and tolerability of medications for attention-deficit hyperactivity disorder: a systematic review and network meta-analysis. Lancet Psychiatry, 5(9), 727-738. https://pubmed.ncbi.nlm.nih.gov/30097390/
- Sangroula D, Motiwala F, Wagle B, et al. (2017). Modafinil treatment of cocaine dependence: a systematic review and meta-analysis. Substance Use & Misuse, 52(10), 1292-1306. https://pubmed.ncbi.nlm.nih.gov/28350194/
- Anderson AL, Reid MS, Li SH, et al. (2009). Modafinil for the treatment of cocaine dependence — randomised controlled trial. Drug and Alcohol Dependence, 104(1-2), 133-139. https://pubmed.ncbi.nlm.nih.gov/19560290/
- Hovey E, de Souza P, Marx G, et al. (2014). Phase III, randomized, double-blind, placebo-controlled study of modafinil for fatigue in patients treated with docetaxel-based chemotherapy. Supportive Care in Cancer, 22(5), 1233-1242. https://pubmed.ncbi.nlm.nih.gov/24337761/
- Volkow ND, Fowler JS, Logan J, et al. (2009). Effects of modafinil on dopamine and dopamine transporters in the male human brain. JAMA, 301(11), 1148-1154. https://pubmed.ncbi.nlm.nih.gov/19293415/
- Scammell TE, Estabrooke IV, McCarthy MT, et al. (2000). Hypothalamic arousal regions are activated during modafinil-induced wakefulness — animal study. Journal of Neuroscience, 20(22), 8620-8628. https://pubmed.ncbi.nlm.nih.gov/11069971/
- Robertson P Jr, Hellriegel ET, Arora S, Nelson M. (2002). Effect of modafinil on the pharmacokinetics of ethinyl estradiol and triazolam in healthy volunteers — randomised controlled trial. Clinical Pharmacology & Therapeutics, 71(1), 46-56. https://pubmed.ncbi.nlm.nih.gov/11823757/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.



