
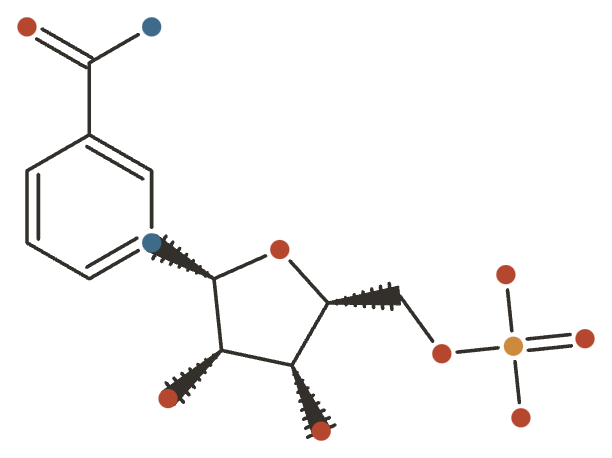
NMN (Nicotinamide mononucleotide)
The direct nucleotide precursor to NAD+, taken to raise NAD+ and studied for longevity, metabolism and blood pressure in mostly small, short human trials.

NMN (Nicotinamide mononucleotide) at a Glance
NMN (nicotinamide mononucleotide) is a nucleotide built from vitamin B3 and the direct precursor to NAD+, the coenzyme every cell uses to move electrons through metabolism.
NAD+ falls with age, and NMN sits one enzymatic step from restoring it — which is why it became the centrepiece of the longevity supplement market. It raises blood NAD+ reliably and dose-dependently.
What It’s Used For
- Raising blood NAD+ — its core effect, established across multiple trials.
- Blood pressure — lowers diastolic blood pressure.
- Aerobic capacity & physical performance — improves aerobic capacity, studied in older and trained subgroups.
- Insulin sensitivity & metabolic markers — supports insulin signalling in muscle.
- Sleep quality & fatigue — improves reported sleep and fatigue in older adults.
How It Works
NAD+ cannot be absorbed intact in useful amounts, so it is raised by supplying precursors. NMN sits one step away: NMNAT converts it directly to NAD+ through the salvage pathway, the short route that makes it preferable to plain nicotinamide.
Raised NAD+ feeds the sirtuins, the NAD+-dependent enzymes governing metabolic and stress-response signalling. More concretely it supports endothelial eNOS signalling, the route to the blood-pressure effect, and mitochondrial function in skeletal muscle. It is dosed daily in the hundreds of milligrams and builds up rather than acting acutely.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
NMN (β-nicotinamide mononucleotide) is a nucleotide and the immediate biosynthetic precursor to NAD+, the coenzyme that drives cellular energy metabolism and fuels the sirtuin and PARP enzyme families. Because tissue NAD+ falls with age, NMN is sold on the premise that topping it back up will slow aging and sharpen metabolism — a hypothesis that, unusually for a longevity supplement, now rests on a growing set of human randomized trials rather than mouse data alone. The consistent finding across those trials is that oral NMN reliably raises blood NAD+, but the downstream clinical benefits are small, inconsistent, or absent once you demand hard outcomes and placebo controls. Almost all trials are short (2–24 weeks), modestly sized (typically 10–80 people), and skewed toward older or metabolically at-risk adults, so a benefit that shows up in a 65-year-old may not generalize to a healthy 35-year-old. Form and dose matter less here than for a mineral — most trials used generic oral β-NMN at 250–1250 mg/day — but the gap between “moved the biomarker” and “changed how you age” is the whole story.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the one thing NMN unambiguously does. Across trials, oral β-NMN raises whole-blood NAD+ and its metabolites in a dose-dependent way: a 60-day dose-ranging RCT in 80 middle-aged adults (placebo, 300, 600, 900 mg/day) confirmed dose-dependent NAD+ elevation 6Reference 6RCTThe efficacy and safety of β-nicotinamide mononucleotide (NMN) supplementation in healthy middle-aged adults — [RCT, dose-ranging]View study →, and a 14-day RCT of a microcrystalline formulation (MIB-626, 1000 mg once or twice daily) raised blood NMN 1.7- to 3.7-fold above baseline with a corresponding rise in NAD+ 13Reference 13RCTMIB-626, an oral formulation of a microcrystalline unique polymorph of β-nicotinamide mononucleotide, increases circulating NAD and its metabolome in middle-aged and older adults — [RCT]View study →.
Other older-adult trials that tracked NAD+ alongside clinical endpoints likewise saw it climb with 250 mg/day dosing 8Reference 8RCTIngestion of β-nicotinamide mononucleotide increased blood NAD levels, maintained walking speed, and improved sleep quality in older adults — [RCT]View study →.
The key limitation is conceptual, not statistical: raising a blood biomarker is a mechanism-of-action check, not a health outcome, and the trials that measured clinical endpoints alongside NAD+ generally failed to show them move in step.
Gap: every positive trial here reports a surrogate marker; none demonstrates that the extra NAD+ translates into a clinical benefit.
The most credible clinical signal comes from cardiovascular measures. A 2026 systematic review and meta-analysis pooled 10 RCTs (11 arms, 349 participants) and found NMN produced a statistically significant but modest reduction in resting diastolic pressure (−2.15 mmHg; 95% CI −3.68 to −0.61), with systolic pressure falling significantly only in the subgroup aged 60 and over (−3.94 mmHg; 95% CI −7.06 to −0.82) 12Reference 12Meta-analysisEffects of nicotinamide mononucleotide supplementation on blood pressure: a systematic review and meta-analysis of RCTs — [meta-analysis]View study →.
This is consistent with a single physiologic RCT (MIB-626, 30 overweight/obese adults ≥45 y) that reported a −7.0 mmHg diastolic difference versus placebo alongside reductions in body weight and LDL cholesterol 7Reference 7RCTNicotinamide adenine dinucleotide augmentation in overweight or obese middle-aged and older adults: a physiologic study — [RCT]View study →.
Effects are small, seen mainly in older or at-risk groups, and the authors themselves frame them as preliminary and hypothesis-generating.
Gap: the effect is modest, concentrated in older adults, and awaits confirmation in large, long-term trials powered for cardiovascular endpoints rather than office blood pressure.
A 6-week, four-arm RCT in 48 amateur runners (300, 600, 1200 mg/day vs placebo) found that oxygen uptake and power at the ventilatory thresholds improved more in the medium- and high-dose groups than placebo — but VO2max itself, O2-pulse, and peak power did not change, and the effect was interpreted as better muscle O2 utilization during training rather than a raw fitness gain 4Reference 4RCTNicotinamide mononucleotide supplementation enhances aerobic capacity in amateur runners — [RCT]View study →.
In older adults, a 12-week RCT at 250 mg/day found no difference in the primary stepping test, though the NMN group had a significantly shorter 4-m walking time as a secondary outcome 8Reference 8RCTIngestion of β-nicotinamide mononucleotide increased blood NAD levels, maintained walking speed, and improved sleep quality in older adults — [RCT]View study →.
Against these, a 24-week RCT in older diabetic men with impaired performance found no difference in grip strength or walking speed 16Reference 16RCTEffects of nicotinamide mononucleotide on older patients with diabetes and impaired physical performance — [RCT, null]View study →, and a 2025 meta-analysis on muscle mass and function found no significant effect on skeletal muscle index, grip strength, or gait speed 11Reference 11Meta-analysisThe effect of nicotinamide mononucleotide and riboside on skeletal muscle mass and function: a systematic review and meta-analysis — [meta-analysis]View study →.
Gap: benefits appear only in specific groups (trained or frail older adults) and mostly on secondary endpoints; primary performance outcomes and the muscle meta-analysis are null.
The headline positive study is a 10-week RCT in postmenopausal prediabetic women with overweight/obesity, where NMN (250 mg/day) increased insulin-stimulated glucose disposal measured by hyperinsulinemic–euglycemic clamp and enhanced skeletal-muscle insulin signaling (AKT/mTOR phosphorylation) versus placebo 3Reference 3RCTNicotinamide mononucleotide increases muscle insulin sensitivity in prediabetic women — [RCT]View study →.
That result is real but narrow — a deficiency-and-risk population, a mechanistic endpoint — and it has not generalized. Two 2024–2025 meta-analyses of RCTs (8 trials/342 adults; and 12 trials/513 adults) found no significant effect of NMN on fasting glucose, fasting insulin, HbA1c, HOMA-IR, or the lipid panel, while confirming the NAD+ rise; both flagged substantial risk of bias in the underlying trials 9,
A physiologic RCT in overweight/obese adults similarly found no change in insulin sensitivity or ectopic fat 7Reference 7RCTNicotinamide adenine dinucleotide augmentation in overweight or obese middle-aged and older adults: a physiologic study — [RCT]View study →.
Gap: the one positive clamp study is in a specific at-risk group; pooled RCT evidence in broader, mostly healthy adults shows no metabolic benefit.
Sleep and fatigue signals come from secondary endpoints. A 12-week RCT in 108 older Japanese adults (250 mg/day, timed morning vs afternoon) found afternoon NMN produced the largest effect on lower-limb function (5-times sit-to-stand, d = 0.72) and reduced drowsiness (d = 0.64), suggesting a timing-dependent benefit 5Reference 5RCTEffect of 12-week intake of nicotinamide mononucleotide on sleep quality, fatigue, and physical performance in older Japanese adults — [RCT]View study →.
A separate 12-week RCT in older adults reported improved subjective sleep quality alongside maintained walking speed 8Reference 8RCTIngestion of β-nicotinamide mononucleotide increased blood NAD levels, maintained walking speed, and improved sleep quality in older adults — [RCT]View study →.
These are modest, questionnaire-based, timing-sensitive findings in older populations, and a dedicated multicenter insomnia RCT is registered but not yet reported.
Gap: results rest on subjective secondary endpoints in older adults, are sensitive to dose timing, and lack confirmation from a trial designed primarily around sleep.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| NAD+ biosynthesis (salvage pathway) | NMN → NMNAT → NAD+ ↑ | All applications — the shared upstream mechanism |
| Sirtuins (SIRT1–7) | ↑ activity (NAD+-dependent deacylases) | Metabolicvascularputative anti-aging |
| Slc12a8 NMN transporter | Direct NMN uptake (shown in mouse intestine; disputed) 15Reference 15AnimalSlc12a8 is a nicotinamide mononucleotide transporter — [mechanistic, mouse]View study → | Absorption/bioavailability rationale |
| Endothelial / vascular NAD+ | ↑ eNOS signaling, ↓ arterial stiffness (trend) | Blood pressure |
| Skeletal-muscle NAD+ / mitochondrial function | ↑ O2 utilization, insulin signaling | Aerobic capacityinsulin sensitivity |
Pharmacokinetics
Oral NMN is absorbed rapidly; plasma NMN metabolites rise within minutes to hours, and single doses of 100–500 mg produce dose-related increases in nicotinamide-pathway metabolites without acute clinical changes 14Reference 14Clinical trialEffect of oral administration of nicotinamide mononucleotide on clinical parameters and nicotinamide metabolite levels in healthy Japanese men — [clinical trial]View study →. Whether NMN is absorbed intact or first cleaved to nicotinamide riboside/nicotinamide at the gut wall remains contested: a mouse NMN transporter (Slc12a8) was reported in 2019 15Reference 15AnimalSlc12a8 is a nicotinamide mononucleotide transporter — [mechanistic, mouse]View study → but the finding was challenged, so the exact route of human uptake is unresolved. Regardless of route, blood NAD+ rises dose-dependently and plateaus over days to weeks of daily dosing 6,
Clinical trials
NMN has an active and growing registered-trial footprint — dozens of small RCTs completed since 2020, several ongoing (including a registered multicenter insomnia trial), and one line of industry-sponsored development around the microcrystalline MIB-626 formulation, which has since been tested in hospitalized COVID-19/acute-kidney-injury patients as well. Because NMN is a commodity molecule, most trials are small, investigator- or supplement-industry-funded, and short; there is no large, long-duration outcomes trial.
| Completed | Planned/ongoing | Terminated | Preclinical |
|---|---|---|---|
| ~15–20human RCTs | several(incl. insomnia, cardiometabolic) | few | hundreds(rodent/in vitro) |
Last checked: July 2026.
Dietary Sources
NMN occurs naturally in small amounts in a range of foods, but dietary intake is orders of magnitude below the doses used in supplements. Reported natural NMN contents are in the low milligrams — or fractions of a milligram — per kilogram of food, so ordinary eating supplies at most a few milligrams a day, versus the 250–900 mg used in trials. Foods most often cited as sources include edamame and other soy products, broccoli, cabbage, cucumber, avocado, and tomato, with smaller amounts in raw beef and shrimp.
| Food | Approx. NMN content | Notes |
|---|---|---|
| Edamame / soybean | ~0.5–2 mg per 100 g | Among the richer plant sources |
| Broccoli | ~0.2–1 mg per 100 g | Cruciferous vegetable |
| Cucumber (seed) | ~0.5–1.5 mg per 100 g | Concentrated in seed |
| Avocado | ~0.3–1.5 mg per 100 g | |
| Cabbage, tomato | ~0.1–0.7 mg per 100 g | |
| Raw beef, shrimp | ~0.06–0.4 mg per 100 g | Animal sources, lower |
Values are approximate and drawn from limited food-analysis literature; NMN content varies with ripeness, storage, and cooking.
The body also makes NMN endogenously from dietary niacin-family vitamins (nicotinamide, nicotinamide riboside) via the NAD+ salvage pathway, so NMN is not an essential dietary nutrient — there is no deficiency state and no recommended intake. The practical implication: no realistic diet delivers a “supplemental” NMN dose, which is precisely why the supplement exists — but it also means NMN sits outside the usual “correct a dietary shortfall” logic that justifies most vitamins and minerals.
Dosage & Intake
Human trials have used roughly 150–1250 mg/day, with 250–900 mg/day the most common range; single-dose safety work has gone up to 500 mg and repeated-dose safety work up to 1250 mg/day. These are doses studied in research, not a personal recommendation.
A few practical notes from the trial literature:
- No established optimal dose. Blood NAD+ rises dose-dependently, but because clinical outcomes rarely track the biomarker, there is no dose proven to deliver a health benefit. Higher is not demonstrably better for outcomes.
- Timing may matter for some effects. In one older-adult trial, afternoon dosing outperformed morning dosing for lower-limb function and drowsiness 5Reference 5RCTEffect of 12-week intake of nicotinamide mononucleotide on sleep quality, fatigue, and physical performance in older Japanese adults — [RCT]View study → — a single finding, not a rule.
- Daily dosing builds a steady state. NAD+ elevation accumulates over days to weeks of consistent daily intake rather than from a single dose.
- Formulation. Generic oral β-NMN was used in most trials; microcrystalline (MIB-626), sublingual, and nano-delivery forms exist but none has shown a clinical-outcome advantage, so paying a premium for a “high-absorption” form is not evidence-backed.
- Not an essential nutrient, so there is no RDA/AI to meet and no established Tolerable Upper Intake Level to stay under.
- Regulatory status. In the United States, the FDA has taken the position that NMN is excluded from the dietary-supplement definition (it was investigated as a drug), so its legal status as a supplement is contested and product availability may vary.
Safety
NMN has looked benign in every short human trial run so far, and the real gaps are about duration rather than toxicity — the longest studies run about 24 weeks for a product marketed as a lifelong daily habit.
- No serious adverse events in trials. 1250 mg/day for 4 weeks produced no changes beyond normal physiological variation.
- Side effects are infrequent and mild. Occasional digestive upset is the usual complaint.
- Not used in pregnancy or breastfeeding. No human data and no established upper limit — see the box below.
- No long-term safety data. The longest trials run about 24 weeks; lifelong daily use is unstudied.
- Drug interactions never formally assessed. No dedicated interaction studies exist, and dosing in renal or hepatic impairment is unstudied.
- Contested US supplement status. The FDA takes the position that NMN is excluded from the dietary-supplement definition.
Full Safety & Interactions Detail
NMN has looked reassuringly benign in the short human trials conducted so far. A randomized, double-blind, placebo-controlled trial of 1250 mg/day for up to 4 weeks in 31 healthy adults found no changes beyond normal physiological variation and no serious adverse events 2Reference 2RCTSafety evaluation of β-nicotinamide mononucleotide oral administration in healthy adult men and women — [RCT, safety]View study →, and single oral doses of 100–500 mg caused no significant changes in heart rate, blood pressure, oxygen saturation, or laboratory parameters 14Reference 14Clinical trialEffect of oral administration of nicotinamide mononucleotide on clinical parameters and nicotinamide metabolite levels in healthy Japanese men — [clinical trial]View study →.
Across the trial base, reported side effects are infrequent and mild (occasional digestive upset). The 2024 systematic review of RCTs likewise reported no serious adverse effects 1Reference 1Systematic reviewImproved physical performance parameters in patients taking nicotinamide mononucleotide (NMN): a systematic review of randomized control trials — [systematic review]View study →.
The honest caveats are about what has not been studied:
- Duration. The longest trials run about 24 weeks; NMN is marketed for lifelong daily use, and there is no long-term safety data at all.
- Populations. Trials skew toward healthy or metabolically at-risk middle-aged and older adults. Effects in the young, the frail, or people with significant disease are largely uncharacterized.
- Drug interactions — not formally assessed. No dedicated interaction studies exist. Because NMN feeds the NAD+/sirtuin/PARP axis, theoretical interactions with drugs affecting NAD+ metabolism cannot be excluded, but none has been characterized in humans.
- Renal/hepatic impairment — not studied. No dosing data in organ impairment.
- Regulatory status. In the United States, the FDA has taken the position that NMN is excluded from the dietary-supplement definition (it was investigated as a drug), so its legal status as a supplement is contested and product availability may vary.
Verdict: avoid. There are no human safety data on NMN during pregnancy or lactation, and no established upper limit. Absence of reported harm is not evidence of safety — it reflects that the studies have not been done. NMN should not be used during pregnancy or breastfeeding.
References
- Wen, J., et al. (2024). Improved physical performance parameters in patients taking nicotinamide mononucleotide (NMN): a systematic review of randomized control trials — [systematic review]. Cureus. https://pubmed.ncbi.nlm.nih.gov/39221308/
- Fukamizu, Y., et al. (2022). Safety evaluation of β-nicotinamide mononucleotide oral administration in healthy adult men and women — [RCT, safety]. Scientific Reports. https://pubmed.ncbi.nlm.nih.gov/36002548/
- Yoshino, M., et al. (2021). Nicotinamide mononucleotide increases muscle insulin sensitivity in prediabetic women — [RCT]. Science. https://pubmed.ncbi.nlm.nih.gov/33888596/
- Liao, B., et al. (2021). Nicotinamide mononucleotide supplementation enhances aerobic capacity in amateur runners — [RCT]. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/34238308/
- Kim, M., et al. (2022). Effect of 12-week intake of nicotinamide mononucleotide on sleep quality, fatigue, and physical performance in older Japanese adults — [RCT]. Nutrients. https://pubmed.ncbi.nlm.nih.gov/35215405/
- Yi, L., et al. (2023). The efficacy and safety of β-nicotinamide mononucleotide (NMN) supplementation in healthy middle-aged adults — [RCT, dose-ranging]. GeroScience. https://pubmed.ncbi.nlm.nih.gov/36482258/
- Pencina, K. M., et al. (2023). Nicotinamide adenine dinucleotide augmentation in overweight or obese middle-aged and older adults: a physiologic study — [RCT]. Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/36740954/
- Morifuji, M., et al. (2024). Ingestion of β-nicotinamide mononucleotide increased blood NAD levels, maintained walking speed, and improved sleep quality in older adults — [RCT]. GeroScience. https://pubmed.ncbi.nlm.nih.gov/38789831/
- Chen, F., et al. (2024). Effects of nicotinamide mononucleotide on glucose and lipid metabolism in adults: a systematic review and meta-analysis of RCTs — [meta-analysis]. Current Diabetes Reports. https://pubmed.ncbi.nlm.nih.gov/39531138/
- Zhang, J., et al. (2025). Efficacy of oral nicotinamide mononucleotide supplementation on glucose and lipid metabolism for adults: a systematic review with meta-analysis of RCTs — [meta-analysis]. Critical Reviews in Food Science and Nutrition. https://pubmed.ncbi.nlm.nih.gov/39116016/
- Prokopidis, K., et al. (2025). The effect of nicotinamide mononucleotide and riboside on skeletal muscle mass and function: a systematic review and meta-analysis — [meta-analysis]. Journal of Cachexia, Sarcopenia and Muscle. https://pubmed.ncbi.nlm.nih.gov/40275690/
- Zhang, M., et al. (2026). Effects of nicotinamide mononucleotide supplementation on blood pressure: a systematic review and meta-analysis of RCTs — [meta-analysis]. Nutrients. https://pubmed.ncbi.nlm.nih.gov/41901064/
- Pencina, K. M., et al. (2023). MIB-626, an oral formulation of a microcrystalline unique polymorph of β-nicotinamide mononucleotide, increases circulating NAD and its metabolome in middle-aged and older adults — [RCT]. Journals of Gerontology Series A. https://pubmed.ncbi.nlm.nih.gov/35182418/
- Irie, J., et al. (2020). Effect of oral administration of nicotinamide mononucleotide on clinical parameters and nicotinamide metabolite levels in healthy Japanese men — [clinical trial]. Endocrine Journal. https://pubmed.ncbi.nlm.nih.gov/31685720/
- Grozio, A., et al. (2019). Slc12a8 is a nicotinamide mononucleotide transporter — [mechanistic, mouse]. Nature Metabolism. https://pubmed.ncbi.nlm.nih.gov/31131364/
- Akasaka, H., et al. (2023). Effects of nicotinamide mononucleotide on older patients with diabetes and impaired physical performance — [RCT, null]. Geriatrics & Gerontology International. https://pubmed.ncbi.nlm.nih.gov/36443648/



