
PRL-8-53
A synthetic research nootropic whose memory-enhancement reputation rests on a single 1978 human study; modern evidence is essentially absent.

PRL-8-53 at a Glance
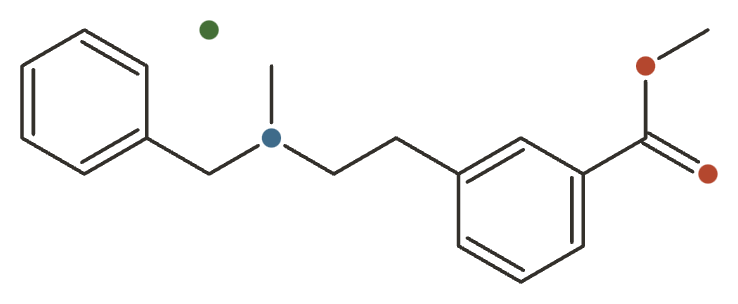
PRL-8-53 is a synthetic research nootropic — chemically a benzoic-acid methyl ester with a benzyl(methyl)aminoethyl side chain, sold as the hydrochloride salt. It does not occur in food or in nature, and it has never been an approved drug or dietary supplement anywhere.
It is not a nutrient, so there is no deficiency-versus-repletion question here: any claimed effect is purely pharmacological, in an otherwise normal brain.
The reason is simple. The entire clinical reputation of PRL-8-53 rests on one study, published in 1978. That study was a genuine double-blind, placebo-controlled trial and it did report a statistically significant improvement in verbal retention — but it is roughly fifty years old, its sample size is not stated in the accessible record, and nothing has replicated it since. There are no registered trials, no human pharmacokinetics, and no characterised safety profile.
The honest bottom line: a single unreplicated 1978 trial cannot carry the marketing built on top of it. The blog posts, vendor pages and forum summaries that circulate impressive-sounding percentages are all re-tellings of that one paper — they are not additional evidence.
What It’s Used For
There is exactly one application with any human evidence behind it:
- Verbal memory and learning retention — improved retention of verbal material at a single 5 mg oral dose in the 1978 trial.
Be sceptical of the specific numbers you will see quoted. Claims of “doubled recall,” or gains of 87–108% in older or poor-baseline subjects, trace back to readings of that same study and its secondary summaries; those effect sizes could not be verified from the primary record. Note also what the study didn’t find: no significant change in visual reaction time or motor control. Whatever the compound did, it did not make people generally faster or sharper.
How It Works
Honestly: nobody knows. The mechanism of PRL-8-53 in humans is not established, and this is the rare page where the mechanism section has nothing solid to offer.
The hypotheses that circulate — potentiation of cholinergic responses, enhancement of dopamine-linked responses, partial serotonergic antagonism — come from the original developer’s characterisation and from structural inference. No receptor-binding, occupancy, or human target-engagement data exist to confirm any of them.
Treat any confident mechanistic story about this compound as an extrapolation. The 1978 paper demonstrated an effect on a memory task; it did not demonstrate why.
Pharmacology & Research
PRL-8-53 is a synthetic research nootropic — chemically a benzoic-acid methyl-ester with a benzyl(methyl)aminoethyl side chain (methyl 3-[2-[benzyl(methyl)amino]ethyl]benzoate hydrochloride) — that is sold as a research chemical, not as an approved drug or dietary supplement. Its entire clinical reputation rests on one small, double-blind, placebo-controlled human study published in 1978, and no modern controlled trial has replicated it. Because it is not a nutrient, there is no deficiency-versus-repletion question here: any claimed effect is a pharmacological one in healthy adults, and the evidence for it is thin and old. Its human pharmacokinetics, long-term safety, and toxicity are essentially uncharacterized, and consumer-product purity is unverified. Secondary write-ups (blogs, vendor pages, forums) frequently amplify the single 1978 result — those summaries are not additional evidence.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
The only primary human trial, Hansl & Mead (1978), was a double-blind, placebo-controlled study using the serial-anticipation method (learning of nonsense syllables / verbal material) at a single 5 mg oral dose of PRL-8-53. It reported slight improvement of acquisition and improvement of retention of verbal information to a statistically significant degree (reported P values better than 0.01, some better than 0.001), with no significant change in visual reaction time or motor control versus placebo 1Reference 1RCTPRL-8-53: enhanced learning and subsequent retention in humans as a result of low oral doses of new psychotropic agent — randomised double-blind, placebo-controlled trialView study →. This is a single, small, roughly 50-year-old study; the accessible abstract does not report the sample size, and the trial has not been independently replicated in any modern controlled trial. The frequently cited large percentage gains (e.g. “doubled recall,” ~87–108% improvement in older or poor-baseline subjects) come from readings of this one study and its secondary summaries and could not be verified from the primary record available in this pass.
Gap: A single unreplicated 1978 RCT with an unstated sample size, no dose-ranging, no modern replication, and no accompanying pharmacokinetic or safety data — far too thin to treat the memory effect as established.
Mechanisms
The mechanism of PRL-8-53 in humans is not established; the entries below are hypotheses from the original developer’s characterization and structural inference, not demonstrated human pharmacology.
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Cholinergic tone (proposed) | Possible potentiation of acetylcholine-mediated responses | Hypothesized basis for verbal-memory effect (unverified) |
| Dopaminergic modulation (proposed) | Possible enhancement of dopamine-linked responses | Hypothesized basis for learning effect (unverified) |
| Serotonergic activity (proposed) | Possible partial antagonism | Speculative; no human data |
No receptor-binding, occupancy, or human target-engagement data are available to confirm any of these.
Pharmacokinetics
Human pharmacokinetics for PRL-8-53 are uncharacterized. The single human study used a 5 mg single oral dose; absorption fraction, time-to-peak, volume of distribution, metabolism, elimination route, and half-life have not been reported in accessible peer-reviewed literature. No food-effect or repeat-dose (steady-state) data exist. Any half-life or dosing-frequency figures circulating in nootropic communities are not supported by citable human PK studies.
Clinical trials
There is essentially no registered or modern trial activity. A search of ClinicalTrials.gov returned no registered studies for PRL-8-53, and PubMed / Europe PMC return a single primary human trial (1978); the compound is off-patent, commercially unregulated, and attracts no evident industry-sponsored clinical development.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| 1 | 0 | 0 | ~few(undocumented developer-era work) |
Last checked: August 2026.
Dietary Sources
PRL-8-53 has no dietary source — it does not occur in food or in nature. It is a fully synthetic compound (a benzoic-acid methyl-ester derivative; C₁₈H₂₁NO₂ as the free base, C₁₈H₂₂ClNO₂ / MW 319.8 as the hydrochloride salt used in study and commerce; PubChem CID 70700868). It is prepared by chemical synthesis and sold as a research chemical, so there is no food-sources analysis to give and no absorption-from-diet figure.
Dosage
The only dose ever studied in humans is a single 5 mg oral dose (Hansl & Mead, 1978) 1Reference 1RCTPRL-8-53: enhanced learning and subsequent retention in humans as a result of low oral doses of new psychotropic agent — randomised double-blind, placebo-controlled trialView study →. That figure is reported for context, not as a recommendation.
No validated dosing range, titration schedule, dose-response curve, timing guidance, or food-effect data exists in the peer-reviewed literature. Because PRL-8-53 is not a nutrient, there is no RDA/AI and no Tolerable Upper Intake Level either. There is genuinely nothing else to report here — which is itself the most useful thing this section can say.
Safety
PRL-8-53’s safety profile is not “clean” — it is unstudied, which is a different claim entirely.
- A research chemical, not an approved medicine or supplement. Purity in consumer products is unverified.
- Human safety is essentially uncharacterized. No adverse-effect frequency, no dose-limiting toxicity, no long-term data.
- No interaction data exist against any drug class — so nothing can be ruled in or out.
- The one reassuring observation is very thin. The 1978 study found no change in visual reaction time or motor control at 5 mg — a single-dose observation in one small trial, not a safety profile.
- No upper limit is set. Not a nutrient; the absence of a ceiling is not evidence that any dose is safe.
Full Safety & Interactions Detail
PRL-8-53 is a research chemical: it is not an approved medicine or dietary supplement, its purity in consumer products is unverified, and its human safety profile is essentially uncharacterized. The single 1978 study reported no significant change in visual reaction time or motor control at 5 mg versus placebo 1Reference 1RCTPRL-8-53: enhanced learning and subsequent retention in humans as a result of low oral doses of new psychotropic agent — randomised double-blind, placebo-controlled trialView study →, but a one-time, single-dose observation in one small trial does not establish a safety profile.
Human toxicity, adverse-effect frequency, dose-limiting toxicity, drug interactions, and long-term effects have not been studied at all. No interaction data against any drug class exist, so no specific interaction can be ruled in or out. This entry is informational only and is not a recommendation to use the compound.
Scope disclosure. Interactions assessed? No — no human interaction studies exist for any drug class; none could be checked. Pregnancy/lactation assessed? No — no reproductive or lactation data exist. Upper limit established? No. Where PRL-8-53 was not studied, that is recorded as “not assessed” rather than implying safety from an absence of reports.
Avoid — not assessed. There are no reproductive, developmental, or lactation-safety data for PRL-8-53. Absence of reports is not evidence of safety; it should be avoided in pregnancy and breastfeeding.
References
- Hansl NR, Mead BT (1978). PRL-8-53: enhanced learning and subsequent retention in humans as a result of low oral doses of new psychotropic agent — randomised double-blind, placebo-controlled trial. Psychopharmacology, 56(3):249–253. doi:10.1007/BF00432846. https://pubmed.ncbi.nlm.nih.gov/418433/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.



