
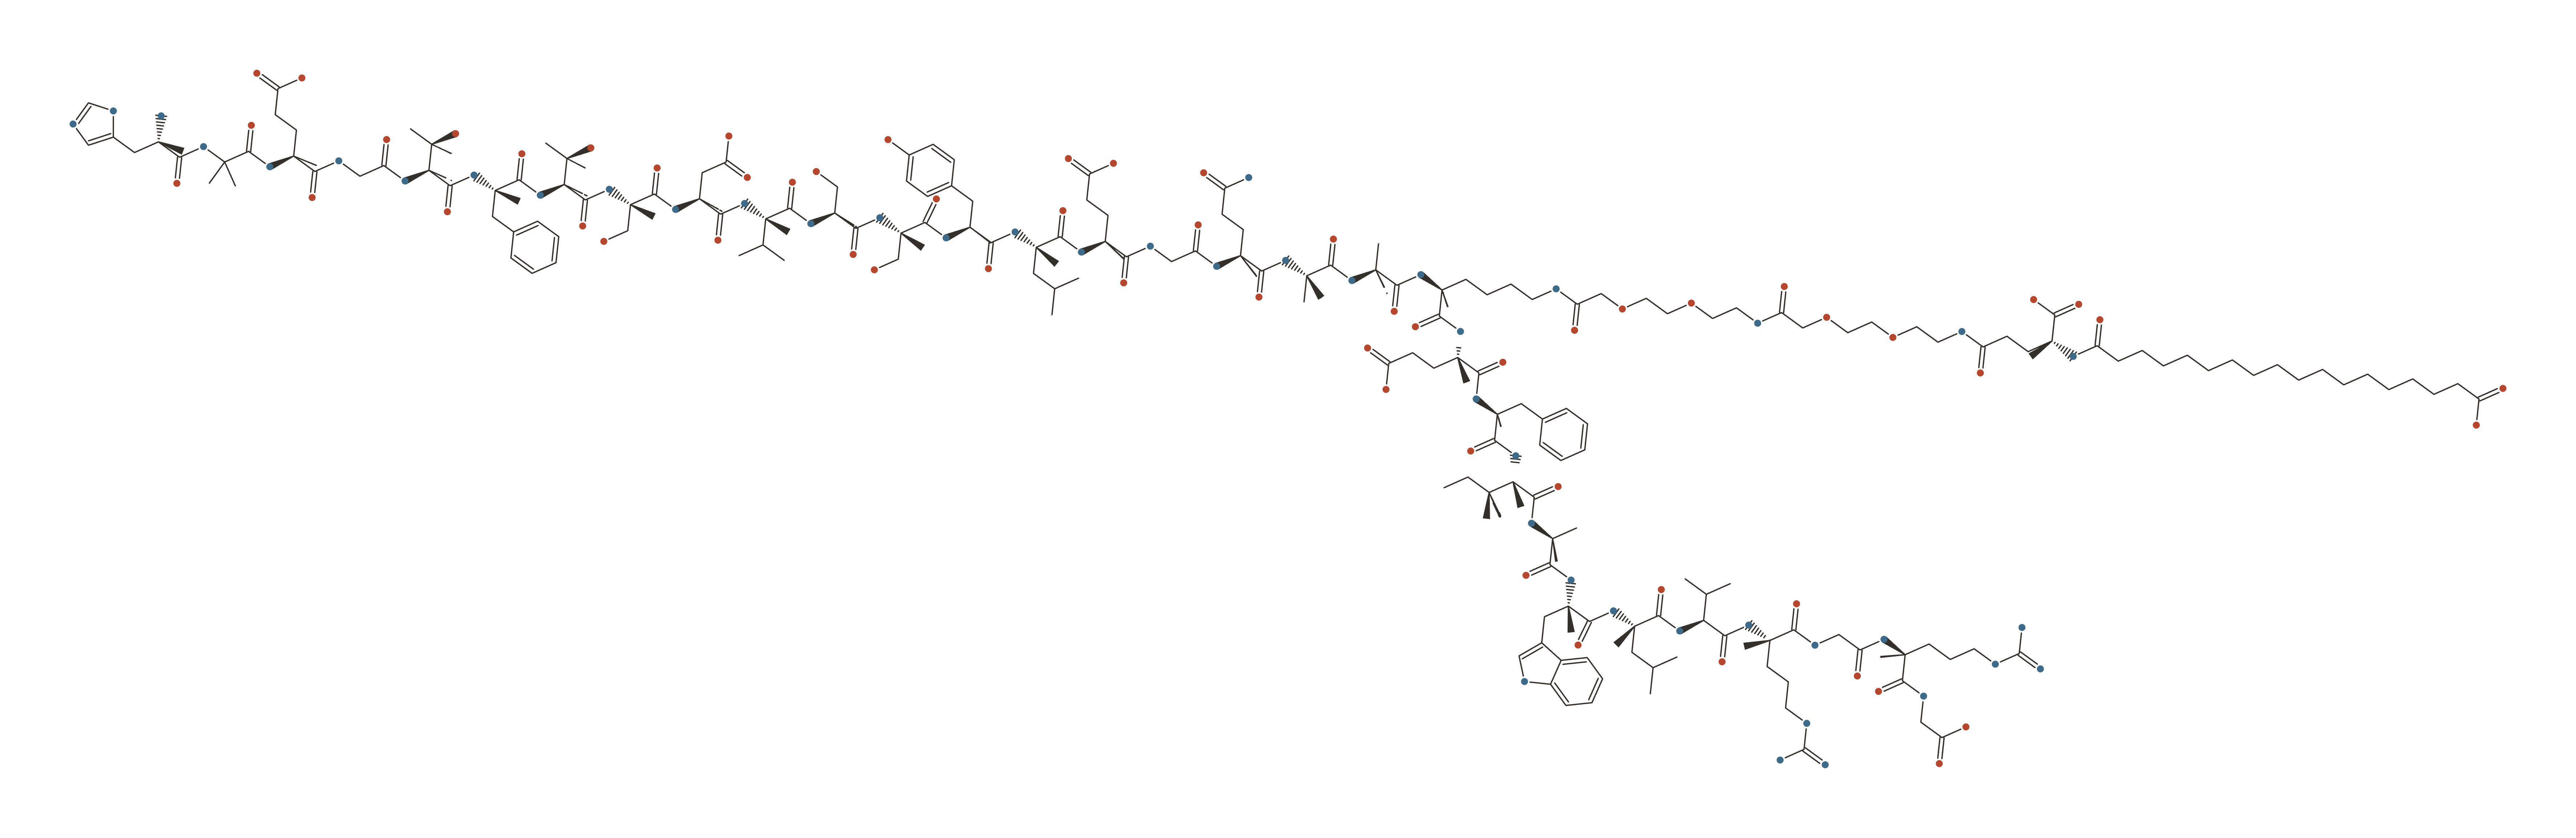

Semaglutide (Ozempic / Wegovy / Rybelsus) at a Glance
Semaglutide mimics GLP-1, a hormone the gut releases after eating that tells the pancreas to release insulin and the brain that you are full. Modified to resist breakdown and to bind albumin, it lasts long enough for once-weekly dosing. It is a prescription medicine with among the strongest evidence of anything here — approved for type 2 diabetes, chronic weight management and cardiovascular risk reduction, on the basis of large outcome trials rather than surrogate markers. It is the compound that made this drug class a cultural phenomenon.
History & Development
Semaglutide is the end point of a twenty-year engineering problem at a single company: how to take a gut hormone that survives about two minutes in the bloodstream and make it last a week.
| First described | Programme described by its originators in 2019; semaglutide entered clinical trials from 2008 32Reference 32The discovery and development of liraglutide and semaglutideView study → |
| Discovered / synthesised by | Novo Nordisk research programme; the discovery account is authored by Lotte Bjerre Knudsen and Jesper Lau 32Reference 32The discovery and development of liraglutide and semaglutideView study → |
| Institution | Novo Nordisk A/S, Maalov, Denmark 32Reference 32The discovery and development of liraglutide and semaglutideView study → |
| Origin | De-novo synthetic analogue of human GLP-1, engineered from the earlier analogue liraglutide |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Novo Nordisk A/S |
| Development status | Approved - FDA, Ozempic (type 2 diabetes) 2017; Rybelsus (oral) 2019; Wegovy (chronic weight management) 2021 |
Discovery
The starting point was not obesity. GLP-1 was identified as an incretin - a gut hormone released after eating that prompts insulin release - and the therapeutic interest was type 2 diabetes. The obstacle was pharmacokinetic rather than pharmacological: native GLP-1 is destroyed by the enzyme DPP-4 within minutes, making the natural hormone useless as a medicine.
Novo Nordisk’s programme solved this in two stages, and semaglutide is the second. Liraglutide, the first, attached a C16 fatty acid so the molecule would bind albumin and circulate longer, reaching once-daily dosing. Semaglutide pushed the same idea further, and its originators describe the goal plainly: “there was focus on improving convenience, ideally with an effective GLP-1 analog that could be administered once weekly” 32Reference 32The discovery and development of liraglutide and semaglutideView study →.
Three changes achieved it. The peptide backbone was modified at position 8, substituting alanine with aminoisobutyric acid to block DPP-4 cleavage; the C16 mono-acid was replaced with a C18 di-acid with stronger albumin binding; and a longer gamma-Glu-2xOEG linker was introduced between the two 32Reference 32The discovery and development of liraglutide and semaglutideView study →. The result circulates bound to albumin and is released slowly, giving a half-life measured in days rather than minutes.
Development & ownership
Semaglutide has stayed with its originator throughout - there is no licensing or acquisition story here, which is unusual for this site and reflects that it was developed inside an established pharmaceutical company rather than spun out of academic work.
Clinical trials began in 2008. FDA approval followed for Ozempic in type 2 diabetes in December 2017, for Rybelsus - an oral formulation, itself a substantial delivery achievement for a peptide - in September 2019, and for Wegovy in chronic weight management in June 2021. Cardiovascular outcome data subsequently extended the labelled indications beyond glycaemic control.
The specific composition-of-matter patent and its filing date were not established in the sources consulted for this section, and are not asserted here.
How it reached the market
Semaglutide reached patients through the ordinary regulatory route, and the interesting part of its market history is what happened afterwards. Demand for weight management outstripped supply, placing it on the FDA drug shortage list and opening a legal window for compounding pharmacies to produce copies - a channel that has since attracted regulatory attention over formulation differences and salt forms not present in the approved product 31Reference 31Compounded Semaglutide and Tirzepatide Products Use Unique Formulations but Efficacy and Safety Largely Unknown — editorial / product analysisView study →. That grey market sits alongside, rather than in place of, a fully approved medicine - the reverse of most compounds here.
What It's Used For
Semaglutide is a long-acting glucagon-like peptide-1 (GLP-1) receptor agonist — a 31-amino-acid analogue of human GLP-1(7-37) carrying two substitutions (Aib8, Arg34) that block degradation by dipeptidyl peptidase-4, plus a C18 fatty-diacid linker that binds albumin and stretches the half-life to about a week. It is the outlier on this hub: unlike the research peptides around it, its evidence base is approval-grade human data, and the SUSTAIN (diabetes), STEP (obesity), SELECT/SUSTAIN-6/PIONEER-6 (cardiovascular), FLOW (kidney), STEP-HFpEF (heart failure), ESSENCE (liver) and STRIDE (peripheral artery disease) programs have converted, one after another, into licensed indications. The strongest signals remain chronic weight management and glycemic control; the outcome trials extend it into cardiovascular, renal, hepatic, heart-failure and limb disease. The most instructive result of the last year is a null: the phase 3 evoke and evoke+ trials found no meaningful cognitive benefit in early Alzheimer’s disease 18Reference 18RCTEfficacy and safety of oral semaglutide 14 mg (flexible dose) in early-stage symptomatic Alzheimer’s disease (evoke and evoke+) — human (RCT, negative)View study →, a hard demonstration that metabolic success does not transfer to the brain. Route is load-bearing even here — semaglutide works only as a weekly subcutaneous injection or a specially formulated daily oral tablet, because unformulated oral peptide bioavailability is negligible.
The peptide discipline still applies, for one reason: a very large volume of semaglutide reaches people outside the prescription channel, through compounded preparations, “research use only” vials, and outright counterfeits. None of the evidence below speaks to that material.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is human, approval-grade evidence. In the phase 3 STEP 1 RCT (n=1,961 adults with overweight or obesity, without diabetes), once-weekly subcutaneous semaglutide 2.4 mg produced a mean body-weight change of about −14.9% versus −2.4% for placebo over 68 weeks alongside a lifestyle intervention 1Reference 1RCTOnce-Weekly Semaglutide in Adults with Overweight or Obesity (STEP 1) — human (RCT)View study →.
The effect replicates across the program: in type 2 diabetes (STEP 2, ~−9.6%) 2Reference 2RCTSemaglutide 2·4 mg once a week in adults with overweight or obesity, and type 2 diabetes (STEP 2) — human (RCT)View study →, with intensive behavioral therapy (STEP 3) 3Reference 3RCTEffect of Subcutaneous Semaglutide vs Placebo as an Adjunct to Intensive Behavioral Therapy on Body Weight (STEP 3) — human (RCT)View study →, as maintenance after a run-in (STEP 4 — continued treatment held the loss while switching to placebo regained it) 4Reference 4RCTEffect of Continued Weekly Subcutaneous Semaglutide vs Placebo on Weight Loss Maintenance (STEP 4) — human (RCT)View study →, and out to two years (STEP 5) 5Reference 5RCTTwo-year effects of semaglutide in adults with overweight or obesity (STEP 5) — human (RCT)View study →.
Head to head, weekly semaglutide beat daily liraglutide (STEP 8) 6Reference 6RCTEffect of Weekly Subcutaneous Semaglutide vs Daily Liraglutide on Body Weight (STEP 8) — human (RCT)View study →.
A daily oral formulation reached comparable loss at 50 mg (OASIS 1) 7Reference 7RCTOral semaglutide 50 mg taken once per day in adults with overweight or obesity (OASIS 1) — human (RCT)View study →, and modeling of the 25 mg oral dose that reached market puts it in the same range 20Reference 20Efficacy, Safety and Pharmacokinetics of Once-Daily Oral Semaglutide 25 mg for Obesity With and Without Type 2 Diabetes — human (comparative analysis)View study →.
In adolescents aged 12 and over, a single phase 3 trial reported a mean BMI reduction of about 16% versus a small placebo gain 17Reference 17RCTOnce-Weekly Semaglutide in Adolescents with Obesity (STEP TEENS) — human (RCT)View study →, which is the basis for the pediatric indication.
Gap: durability past ~2 years and post-cessation regain are the live questions — the STEP 1 extension found that one year after withdrawal participants had regained roughly two-thirds of the lost weight, with cardiometabolic improvements reverting in step 19Reference 19RCTWeight regain and cardiometabolic effects after withdrawal of semaglutide: the STEP 1 trial extension — human (RCT extension)View study →. Most trials also pair the drug with structured lifestyle programs, so drug-alone effect sizes in routine practice run smaller.
This is human, approval-grade evidence. Semaglutide is a licensed glucose-lowering agent in both subcutaneous (Ozempic) and oral (Rybelsus) form. It lowers HbA1c glucose-dependently — enhancing insulin secretion, suppressing glucagon and slowing gastric emptying — with weight loss as a co-benefit. STEP 2 confirmed both the glycemic and weight effects in adults with type 2 diabetes 2Reference 2RCTSemaglutide 2·4 mg once a week in adults with overweight or obesity, and type 2 diabetes (STEP 2) — human (RCT)View study →, and glycemic efficacy is established across the SUSTAIN (subcutaneous) and PIONEER (oral) phase 3 programs that underpin the diabetes approvals 8,
Gap: none for the approved indication. The practical limits are gastrointestinal tolerability during escalation and the formulation constraint — there is no ordinary oral route (see Pharmacokinetics) — not efficacy.
This is human, approval-grade evidence. In SELECT (n≈17,600 adults with established cardiovascular disease and obesity but without diabetes), weekly semaglutide 2.4 mg reduced the composite of cardiovascular death, non-fatal myocardial infarction and non-fatal stroke versus placebo 10Reference 10RCTSemaglutide and Cardiovascular Outcomes in Obesity without Diabetes (SELECT) — human (RCT)View study → — the basis for the cardiovascular-risk indication in obesity. In type 2 diabetes, SUSTAIN-6 first showed a reduction in major adverse cardiovascular events with subcutaneous semaglutide 8Reference 8RCTSemaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes (SUSTAIN-6) — human (RCT)View study →, and PIONEER-6 established cardiovascular safety (non-inferiority) for oral semaglutide 9Reference 9RCTOral Semaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes (PIONEER-6) — human (RCT)View study →.
The oral 25 mg product approved for weight management in the US in late 2025 carries the cardiovascular-risk indication as well.
Gap: SUSTAIN-6 was designed as a safety (non-inferiority) trial, and it flagged a signal of worsening diabetic retinopathy complications — a genuine label-carried caveat, most plausibly tied to rapid glycemic improvement rather than a direct drug effect, but unresolved.
This is human, approval-grade evidence from a single dedicated outcome trial. In the phase 3 FLOW RCT (adults with type 2 diabetes and chronic kidney disease), weekly semaglutide reduced the risk of major kidney-disease events — kidney-function decline, kidney failure and cardiovascular death — by roughly a quarter versus placebo, and slowed the rate of eGFR decline 11Reference 11RCTEffects of Semaglutide on Chronic Kidney Disease in Patients with Type 2 Diabetes (FLOW) — human (RCT)View study →. The FDA approved the corresponding indication in January 2025.
Gap: FLOW enrolled type 2 diabetes with CKD. Benefit in non-diabetic kidney disease is not established by any dedicated trial, and the indication does not extend there.
This is human, biopsy-endpoint evidence. A phase 2 RCT first showed higher rates of NASH resolution with subcutaneous semaglutide than placebo, but without a significant improvement in fibrosis stage 13Reference 13RCTA Placebo-Controlled Trial of Subcutaneous Semaglutide in Nonalcoholic Steatohepatitis — human (RCT, phase 2)View study →.
The phase 3 ESSENCE trial in metabolic dysfunction-associated steatohepatitis then reported significant improvement in both steatohepatitis resolution (about 63% vs 34% on placebo) and fibrosis on liver biopsy 14Reference 14RCTPhase 3 Trial of Semaglutide in Metabolic Dysfunction-Associated Steatohepatitis (ESSENCE) — human (RCT)View study →.
On that basis semaglutide received accelerated approval in August 2025 for non-cirrhotic MASH with moderate-to-advanced (F2–F3) fibrosis — the first GLP-1 receptor agonist licensed for the indication.
Gap: this is an accelerated approval on histological surrogates. Hard liver outcomes — progression to cirrhosis, decompensation, transplant, death — are still maturing from the ESSENCE extension, and the phase 2 fibrosis miss is a reminder that these endpoints are demanding. Cirrhotic MASH is outside the indication.
This is a genuine human RCT with soft endpoints. In STEP-HFpEF, adults with obesity-related heart failure with preserved ejection fraction who received weekly semaglutide 2.4 mg had greater improvement in symptoms (KCCQ clinical summary score) and exercise capacity (6-minute walk distance), plus substantial weight loss, versus placebo 12Reference 12RCTSemaglutide in Patients with Heart Failure with Preserved Ejection Fraction and Obesity (STEP-HFpEF) — human (RCT)View study →.
Gap: the trial was not powered for mortality or hospitalization. The benefit is demonstrated on symptom and functional scales, in an obesity-phenotype HFpEF population — it does not establish that semaglutide prevents heart-failure events.
This is a single human phase 3 RCT. In STRIDE (n=792 adults with type 2 diabetes and symptomatic peripheral artery disease with claudication), semaglutide 1 mg weekly improved maximum walking distance by about 13% over placebo at 52 weeks, with gains in pain-free walking distance and quality of life 15Reference 15RCTSemaglutide and walking capacity in people with symptomatic peripheral artery disease and type 2 diabetes (STRIDE) — human (RCT)View study →. The EU regulator recommended a corresponding indication for Ozempic; the US decision was pending as of this check.
Gap: one trial, restricted to people who also have type 2 diabetes, with a functional (walking-distance) endpoint. There is no evidence yet on hard limb outcomes — revascularization, amputation — or on PAD without diabetes.
This is a single human phase 3 RCT and not an approved indication. In STEP 9, adults with obesity and knee osteoarthritis given weekly semaglutide 2.4 mg reported greater reduction in WOMAC pain scores and better physical function than placebo over 68 weeks, alongside about 14% weight loss 16Reference 16RCTOnce-Weekly Semaglutide in Persons with Obesity and Knee Osteoarthritis (STEP 9) — human (RCT)View study →.
Gap: the pain benefit is plausibly mediated by weight loss rather than any joint-specific action, and the trial cannot separate the two. No structural (cartilage, radiographic) endpoints, one trial, and no licensed osteoarthritis indication anywhere.
This row exists to record evidence against, which is worth as much as evidence for. Large observational and preclinical work had suggested GLP-1 agonists might be neuroprotective, and the evoke and evoke+ phase 3 trials tested oral semaglutide 14 mg (flexible dose) in early-stage symptomatic Alzheimer’s disease. They read out in 2026 showing no meaningful improvement on the primary cognitive/functional endpoint 18Reference 18RCTEfficacy and safety of oral semaglutide 14 mg (flexible dose) in early-stage symptomatic Alzheimer’s disease (evoke and evoke+) — human (RCT, negative)View study →.
Gap: none in the usual sense — this is a well-powered human null, and the correct conclusion is that semaglutide should not be used or sold for Alzheimer’s disease. Whether GLP-1 agonism has any role in earlier (pre-symptomatic) neurodegeneration, or in Parkinson’s disease where trials continue, remains open — but the burden of proof has moved substantially.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| GLP-1 receptor (pancreatic β-cell) | ↑ glucose-dependent insulin secretion | Diabetesweight |
| GLP-1 receptor (pancreatic α-cell) | ↓ glucagon secretion | Diabetes |
| GLP-1 receptor (hypothalamic / hindbrain appetite centers) | ↓ appetite, ↑ satiety | WeightMASHHFpEFosteoarthritis pain |
| Gastric motility | Slowed gastric emptying | Glycemic excursions; GI adverse effects; anesthesia aspiration risk |
| Hepatic fat & inflammation (largely weight-mediated) | ↓ steatosis, ↓ steatohepatitis, ↓ fibrosis | MASH |
| Cardiovascular / renal (weight-, glycemia- and possibly anti-inflammatory-mediated) | ↓ MACE, slowed eGFR decline | CVDCKDPAD |
| Mesolimbic reward signaling | ↓ appetitive/consummatory drive (observational human signal only) | Alcohol and substance use — investigational |
| DPP-4 resistance (Aib8) + albumin binding (C18 diacid) | Prolonged half-life | Weekly dosing (PK) |
Pharmacokinetics
Route is load-bearing. Semaglutide is effective only as a once-weekly subcutaneous injection (Ozempic, Wegovy) or a specially formulated daily oral tablet. Oral delivery works at all only because the tablet co-formulates the absorption enhancer SNAC (salcaprozate sodium) and must be taken fasting with minimal water and a wait before eating; bioavailability by that route is still on the order of ~1%, which is why the doses differ so wildly between forms (2.4 mg weekly injected versus 25 mg daily oral for the same indication). Unformulated oral peptide is digested, not absorbed — an important point for anyone offered “oral semaglutide” outside a licensed tablet.
Half-life is about one week (~165 h), driven by albumin binding through the fatty-diacid linker and by DPP-4 resistance from the Aib8 substitution. That is what permits weekly dosing, and it is also why dose titration is slow and deliberate: escalating faster than the label schedule is the main driver of gastrointestinal intolerance, and why washout before a planned pregnancy takes weeks rather than days. Elimination is by proteolytic cleavage and fatty-acid β-oxidation, with no single organ dominating clearance — so no dose adjustment is required for renal or hepatic impairment.
Licensed subcutaneous product is supplied as a sterile, refrigerated solution in prefilled pens; cold chain and in-use stability are part of the product specification, and this connects directly to the sourcing problems below — a self-reconstituted lyophilized powder has none of those guarantees.
Clinical & regulatory status
Semaglutide is an approved prescription medicine (Novo Nordisk), not a dietary supplement and not a research chemical. Licensed forms are Ozempic (subcutaneous, type 2 diabetes), Rybelsus (oral, type 2 diabetes) and Wegovy (subcutaneous, and since late 2025 an oral 25 mg tablet, for chronic weight management). Indications have expanded steadily: cardiovascular-risk reduction in established CVD with obesity (2024), chronic kidney disease in type 2 diabetes (FDA, January 2025), non-cirrhotic MASH with F2–F3 fibrosis (FDA accelerated approval, August 2025), and adolescent obesity from age 12. The EU regulator recommended a peripheral arterial disease indication for Ozempic on the strength of STRIDE; the corresponding US decision was pending at the time of this check. It is prescription-only but not a scheduled/controlled substance.
Registered trial activity remains among the largest for any single molecule, spanning the approved indications plus Parkinson’s disease, alcohol and substance use disorders, pediatric populations and further cardiometabolic outcomes. The headline completed program of the last year is the evoke/evoke+ Alzheimer’s readout, which was negative 18Reference 18RCTEfficacy and safety of oral semaglutide 14 mg (flexible dose) in early-stage symptomatic Alzheimer’s disease (evoke and evoke+) — human (RCT, negative)View study →.
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 30+phase 3 (SUSTAIN, STEP, PIONEER, OASIS, SELECT, FLOW, STEP-HFpEF, ESSENCE, STRIDE, evoke) | many(neuro, cardiometabolic, addiction, pediatric) | few | extensive(foundational GLP-1 biology) |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. Semaglutide is an approved prescription pharmaceutical, prescription-only and unscheduled. That status is the whole frame for this section: everything below concerns the substantial volume of semaglutide that reaches people outside the prescription channel.
How it’s supplied & administered. Licensed product is a sterile refrigerated solution in prefilled multi-dose pens (subcutaneous), or a fasting-state oral tablet co-formulated with SNAC. Dosing is clinician-titrated and deliberately slow, starting low and escalating over weeks specifically to limit gastrointestinal effects. Gray-market and “research use only” semaglutide, by contrast, is typically sold as a lyophilized powder requiring reconstitution with bacteriostatic water, leaving the user to perform the sterile handling, the concentration arithmetic and the dose measurement that a licensed pen is engineered to remove.
The compounding situation has changed, and this is the biggest delta of the last year. During the 2022–2024 shortages, US compounding pharmacies were permitted to prepare semaglutide, and an enormous telehealth market grew on that allowance. The FDA declared the injectable semaglutide shortage resolved in February 2025, which ended the exemption: 503A pharmacies had to stop compounding by April 2025 and 503B outsourcing facilities by May 2025, since neither may produce what is “essentially a copy” of an available approved drug. Enforcement followed — large-scale warning letters to compounders and telehealth firms, the exit of the major telehealth platforms from compounded semaglutide, and a 2026 FDA proposal to remove semaglutide from the 503B bulk-substances list altogether. Compounded semaglutide has accordingly moved from a widely available gray channel to a largely unlawful one, while demand did not fall with it — which pushes buyers toward worse sources, not better ones.
Sourcing reality (a safety issue, not a footnote). Semaglutide now circulates outside the licensed channel through “research chemical” vials sold online labeled not for human consumption, through remaining compounded preparations of contested legality, and through outright counterfeits. All three sit outside manufacturing oversight, and the documented failure modes are concrete: mislabeling (wrong peptide, wrong quantity, or a salt form never shown to be equivalent), sub- or super-potency, endotoxin and sterility failures, and no cold chain. An analysis of compounded products found they use formulations that differ from the licensed drug, with efficacy and safety largely unstudied 31Reference 31Compounded Semaglutide and Tirzepatide Products Use Unique Formulations but Efficacy and Safety Largely Unknown — editorial / product analysisView study →. Pharmacovigilance analysis of European adverse-event data specifically on counterfeit semaglutide has documented harm traceable to falsified product 30Reference 30Unmasking counterfeit semaglutide: analysis of real-world safety data from EudraVigilance — human (pharmacovigilance)View study →, and case reports include euglycemic ketoacidosis following counterfeit use and severe events after dosing errors with self-measured product. Third-party certificates of analysis are the minimum any buyer would want, but a COA from an unaccountable vendor is itself unverifiable.
This page does not recommend or link vendors. The efficacy and safety record described above belongs to pharmaceutical-grade drug used under medical supervision, and it does not transfer to material of unknown provenance.
Safety
Semaglutide is a prescription medicine with an approval-grade trial record, and its risks are correspondingly well characterized: gastrointestinal side effects dominate day to day, but the label-level constraints — a boxed thyroid C-cell warning, pancreatitis and gallbladder events, and a very rare sudden vision loss — are what decide who should not take it.
- Boxed warning for thyroid C-cell tumors. Contraindicated with a personal or family history of medullary thyroid carcinoma or MEN 2.
- Sudden vision loss (NAION). A very rare side effect, up to about 1 in 10,000 — rapidly worsening eyesight is an urgent medical problem.
- Pancreatitis and gallbladder events. Reported in trials; a history of pancreatitis is a reason to avoid.
- Not recommended in pregnancy. Discontinue ahead of a planned pregnancy — see the box below.
- Tell your anesthetist before any sedation or surgery. Delayed gastric emptying raises the aspiration risk despite standard fasting.
- Interacts with insulin and sulfonylureas. Additive hypoglycemia; these commonly need dose reduction.
Full Safety & Interactions Detail
Adverse effects (from trials). The dominant, dose-limiting effects are gastrointestinal — nausea, vomiting, diarrhea, constipation — usually worst during dose escalation and substantially mitigated by slow titration. A large comparative analysis in type 2 diabetes confirms the GI burden and ranks it against other incretins 23Reference 23ObservationalComparative Gastrointestinal Safety of Dulaglutide, Semaglutide, and Tirzepatide in Adults With Type 2 Diabetes — human (cohort)View study →. Gallbladder events (cholelithiasis) and acute pancreatitis are reported. In the diabetes cardiovascular-outcome setting, a signal of worsening diabetic retinopathy appeared in SUSTAIN-6 8Reference 8RCTSemaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes (SUSTAIN-6) — human (RCT)View study → and is carried on the label. Injectable use adds injection-site reactions, and — for reconstituted gray-market powder — sterility and dosing-error risk that licensed pens are designed to prevent.
Boxed warning. Semaglutide carries a boxed warning for thyroid C-cell tumors (medullary thyroid carcinoma) observed in rodents, and is contraindicated in anyone with a personal or family history of medullary thyroid carcinoma or Multiple Endocrine Neoplasia syndrome type 2 (MEN 2). The rodent finding has not been established in humans, but the contraindication is absolute in practice.
NAION — the significant new safety signal. Non-arteritic anterior ischemic optic neuropathy is a sudden, painless, usually irreversible loss of vision in one eye. Following observational reports of an increased rate in semaglutide users, the EMA’s pharmacovigilance committee concluded in June 2025 that NAION is a very rare side effect (up to about 1 in 10,000) of semaglutide medicines, and product information was updated accordingly; the WHO issued a corresponding statement. The evidence has continued to accumulate and remains genuinely mixed: two large 2026 analyses published together — a nationwide cohort study 21Reference 21ObservationalGlucagon-like Peptide-1 Receptor Agonists and Risk for Anterior Ischemic Optic Neuropathy: A Nationwide Cohort Study — human (cohort)View study → and a target-trial-emulation study 22Reference 22ObservationalGlucagon-Like Peptide-1 Receptor Agonists and Risk for Ischemic Optic Neuropathy: A Target Trial Emulation — human (cohort)View study → — refine the risk estimate, and at least one earlier ophthalmology paper on the question has since been retracted, so this is an area where individual reports should be treated with care. The practical guidance is unambiguous regardless of effect size: sudden vision loss or rapidly worsening eyesight during treatment is an urgent medical problem and warrants immediate contact with a clinician.
Delayed gastric emptying and anesthesia. Because semaglutide slows gastric emptying by design, retained stomach contents at induction of anesthesia are a documented aspiration concern. A prospective multicenter gastric-ultrasound study found a higher rate of residual gastric content in semaglutide users than matched controls despite standard fasting 24Reference 24Clinical trialGastric ultrasound in patients receiving semaglutide: a prospective, multicentre, matched control study — human (prospective)View study →, and peri-procedural guidance in several jurisdictions now addresses this. Anyone taking semaglutide should tell the anesthetist or proceduralist before any sedation or surgery.
Body composition. Weight lost on semaglutide includes lean mass, not only fat. A dedicated body-composition study reported the fat/lean split and muscle-function outcomes in people with obesity 25Reference 25Clinical trialImpact of semaglutide on fat mass, lean mass and muscle function in patients with obesity (SEMALEAN) — human (clinical study)View study →, and a systematic review comparing incretin-based with non-pharmacological weight loss found lean-mass loss broadly proportionate to the total loss rather than disproportionate 26Reference 26Systematic reviewEffect of Incretin-Based and Nonpharmacologic Weight Loss on Body Composition: A Systematic Review — human (systematic review)View study →. The clinically sensible response — adequate protein intake and resistance training during weight loss — is standard advice rather than a trial-proven mitigation for this drug.
Psychiatric signals. Early pharmacovigilance concern about suicidality has not been borne out: a systematic review of GLP-1 receptor agonists and suicidality found no consistent evidence of increased risk 28Reference 28Systematic reviewAssociation Between Glucagon-Like Peptide-1 Receptor Agonists and Suicidality: A Systematic Review — human (systematic review)View study →. Separately, and in the opposite direction, observational data associate GLP-1 agonist use with reduced alcohol- and substance-use-related hospital admissions 29Reference 29ObservationalAssociation of GLP-1 receptor agonists with alcohol use disorder-related and substance use disorder-related hospital admissions — human (observational)View study → — an interesting signal, but observational, confounded, and not a basis for prescribing semaglutide for addiction.
Interactions. The clinically important, mechanism-based interactions are with insulin and sulfonylureas (additive hypoglycemia — these commonly need dose reduction), and, through delayed gastric emptying, potential effects on the timing and absorption of other oral medications. The anesthesia/aspiration issue above is the other mechanism-based caution. A full interaction census should be taken from the current label, not from here.
Who should avoid it. Anyone with a personal or family history of medullary thyroid carcinoma or MEN 2 (contraindicated); anyone with a history of pancreatitis; and — outside a supervised prescription — anyone who cannot guarantee product identity, sterility and correct dosing.
Scope disclosure (honesty, not a claim):
- Human data? Yes — extensive, approval-grade phase 3 RCTs across weight, diabetes, cardiovascular, renal, hepatic, heart-failure and limb outcomes, plus a well-powered negative trial in Alzheimer’s disease.
- Interactions assessed? Partially. The mechanism-based ones (insulin/sulfonylurea hypoglycemia, delayed gastric emptying affecting oral absorption, peri-procedural aspiration) are established; a complete drug-interaction census belongs to the current FDA/EMA label.
- Pregnancy/lactation assessed? At label level — not recommended in pregnancy, limited lactation data. Human outcome data are early and observational.
- Long-term safety established? Multi-year trial data exist (STEP 5 to two years; cardiovascular-outcome trials over several years), but decade-scale safety, safety of indefinite use for weight maintenance, and the safety of off-label or gray-market use are not established.
Never imply safety from silence — and never transfer this trial record to unlicensed product. Everything above describes pharmaceutical-grade semaglutide used as prescribed.
Not recommended in pregnancy. The label advises discontinuation ahead of a planned pregnancy, allowing for the long half-life (weeks of washout), on the basis of animal reproductive-toxicity findings; human pregnancy safety is not established and lactation data are limited. Human evidence is beginning to accrue — a 2026 cohort examined gestational weight gain and pregnancy outcomes after semaglutide exposure 27Reference 27ObservationalGestational Weight Gain and Pregnancy Outcomes After Semaglutide Exposure — human (cohort)View study → — but it is observational, small relative to the exposed population, and does not change the label position. Semaglutide also reduces the efficacy of oral contraceptives indirectly in some settings by altering absorption, and weight loss itself can restore fertility in people who did not expect it; unintended pregnancy on treatment is a real scenario worth planning for.
Dosage
Semaglutide is a prescription medicine that is dosed and titrated by a clinician. Nothing here is a recommendation, and it must not be self-sourced or self-dosed. The figures below are reported as trial and label data for context.
For chronic weight management, the STEP program escalated to 2.4 mg once weekly by subcutaneous injection over roughly 16 weeks 1Reference 1RCTOnce-Weekly Semaglutide in Adults with Overweight or Obesity (STEP 1) — human (RCT)View study →, and the oral form approved for the same indication is 25 mg once daily 20Reference 20Efficacy, Safety and Pharmacokinetics of Once-Daily Oral Semaglutide 25 mg for Obesity With and Without Type 2 Diabetes — human (comparative analysis)View study →. For type 2 diabetes, subcutaneous dosing runs 0.5–2.0 mg once weekly and oral Rybelsus 7–14 mg once daily; the STRIDE peripheral-artery-disease trial used 1 mg weekly 15Reference 15RCTSemaglutide and walking capacity in people with symptomatic peripheral artery disease and type 2 diabetes (STRIDE) — human (RCT)View study →. Oral tablets must be taken fasting, with a small sip of water and a wait before eating or taking other medicines — the SNAC absorption enhancer only works under those conditions.
The titration schedule is not a formality. Escalating faster than the label sequence is the main cause of severe gastrointestinal effects, and the case literature includes gastroparesis and obstruction associated with rapid escalation. “Microdosing” — the practice of using sub-therapeutic amounts indefinitely, common in the compounded and gray markets — has no trial evidence at all; it is extrapolation from a dose-response curve that was never studied at those doses. This entry is informational only.
References
- Wilding JPH, et al. (2021). Once-Weekly Semaglutide in Adults with Overweight or Obesity (STEP 1) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/33567185/
- Davies M, et al. (2021). Semaglutide 2·4 mg once a week in adults with overweight or obesity, and type 2 diabetes (STEP 2) — human (RCT). Lancet. https://pubmed.ncbi.nlm.nih.gov/33667417/
- Wadden TA, et al. (2021). Effect of Subcutaneous Semaglutide vs Placebo as an Adjunct to Intensive Behavioral Therapy on Body Weight (STEP 3) — human (RCT). JAMA. https://pubmed.ncbi.nlm.nih.gov/33625476/
- Rubino D, et al. (2021). Effect of Continued Weekly Subcutaneous Semaglutide vs Placebo on Weight Loss Maintenance (STEP 4) — human (RCT). JAMA. https://pubmed.ncbi.nlm.nih.gov/33755728/
- Garvey WT, et al. (2022). Two-year effects of semaglutide in adults with overweight or obesity (STEP 5) — human (RCT). Nat Med. https://pubmed.ncbi.nlm.nih.gov/36216945/
- Rubino DM, et al. (2022). Effect of Weekly Subcutaneous Semaglutide vs Daily Liraglutide on Body Weight (STEP 8) — human (RCT). JAMA. https://pubmed.ncbi.nlm.nih.gov/35015037/
- Knop FK, et al. (2023). Oral semaglutide 50 mg taken once per day in adults with overweight or obesity (OASIS 1) — human (RCT). Lancet. https://pubmed.ncbi.nlm.nih.gov/37385278/
- Marso SP, et al. (2016). Semaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes (SUSTAIN-6) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/27633186/
- Husain M, et al. (2019). Oral Semaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes (PIONEER-6) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/31185157/
- Lincoff AM, et al. (2023). Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes (SELECT) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/37952131/
- Perkovic V, et al. (2024). Effects of Semaglutide on Chronic Kidney Disease in Patients with Type 2 Diabetes (FLOW) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/38785209/
- Kosiborod MN, et al. (2023). Semaglutide in Patients with Heart Failure with Preserved Ejection Fraction and Obesity (STEP-HFpEF) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/37622681/
- Newsome PN, et al. (2021). A Placebo-Controlled Trial of Subcutaneous Semaglutide in Nonalcoholic Steatohepatitis — human (RCT, phase 2). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/33185364/
- Sanyal AJ, et al. (2025). Phase 3 Trial of Semaglutide in Metabolic Dysfunction-Associated Steatohepatitis (ESSENCE) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/40305708/
- Bonaca MP, et al. (2025). Semaglutide and walking capacity in people with symptomatic peripheral artery disease and type 2 diabetes (STRIDE) — human (RCT). Lancet. https://pubmed.ncbi.nlm.nih.gov/40169145/
- Bliddal H, et al. (2024). Once-Weekly Semaglutide in Persons with Obesity and Knee Osteoarthritis (STEP 9) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/39476339/
- Weghuber D, et al. (2022). Once-Weekly Semaglutide in Adolescents with Obesity (STEP TEENS) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/36322838/
- Cummings JL, et al. (2026). Efficacy and safety of oral semaglutide 14 mg (flexible dose) in early-stage symptomatic Alzheimer’s disease (evoke and evoke+) — human (RCT, negative). Lancet. https://pubmed.ncbi.nlm.nih.gov/41865758/
- Wilding JPH, et al. (2022). Weight regain and cardiometabolic effects after withdrawal of semaglutide: the STEP 1 trial extension — human (RCT extension). Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/35441470/
- Overgaard RV, et al. (2026). Efficacy, Safety and Pharmacokinetics of Once-Daily Oral Semaglutide 25 mg for Obesity With and Without Type 2 Diabetes — human (comparative analysis). Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/42023428/
- Ueda P, et al. (2026). Glucagon-like Peptide-1 Receptor Agonists and Risk for Anterior Ischemic Optic Neuropathy: A Nationwide Cohort Study — human (cohort). Ann Intern Med. https://pubmed.ncbi.nlm.nih.gov/42441962/
- Reynolds KR, et al. (2026). Glucagon-Like Peptide-1 Receptor Agonists and Risk for Ischemic Optic Neuropathy: A Target Trial Emulation — human (cohort). Ann Intern Med. https://pubmed.ncbi.nlm.nih.gov/42441967/
- Crisafulli S, et al. (2026). Comparative Gastrointestinal Safety of Dulaglutide, Semaglutide, and Tirzepatide in Adults With Type 2 Diabetes — human (cohort). Ann Intern Med. https://pubmed.ncbi.nlm.nih.gov/41183330/
- Vlaeminck N, et al. (2026). Gastric ultrasound in patients receiving semaglutide: a prospective, multicentre, matched control study — human (prospective). Anaesthesia. https://pubmed.ncbi.nlm.nih.gov/41631344/
- Alissou M, et al. (2026). Impact of semaglutide on fat mass, lean mass and muscle function in patients with obesity (SEMALEAN) — human (clinical study). Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/41068996/
- Batsis JA, et al. (2026). Effect of Incretin-Based and Nonpharmacologic Weight Loss on Body Composition: A Systematic Review — human (systematic review). Ann Intern Med. https://pubmed.ncbi.nlm.nih.gov/41996180/
- Yu Y, et al. (2026). Gestational Weight Gain and Pregnancy Outcomes After Semaglutide Exposure — human (cohort). Obstet Gynecol. https://pubmed.ncbi.nlm.nih.gov/42208070/
- Chan TH, et al. (2026). Association Between Glucagon-Like Peptide-1 Receptor Agonists and Suicidality: A Systematic Review — human (systematic review). Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/42150748/
- Bach P, et al. (2026). Association of GLP-1 receptor agonists with alcohol use disorder-related and substance use disorder-related hospital admissions — human (observational). Lancet Psychiatry. https://pubmed.ncbi.nlm.nih.gov/42456704/
- Zinzi A, et al. (2026). Unmasking counterfeit semaglutide: analysis of real-world safety data from EudraVigilance — human (pharmacovigilance). Front Pharmacol. https://pubmed.ncbi.nlm.nih.gov/42137313/
- Belcourt J, et al. (2026). Compounded Semaglutide and Tirzepatide Products Use Unique Formulations but Efficacy and Safety Largely Unknown — editorial / product analysis. Ann Pharmacother. https://pubmed.ncbi.nlm.nih.gov/41689811/
- Knudsen, L. B., & Lau, J. (2019). The discovery and development of liraglutide and semaglutide. Frontiers in Endocrinology, 10, 155. https://pmc.ncbi.nlm.nih.gov/articles/PMC6474072/



