
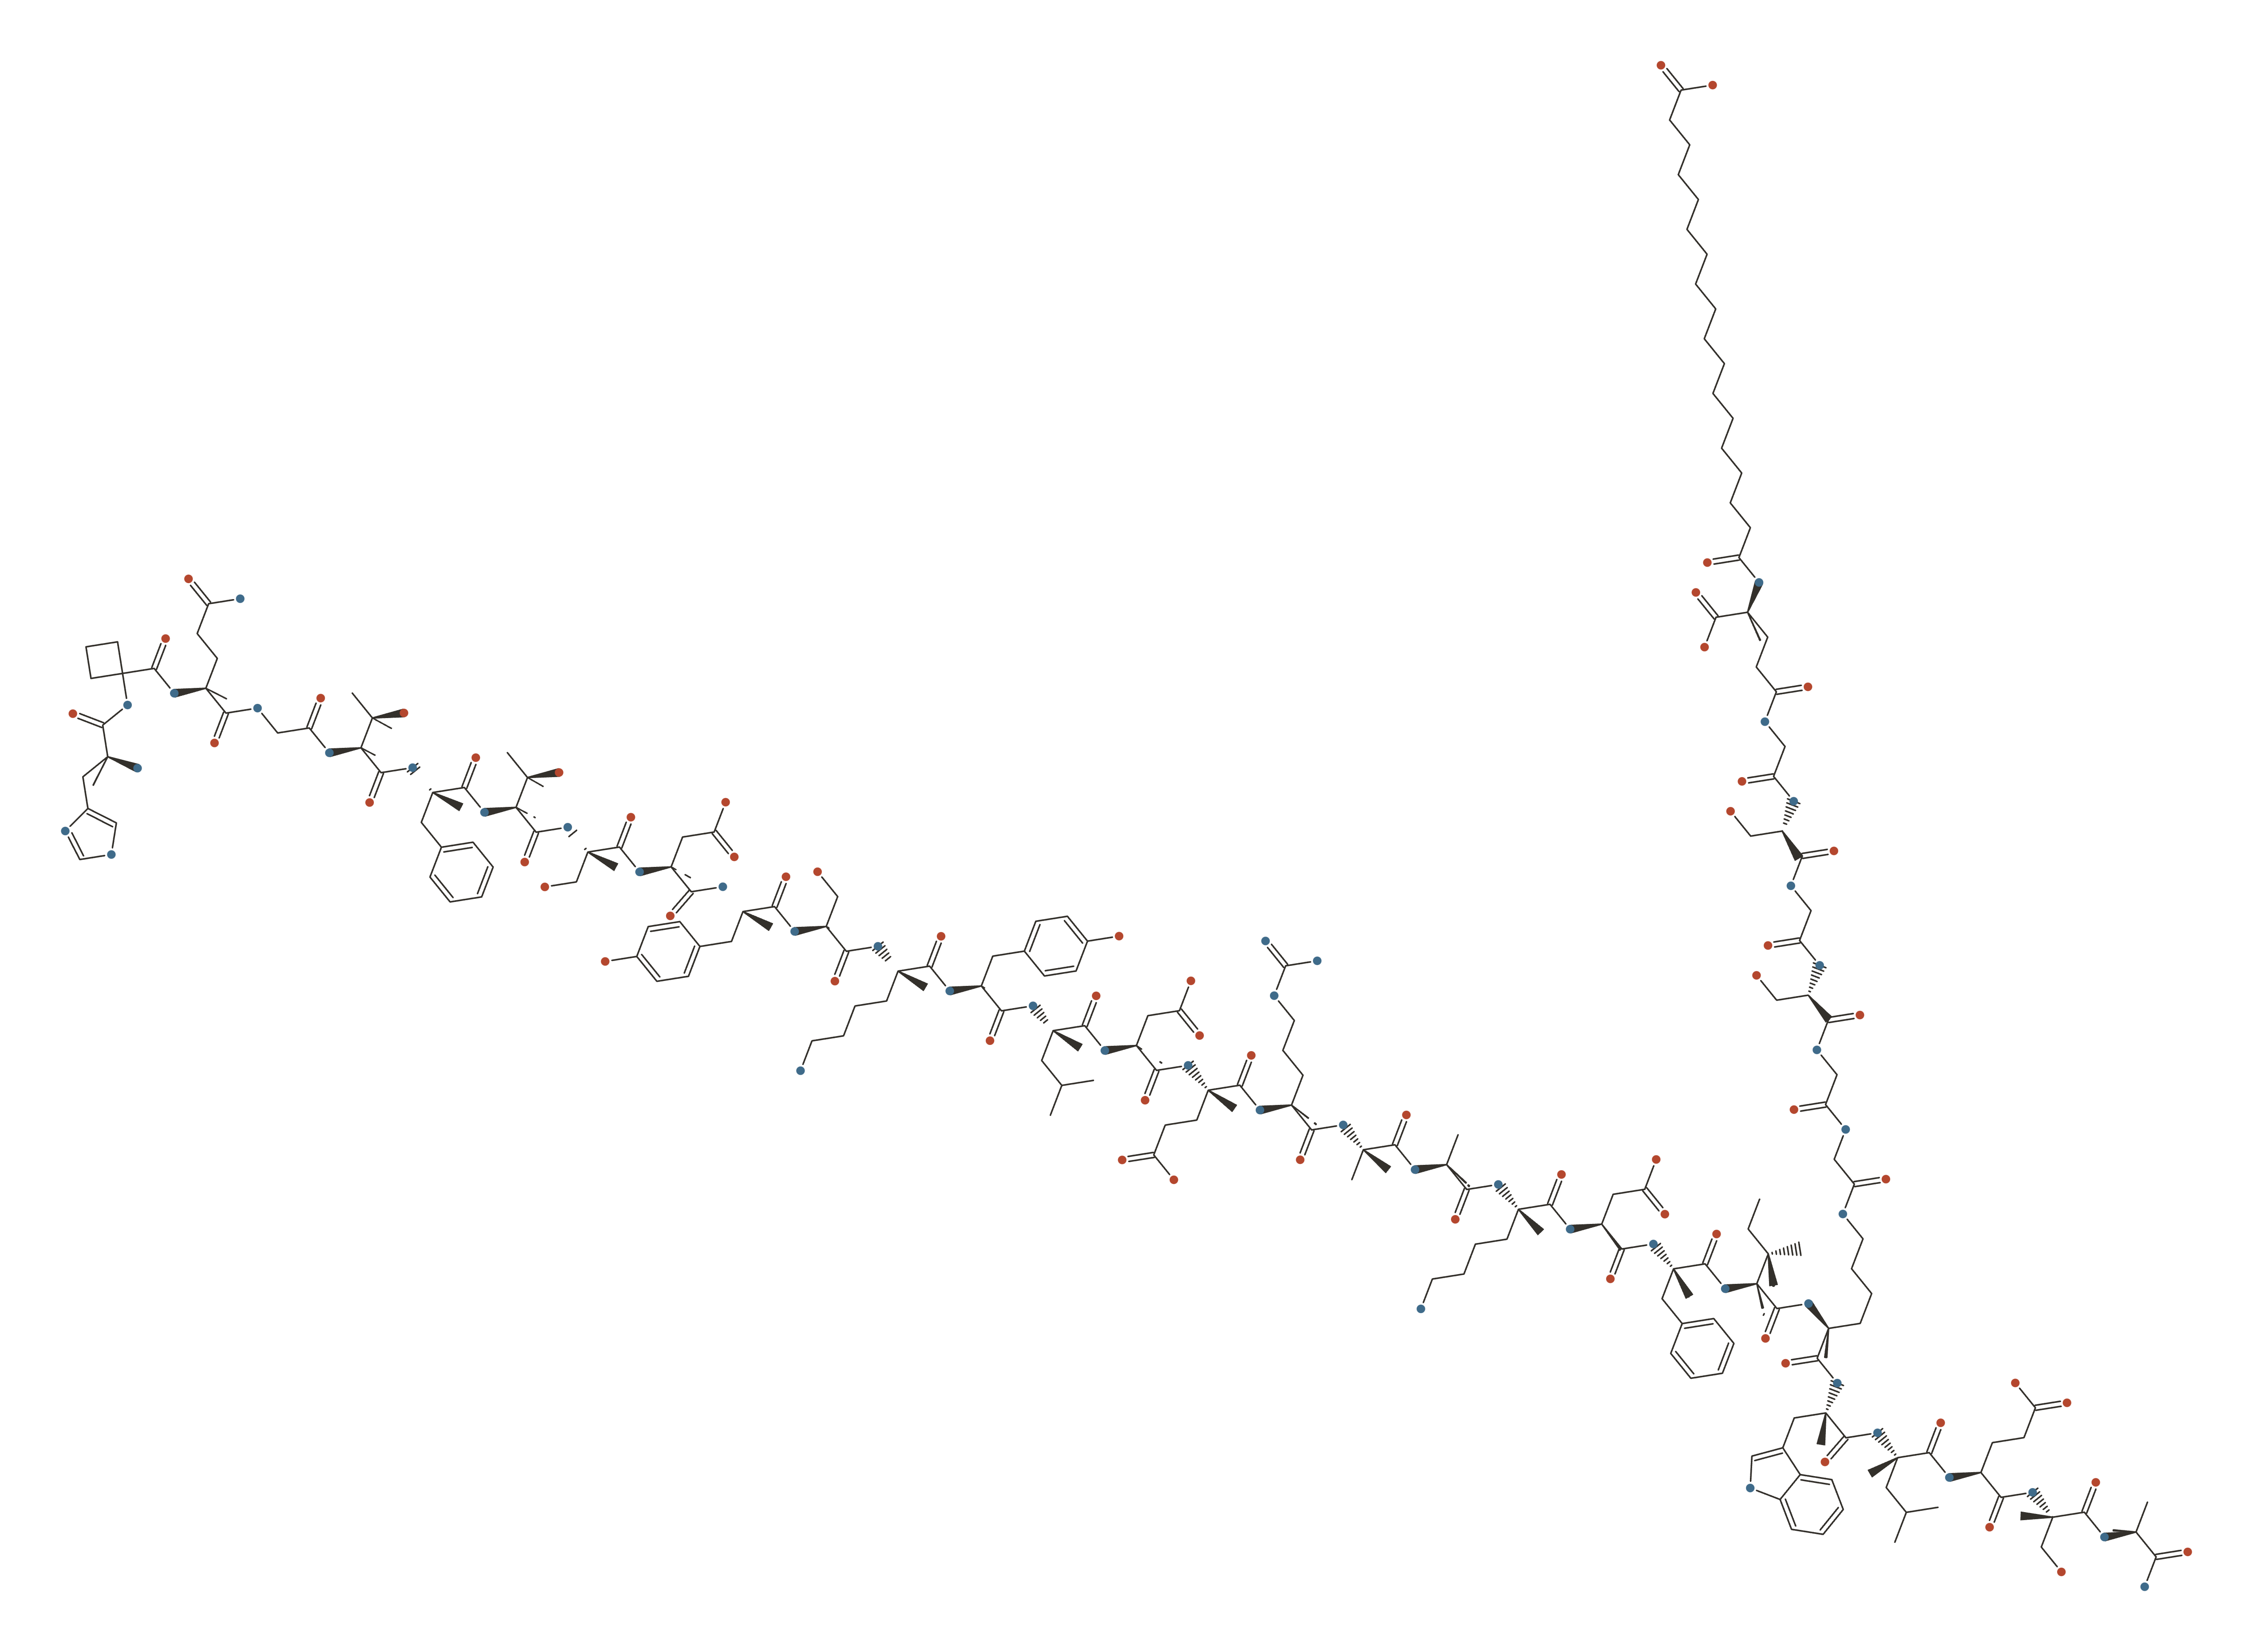
Survodutide
An investigational once-weekly injectable glucagon/GLP-1 receptor dual agonist in phase 3 trials for obesity and MASH. Not approved anywhere.

Survodutide at a Glance
Survodutide is a dual glucagon/GLP-1 receptor agonist given once weekly, pairing appetite suppression and improved insulin response with the increased energy expenditure that glucagon-receptor activation produces. Its development has focused on obesity and, notably, on liver disease — glucagon agonism acts directly on hepatocytes, which gives this combination a mechanistic rationale in steatohepatitis that pure GLP-1 agonists lack. It is investigational and in phase 3.
History & Development
Survodutide adds glucagon to the incretin recipe - a counterintuitive move, since glucagon raises blood sugar, and the reason the compound is being tested as hard in liver disease as in obesity.
| First described | Discovery and preclinical pharmacology published 2022, as BI 456906 15Reference 15BI 456906: discovery and preclinical pharmacology of a novel GCGR/GLP-1R dual agonist with robust anti-obesity efficacyView study → |
| Discovered / synthesised by | Originated at Zealand Pharma; developed by Boehringer Ingelheim 15, |
| Institution | Zealand Pharma (origination); Boehringer Ingelheim (development) 16Reference 16Survodutide (BI 456906) trial programme, sponsor Boehringer Ingelheim - including NCT04667377 (phase 2) and the SYNCHRONIZE phase 3 trialsView study → |
| Origin | De-novo synthetic peptide; dual agonist at the glucagon (GCGR) and GLP-1 receptors |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Licensed to Boehringer Ingelheim from Zealand Pharma 16Reference 16Survodutide (BI 456906) trial programme, sponsor Boehringer Ingelheim - including NCT04667377 (phase 2) and the SYNCHRONIZE phase 3 trialsView study → |
| Development status | Investigational - phase 3 (SYNCHRONIZE programme); not approved anywhere 16Reference 16Survodutide (BI 456906) trial programme, sponsor Boehringer Ingelheim - including NCT04667377 (phase 2) and the SYNCHRONIZE phase 3 trialsView study → |
Discovery
The design question was what to add to GLP-1. Glucagon looks like the wrong partner - it is the hormone that raises blood glucose, the opposite of what a diabetes drug wants - but it also increases energy expenditure and acts directly on hepatocytes. Combined with GLP-1’s appetite suppression and glucose-dependent insulin release, the glucose effect is offset while the energy expenditure is kept.
The discovery and preclinical pharmacology of the compound were published in 2022 under its development code BI 456906, describing a GCGR/GLP-1R dual agonist with robust anti-obesity efficacy in preclinical models 15Reference 15BI 456906: discovery and preclinical pharmacology of a novel GCGR/GLP-1R dual agonist with robust anti-obesity efficacyView study →.
The hepatic action is what distinguishes this compound from the GLP-1 and GIP agonists. Glucagon receptors are abundant on liver cells, which gives survodutide a mechanistic rationale in metabolic dysfunction-associated steatohepatitis that pure incretin agonists lack - and that is now a major arm of its development.
Development & ownership
Survodutide originated at Zealand Pharma and is licensed to Boehringer Ingelheim, which is solely responsible for development and commercialisation globally 16Reference 16Survodutide (BI 456906) trial programme, sponsor Boehringer Ingelheim - including NCT04667377 (phase 2) and the SYNCHRONIZE phase 3 trialsView study →. That split - a Danish peptide specialist originating the molecule, a large pharmaceutical company developing it - is a common shape in this field and is worth stating, since the compound is frequently attributed to Boehringer alone.
It has completed phase 2 trials in obesity, type 2 diabetes and biopsy-confirmed MASH, and is in phase 3 under the SYNCHRONIZE programme, including SYNCHRONIZE-1 in obesity without type 2 diabetes and SYNCHRONIZE-MASLD in obesity with steatotic liver disease 16Reference 16Survodutide (BI 456906) trial programme, sponsor Boehringer Ingelheim - including NCT04667377 (phase 2) and the SYNCHRONIZE phase 3 trialsView study →.
It is not approved by the FDA, the EMA or any other regulator, for any indication, anywhere.
How it reached the market
It has not. Survodutide is investigational and available only through clinical trials - there is no approved product and no legitimate commercial supply. Its appearance in grey-market peptide channels, where investigational GLP-1-class compounds are increasingly sold ahead of approval, is supply without any of the dose, purity or safety oversight that a trial provides.
What It's Used For
Survodutide (BI 456906) is an investigational drug. It is not approved by the FDA, the EMA, or any other regulator, for any indication, anywhere in the world — and that status, not the weight-loss numbers, is the first thing to understand about it. It is Boehringer Ingelheim’s dual receptor agonist, licensed from Zealand Pharma: a once-weekly injectable acylated peptide, structurally derived from glucagon, that activates the glucagon receptor (GCGR) and the GLP-1 receptor — and, importantly, only those two.
That pairing is the thing to get right, because survodutide’s nearest neighbors on this hub are built differently. Tirzepatide is a GIP/GLP-1 dual agonist; retatrutide is a GIP/GLP-1/glucagon triple. Survodutide has no GIP component at all. Its second arm is glucagon, which is the more counterintuitive design — glucagon is the hormone that raises blood glucose — and the rationale for adding it is explained in Mechanisms below. Whether the two opposing effects net out favorably is precisely what the trial program has been testing, not something the mechanism settles in advance.
Unlike most of this hub, the evidence here is genuinely clinical rather than preclinical. Survodutide has completed phase 2 trials in obesity, type 2 diabetes and biopsy-confirmed MASH, and two phase 3 trials read out and were published in June 2026 — SYNCHRONIZE-1 in obesity 1Reference 1RCTSurvodutide Once Weekly for the Treatment of Adults with Obesity (SYNCHRONIZE-1) — human (RCT, phase 3)View study → and SYNCHRONIZE-MASLD in fatty liver disease 4Reference 4RCTSurvodutide in adults with obesity and metabolic dysfunction-associated steatotic liver disease: SYNCHRONIZE-MASLD, a randomized, double-blind, placebo-controlled phase 3 trial — human (RCT, phase 3)View study →.
But “published phase 3” is not “approved,” and the rest of the phase 3 program is in a third state that is easy to misread: completed and unreported. SYNCHRONIZE-2, the Japanese and Chinese regional trials, and the ~5,500-participant cardiovascular-outcomes trial have all finished, and none of them has posted results or a publication. A finished trial is not a result.
Route is load-bearing: this is a subcutaneous injection, once weekly, oral-inactive. And because there is no approved product anywhere, there is no legitimate supply route for an individual outside a clinical trial — every vial sold as “survodutide” is unregulated research-chemical material of unverified identity. See Sourcing, Route & Legal Status.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up. No score here can exceed the ceiling imposed by the compound being unapproved everywhere.
Two notes on the ranking. Obesity and MASH sit within two points of each other and the ordering is arguable: obesity has the deeper chain (phase 1 → phase 2 → a 76-week phase 3 on a definitive endpoint), while MASH is the lead regulatory story (the biopsy-confirmed phase 2 is what earned the Breakthrough Therapy designation) but its phase 3 to date rests on an imaging surrogate. And the low score on cardiovascular outcomes means “tested, finished, and not reported” — not “never studied,” and not “failed.”
Human RCT evidence, and the one place survodutide has a published phase 3 result on a definitive endpoint. The chain runs the full length. Phase 1 multiple-rising-dose work in adults with overweight or obesity reached a placebo-corrected weight loss of −13.8% at 16 weeks 7Reference 7Phase I studies of the safety, tolerability, pharmacokinetics and pharmacodynamics of the dual glucagon receptor/glucagon-like peptide-1 receptor agonist BI 456906 — human (phase 1)View study →; a parallel phase 1 study in Japanese men reached −12.4% 8Reference 8RCTA randomized Phase I study of the safety, tolerability, pharmacokinetics and pharmacodynamics of BI 456906 in healthy Japanese men with overweight/obesity — human (RCT, phase 1)View study →. The phase 2 dose-finding trial (NCT04667377, n=387, BMI ≥27 without diabetes, 43 centers in 12 countries) then produced mean weight changes at 46 weeks of −6.2% (0.6 mg), −12.5% (2.4 mg), −13.2% (3.6 mg) and −14.9% (4.8 mg) versus −2.8% on placebo 2Reference 2RCTGlucagon and GLP-1 receptor dual agonist survodutide for obesity: a randomised, double-blind, placebo-controlled, dose-finding phase 2 trial — human (RCT, phase 2)View study →.
SYNCHRONIZE-1 (NCT06066515) is the registrational read-out: a phase 3, double-blind, placebo-controlled trial in 725 adults with obesity — or overweight with a complication, excluding diabetes — treated for 76 weeks with once-weekly subcutaneous survodutide titrated to 3.6 mg or 6.0 mg. Both co-primary endpoints were met: mean weight change of −12.2% (3.6 mg) and −13.0% (6.0 mg) versus −5.4% for placebo, with ≥5% weight loss in 72.6% and 71.9% of participants versus 46.3% on placebo (P<0.001 for all comparisons). No deaths were reported 1Reference 1RCTSurvodutide Once Weekly for the Treatment of Adults with Obesity (SYNCHRONIZE-1) — human (RCT, phase 3)View study →.
One number needs care, because it is the one circulating. Boehringer’s April 2026 topline press release led with “up to 16.6%” weight loss and a placebo figure of 3.2%. That is the efficacy estimand — the on-treatment, per-protocol-flavored analysis. The NEJM paper’s headline −13.0% is the treatment-regimen estimand, which absorbs early discontinuation and prohibited-medication use and is the more conservative, more realistic figure 1Reference 1RCTSurvodutide Once Weekly for the Treatment of Adults with Obesity (SYNCHRONIZE-1) — human (RCT, phase 3)View study →.
Both are honest; they answer different questions. Quoting 16.6% alongside another drug’s treatment-regimen number is not a comparison.
Gap: unapproved. There is no published head-to-head against tirzepatide or semaglutide at phase 3, so survodutide has never been shown to beat an approved obesity drug. SYNCHRONIZE-2 (obesity with type 2 diabetes, n=755) — designed alongside SYNCHRONIZE-1 as its diabetes counterpart 14Reference 14RCTSurvodutide for treatment of obesity: rationale and design of two randomized phase 3 clinical trials (SYNCHRONIZE-1 and -2) — trial design paper (no results)View study → — and the Japanese (n=274) and Chinese (n=307) regional trials are all completed with no results posted. Durability past 76 weeks and regain after stopping are unaddressed.
The application where the glucagon arm is most differentiating, since GCGR activation acts directly on hepatic lipid metabolism rather than only through weight loss — and the one that carries the regulatory momentum.
The phase 2 trial (NCT04771273) is the strong piece, because it used liver biopsy, not imaging. In 293 adults with biopsy-confirmed MASH and F1–F3 fibrosis, treated for 48 weeks, histologic improvement in MASH without worsening of fibrosis occurred in 47% (2.4 mg), 62% (4.8 mg) and 43% (6.0 mg) versus 14% on placebo 3Reference 3RCTA Phase 2 Randomized Trial of Survodutide in MASH and Fibrosis — human (RCT, phase 2, biopsy endpoint)View study →.
Note the shape of that dose-response: it is non-monotonic — the top dose performed below the middle dose, and the trial’s own analysis fit a quadratic curve. That is a real finding, not a rounding artifact, and it means “more is better” does not hold here. Liver fat fell by ≥30% in 57–67% versus 14% on placebo, and fibrosis improved by ≥1 stage in 34–36% versus 22% — the fibrosis difference being the weaker of the two.
SYNCHRONIZE-MASLD (NCT06309992) is the phase 3, in 216 adults with obesity and at-risk MASLD, randomized 2:1 to survodutide 6.0 mg or placebo for 48 weeks. Both co-primary endpoints were met: 84.2% versus 24.3% achieved a ≥30% reduction in MRI-PDFF liver fat (efficacy estimand; 68.5% vs 28.6% on the treatment-regimen estimand), with mean weight change of −12.2% versus −1.0% 4Reference 4RCTSurvodutide in adults with obesity and metabolic dysfunction-associated steatotic liver disease: SYNCHRONIZE-MASLD, a randomized, double-blind, placebo-controlled phase 3 trial — human (RCT, phase 3)View study →. Separately, a phase 1 study in people with compensated and decompensated cirrhosis (NCT05296733, n=82) found exposure was not meaningfully altered by hepatic impairment — no PK-driven dose adjustment — and observed reductions in liver fat, liver stiffness and liver volume 9Reference 9Efficacy, tolerability and pharmacokinetics of survodutide, a glucagon/glucagon-like peptide-1 receptor dual agonist, in cirrhosis — human (phase 1, open-label)View study →.
The distinction that matters clinically: the phase 3 endpoint was liver fat on MRI, not steatohepatitis resolution or fibrosis improvement on biopsy. The trials that would supply that — LIVERAGE (NCT06632444, n=1,800) and LIVERAGE-Cirrhosis (NCT06632457, n=1,590) — were recruiting at this check with completion projected for 2031 and 2029 respectively.
Regulators have signaled interest ahead of that. The FDA granted survodutide Breakthrough Therapy designation for non-cirrhotic MASH with moderate or advanced fibrosis in 2024 (announced by Boehringer Ingelheim in October 2024); China’s NMPA granted its own breakthrough designation in June 2024, and the EMA accepted survodutide into its PRIME scheme in November 2023. None of these is an approval, and none is a finding about efficacy — they are procedural mechanisms that accelerate review of a candidate addressing an unmet need. Drugs with breakthrough designation still fail.
Gap: phase 3 evidence to date is an imaging surrogate in 216 people over 48 weeks. No phase 3 histology, no fibrosis outcome, no clinical liver events, and the non-monotonic phase 2 dose-response means the right dose is not yet settled. Nothing reads out before 2029.
Human, randomized, semaglutide-controlled — and stuck at phase 2. A phase 2, multicenter, double-blind trial (NCT04153929) randomized 413 adults with type 2 diabetes on background metformin to survodutide (up to 0.3, 0.9, 1.8 or 2.7 mg once weekly, or 1.2/1.8 mg twice weekly), placebo, or open-label semaglutide up to 1.0 mg weekly, for 16 weeks. HbA1c fell dose-dependently to a maximum of −1.71% (−18.7 mmol/mol). The comparison people quote is real but narrower than it sounds: the ~0.9 mg survodutide arm produced −1.46%, essentially matching semaglutide’s −1.47% — a single dose arm at parity, not superiority. On weight, survodutide at ≥1.8 mg weekly did beat semaglutide (up to −8.7% versus −5.3%) 5Reference 5RCTDose-response effects on HbA1c and bodyweight reduction of survodutide, a dual glucagon/GLP-1 receptor agonist, compared with placebo and open-label semaglutide in people with type 2 diabetes — human (RCT, phase 2)View study →. Adverse events occurred in 77.8% of survodutide participants versus 52.0% on semaglutide.
Note the design constraint: the semaglutide arm was open-label while survodutide and placebo were blinded, so that comparison is not a like-for-like blinded head-to-head. And 16 weeks is short for a glycemic endpoint.
Glycemic control is being carried forward inside the obesity-with-diabetes phase 3 trial SYNCHRONIZE-2 (NCT06066528, n=755) rather than as a standalone diabetes registration path. That trial is completed with no results posted and no publication located.
Gap: no published phase 3 diabetes efficacy data. No long-term glycemic durability, no hard diabetes outcomes, no blinded head-to-head against an approved agent, and — the point of the whole design — no demonstration that the glucagon arm does not erode glycemic control over years rather than 16 weeks.
Human, but post-hoc and biomarker-level. A 2026 analysis pooled the two phase 2 trials — the diabetes trial (n=413) and the obesity trial (n=387) — and examined metabolic biomarkers. In the diabetes population, survodutide significantly increased HOMA-β (a beta-cell function index) and decreased HOMA-IR, glucagon and fasting plasma glucose versus placebo. In the obesity population, where participants were normoglycemic, HOMA-β did not change significantly, but HOMA-IR, glucagon, C-peptide and fasting insulin fell and high-molecular-weight adiponectin rose 6Reference 6Dual Glucagon and GLP-1 Receptor Agonist Survodutide Improves Biomarkers of Beta-Cell Function and Insulin Sensitivity in People With Type 2 Diabetes or Living With Overweight/Obesity — human (post-hoc analysis of two phase 2 trials)View study →.
The interesting part, and the reason this is worth a row at all: regression analysis found that weight change explained the largest share of the variability in fasting insulin and HOMA-IR but did not explain the other changes — suggesting metabolic effects partly independent of weight loss. That is a mechanistically meaningful hint, and it is also exactly the kind of finding that post-hoc analyses generate and prospective trials sometimes fail to confirm.
Gap: post-hoc, exploratory, and entirely on surrogate indices — HOMA-β and HOMA-IR are calculated ratios, not measured beta-cell function. No prospective endpoint, and the authors state plainly that durability of any beta-cell improvement after treatment cessation is unknown.
This row exists to record a specific state: registered, completed, and not reported. It is not an efficacy application and should not be read as one.
SYNCHRONIZE-CVOT (NCT06077864) is a phase 3, randomized, double-blind, event-driven cardiovascular safety trial in 5,531 adults with BMI ≥27 and either established cardiovascular disease or chronic kidney disease, or at least two weight-related complications or CV risk factors, randomized 1:1:1 to survodutide 6.0 mg, survodutide 3.6 mg, or placebo 13Reference 13Survodutide for the Treatment of Obesity: Rationale and Design of the SYNCHRONIZE Cardiovascular Outcomes Trial — trial design paper (no efficacy or safety results)View study →. At this check the registry listed it as COMPLETED — primary completion 16 June 2026 — with no results posted and no publication located.
The reason it exists is the glucagon arm. Glucagon-receptor agonism can raise heart rate and move blood pressure and lipids, and in the phase 1 multiple-rising-dose program cardiac or vascular adverse events were the most common reason for discontinuation in one cohort (6 of 80 participants, 7.5%) 7Reference 7Phase I studies of the safety, tolerability, pharmacokinetics and pharmacodynamics of the dual glucagon receptor/glucagon-like peptide-1 receptor agonist BI 456906 — human (phase 1)View study →. A dedicated outcomes trial is the correct response to that signal. Its result is currently unknown.
Gap: no cardiovascular outcome data of any kind is publicly available for survodutide. A completed CV safety trial with unposted results is not evidence of safety — it is an unanswered question with a known answer date approaching. Re-check this row.
Mechanisms
The glucagon arm is the counterintuitive part, so it is worth stating the logic plainly. Glucagon raises blood glucose — which is the opposite of what a diabetes drug should do. It also increases energy expenditure and acts directly on the liver to mobilize fat. The design bet is that pairing it with GLP-1 agonism lets you keep the energy-expenditure and hepatic effects while GLP-1’s glucose-dependent insulin secretion offsets the glycemic penalty, netting out to more weight loss and more liver-fat reduction than GLP-1 alone. The endogenous precedent is oxyntomodulin, a gut peptide that hits both receptors naturally. In mice, survodutide out-performed maximally effective doses of semaglutide, and the mechanism was decomposed into both increased energy expenditure and reduced food intake 10Reference 10In vitroBI 456906: Discovery and preclinical pharmacology of a novel GCGR/GLP-1R dual agonist with robust anti-obesity efficacy — animal (mouse) + in vitroView study →.
That is a coherent rationale. It is not a settled result. Whether the two opposing glycemic effects balance favorably over years rather than weeks, and at what cost in heart rate, is what the trial program has been testing — and the trial built to answer the cardiovascular half of it has not reported.
| Target / pathway | Effect | Relevant to |
|---|---|---|
| GLP-1 receptor | Agonist → glucose-dependent insulin secretion, ↓ appetite, slowed gastric emptying | Diabetesobesity — and the offset to the glucagon arm |
| Glucagon receptor (GCGR) | Agonist → ↑ energy expenditure, direct hepatic lipid mobilization. No GIP component — this is what distinguishes it from tirzepatide | Weight lossliver fat |
| Hepatic GCGR readouts (NNMT mRNA, FGF21, plasma amino acids) | Confirmed target engagement in animals and, via amino-acid and glucagon lowering, in humans | Evidence the glucagon arm is actually engaged |
| Circumventricular organs (area postrema, arcuate nucleus) | Drug accesses these regions without uniformly crossing the blood–brain barrier; appetite-nucleus activation is GLP-1R-dependent, not glucagon-dependent | Appetite suppression |
| Insulin-sensitivity axis (HOMA-IR, HMW adiponectin) | ↓ insulin resistance, ↑ adiponectin — partly independent of weight change | Metabolic effects beyond weight loss |
| C18 fatty-acid acylation → albumin binding | Prolonged residence time | Once-weekly dosing (PK) |
A useful detail from the 2026 brain-mapping work: GCGR is barely detectable in the area postrema and arcuate nucleus at single-cell level, while GLP-1R is expressed there — and a long-acting GCGR agonist alone reduced body weight but did not activate satiety nuclei or reduce food intake 12Reference 12AnimalSurvodutide acts through circumventricular organs in the brain and activates neuronal regions associated with appetite regulation — animal (mouse) + human tissue expressionView study →. So the two arms divide the labor: GLP-1 does the appetite suppression centrally, glucagon does the energy expenditure and hepatic work peripherally.
Pharmacokinetics
Route is load-bearing. Survodutide is given by once-weekly subcutaneous injection. Like other therapeutic peptides of this size its oral bioavailability is negligible — it is digested rather than absorbed — so any “oral survodutide” product is pharmacologically inert regardless of the label. Several phase 1 formulation and bioequivalence studies are running, but no oral formulation has been reported.
The half-life is not published as a number. The discovery paper describes the C18 fatty acid as “a half-life extending principle to support once-weekly dosing in humans” 10Reference 10In vitroBI 456906: Discovery and preclinical pharmacology of a novel GCGR/GLP-1R dual agonist with robust anti-obesity efficacy — animal (mouse) + in vitroView study →, and the phase 1 reports describe dose-proportional exposure increases without publishing a terminal t½ 7,
Dose escalation is slow by design and is the practical constraint on the drug. Trials escalate over roughly 16–24 weeks to a maintenance dose of 3.6 mg or 6.0 mg. That is not caution for its own sake — it is the mitigation for the dose-limiting adverse effect, and it has repeatedly proved insufficient (see Safety). Pharmacodynamic target engagement is confirmed in humans by reduced plasma amino acids and glucagon (GCGR) and delayed gastric emptying with improved glucose tolerance (GLP-1R) 7,
Reconstitution and stability parameters for lyophilized gray-market powder are not independently documented anywhere, because no such product is a characterized pharmaceutical.
Clinical & regulatory status
Survodutide is an investigational drug with no marketing approval anywhere in the world as of this check — not approved by the FDA, EMA, PMDA, NMPA or TGA, not a prescription medicine, and not a dietary supplement. It is Boehringer Ingelheim’s asset, in-licensed from Zealand Pharma. A ClinicalTrials.gov search across the survodutide and “BI 456906” record sets returns 31 studies — 19 phase 1, 4 phase 2 and 8 phase 3 — and none has been terminated.
It holds an FDA Breakthrough Therapy designation for non-cirrhotic MASH with moderate or advanced fibrosis (2024), an NMPA breakthrough designation (June 2024), and EMA PRIME scheme access (November 2023). These are review-acceleration mechanisms. They are not approvals, and they say nothing about whether the drug works. No regulatory submission has been confirmed by the sponsor in the public record I could verify.
The temporal picture is the important part, and it has three states, not two. Published: SYNCHRONIZE-1 (obesity) 1Reference 1RCTSurvodutide Once Weekly for the Treatment of Adults with Obesity (SYNCHRONIZE-1) — human (RCT, phase 3)View study → and SYNCHRONIZE-MASLD 4Reference 4RCTSurvodutide in adults with obesity and metabolic dysfunction-associated steatotic liver disease: SYNCHRONIZE-MASLD, a randomized, double-blind, placebo-controlled phase 3 trial — human (RCT, phase 3)View study →, plus the three phase 2 trials. Completed but unreported — no posted registry results, no located publication: SYNCHRONIZE-2 (NCT06066528, n=755), SYNCHRONIZE-JP (NCT06176365, n=274), the China trial (NCT06214741, n=307), and SYNCHRONIZE-CVOT (NCT06077864, n=5,531, completed June 2026). Ongoing: LIVERAGE (NCT06632444, n=1,800, to 2031) and LIVERAGE-Cirrhosis (NCT06632457, n=1,590, to 2029), several phase 1 formulation studies, and a not-yet-recruiting phase 2 in albuminuria and kidney disease (NCT07206290). Notably, not one of the eight phase 3 trials has posted results on the registry, including the two that have been published in journals.
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 24(2 phase 3 published; 4 phase 3 unreported) | 7(4 recruiting, 2 active-not-recruiting, 1 not yet recruiting) | 0 | Mouse and in-vitro discovery and profiling 10, |
Trial counts from the combined ClinicalTrials.gov “survodutide” and “BI 456906” record sets (31 unique studies). Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status — read this before anything else on the page. Survodutide has no marketing approval in any jurisdiction. It is not FDA-approved, not EMA-approved, not approved in Japan or China, not a prescription drug, and not a dietary supplement. There is no label, no approved indication, no approved dose, and no pharmacy anywhere that can lawfully dispense it. The only lawful way for a person to receive survodutide is as a participant in a registered clinical trial. A Breakthrough Therapy designation does not change any of that; it is a scheduling arrangement between a company and a regulator.
This means there is no legitimate source, and that is the spine of this section. Because no approved product exists anywhere in the world, there is no diverted-pharmaceutical channel, no compounded-from-approved-drug channel, and no counterfeit-of-a-real-product channel of the kind that complicates semaglutide and tirzepatide. One hundred per cent of consumer supply is research-chemical material — synthesized by an unaccountable manufacturer, labeled “for research use only / not for human consumption,” never subject to any regulatory or pharmacopoeial standard. There is no version of buying survodutide online that is the trial drug.
The specific trap here is that the trial results are excellent and public. A buyer reads “−13.0% at 76 weeks” from a NEJM phase 3 and a positive biopsy trial from the same journal, and then buys a vial on the strength of those numbers. But the numbers describe pharmaceutical-grade BI 456906 manufactured to GMP, titrated over months under supervision, in a monitored trial. Nothing about that evidence transfers to the vial, and the buyer has no way to establish that it should: there is no reference product, no known pen, no authorized appearance, no legitimate price, and no pharmacist in the loop. Genuine survodutide, a cheaper GLP-1 peptide, a degraded batch, an underfilled vial and plain mannitol are indistinguishable to the person injecting them.
Be skeptical of secondary write-ups too. Vendor-adjacent sites were found vendor-adjacent sites confidently reporting an FDA submission date and quoting efficacy figures that do not match any published trial — numbers that appear to be fabricated or garbled from the real ones. That content exists to sell vials. Sponsor press releases are also not publications: Boehringer’s April 2026 topline release led with the more favorable efficacy estimand figure (16.6%), which is legitimate but is not the number the peer-reviewed paper leads with (13.0%). Neither is a lie; the difference matters, and only one of them survived peer review as the headline.
How it is supplied (in trials, and on the gray market). In trials, survodutide is a subcutaneous injection given once weekly, escalated over 16–24 weeks under supervision. Gray-market material is typically sold as a lyophilized powder requiring reconstitution with bacteriostatic water, which transfers to the buyer the sterile handling, concentration arithmetic and dose measurement that a clinical supply chain exists to remove. Non-sterile reconstitution adds infection and endotoxin risk on top of the identity risk, and dosing error is amplified because the therapeutic range is single-digit milligrams. The slow escalation that trials use to manage tolerability is exactly the thing self-directed users are least likely to replicate.
Third-party certificates of analysis are not a solution. A COA supplied or arranged by the seller is unverifiable, and a test showing “a peptide” is not a test showing this peptide at this purity with acceptable endotoxin.
This page does not recommend, review, rank, or link vendors, and no request will change that.
Safety
Survodutide has a substantial late-phase-3 safety dataset and two specific holes in it: the 5,531-participant cardiovascular-outcomes trial is completed and unreported, and dose-escalation tolerability has been the program’s persistent limiter, with withdrawal rates during escalation reaching 37% in one phase 1 cohort.
- Cardiovascular signal from the glucagon arm. Cardiac or vascular events were the commonest reason for discontinuation in one phase 1 cohort — the outcomes trial has not reported.
- Contraindicated in pregnancy and breastfeeding by default. No reproductive data exist — see the box below.
- Gastrointestinal events in 81–90% of phase 3 participants. Versus 48% on placebo, concentrated during escalation.
- Dose escalation is where people drop out. Up to 37% withdrew during escalation in one phase 1 study; only 60% completed 46 weeks in phase 2.
- No interaction profile published. Delayed gastric emptying was demonstrated with paracetamol; the rest is class reasoning.
- Gray-market vials carry risks absent from every trial figure. Unverified identity, non-sterile reconstitution, dosing error.
Full Safety & Interactions Detail
Overall posture. Survodutide’s human safety data are trial data, and they are substantial for a late-phase-3 asset — thousands of participants, placebo-controlled, up to 76 weeks. They are also incomplete in a specific way: the largest safety dataset of all, the 5,531-participant cardiovascular-outcomes trial, is completed and unreported. There is no post-marketing pharmacovigilance for the obvious reason that there is no market.
Gastrointestinal effects are the dominant and dose-limiting adverse events, as with the whole incretin class — but the frequencies here are high. In the phase 3 obesity trial, gastrointestinal events occurred in 80.9% (3.6 mg) and 89.7% (6.0 mg) of participants versus 47.9% on placebo, typically mild to moderate and concentrated during dose escalation; no deaths were reported 1Reference 1RCTSurvodutide Once Weekly for the Treatment of Adults with Obesity (SYNCHRONIZE-1) — human (RCT, phase 3)View study →. In the phase 2 MASH trial, nausea (66% vs 23% placebo), diarrhea (49% vs 23%) and vomiting (41% vs 4%) were all substantially more frequent, while serious adverse events were similar between arms (8% vs 7%) 3Reference 3RCTA Phase 2 Randomized Trial of Survodutide in MASH and Fibrosis — human (RCT, phase 2, biopsy endpoint)View study →. In the phase 2 obesity trial, adverse events occurred in 91% of survodutide recipients versus 75% on placebo 2Reference 2RCTGlucagon and GLP-1 receptor dual agonist survodutide for obesity: a randomised, double-blind, placebo-controlled, dose-finding phase 2 trial — human (RCT, phase 2)View study →.
Dose-escalation tolerability is the program’s persistent limiter, and it is worth its own paragraph. In phase 1 multiple-rising-dose work, 12.5% of participants in one cohort and 17.8% in another discontinued during escalation 7Reference 7Phase I studies of the safety, tolerability, pharmacokinetics and pharmacodynamics of the dual glucagon receptor/glucagon-like peptide-1 receptor agonist BI 456906 — human (phase 1)View study →. In the Japanese phase 1 study the figure was 37.0% — 10 of 27 treated participants withdrew during escalation, nine of them for decreased appetite alone, and the withdrawal rate reached 66.7% in the 4.8 mg cohort 8Reference 8RCTA randomized Phase I study of the safety, tolerability, pharmacokinetics and pharmacodynamics of BI 456906 in healthy Japanese men with overweight/obesity — human (RCT, phase 1)View study →. Even in the phase 2 obesity trial only 60.4% of participants completed the 46-week treatment period 2Reference 2RCTGlucagon and GLP-1 receptor dual agonist survodutide for obesity: a randomised, double-blind, placebo-controlled, dose-finding phase 2 trial — human (RCT, phase 2)View study →. This is not a footnote: it is the reason escalation stretches over four to six months, and it is the single thing a self-directed user is most likely to get wrong.
The glucagon-specific concern is cardiovascular. Glucagon-receptor agonism can raise heart rate and affect blood pressure and lipids. In the phase 1 multiple-rising-dose program, cardiac or vascular adverse events were the most frequent reason for discontinuation in one cohort (6 of 80, 7.5%) 7Reference 7Phase I studies of the safety, tolerability, pharmacokinetics and pharmacodynamics of the dual glucagon receptor/glucagon-like peptide-1 receptor agonist BI 456906 — human (phase 1)View study →. That signal — not a general class worry — is why SYNCHRONIZE-CVOT was built 13Reference 13Survodutide for the Treatment of Obesity: Rationale and Design of the SYNCHRONIZE Cardiovascular Outcomes Trial — trial design paper (no efficacy or safety results)View study →, and that trial’s result is not public. This is an unresolved question, not a resolved reassurance.
Interactions. No comprehensive interaction profile is published. The cautions below are mechanism- and class-based expectations, not assessed findings: as an agent that delays gastric emptying — directly demonstrated with paracetamol absorption in phase 1 8Reference 8RCTA randomized Phase I study of the safety, tolerability, pharmacokinetics and pharmacodynamics of BI 456906 in healthy Japanese men with overweight/obesity — human (RCT, phase 1)View study → — it can alter the absorption of concomitant oral medications, which matters most for narrow-therapeutic-index drugs; combined with insulin or sulfonylureas it would be expected to raise hypoglycemia risk; and by analogy with the GLP-1 class, retained gastric contents are a peri-procedural aspiration concern for anesthesia.
Who should avoid it. In practice, everyone outside a clinical trial — there is no supervised way to use it. Within the class-based cautions a future label would likely carry: prior pancreatitis, severe gastrointestinal disease, personal or family history of medullary thyroid carcinoma or MEN 2, and pregnancy or lactation. These are extrapolated from GLP-1-class labels, not established survodutide findings.
Injection-specific risks. Injection-site reactions in trials. For self-sourced product, add non-sterile reconstitution (infection, endotoxin), unverified contents (wrong compound, wrong amount), and dosing error from self-mixed concentrations — risks absent from every trial figure quoted here.
Scope disclosure (honesty, not a claim):
- Human data? Yes — extensive. Phase 1, phase 2 and two published phase 3 RCTs in obesity and fatty liver disease. This is trial-grade human evidence, not preclinical extrapolation. But the drug is unapproved everywhere, four phase 3 trials are completed and unreported, and no phase 3 has posted registry results.
- Interactions assessed? No. No dedicated interaction program located; the interactions above are class and mechanism reasoning.
- Pregnancy/lactation assessed? No. No human or animal reproductive data located for survodutide specifically.
- Long-term safety established? No. Longest published exposure is 76 weeks. The cardiovascular-outcomes trial completed in June 2026 and has not reported — treat its silence as an open question, not a result.
- Is the half-life known? No numeric value is published. Once-weekly dosing is a design claim supported by the acylation chemistry, not a citable t½.
- Does any of this describe gray-market product? No. Every figure above comes from pharmaceutical-grade drug in a monitored trial.
Never imply safety from silence. Where survodutide has not been studied — long-term use, interactions, pregnancy, cardiovascular outcomes as currently published, and the identity and purity of anything sold outside a trial — the correct statement is “not assessed,” not “safe.”
Not assessed, and contraindicated by default. No human pregnancy or lactation data exist for survodutide; the reviewed trials excluded pregnancy. Intentional weight loss is generally inappropriate in pregnancy, and the incretin class carries pregnancy cautions with washout recommendations reflecting long half-lives — survodutide’s once-weekly design implies a washout measured in weeks, though the exact half-life is not published. Note also that weight loss can restore fertility unexpectedly, so unintended pregnancy during use is a realistic scenario. Treat as contraindicated in pregnancy and breastfeeding.
Dosage
There is no approved or established human dose for survodutide, and none is recommended here. It is an investigational drug with no label, no approved indication, and no lawful self-administration pathway. The figures below are reported as trial data for context only — they are not a protocol, and reproducing them with gray-market material does not reproduce the trial.
In the phase 3 obesity and fatty-liver trials, survodutide was titrated over roughly 16–24 weeks to a maintenance dose of 3.6 mg or 6.0 mg once weekly by subcutaneous injection 1,
Two things about those numbers deserve emphasis. First, the escalation schedule is the safety mechanism, not an inconvenience — and it demonstrably failed for a large minority even under supervision, with escalation-phase withdrawal rates of 12–18% in phase 1 and 37% in one Japanese cohort 7,
Oral products cannot deliver intact peptide (see Pharmacokinetics), so any oral “survodutide” is inert whatever the label says. And because no reference product exists, dose figures are meaningless applied to a vial of unverified concentration and unverified identity. This entry is informational only.
References
- le Roux CW, et al. (2026). Survodutide Once Weekly for the Treatment of Adults with Obesity (SYNCHRONIZE-1) — human (RCT, phase 3). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/42253238/
- le Roux CW, et al. (2024). Glucagon and GLP-1 receptor dual agonist survodutide for obesity: a randomised, double-blind, placebo-controlled, dose-finding phase 2 trial — human (RCT, phase 2). Lancet Diabetes Endocrinol. https://pubmed.ncbi.nlm.nih.gov/38330987/
- Sanyal AJ, et al. (2024). A Phase 2 Randomized Trial of Survodutide in MASH and Fibrosis — human (RCT, phase 2, biopsy endpoint). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/38847460/
- Kaplan LM, et al. (2026). Survodutide in adults with obesity and metabolic dysfunction-associated steatotic liver disease: SYNCHRONIZE-MASLD, a randomized, double-blind, placebo-controlled phase 3 trial — human (RCT, phase 3). Nat Med. https://pubmed.ncbi.nlm.nih.gov/42252333/
- Blüher M, et al. (2024). Dose-response effects on HbA1c and bodyweight reduction of survodutide, a dual glucagon/GLP-1 receptor agonist, compared with placebo and open-label semaglutide in people with type 2 diabetes — human (RCT, phase 2). Diabetologia. https://pubmed.ncbi.nlm.nih.gov/38095657/
- Ekinci EI, et al. (2026). Dual Glucagon and GLP-1 Receptor Agonist Survodutide Improves Biomarkers of Beta-Cell Function and Insulin Sensitivity in People With Type 2 Diabetes or Living With Overweight/Obesity — human (post-hoc analysis of two phase 2 trials). Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/42331726/
- Jungnik A, et al. (2023). Phase I studies of the safety, tolerability, pharmacokinetics and pharmacodynamics of the dual glucagon receptor/glucagon-like peptide-1 receptor agonist BI 456906 — human (phase 1). Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/36527386/
- Yazawa R, et al. (2023). A randomized Phase I study of the safety, tolerability, pharmacokinetics and pharmacodynamics of BI 456906 in healthy Japanese men with overweight/obesity — human (RCT, phase 1). Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/36974349/
- Lawitz EJ, et al. (2024). Efficacy, tolerability and pharmacokinetics of survodutide, a glucagon/glucagon-like peptide-1 receptor dual agonist, in cirrhosis — human (phase 1, open-label). J Hepatol. https://pubmed.ncbi.nlm.nih.gov/38857788/
- Zimmermann T, et al. (2022). BI 456906: Discovery and preclinical pharmacology of a novel GCGR/GLP-1R dual agonist with robust anti-obesity efficacy — animal (mouse) + in vitro. Mol Metab. https://pubmed.ncbi.nlm.nih.gov/36356832/
- Thomas L, et al. (2024). The dual GCGR/GLP-1R agonist survodutide: Biomarkers and pharmacological profiling for clinical candidate selection — animal + in vitro. Diabetes Obes Metab. https://pubmed.ncbi.nlm.nih.gov/38560764/
- Zimmermann T, et al. (2026). Survodutide acts through circumventricular organs in the brain and activates neuronal regions associated with appetite regulation — animal (mouse) + human tissue expression. Mol Metab. https://pubmed.ncbi.nlm.nih.gov/41638399/
- Kosiborod MN, et al. (2024). Survodutide for the Treatment of Obesity: Rationale and Design of the SYNCHRONIZE Cardiovascular Outcomes Trial — trial design paper (no efficacy or safety results). JACC Heart Fail. https://pubmed.ncbi.nlm.nih.gov/39453356/
- Wharton S, et al. (2025). Survodutide for treatment of obesity: rationale and design of two randomized phase 3 clinical trials (SYNCHRONIZE-1 and -2) — trial design paper (no results). Obesity (Silver Spring). https://pubmed.ncbi.nlm.nih.gov/39495965/
- Zimmermann, T., Thomas, L., Baader-Pagler, T., et al. (2022). BI 456906: discovery and preclinical pharmacology of a novel GCGR/GLP-1R dual agonist with robust anti-obesity efficacy. Molecular Metabolism. https://pmc.ncbi.nlm.nih.gov/articles/PMC9679702/
- ClinicalTrials.gov. Survodutide (BI 456906) trial programme, sponsor Boehringer Ingelheim - including NCT04667377 (phase 2) and the SYNCHRONIZE phase 3 trials. https://clinicaltrials.gov/study/NCT04667377



