
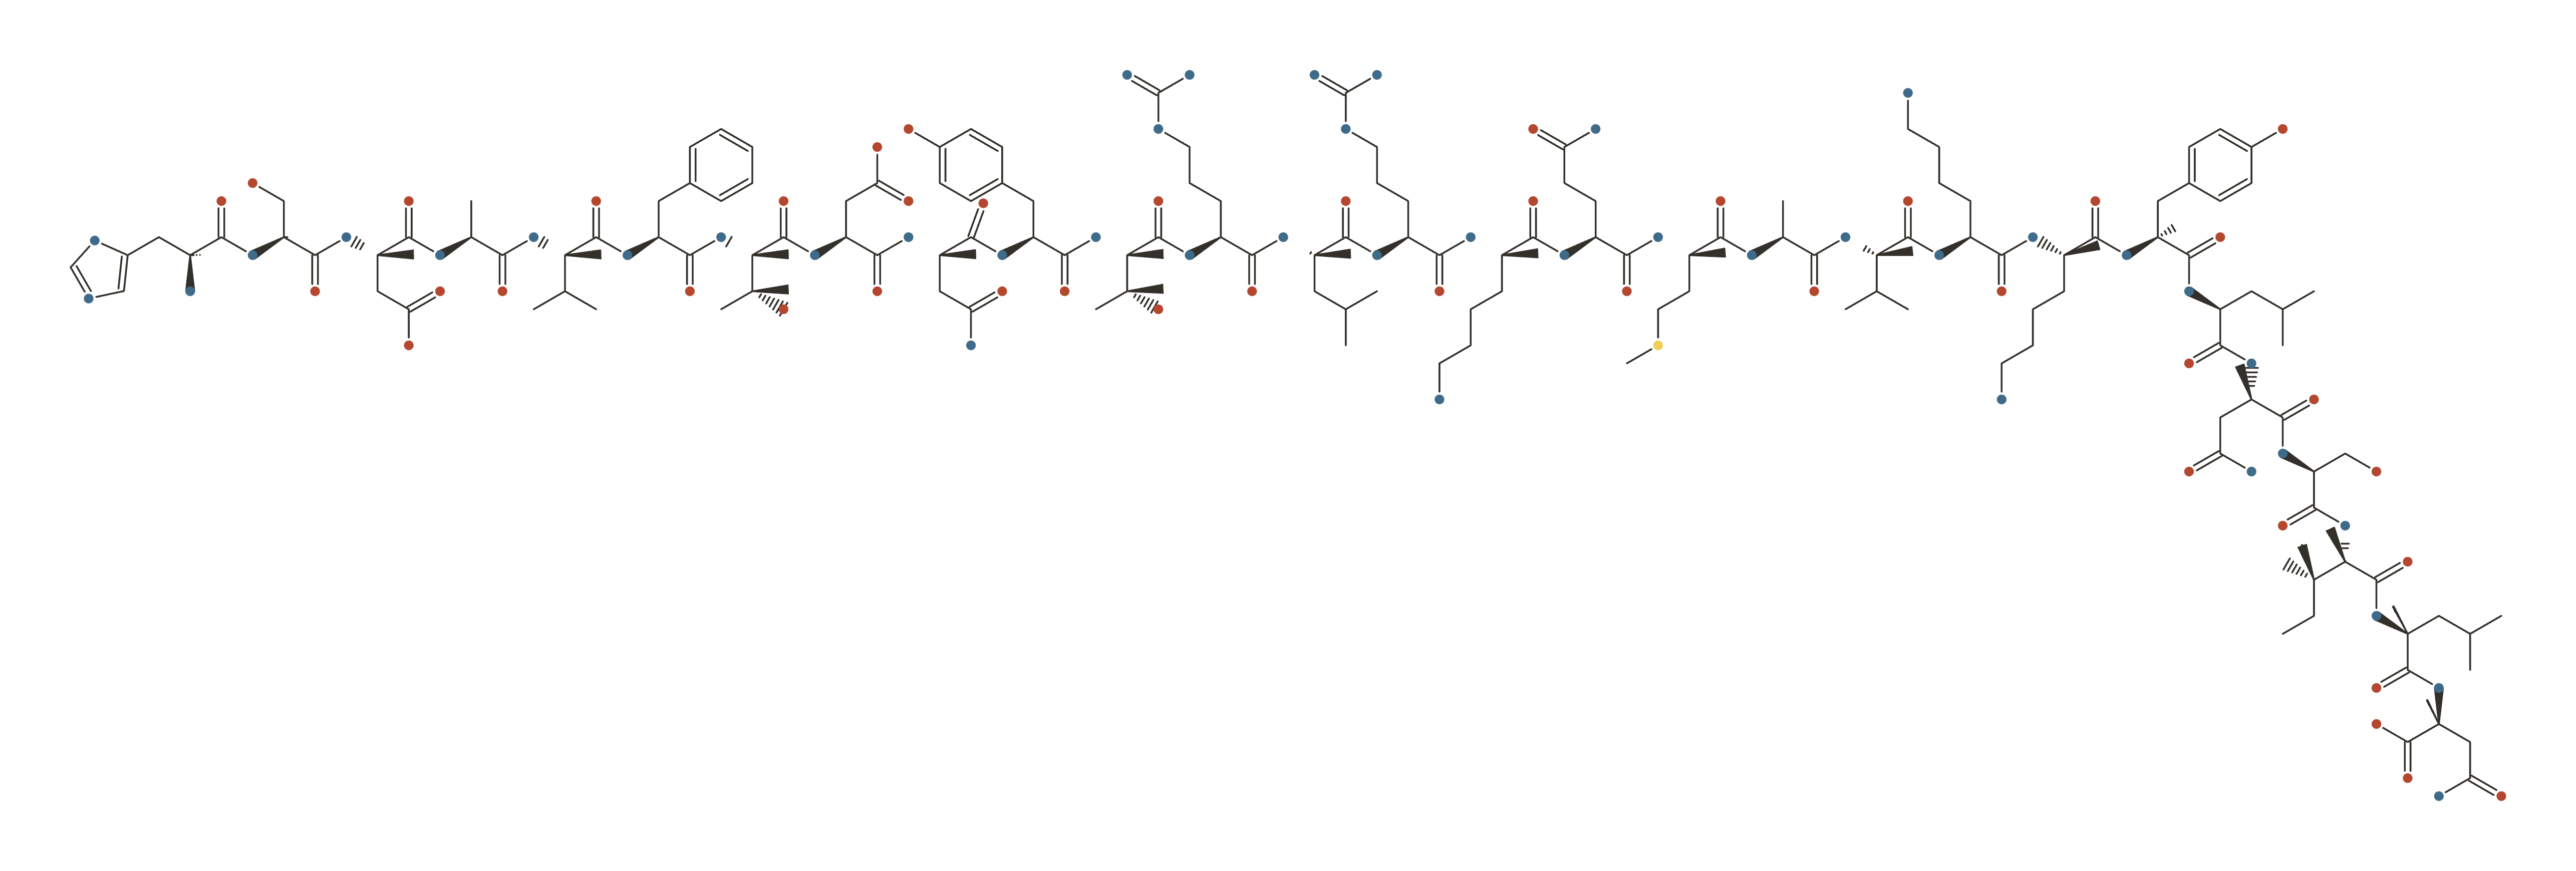
VIP (vasoactive intestinal peptide)
An endogenous 28-amino-acid neuropeptide; its synthetic copy aviptadil is an approved erectile-dysfunction injection in parts of Europe.

VIP (vasoactive intestinal peptide) at a Glance
VIP — vasoactive intestinal peptide — is a 28-amino-acid neuropeptide the body produces widely, acting as a vasodilator, bronchodilator and immune regulator. Its synthetic copy, aviptadil, is an approved medicine: given by intracavernosal injection with phentolamine for erectile dysfunction, and investigated more recently in acute respiratory failure. It is also sold as a nasal spray outside that approval, most often in chronic inflammatory response protocols.
History & Development
VIP is a hormone the body makes, and its synthetic copy is an approved medicine - for erectile dysfunction, in a handful of European countries. It also went through a large, well-funded COVID-19 programme and failed it outright.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Not established in the sources consulted for this section |
| Origin | Endogenous 28-amino-acid human neuropeptide of the secretin/glucagon superfamily; signals through VPAC1 and VPAC2 receptors |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Approved in a small number of European countries as Invicorp (aviptadil + phentolamine, intracavernosal); investigational and failed in COVID-19 as Zyesami / RLF-100 |
Discovery
Vasoactive intestinal peptide was named for what it was first observed doing - dilating blood vessels, and coming from the gut. It belongs to the secretin/glucagon superfamily and shares its two receptors, VPAC1 and VPAC2, with its close relative PACAP.
Its biology is broad rather than specialised: vasodilator, bronchodilator and immune regulator. That breadth is what has repeatedly made it look like a candidate for serious lung disease, and what has repeatedly failed to translate.
Development & ownership
The approved product is narrow and it is not what the peptide market sells. Invicorp combines aviptadil 25 µg with phentolamine mesylate 1-2 mg, given by intracavernosal injection for erectile dysfunction, and it holds approval in a small number of European countries.
The far larger programme was COVID-19 respiratory failure, where intravenous aviptadil was developed as Zyesami / RLF-100 on the rationale that VPAC1 receptors are densely expressed on the alveolar cells the virus attacks. It received substantial attention and funding, and the NIH-funded TESICO trial settled it: with 461 participants analysed, the odds ratio was 1.11 (95% CI 0.80-1.55, p=0.54). It did not work.
That result is worth keeping attached to the compound. It is one of the few peptides here to have been tested at genuine scale in a serious indication, and the answer was negative.
How it reached the market
Outside the European erectile-dysfunction product, VIP and aviptadil are unapproved. What is sold online is an endogenous neuropeptide with an approved route that is intracavernosal, a failed intravenous programme, and no evidence for the subcutaneous or nasal use it is marketed for.
What It's Used For
Vasoactive intestinal peptide is a 28-amino-acid endogenous human neuropeptide of the secretin/glucagon superfamily, signaling through the VPAC1 and VPAC2 G-protein-coupled receptors it shares with its close relative PACAP 17,
Two things have to be separated before any of the evidence below can be read correctly. The first is that VIP’s native physiology is not evidence about VIP as a drug. There is an enormous literature on what endogenous VIP does in the body — gut motility, vasodilation, bronchodilation, circadian pacemaking, immune regulation — and almost none of it tells you what happens when you administer VIP to a person. Only interventional administration studies are scored here; the physiology lives in Mechanisms as background. The second is that “VIP” and “aviptadil” get used interchangeably and should not be. Aviptadil is synthetic VIP, and it is the agent in essentially all of the recent clinical record — including one approved combination product and one large, well-conducted failure. Where a result belongs to aviptadil, or to a different stabilized analogue, it is named.
Route is the third load-bearing fact, and it is unusually varied: intracavernosal injection, nebulized inhalation, continuous intravenous infusion, and — in the gray market — intranasal. The reason is pharmacokinetic and it is decisive. Human infusion work measured VIP’s plasma disappearance half-time at about one minute 2Reference 2Vasoactive intestinal peptide in man: pharmacokinetics, metabolic and circulatory effects — human (infusion PK)View study →. Nothing about VIP survives being treated as a systemic, self-dosed peptide.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Read the second row as a failure, not an absence. COVID-19 respiratory failure scores low despite having the largest and best-controlled human dataset here, because that dataset is negative. A low score elsewhere on this table usually means “barely tested”; here it means “tested properly and it did not work.” The two are not interchangeable, and neither is interchangeable with the CIRS row, which is not scored at all because nothing has ever been measured.
Human, and the only application here with a marketing approval behind it. The product is a fixed intracavernosal injection of aviptadil (synthetic VIP) 25 µg with phentolamine mesylate 1–2 mg, marketed as Invicorp for moderate-to-severe erectile dysfunction. The pairing is rational rather than arbitrary: VIP acts on the veno-occlusive mechanism with little effect on arterial inflow, while phentolamine, an α-adrenergic antagonist, increases arterial inflow — complementary halves of an erection 11Reference 11ReviewVasoactive intestinal polypeptide/phentolamine for intracavernosal injection in erectile dysfunction — reviewView study →. The product has a long and slow development history — aviptadil was under investigation for erectile dysfunction by its original developer (Senatek) well before it acquired its COVID-era reputation 12Reference 12ReviewAviptadil (Senatek) — reviewView study →. A 2019 systematic review of intracavernosal injectables states the regulatory position plainly: approval of ICI agents is mainly limited to alprostadil, “with the recent addition of aviptadil/phentolamine combination therapy in a select few geographical regions” 13Reference 13Systematic reviewErectile dysfunction: a global review of intracavernosal injectables — systematic reviewView study →. That is the approval, and it is narrow.
The efficacy numbers deserve care, because two sources disagree and the more optimistic one is the less independent. A 2008 narrative review written from within the product’s development orbit reported effectiveness in ≥80% of men with very low penile pain and negligible priapism risk 11Reference 11ReviewVasoactive intestinal polypeptide/phentolamine for intracavernosal injection in erectile dysfunction — reviewView study →.
The largest independent dataset is a 2025 retrospective single-center series of 308 men referred specifically because they had failed or could not tolerate alprostadil: 59% overall resumed penetrative sexual activity, and the result split sharply by why they were referred — 76% among men who had found alprostadil too painful, versus 36% among men who had failed maximal-dose alprostadil 14Reference 14Intracavernosal injection of aviptadil and phentolamine for refractory erectile dysfunction — human (retrospective series, n=308)View study →.
Facial flushing occurred in 22.5%, and ischemic priapism in one patient (0.3%) 14Reference 14Intracavernosal injection of aviptadil and phentolamine for refractory erectile dysfunction — human (retrospective series, n=308)View study →.
So the tolerability advantage over alprostadil looks real; the ≥80% efficacy figure does not survive contact with contemporary practice in a refractory population.
Gap: Every efficacy figure belongs to the combination, and no trial randomized VIP alone — its independent contribution is unknown. The best contemporary dataset is retrospective, single-center, and uncontrolled, in a pre-selected refractory population. There is no US approval. And all of this is intracavernosal injection: none of it transfers to inhaled, intranasal or systemic VIP.
Human RCTs — and the headline result is negative. Synthetic VIP (aviptadil, branded Zyesami/RLF-100) was developed for COVID-19 hypoxemic respiratory failure on a lung-protective rationale: VIP concentrates in alveolar type-II cells, upregulates surfactant and suppresses cytokine synthesis 3Reference 3RCTThe use of IV vasoactive intestinal peptide (aviptadil) in patients with critical COVID-19 respiratory failure: results of a 60-day randomized controlled trial — human (RCT, n=196)View study →. This produced the largest human clinical program any peptide here has, so the null it delivered is unusually well-earned.
The first substantial trial randomized 196 patients 2:1 to three days of IV aviptadil or placebo. Its primary endpoint — alive and free of respiratory failure at day 60 — was not met (OR 1.6, 95% CI 0.86–3.11). A secondary 60-day survival analysis reached significance (OR 2.0, 95% CI 1.1–3.9, p=0.035), and the authors argued from it, but their own stated conclusion on the primary was that “there was no difference between Aviptadil versus placebo” 3Reference 3RCTThe use of IV vasoactive intestinal peptide (aviptadil) in patients with critical COVID-19 respiratory failure: results of a 60-day randomized controlled trial — human (RCT, n=196)View study →.
The definitive test was TESICO (NCT04843761), a NIH-funded, randomized, placebo-controlled trial across 28 US sites. Among 461 patients in the modified intention-to-treat analysis, the odds ratio for a better outcome on the primary ordinal endpoint at day 90 was 1.11 (95% CI 0.80–1.55, p=0.54); cumulative 90-day mortality was 38% on aviptadil versus 36% on placebo (HR 1.04, 95% CI 0.77–1.41, p=0.78). The data and safety monitoring board recommended stopping the aviptadil arm for futility in May 2022 4Reference 4RCTIntravenous aviptadil and remdesivir for treatment of COVID-19-associated hypoxaemic respiratory failure in the USA (TESICO): a randomised, placebo-controlled trial — human (RCT, n=461 analysed; stopped for futility)View study →.
A separate, smaller line of work used the inhaled route: a multicenter double-blind RCT in 80 hospitalized patients reported a mean time to discharge of 7.8 versus 10 days (p=0.049) and greater day-28 CT improvement (p=0.028) 5Reference 5RCTInhaled aviptadil is a new hope for recovery of lung damage due to COVID-19 — human (RCT, n=80)View study →.
That is a single small positive trial against a large negative one, and the 2025 systematic review and meta-analysis is the fairest summary: pooling the randomized evidence gave a survival odds ratio of 1.01 (95% CI 0.72–1.42, p=0.93) — no significant benefit 6Reference 6Meta-analysisAviptadil therapy in acute respiratory distress syndrome patients: a systematic review and meta-analysis — meta-analysis of human studiesView study →.
Note that the pooled RCT evidence in that meta-analysis is the same two trials described above, so it is a re-analysis of this data, not additional confirmation of it.
Aviptadil is not approved for COVID-19 or ARDS anywhere. Public reporting and sponsor announcements describe the FDA declining Emergency Use Authorization; those are company and regulator statements rather than indexed literature, so they are noted here without a reference number.
Gap: This is a well-evidenced null, not an untested idea. The remaining uncertainty is narrow: whether the inhaled route behaves differently from intravenous infusion, which rests on one 80-patient trial that has never been confirmed at scale. All human data are in critically ill hospitalized inpatients receiving supervised IV or nebulized dosing.
Human, but open-label and biomarker-only — and this is native VIP, not an analogue. Twenty patients with histologically proven active pulmonary sarcoidosis inhaled nebulized VIP for four weeks in an open phase II study. Treatment was safe and well tolerated and produced a coherent immunoregulatory shift within the lung: significantly reduced TNF-α production by cells isolated from bronchoalveolar lavage fluid, and increased numbers of bronchoalveolar CD4⁺CD127⁻CD25⁺ regulatory T cells with demonstrable suppressive activity on effector T cells. Parallel in-vitro work showed VIP converting naïve CD4⁺CD25⁻ T cells into FoxP3⁺ regulatory T cells 1Reference 1Inhaled vasoactive intestinal peptide exerts immunoregulatory effects in sarcoidosis — human (open-label phase II, n=20)View study →. The authors describe it as the first demonstration of an immunoregulatory effect of VIP in humans, which it plausibly is.
What it is not is a demonstration that patients got better. There was no control group, no blinding, no randomization, twenty participants, and the endpoints were immune-cell measurements rather than lung function, symptoms or disease progression. Sixteen years on it has not been replicated or followed by a controlled trial.
Gap: One small uncontrolled study with surrogate endpoints. No randomized trial, no clinical-outcome data, no replication.
Human RCT — but of a different molecule. Endogenous VIP is a potent airway bronchodilator, and reviews have long framed inhaled VIP agonists as a plausible respiratory therapy while flagging the half-life as the practical obstacle 7Reference 7ReviewVasoactive intestinal peptide inhaled agonists: potential role in respiratory therapeutics — reviewView study →. That obstacle is why the human asthma data are for a stabilized analogue, not VIP: Ro 25-1553, a cyclic VPAC2-selective agonist.
In a double-blind, randomized, placebo-controlled crossover study in 24 patients with moderate stable asthma, inhaled Ro 25-1553 600 µg produced rapid bronchodilation — a geometric mean FEV₁ increase over placebo of 6% (95% CI 4–9) within three minutes, comparable to formoterol’s 8% (95% CI 5–10). Maximum effect over 24 hours was similar too (7% versus 10%). The difference was duration: the Ro 25-1553 effect was attenuated by five hours, while formoterol was still bronchodilating at twelve 10Reference 10RCTBronchodilation by an inhaled VPAC(2) receptor agonist in patients with stable asthma — human (randomised placebo-controlled crossover, n=24; analogue Ro 25-1553)View study →.
Neither produced clinically relevant side effects. Related stable analogues relax airway and pulmonary vasculature in mouse and rat lungs 19Reference 19AnimalVasodilatory effect of the stable vasoactive intestinal peptide analog RO 25-1553 in murine and rat lungs — animal (mouse, rat)View study →.
Gap: The human efficacy belongs to an analogue, not to VIP, and the analogue was weaker and much shorter-acting than an existing standard drug — which is why it was not developed further. Native VIP is not a viable inhaled asthma therapy on pharmacokinetic grounds alone.
One small open-label human study, and a follow-up program that never reported. The rationale is a deficiency argument: patients with primary pulmonary hypertension were found to have reduced VIP in serum and lung tissue with compensatory upregulation of VPAC receptors. On that basis, eight patients received VIP and showed decreased mean pulmonary artery pressure, increased cardiac output and increased mixed venous oxygen saturation, without reported side effects 9Reference 9Vasoactive intestinal peptide as a new drug for treatment of primary pulmonary hypertension — human (open-label, n=8)View study →. The authors themselves framed it as providing “enough proof for further investigation” — an explicitly preliminary claim, from an uncontrolled study of eight people.
What happened next is worth stating precisely, because it is easy to describe wrongly in either direction. The follow-up was pemziviptadil (PB1046), a long-acting sustained-release VIP analogue designed to solve the half-life problem; its phase 2 trial in pulmonary arterial hypertension (NCT03556020, n=35) was terminated — but for study-drug resupply delays during COVID-19, not for futility or harm. A second pemziviptadil trial (NCT04433546) was terminated because the company was “no longer pursuing” the indication. So the correct statement is not that controlled work disproved the idea; it is that the controlled work was abandoned before it produced an efficacy readout. Current reviews treat VIP’s role in pulmonary disease as unproven and pharmacokinetically constrained 8Reference 8ReviewThe role of vasoactive intestinal peptide in pulmonary diseases — reviewView study →.
Gap: The only positive human data are an uncontrolled n=8 study from 2003. No randomized trial has ever reported, no VIP-based therapy is approved for PAH, and the analogue program that would have answered the question was discontinued for commercial and supply reasons.
Animal only — and the gap here is total. VIP is a genuine endogenous immunomodulator: it shifts Th1/Th2 balance, induces regulatory T cells and dampens innate inflammation through VPAC1 and VPAC2 15Reference 15ReviewA clinical approach for the use of VIP axis in inflammatory and autoimmune diseases — reviewView study →. Administered exogenously, it is protective across a wide spread of rodent models — collagen-induced arthritis, the K/BxN autoimmune arthritis model, colitis, and lupus-like disease 15,
What does not exist is any human efficacy data whatsoever. There is no randomized trial of VIP in rheumatoid arthritis, inflammatory bowel disease, lupus, or any other autoimmune indication, and the one-minute half-life is the obvious reason no one has attempted one with native peptide. The sarcoidosis study above is the closest thing to human evidence for VIP as an immunomodulator, and it measured immune cells rather than disease.
Gap: Animal-only for efficacy. Consistent rodent benefit and a clear mechanism do not make a human result. Anyone citing “VIP is anti-inflammatory” as a reason to take it is citing mouse data and receptor biology.
This is deliberately left un-scored, and the reason is that there is nothing to score. Intranasal VIP is promoted within the “chronic inflammatory response syndrome” (CIRS) / biotoxin-illness community, principally as a late step in the Shoemaker protocol for people with reported water-damaged-building exposure. It is supplied as a compounded prescription nasal spray, and for many people it is the only context in which they have encountered VIP at all.
Two things can be said neutrally. First, CIRS is not an established diagnostic entity in mainstream medicine — it does not appear as a recognized diagnosis in standard classifications, and the framework around it is largely maintained outside conventional clinical research. Second, and separately from that dispute: a search of ClinicalTrials.gov returns no registered trial of VIP for CIRS, mold illness or biotoxin illness of any design — not a randomized trial, not an open-label one. The available human material is case reports. That is not a criticism of anyone’s experience; it is a statement about what has and has not been measured.
The practical consequence is that the intranasal route — the one actually being sold and used for this purpose — is also the route with the least evidence behind it. Every scored application above used intracavernosal, nebulized or intravenous administration. No study here establishes what an intranasal dose of VIP does in a human being.
Gap: Everything. No controlled trial, no dose-finding, no pharmacokinetic characterization of the intranasal route, and no safety data for chronic intranasal use.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| VPAC1 receptor (Gs → ↑cAMP/PKA) | Anti-inflammatory signaling on immune cells; vasodilation | Sarcoidosisautoimmune modelsARDS rationale |
| VPAC2 receptor (Gs → ↑cAMP) | Airway and vascular smooth-muscle relaxation | Asthma (analogues)PAHerectile function |
| Vascular smooth muscle | Potent vasodilation — flushing, ↑ heart rate in human infusion | Safety profile; PAH; erectile function |
| Cavernosal veno-occlusive mechanism | Enhanced; paired with phentolamine for arterial inflow | Erectile dysfunction |
| TNF-α / pro-inflammatory cytokine synthesis | ↓ (bronchoalveolar cells, human) | Sarcoidosisautoimmune models |
| CD4⁺ regulatory T cells (FoxP3⁺) | ↑ induced and expanded | Sarcoidosisimmune tolerance |
| Alveolar type-II cells / surfactant | ↑ (preclinical rationale) | COVID-19 / acute lung injury program |
| Intestinal secretion (endogenous physiology) | ↑ water and electrolyte secretion | The VIPoma diarrhea syndrome — see Safety |
| Cranial parasympathetic outflow | ↑ activation; extracranial arterial dilation | Headache observed in human infusion studies |
Pharmacokinetics
One number governs this entire page. In a human study, graded intravenous VIP infusions were given to healthy volunteers and plasma VIP was tracked by radioimmunoassay. After the infusions stopped, plasma levels fell by first-order kinetics with an average disappearance half-time of one minute, an apparent metabolic clearance rate of about 9 mL/kg/min and an apparent volume of distribution of roughly 14 mL/kg 2Reference 2Vasoactive intestinal peptide in man: pharmacokinetics, metabolic and circulatory effects — human (infusion PK)View study →. VIP is a 28-residue peptide with negligible oral bioavailability — it is digested, not absorbed — so oral products cannot deliver intact peptide regardless of labeling.
The consequence is that every real therapeutic use of VIP is local or continuous, never a systemic bolus: intracavernosal injection into the target tissue (erectile dysfunction), nebulized inhalation into the lung (sarcoidosis, pulmonary hypertension, inhaled aviptadil), or continuous intravenous infusion maintained over days in hospital (aviptadil in the COVID trials, dosed as daily 12-hour infusions) 4Reference 4RCTIntravenous aviptadil and remdesivir for treatment of COVID-19-associated hypoxaemic respiratory failure in the USA (TESICO): a randomised, placebo-controlled trial — human (RCT, n=461 analysed; stopped for futility)View study →. This is also why the field largely stopped pursuing native VIP and moved to engineered molecules — the VPAC2-selective analogue Ro 25-1553, and the long-acting sustained-release analogue pemziviptadil — in an attempt to buy duration the parent peptide does not have 8Reference 8ReviewThe role of vasoactive intestinal peptide in pulmonary diseases — reviewView study →.
The intranasal route sold for CIRS use has no published human pharmacokinetic characterization at all. There is no evidence that an intranasal dose produces meaningful or sustained systemic VIP exposure, and the one-minute plasma half-life is a strong prior against it.
Clinical & regulatory status
VIP occupies three regulatory positions at once and they must not be blurred into one another.
Approved, narrowly. The intracavernosal combination of aviptadil with phentolamine is an approved prescription medicine for erectile dysfunction in a small number of European countries — a 2019 systematic review confirms approval of the aviptadil/phentolamine combination “in a select few geographical regions,” alongside alprostadil as the mainstay 13Reference 13Systematic reviewErectile dysfunction: a global review of intracavernosal injectables — systematic reviewView study →. It is a combination product, it is not FDA-approved, and the approval covers one indication by one route in one population. It does not extend to VIP administered any other way, for any other reason.
Investigational and failed. Aviptadil for COVID-19 respiratory failure and ARDS holds no approval anywhere. The NIH-funded TESICO trial was stopped for futility 4Reference 4RCTIntravenous aviptadil and remdesivir for treatment of COVID-19-associated hypoxaemic respiratory failure in the USA (TESICO): a randomised, placebo-controlled trial — human (RCT, n=461 analysed; stopped for futility)View study →, and per sponsor and press reporting the FDA declined Emergency Use Authorization — a regulatory action documented in company announcements rather than the indexed literature, so it is stated here without a reference number.
Compounded and off-label. Intranasal VIP for CIRS is a compounded prescription preparation, not an approved product, supported by no controlled trial.
VIP is not a dietary supplement and there is no lawful over-the-counter form of it for human use in the US, UK, EU or Australia.
| Completed | Ongoing | Terminated / withdrawn | Preclinical |
|---|---|---|---|
| 4registered aviptadil trials — but two of these records (NCT04843761, NCT06729606) are the same TESICO dataset registered twice, so 3 distinct completed trials | 1(I-SPY COVID adaptive platform, NCT04488081, active not recruiting) | 6(inhaled ZYESAMI NCT04360096 and NCT05137795, inhaled aviptadil NCT04536350, expanded access NCT04453839, plus both pemziviptadil analogue trials NCT03556020 and NCT04433546) | Extensive — rodent autoimmune, colitis, arthritis and pulmonary models |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status — three positions, stated separately. (1) The aviptadil + phentolamine intracavernosal injection is an approved prescription medicine for erectile dysfunction in a few European jurisdictions, positioned as a second-line option after PDE5-inhibitor failure or alprostadil intolerance 13,
How it is supplied and administered. Never orally — the peptide is digested. The approved product is a pre-filled intracavernosal injection. Research and off-label routes are nebulized inhalation, continuous intravenous infusion in hospital, and compounded intranasal spray. Gray-market material is typically lyophilized powder requiring reconstitution by the end user.
Sourcing is a safety issue here, more than for most peptides. Because there is no legal OTC form, consumer-obtained VIP comes either from compounding pharmacies — which vary widely in oversight and are not held to the manufacturing standards applied to approved drugs — or from unregulated research-chemical vendors with no manufacturing controls at all. Identity, correct sequence, peptide content, and bacterial endotoxin cannot be assumed without independent third-party certificates of analysis, and even those can be falsified. This matters especially for VIP because its routes are inhalation into the lung and injection into sterile compartments, where contaminated or endotoxin-bearing material has somewhere consequential to go. Self-reconstitution of lyophilized peptide adds a further sterility hazard. No vendor links appear here, and the only quality-controlled VIP-containing product in existence is the approved combination injection obtained on prescription.
Safety
VIP is a potent vasodilator, and its clearest human safety lesson comes not from a trial but from VIPoma — a tumor of sustained VIP excess that causes life-threatening diarrhea and potassium loss.
- Sustained VIP excess is dangerous in humans. VIPoma causes profuse watery diarrhea, hypokalemia and achlorhydria, fatal through dehydration and electrolyte loss.
- Potent vasodilator by design. Flushing, raised heart rate and delayed headache were produced deliberately in human infusion studies, and set the ceiling on any systemic dose.
- Pregnancy and lactation not assessed. Treated as contraindicated by default — see the box below.
- Additive hypotension is predictable. Nitrates, PDE5 inhibitors, alpha-blockers and other vasodilators — reasoning from mechanism, not a studied interaction.
- The intranasal route has no safety or pharmacokinetic data. It is the route most sold to consumers and the least characterized.
- Compounded and gray-market material is its own hazard. Unverified identity, purity and endotoxin, going into the lung or a sterile compartment.
Full Safety & Interactions Detail
The most important human safety dataset for VIP is not a trial — it is a tumor. A VIPoma is a rare functional neuroendocrine tumor, usually of the pancreatic islet cells, that secretes VIP autonomously and continuously. The resulting clinical syndrome — described by Verner and Morrison in 1958 and known as WDHA syndrome — is profuse refractory watery diarrhea, hypokalemia and achlorhydria, with metabolic acidosis; the combination of that picture with elevated plasma VIP is diagnostic 20,
Acute effects follow directly from the pharmacology, and were produced deliberately in humans. In the controlled infusion study that established VIP’s half-life, the highest dose raised pulse rate, increased blood-pressure amplitude, produced cutaneous flushing, and modestly raised plasma glucose, free fatty acids and calcium — and the authors explicitly noted that this spectrum of effects matched abnormalities seen in Verner-Morrison syndrome 2Reference 2Vasoactive intestinal peptide in man: pharmacokinetics, metabolic and circulatory effects — human (infusion PK)View study →. Two later placebo-controlled crossover studies in healthy volunteers add detail: a 25-minute infusion produced marked dilation of the superficial temporal artery and a significant increase in heart rate, with only very mild headache 23Reference 23RCTVasoactive intestinal polypeptide evokes only a minimal headache in healthy volunteers — human (double-blind crossover, n=12)View study →; a two-hour continuous infusion produced long-lasting cranial vasodilation, activation of cranial parasympathetic outflow, and a significantly higher incidence of delayed headache than placebo, most evident 4–12 hours afterwards 22Reference 22RCTTwo-hour infusion of vasoactive intestinal polypeptide induces delayed headache and extracranial vasodilation in healthy volunteers — human (placebo-controlled crossover, n=12)View study →. Longer exposure means more headache — a relevant pattern for anyone dosing repeatedly.
Hypotension and flushing are the reason systemic VIP has been so hard to develop as a drug. Vasodilation is not a side effect of VIP; it is its defining action, and it sets the ceiling on any systemic dose. In the intracavernosal ED setting the dominant adverse event is transient facial flushing, reported in 22.5% of 308 men, with ischemic priapism in 0.3% — a lower priapism rate than prostaglandin injections carry, but not zero 14Reference 14Intracavernosal injection of aviptadil and phentolamine for refractory erectile dysfunction — human (retrospective series, n=308)View study →. In the intravenous COVID trials aviptadil was broadly tolerated, though TESICO’s composite primary safety outcome occurred in 63% of the aviptadil group versus 56% on placebo (OR 1.40, 95% CI 0.94–2.08) — not statistically significant, but not reassuring either 4Reference 4RCTIntravenous aviptadil and remdesivir for treatment of COVID-19-associated hypoxaemic respiratory failure in the USA (TESICO): a randomised, placebo-controlled trial — human (RCT, n=461 analysed; stopped for futility)View study →. Inhaled and nebulized VIP was well tolerated over the short durations studied 1,
Interactions are mechanism-based, not studied. No dedicated interaction studies exist for any VIP preparation. On mechanism, additive hypotension with nitrates, PDE5 inhibitors, alpha-blockers, other vasodilators and antihypertensives is the predictable concern. This is reasoning from pharmacology, not a demonstrated interaction.
Who should avoid it. Anyone with significant hypotension, unstable cardiovascular disease, or a condition in which vasodilation or tachycardia would be dangerous. Anyone with unexplained chronic diarrhea should be evaluated rather than treated, given the VIPoma picture above. For the intracavernosal route, the standard ED-injectable contraindications apply — predisposition to priapism, sickle-cell disease, and penile anatomical abnormalities. And anyone unwilling to accept compounded or unregulated material of unverified identity, purity and endotoxin content.
Scope disclosure (honesty, not a claim):
- Human data? Yes, and unusually so for this collection — but unevenly. Approved-product and retrospective-series data for erectile dysfunction; multiple RCTs for intravenous aviptadil in COVID-19, of which the largest was negative; one small open-label study each for sarcoidosis and pulmonary hypertension; an RCT of an analogue in asthma. None for CIRS. None for any autoimmune indication.
- Interactions assessed? No. The additive-hypotension caution is mechanism-based only.
- Pregnancy/lactation assessed? No.
- Long-term safety established? No. Even the approved product is used intermittently. There is no long-term systemic-exposure safety dataset for any route, and none at all for chronic intranasal use.
- Intranasal route characterized? No — no published human pharmacokinetics, no dose-finding, no safety study, despite this being the route most commonly sold to consumers.
Never imply safety from silence. Where VIP has not been studied — intranasal dosing, interactions, pregnancy, long-term use, compounded product quality — the correct statement is “not assessed,” not “safe.”
Not assessed and not established for any VIP preparation or route. There are no adequate human pregnancy or lactation data. Treat as contraindicated by default.
Dosage
There is no established self-administered dose for VIP, and none is recommended here. It is a prescription and compounded molecule, its therapeutic uses all require clinical administration by injection, nebulizer or infusion, and the figures below are reported as data for context, not as a protocol.
The only approved regimen is the intracavernosal combination: aviptadil 25 µg with phentolamine mesylate 1–2 mg per injection, self-administered after training in a clinical setting 11,
The intranasal doses circulating in CIRS protocols are not established by any controlled trial, have no published pharmacokinetic basis, and are not reproduced here. Oral VIP products cannot deliver intact peptide and are pharmacologically inert regardless of what the label claims. This entry is informational only.
References
- Prasse A, Zissel G, Lützen N, et al. (2010). Inhaled vasoactive intestinal peptide exerts immunoregulatory effects in sarcoidosis — human (open-label phase II, n=20). American Journal of Respiratory and Critical Care Medicine. https://pubmed.ncbi.nlm.nih.gov/20442436/
- Domschke S, Domschke W, Bloom SR, et al. (1978). Vasoactive intestinal peptide in man: pharmacokinetics, metabolic and circulatory effects — human (infusion PK). Gut. https://pubmed.ncbi.nlm.nih.gov/730072/
- Youssef JG, Lavin P, Schoenfeld DA, et al. (2022). The use of IV vasoactive intestinal peptide (aviptadil) in patients with critical COVID-19 respiratory failure: results of a 60-day randomized controlled trial — human (RCT, n=196). Critical Care Medicine. https://pubmed.ncbi.nlm.nih.gov/36044317/
- Brown SM, Barkauskas CE, Grund B, et al. (2023). Intravenous aviptadil and remdesivir for treatment of COVID-19-associated hypoxaemic respiratory failure in the USA (TESICO): a randomised, placebo-controlled trial — human (RCT, n=461 analysed; stopped for futility). The Lancet Respiratory Medicine. https://pubmed.ncbi.nlm.nih.gov/37348524/
- Esendagli D, et al. (2025). Inhaled aviptadil is a new hope for recovery of lung damage due to COVID-19 — human (RCT, n=80). Medical Principles and Practice. https://pubmed.ncbi.nlm.nih.gov/39870064/
- Udupa AA, Todur P, Chaudhuri S, et al. (2025). Aviptadil therapy in acute respiratory distress syndrome patients: a systematic review and meta-analysis — meta-analysis of human studies. Indian Journal of Critical Care Medicine. https://pubmed.ncbi.nlm.nih.gov/41368449/
- Mathioudakis A, Chatzimavridou-Grigoriadou V, Evangelopoulou E, et al. (2013). Vasoactive intestinal peptide inhaled agonists: potential role in respiratory therapeutics — review. Hippokratia. https://pubmed.ncbi.nlm.nih.gov/23935337/
- Zhong HL, et al. (2023). The role of vasoactive intestinal peptide in pulmonary diseases — review. Life Sciences. https://pubmed.ncbi.nlm.nih.gov/37742737/
- Petkov V, Mosgoeller W, Ziesche R, et al. (2003). Vasoactive intestinal peptide as a new drug for treatment of primary pulmonary hypertension — human (open-label, n=8). Journal of Clinical Investigation. https://pubmed.ncbi.nlm.nih.gov/12727925/
- Lindén A, Hansson L, Andersson A, et al. (2003). Bronchodilation by an inhaled VPAC(2) receptor agonist in patients with stable asthma — human (randomised placebo-controlled crossover, n=24; analogue Ro 25-1553). Thorax. https://pubmed.ncbi.nlm.nih.gov/12612296/
- Dinsmore WW, Wyllie MG. (2008). Vasoactive intestinal polypeptide/phentolamine for intracavernosal injection in erectile dysfunction — review. BJU International. https://pubmed.ncbi.nlm.nih.gov/18485029/
- Keijzers GB. (2001). Aviptadil (Senatek) — review. Current Opinion in Investigational Drugs. https://pubmed.ncbi.nlm.nih.gov/11566015/
- Duncan C, Omran GJ, Teh J, et al. (2019). Erectile dysfunction: a global review of intracavernosal injectables — systematic review. World Journal of Urology. https://pubmed.ncbi.nlm.nih.gov/30895359/
- Al-Mitwalli A, et al. (2025). Intracavernosal injection of aviptadil and phentolamine for refractory erectile dysfunction — human (retrospective series, n=308). The Journal of Sexual Medicine. https://pubmed.ncbi.nlm.nih.gov/40192471/
- Martínez C, Juarranz Y, Gutiérrez-Cañas I, et al. (2019). A clinical approach for the use of VIP axis in inflammatory and autoimmune diseases — review. International Journal of Molecular Sciences. https://pubmed.ncbi.nlm.nih.gov/31861827/
- Leceta J, et al. (2021). Mechanism of immunoregulatory properties of vasoactive intestinal peptide in the K/BxN mice model of autoimmune arthritis — animal (mouse). Frontiers in Immunology. https://pubmed.ncbi.nlm.nih.gov/34335612/
- Langer I, Jeandriens J, Couvineau A, et al. (2022). Signal transduction by VIP and PACAP receptors — review. Biomedicines. https://pubmed.ncbi.nlm.nih.gov/35203615/
- Xu Y, et al. (2022). A distinctive ligand recognition mechanism by the human vasoactive intestinal polypeptide receptor 2 — in vitro (cryo-EM structural). Nature Communications. https://pubmed.ncbi.nlm.nih.gov/35477937/
- Yin J, et al. (2013). Vasodilatory effect of the stable vasoactive intestinal peptide analog RO 25-1553 in murine and rat lungs — animal (mouse, rat). PLoS One. https://pubmed.ncbi.nlm.nih.gov/24069452/
- Una Cidon E. (2022). Vasoactive intestinal peptide secreting tumour: an overview — review (human clinical). World Journal of Gastrointestinal Oncology. https://pubmed.ncbi.nlm.nih.gov/35582098/
- Belei OA, Heredea ER, Boeriu E, et al. (2017). Verner-Morrison syndrome: literature review — review (human clinical). Romanian Journal of Morphology and Embryology. https://pubmed.ncbi.nlm.nih.gov/28730220/
- Pellesi L, Al-Karagholi MA, Chaudhry BA, et al. (2020). Two-hour infusion of vasoactive intestinal polypeptide induces delayed headache and extracranial vasodilation in healthy volunteers — human (placebo-controlled crossover, n=12). Cephalalgia. https://pubmed.ncbi.nlm.nih.gov/32594760/
- Hansen JM, Sitarz J, Birk S, et al. (2006). Vasoactive intestinal polypeptide evokes only a minimal headache in healthy volunteers — human (double-blind crossover, n=12). Cephalalgia. https://pubmed.ncbi.nlm.nih.gov/16886936/



