
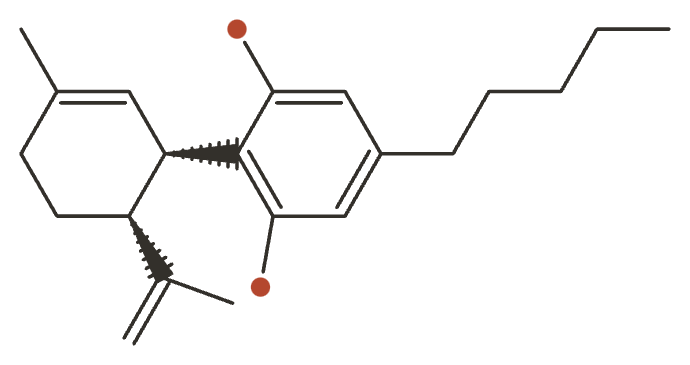
Compound Monograph
Cannabidiol
Cannabidiol (CBD) is the major non-intoxicating cannabinoid of cannabis and hemp — the active ingredient in an approved epilepsy medicine and a widely sold supplement, with a pharmacology that works largely around, not through, the CB1 receptor.

Sources · 1
Where Does It Come From?
Cannabidiol is a naturally occurring phytocannabinoid, found in Hemp and Cannabis. It is well tolerated orally (low toxicity).

Concentration
Content by Source
Concentrations not reported. No percent-dry-weight or mg/g figures have been published for this compound in its source plants.
Cannabidiol at a Glance
Cannabidiol (CBD) is the major non-intoxicating cannabinoid of cannabis and hemp, and one of very few plant compounds that is simultaneously an approved prescription medicine and a mass-market supplement.
Its pharmacology is the reason it does not get you high: CBD works largely around the CB1 receptor rather than through it, acting instead on serotonin 5-HT1A, TRPV1, GPR55 and adenosine signalling among others — a genuinely polypharmacological profile.
Its strongest evidence is in rare epilepsies, which is what it is approved for; that is a narrow and severe indication rather than the general wellness use it is sold for. The doses that produced that evidence are also far larger than the doses most people take.
Epidiolex vs. the CBD You Can Buy
Both are cannabidiol. Almost nothing else about them is the same, and the difference is mostly one of scale.
The dose gap is one to two orders of magnitude. The epilepsy trials used purified CBD oral solution at
10–20 mg/kg/day 1,
Absorption makes the gap wider, not narrower. Oral CBD bioavailability is about 6% and highly variable, and a high-fat meal can multiply exposure several-fold 7Reference 7Systematic reviewA Systematic Review on the Pharmacokinetics of Cannabidiol in Humans — review of human PKView study →. So the milligram figure on a label is a poor predictor of what reaches the blood, and two people taking the same product can be at very different exposures.
The high doses are not free. In healthy adults given 1,500 mg/day, ALT rose above normal in a substantial fraction and met drug-induced-liver-injury thresholds in some, resolving on stopping 9Reference 9Clinical trialCannabidiol and abnormal liver chemistries in healthy adults: results of a phase I clinical trialView study →. CBD inhibits several cytochrome P450 enzymes and roughly tripled exposure to clobazam’s active metabolite in a controlled study 8Reference 8A Phase 1 Open-Label Trial of Drug-Drug Interactions Between Clobazam, Stiripentol or Valproate and Cannabidiol in Healthy Subjects — human pharmacokinetic studyView study →. These are properties of the dose that works, which is exactly why the effective form is a prescription medicine with monitoring rather than a shelf product.
The honest position is not that retail CBD is fake. It is that the evidence belongs to a purified, high-dose, monitored preparation, and the retail product shares its molecule and very little else.
Working Around the Cannabinoid Receptor
CBD is a cannabinoid that barely uses the cannabinoid receptors, which is both why it is not intoxicating and why its pharmacology is so hard to summarise.
At CB1 — the receptor THC activates to produce the high — CBD has very low affinity and no meaningful agonism. What it does instead is distributed across a set of unrelated targets: 5-HT1A serotonin receptor agonism, TRPV1/TRPV2 vanilloid channel activation, inhibition of FAAH (which raises the body’s own anandamide rather than supplying an outside agonist), GPR55 antagonism, and PPARγ activation.
Two consequences follow.
It explains the breadth and the weakness together. A molecule with a dozen modest interactions will produce a signal in a dozen different assays, and a strong result in very few. That is precisely the shape of CBD’s evidence: overwhelming in one narrow indication, thin and preliminary everywhere else.
It explains why the anticonvulsant mechanism is still unsettled. CBD’s effect in Dravet and
Lennox-Gastaut syndromes is among the best-replicated findings for any plant compound 1,
What It's Used For
Cannabidiol is the non-intoxicating counterpart to THC and the dominant cannabinoid in most hemp. Its pharmacology is unusual: it barely touches the CB1 receptor that drives the cannabis “high,” and instead works through a scatter of other targets — serotonin 5-HT1A receptors, TRPV vanilloid channels, the enzyme FAAH (which raises the body’s own endocannabinoids), GPR55 and PPARγ. That broad, indirect profile is why CBD turns up in so many contexts, and why its evidence is strongest where it has been tested as a purified pharmaceutical rather than a wellness oil. One purified formulation (Epidiolex) is an approved anti-seizure medicine 1,
CBD’s strongest evidence by far. In placebo-controlled trials of purified CBD added to existing anti-seizure drugs, convulsive seizures in Dravet syndrome fell about 39% versus 13% on placebo 1Reference 1RCTTrial of Cannabidiol for Drug-Resistant Seizures in the Dravet Syndrome — randomised controlled trialView study →, and drop-seizures in Lennox-Gastaut syndrome fell roughly 42–44% versus ~17–22% at 10–20 mg/kg/day 2,
Gap: proven only for specific pediatric syndromes with prescription-grade CBD at high mg/kg doses — it doesn’t generalize to epilepsy broadly or to consumer CBD oils, and the clobazam interaction and the liver-enzyme rises at high dose need monitoring 8,
The calming reputation belongs to CBD specifically (high-THC cannabis can do the opposite). In a double-blind RCT, a single 600 mg oral dose reduced anxiety during a simulated public-speaking test in people with social anxiety disorder 4Reference 4RCTCannabidiol reduces the anxiety induced by simulated public speaking in treatment-naive social phobia patients — randomised controlled trialView study →, and several smaller acute-dosing studies point the same way.
Gap: the evidence is small, acute-challenge studies at 300–600 mg — far above retail doses — with no large trial of sustained dosing for a diagnosed anxiety disorder 4Reference 4RCTCannabidiol reduces the anxiety induced by simulated public speaking in treatment-naive social phobia patients — randomised controlled trialView study →.
Counterintuitively, CBD shows promise for helping people cut down on cannabis itself. In a phase 2a double-blind RCT, 400 mg and 800 mg daily beat placebo on measures of cannabis use in people with moderate-to-severe cannabis use disorder 5Reference 5RCTCannabidiol for the treatment of cannabis use disorder: a phase 2a, double-blind, placebo-controlled, randomised trialView study →.
Gap: a single well-designed trial — a credible signal awaiting replication at scale 5Reference 5RCTCannabidiol for the treatment of cannabis use disorder: a phase 2a, double-blind, placebo-controlled, randomised trialView study →.
An RCT of oral CBD-rich cannabis in Crohn’s disease produced clinical and quality-of-life improvement — but without endoscopic (mucosal) healing 6Reference 6RCTOral CBD-rich Cannabis Induces Clinical but Not Endoscopic Response in Patients with Crohn’s Disease — randomised controlled trialView study →, the recurring pattern for cannabis in IBD: symptoms ease while the underlying inflammation is unchanged.
Gap: symptomatic and quality-of-life benefit only; no evidence it modifies the disease, so it doesn’t replace standard IBD therapy 6Reference 6RCTOral CBD-rich Cannabis Induces Clinical but Not Endoscopic Response in Patients with Crohn’s Disease — randomised controlled trialView study →.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| 5-HT1A (serotonin) agonism | anxiolytic, anti-nausea | anxiety |
| TRPV1/TRPV2 vanilloid agonism | anti-inflammatory, analgesic | IBDpain |
| FAAH inhibition → ↑ anandamide | indirect endocannabinoid tone | anxietybroad |
| GPR55 antagonism; Ca²⁺-channel modulation | anticonvulsant | epilepsy |
| PPARγ activation | anti-inflammatory, neuroprotective | broad |
Clinical trials
CBD has an unusually large trial footprint for a plant compound, concentrated in epilepsy (where a purified product is licensed) with a growing spread into anxiety, substance use, inflammation and pain.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| Many(epilepsy-led) | Several | — | Extensive |
Last checked: July 2026.
Pharmacokinetics
CBD’s practical weak point is absorption. A systematic review of human CBD pharmacokinetics found oral bioavailability low and highly variable, on the order of 6%, because of poor water solubility and extensive first-pass metabolism — and found that a high-fat meal can raise exposure several-fold, the so-called food effect 7Reference 7Systematic reviewA Systematic Review on the Pharmacokinetics of Cannabidiol in Humans — review of human PKView study →. Reported half-life varies widely with route and regimen.
The practical upshot is that dose alone is a poor guide to what reaches the blood: formulation and whether the dose is taken with food matter as much as milligrams 7Reference 7Systematic reviewA Systematic Review on the Pharmacokinetics of Cannabidiol in Humans — review of human PKView study →. It also means the trial doses cannot be scaled down proportionally — a tenth of the dose in a different formulation on an empty stomach is not a tenth of the exposure.
CBD is metabolised largely by CYP3A4 and CYP2C19, and it inhibits several P450 enzymes itself, which is where its interaction burden comes from 8Reference 8A Phase 1 Open-Label Trial of Drug-Drug Interactions Between Clobazam, Stiripentol or Valproate and Cannabidiol in Healthy Subjects — human pharmacokinetic studyView study →.
Isolate vs. Plant Studies
Unusually for a plant compound, the good evidence is the isolate — and that is a strength rather than a caveat.
Every result in the table above used purified CBD except one. The epilepsy trials used a pharmaceutical
oral solution of purified cannabidiol 1,
The exception is instructive. The Crohn’s disease trial used oral CBD-rich cannabis, a whole-plant preparation, and produced clinical and quality-of-life improvement without endoscopic healing 6Reference 6RCTOral CBD-rich Cannabis Induces Clinical but Not Endoscopic Response in Patients with Crohn’s Disease — randomised controlled trialView study → — a result that cannot be attributed to CBD rather than to the other cannabinoids and terpenes in the extract.
What does not exist is evidence for the middle ground that most of the market occupies: “full-spectrum” hemp extracts at retail doses. Those are neither the purified high-dose pharmaceutical nor the studied whole-plant preparation, and no trial has tested them.
Its Role in Plants
CBD is not made as CBD. Cannabis synthesises cannabidiolic acid (CBDA), and heat decarboxylates it — the same chemistry described in detail on tetrahydrocannabinol.
The enzyme is CBDA synthase, purified from Cannabis sativa in 1996 and shown to catalyse the oxidocyclisation of cannabigerolic acid to cannabidiolic acid 13Reference 13Purification and characterization of cannabidiolic-acid synthase from Cannabis sativa L.: biochemical analysis of a novel enzyme that catalyzes the oxidocyclization of cannabigerolic acid to cannabidiolic acidView study →. It competes for that single substrate with THCA synthase and CBCA synthase, and which enzyme a plant carries and expresses is what makes it a chemotype: CBDA synthase is described as the chemotype-determining enzyme of fibre-type cannabis 14Reference 14Cannabidiolic-acid synthase, the chemotype-determining enzyme in the fiber-type Cannabis sativaView study →. A hemp plant is not a cannabis plant with the THC removed; it is a cannabis plant that routes the same precursor down a different branch.
Like the other cannabinoids, CBDA accumulates in the glandular trichomes of the female inflorescence, outside the living cells that make it.
Prevalence in Nature
CBD is, for practical purposes, a Cannabis sativa compound. It sits among more than a hundred catalogued phytocannabinoids from the plant 15Reference 15ReviewPhytocannabinoids: a unified critical inventory — reviewView study →, and no other genus is an established source.
Its distribution within cannabis is the mirror image of THC’s, and it has been moving. In drug-type cannabis CBD is a trace component and shrinking: across 38,681 DEA-seized samples, CBD fell from about 0.28% of dried flower in 2001 to under 0.15% by 2014, taking the THC:CBD ratio from roughly 14:1 to roughly 80:1 as breeders selected for potency 10Reference 10ObservationalChanges in cannabis potency over the last two decades (1995–2014): analysis of current data in the United States — observationalView study →. In the 2013–2022 follow-up, every cannabinoid other than THC sat below 0.5% in high-THC samples, apart from CBG and CBN 10Reference 10ObservationalChanges in cannabis potency over the last two decades (1995–2014): analysis of current data in the United States — observationalView study →.
CBD-chemotype hemp is the opposite plant. Industrial cultivars bred for CBD keep THC below the 0.3% statutory ceiling while accumulating CBDA as their dominant cannabinoid; in one three-cultivar Chinese survey, CBDA content rose across the series as THC fell 16Reference 16Cannabinoids and terpenoids in hemp inflorescence and leaves of three varieties in Yunnan, ChinaView study →. Published percentage figures for CBD in these cultivars are surprisingly scarce, and no consistent range exists that could be compared across provenances.
Major Natural Sources
| Source | Part | Level | Note |
|---|---|---|---|
| CBD-chemotype hemp (Cannabis sativa) | dried female inflorescence | dominant cannabinoid; no consistent published range | present as CBDA before heating 14, |
| Drug-type cannabis (Cannabis sativa) | dried female inflorescence | ~0.28% (2001) → <0.15% (2014) | falling as THC was selected up 10Reference 10ObservationalChanges in cannabis potency over the last two decades (1995–2014): analysis of current data in the United States — observationalView study → |
| Cannabis | leaf, stem | low, trichome-density dependent | no systematic survey |
| Cannabis | seed, root | negligible | no glandular trichomes |
Discovery & Synthesis
CBD was isolated before THC and before anyone knew what it was for. Roger Adams and colleagues at the University of Illinois obtained it from an extract of Minnesota wild hemp and published its structure in 1940 11Reference 11Structure of cannabidiol, a product isolated from the marihuana extract of Minnesota wild hempView study → — twenty-four years before THC was characterised, and at a time when the psychoactive principle of cannabis was still unidentified. The full structure and stereochemistry were settled in 1963 by Mechoulam and Shvo, the first paper in the series that would produce THC the following year 12Reference 12Hashish—I: the structure of cannabidiolView study →.
Manufacture today is extraction. Pharmaceutical CBD is purified from purpose-grown high-CBD cannabis rather than synthesised, and the same is true of the supplement supply. Total synthesis of CBD is straightforward chemistry and is done, but it does not compete on cost with a plant that makes the molecule at percent-level concentrations.
Patents: not yet researched (future patent-loop pass).
Toxicity & Safety
CBD is well tolerated, with the commonest effects being drowsiness, diarrhea and appetite change 1,
Dosage
Studied doses span a wide range depending on the goal — and they sit well above typical wellness products. These are doses studied in research, not a recommendation, and high-dose use is a medical decision given the interactions above.
| Application | Form | Dose (studied) | Source |
|---|---|---|---|
| Drug-resistant epilepsy | Purified CBD oral solution | 10–20 mg/kg/day | 1, |
| Anxiety (acute) | Purified CBD, single oral dose | 300–600 mg | 4Reference 4RCTCannabidiol reduces the anxiety induced by simulated public speaking in treatment-naive social phobia patients — randomised controlled trialView study → |
| Cannabis use disorder | Purified CBD, daily | 400–800 mg/day | 5Reference 5RCTCannabidiol for the treatment of cannabis use disorder: a phase 2a, double-blind, placebo-controlled, randomised trialView study → |
References
- Devinsky O, Cross JH, Laux L, et al. (2017). Trial of Cannabidiol for Drug-Resistant Seizures in the Dravet Syndrome — randomised controlled trial. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/28538134/
- Devinsky O, Patel AD, Cross JH, et al. (2018). Effect of Cannabidiol on Drop Seizures in the Lennox-Gastaut Syndrome — randomised controlled trial. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/29768152/
- Thiele EA, Marsh ED, French JA, et al. (2018). Cannabidiol in patients with seizures associated with Lennox-Gastaut syndrome (GWPCARE4) — randomised controlled trial. The Lancet. https://pubmed.ncbi.nlm.nih.gov/29395273/
- Bergamaschi MM, Queiroz RH, Chagas MH, et al. (2011). Cannabidiol reduces the anxiety induced by simulated public speaking in treatment-naive social phobia patients — randomised controlled trial. Neuropsychopharmacology. https://pubmed.ncbi.nlm.nih.gov/21307846/
- Freeman TP, Hindocha C, Baio G, et al. (2020). Cannabidiol for the treatment of cannabis use disorder: a phase 2a, double-blind, placebo-controlled, randomised trial. The Lancet Psychiatry. https://pubmed.ncbi.nlm.nih.gov/32735782/
- Naftali T, Bar-Lev Schleider L, Almog S, et al. (2021). Oral CBD-rich Cannabis Induces Clinical but Not Endoscopic Response in Patients with Crohn’s Disease — randomised controlled trial. Journal of Crohn’s & Colitis. https://pubmed.ncbi.nlm.nih.gov/33858011/
- Millar SA, Stone NL, Yates AS, O’Sullivan SE (2018). A Systematic Review on the Pharmacokinetics of Cannabidiol in Humans — review of human PK. Frontiers in Pharmacology. https://pubmed.ncbi.nlm.nih.gov/30534073/
- Morrison G, Crockett J, Blakey G, Sommerville K (2019). A Phase 1 Open-Label Trial of Drug-Drug Interactions Between Clobazam, Stiripentol or Valproate and Cannabidiol in Healthy Subjects — human pharmacokinetic study. Clinical Pharmacology in Drug Development. https://pubmed.ncbi.nlm.nih.gov/30791225/
- Watkins PB, Church RJ, Li J, Knappertz V (2021). Cannabidiol and abnormal liver chemistries in healthy adults: results of a phase I clinical trial. Clinical Pharmacology & Therapeutics. https://pubmed.ncbi.nlm.nih.gov/33022751/
- ElSohly MA, Mehmedic Z, Foster S, et al. (2016). Changes in cannabis potency over the last two decades (1995–2014): analysis of current data in the United States — observational. Biological Psychiatry. https://pubmed.ncbi.nlm.nih.gov/26903403/
- Adams R, Hunt M, Clark JH (1940). Structure of cannabidiol, a product isolated from the marihuana extract of Minnesota wild hemp. I. Journal of the American Chemical Society. https://doi.org/10.1021/ja01858a058
- Mechoulam R, Shvo Y (1963). Hashish—I: the structure of cannabidiol. Tetrahedron. https://doi.org/10.1016/0040-4020(63)85022-x
- Taura F, Morimoto S, Shoyama Y (1996). Purification and characterization of cannabidiolic-acid synthase from Cannabis sativa L.: biochemical analysis of a novel enzyme that catalyzes the oxidocyclization of cannabigerolic acid to cannabidiolic acid. Journal of Biological Chemistry. https://pubmed.ncbi.nlm.nih.gov/8663284/
- Taura F, Sirikantaramas S, Shoyama Y, et al. (2007). Cannabidiolic-acid synthase, the chemotype-determining enzyme in the fiber-type Cannabis sativa. FEBS Letters. https://pubmed.ncbi.nlm.nih.gov/17544411/
- Hanuš LO, Meyer SM, Muñoz E, et al. (2016). Phytocannabinoids: a unified critical inventory — review. Natural Product Reports. https://pubmed.ncbi.nlm.nih.gov/27722705/
- Jiang X, Cai Y, Teng Y, et al. (2026). Cannabinoids and terpenoids in hemp inflorescence and leaves of three varieties in Yunnan, China. Rapid Communications in Mass Spectrometry. https://pubmed.ncbi.nlm.nih.gov/42185735/



