
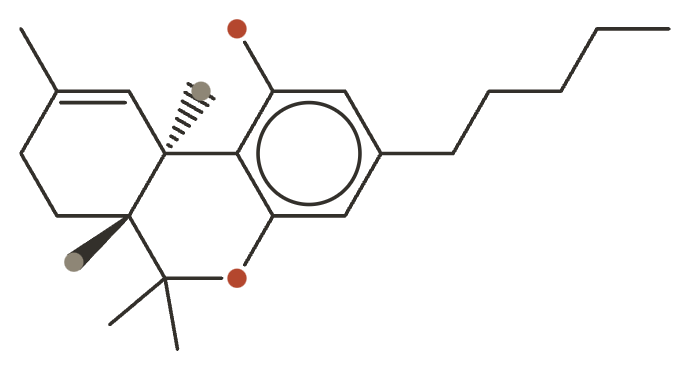
Compound Monograph
Tetrahydrocannabinol
THC is the principal psychoactive cannabinoid of cannabis — a CB1/CB2 agonist behind the plant's "high" and its licensed uses for nausea, appetite and (with CBD) muscle spasticity.

Sources · 1
Where Does It Come From?
Tetrahydrocannabinol is a naturally occurring phytocannabinoid, found in Marijuana and Hemp. It is flagged as moderately toxic.

Concentration
Content by Source
Reported concentrations across the plants that contain tetrahydrocannabinol — the bar marks the typical level, the line shows the reported range.
Literature figures for varying plant parts and preparations. Read them as a comparative guide, not exact assays.
Tetrahydrocannabinol at a Glance
THC is the principal psychoactive cannabinoid of cannabis — a CB1 and CB2 receptor agonist, and the compound responsible for the plant’s intoxicating effects.
CB1 receptors are among the most abundant G-protein-coupled receptors in the brain, which is why THC affects perception, memory, appetite and pain simultaneously rather than producing one discrete effect.
It also has licensed medical uses: chemotherapy-induced nausea, appetite stimulation, and — combined with CBD — muscle spasticity in multiple sclerosis.
The living plant contains almost no THC. It makes THCA, an acid that is not intoxicating, and heat does the rest.
THCA and the Decarboxylation Step
Cannabis does not make THC. It makes tetrahydrocannabinolic acid — THCA — which carries a carboxylic acid group on the aromatic ring and does not activate CB1. Raw, fresh cannabis is not intoxicating for this reason.
Heat removes that carboxyl group as carbon dioxide, converting THCA to THC. Smoking, vaporising and baking all do it; drying and long storage do it slowly. Every route by which cannabis is actually consumed involves a decarboxylation step, which is why the distinction stays invisible to most users and matters enormously to anyone measuring, cooking with or regulating the plant.
Three practical consequences follow.
- A laboratory result quoting “total THC” is a calculated figure: measured THC plus measured THCA multiplied by 0.877, the mass ratio between the two molecules. A flower reported at 20% total THC contains mostly THCA.
- Edibles need deliberate decarboxylation. Raw plant material stirred into food delivers THCA, not THC.
- Juiced or raw cannabis is a different pharmacology entirely — a preparation of cannabinoid acids, which have their own receptor profiles and none of the intoxication.
The enzyme responsible is THCA synthase, an FAD-dependent oxidocyclase that converts cannabigerolic acid into THCA 14Reference 14The gene controlling marijuana psychoactivity: molecular cloning and heterologous expression of Δ1-tetrahydrocannabinolic acid synthase from Cannabis sativa LView study →. Its closest known relative is not another cannabis enzyme: it is the berberine bridge enzyme of California poppy, which builds isoquinoline alkaloids 14Reference 14The gene controlling marijuana psychoactivity: molecular cloning and heterologous expression of Δ1-tetrahydrocannabinolic acid synthase from Cannabis sativa LView study →.
Potency Has Changed, and the Evidence Base Has Not
Almost every clinical trial of THC used a standardised pharmaceutical product with a stated milligram dose. Almost every real-world user consumes flower whose THC content has risen sharply within living memory. The two are drifting apart.
The best long-run dataset is the US DEA seizure series. Across 38,681 samples analysed between 1995 and 2014, the THC content of confiscated cannabis rose from about 4% to about 12%, while CBD content fell from ~0.28% in 2001 to under 0.15% — moving the THC:CBD ratio from roughly 14:1 to roughly 80:1 11Reference 11ObservationalChanges in cannabis potency over the last two decades (1995–2014): analysis of current data in the United States — observationalView study →. A follow-up covering 2013–2022 found most seized high-THC samples above 10% THC with every other cannabinoid under 0.5%, apart from CBG and CBN under 1%, and found the profile essentially unchanged across US regions — genetics rather than geography setting it 12Reference 12ObservationalA 10-year trend in cannabis potency (2013–2022) in different geographical regions of the United States of America — observationalView study →.
Two things follow. The material people use is roughly three times stronger than the material the older epidemiology described, and it now arrives with far less CBD alongside it. Where the psychosis association is concerned, it is high-potency use specifically that carries the strongest signal 10Reference 10Meta-analysisMeta-analysis of the association between the level of cannabis use and risk of psychosisView study → — so a shifting denominator is not a technicality.
What It's Used For
Tetrahydrocannabinol is the main psychoactive constituent of cannabis and the reason the plant is intoxicating. Unlike CBD, it acts directly on the endocannabinoid receptors — a partial agonist at both CB1 (concentrated in the brain, behind the effects on mood, perception, appetite and memory) and CB2 (in immune tissue). That direct CB1 action is a double edge: it powers THC’s genuine medicinal uses — antinausea, appetite stimulation, analgesia — and also its psychoactivity, impairment and dependence liability. Its best clinical evidence comes from standardized pharmaceutical forms: synthetic THC (dronabinol, nabilone) as an antiemetic, and a standardized 1:1 THC:CBD spray (nabiximols) for multiple-sclerosis spasticity 1,
Nabiximols — a standardized 1:1 THC:CBD oromucosal spray — is licensed in many countries for multiple-sclerosis spasticity that resists first-line drugs. A meta-analysis of the pivotal RCTs found a modest but reproducible reduction in patient-rated spasticity 2Reference 2Meta-analysisMeta-analysis of the efficacy and safety of Sativex (nabiximols) on spasticity in people with multiple sclerosisView study →, and the 2022 Cochrane review rates the evidence low-to-moderate certainty with a small average effect 3Reference 3Systematic reviewCannabis and cannabinoids for symptomatic treatment for people with multiple sclerosis — Cochrane systematic reviewView study →.
Gap: the effect is modest and driven partly by subjective self-report; roughly half of patients are non-responders, and the standardized spray doesn’t represent smoked or edible cannabis 3Reference 3Systematic reviewCannabis and cannabinoids for symptomatic treatment for people with multiple sclerosis — Cochrane systematic reviewView study →.
Synthetic THC (dronabinol, nabilone) has been a licensed antiemetic since the 1980s — one of cannabis’s oldest evidence-based uses. A Cochrane review found cannabinoids more effective than placebo and broadly comparable to older antiemetics, and often the treatment patients preferred 1Reference 1Systematic reviewCannabinoids for nausea and vomiting in adults with cancer receiving chemotherapy — Cochrane systematic reviewView study →.
Gap: the trials predate modern antiemetics; benefit over today’s standard drugs (setrons, NK1 antagonists) is unproven, so THC now sits as an option for nausea that resists first-line therapy 1Reference 1Systematic reviewCannabinoids for nausea and vomiting in adults with cancer receiving chemotherapy — Cochrane systematic reviewView study →.
Across many RCTs and a 2026 Cochrane review, cannabis-based medicines produce a small reduction in chronic neuropathic pain, with sedation and dizziness common 6Reference 6Systematic reviewCannabis-based medicines for chronic neuropathic pain in adults — Cochrane systematic reviewView study →; the JAMA umbrella review rated the overall pain evidence moderate-quality 5Reference 5Meta-analysisCannabinoids for Medical Use: A Systematic Review and Meta-analysisView study →. THC is a genuine but modest analgesic, best considered for stubborn nerve pain rather than pain in general.
Gap: effect sizes are small and inconsistent, and in cancer pain specifically the evidence is largely null 5,
The appetite-stimulating “munchies” effect is real — THC drives appetite through CB1 receptors — and dronabinol supported appetite in HIV-associated wasting. In cancer cachexia, though, controlled trials are largely null: cannabinoids didn’t beat placebo or megestrol for appetite or weight 4Reference 4Meta-analysisSystematic review and meta-analysis of cannabinoids in palliative medicineView study →.
Gap: the appetite effect is pharmacologically genuine but clinically unreliable where it’s most needed 4Reference 4Meta-analysisSystematic review and meta-analysis of cannabinoids in palliative medicineView study →.
A textbook case of a real effect that isn’t useful. THC does lower intraocular pressure, but only for about 3–4 hours per dose, which would demand near-continuous (and continuously intoxicating) dosing — which is why ophthalmology bodies don’t recommend it 8Reference 8ReviewCannabinoids and glaucoma — reviewView study →.
Gap: the pressure-lowering is too short-lived to be practical, and no cannabis preparation is a recommended glaucoma therapy 8Reference 8ReviewCannabinoids and glaucoma — reviewView study →.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| CB1 receptor partial agonism (CNS) | psychoactivity, appetite, anti-nausea, analgesia | nauseaappetitepain |
| CB2 receptor agonism (immune tissue) | anti-inflammatory, immunomodulation | spasticityinflammation |
| PPARγ activation | anti-inflammatory, neuroprotective, antitumor (preclinical) | broad |
Clinical trials
THC has a large trial footprint across nausea, spasticity, pain and appetite, much of it via the licensed pharmaceutical forms (dronabinol, nabilone, nabiximols) rather than whole plant.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| Many | Several | Some | Extensive |
Last checked: July 2026.
Pharmacokinetics
Route changes everything. Inhaled THC reaches the blood within minutes; taken orally, bioavailability is low and variable — roughly 6–20% — because of extensive first-pass metabolism 9Reference 9ReviewPharmacokinetics and Pharmacodynamics of Cannabinoids — review of human PKView study →. That first pass also converts THC into 11-hydroxy-THC, a metabolite at least as psychoactive as THC itself, which is why eaten cannabis feels slower in onset, longer in duration and often stronger than the milligram dose predicts 9Reference 9ReviewPharmacokinetics and Pharmacodynamics of Cannabinoids — review of human PKView study →.
THC is highly lipophilic. It distributes into fat and clears with a long, multi-phase terminal half-life, so it and its metabolites are detectable long after any effect has gone — the reason a positive test says nothing about impairment at the time of testing 9Reference 9ReviewPharmacokinetics and Pharmacodynamics of Cannabinoids — review of human PKView study →.
Isolate vs. Plant Studies
This is one of the few pages where the isolate/plant split is also a legal and clinical divide, and it runs almost entirely one way.
The evidence is pharmaceutical. Dronabinol and nabilone are synthetic THC in a capsule with a
milligram dose 1Reference 1Systematic reviewCannabinoids for nausea and vomiting in adults with cancer receiving chemotherapy — Cochrane systematic reviewView study →. Nabiximols is a plant-derived but standardised 1:1 THC:CBD oromucosal spray delivering
2.7 mg THC and 2.5 mg CBD per actuation 2,
The plant side is epidemiology, not efficacy. What is known about whole cannabis in humans at scale comes from observational work — the psychosis dose–response 10Reference 10Meta-analysisMeta-analysis of the association between the level of cannabis use and risk of psychosisView study → — rather than from trials of a defined preparation.
The two do not translate cleanly in either direction. A pharmaceutical trial cannot license a claim about flower, because flower delivers a different dose by a different route alongside dozens of other cannabinoids and terpenes. And an epidemiological harm signal from high-potency flower does not transfer to a 2.7 mg spray. Anyone reasoning from one to the other is making an assumption, not reading a result.
Its Role in Plants
THCA is made and stored in the glandular trichomes that coat the female inflorescence — stalked capitate glands whose secretory cells export the cannabinoid into a resin-filled cavity outside the living cytoplasm. The plant’s most concentrated chemistry is held outside its own cells.
The pathway is short. A polyketide route builds olivetolic acid, geranyl pyrophosphate is attached to
give cannabigerolic acid (CBGA), and three FAD-dependent oxidocyclases then compete for that single
substrate: THCA synthase to THCA, CBDA synthase to CBDA, and CBCA synthase to CBCA 14,
The clearest evidence that this is defensive chemistry is where it sits: on the bracts and calyxes protecting the developing seed, in an extracellular cavity, at concentrations that dominate the tissue’s dry weight. THCA synthase’s closest characterised relative is the berberine bridge enzyme of California poppy 14Reference 14The gene controlling marijuana psychoactivity: molecular cloning and heterologous expression of Δ1-tetrahydrocannabinolic acid synthase from Cannabis sativa LView study → — a reminder that cannabis’s chemistry evolved out of ordinary plant-defence enzymology rather than anything exotic.
Prevalence in Nature
THC is effectively unique to Cannabis sativa. Of the 100-plus phytocannabinoids catalogued from the plant, THC is the one with high-affinity CB1 agonism, and no other plant genus is an established source of it 15Reference 15ReviewPhytocannabinoids: a unified critical inventory — reviewView study →.
Within cannabis it is a female inflorescence compound, concentrated in the glandular trichomes of the flowering tops and the small leaves immediately around them, sparse in fan leaves and stems, and absent from seed and root. Its concentration is set principally by genotype: the 2013–2022 DEA survey found the cannabinoid profile of high-THC samples essentially identical across US regions, concluding that genetics rather than growing location controls it 12Reference 12ObservationalA 10-year trend in cannabis potency (2013–2022) in different geographical regions of the United States of America — observationalView study →.
The quantitative picture, from the largest datasets available:
- Drug-type flower. ~4% THC in 1995 rising to ~12% by 2014 across 38,681 DEA seizures 11Reference 11ObservationalChanges in cannabis potency over the last two decades (1995–2014): analysis of current data in the United States — observationalView study →; most 2013–2022 seized high-THC samples above 10% 12Reference 12ObservationalA 10-year trend in cannabis potency (2013–2022) in different geographical regions of the United States of America — observationalView study →.
- Fibre hemp. Held below 0.3% THC by statute in most jurisdictions, a threshold Chinese industrial cultivars meet with room to spare 16Reference 16Cannabinoids and terpenoids in hemp inflorescence and leaves of three varieties in Yunnan, ChinaView study →.
- Everything else in the plant. In high-THC samples every other cannabinoid sits under 0.5%, except CBG and CBN, which reach up to 1% 12Reference 12ObservationalA 10-year trend in cannabis potency (2013–2022) in different geographical regions of the United States of America — observationalView study →.
Major Natural Sources
| Source | Part | Level | Note |
|---|---|---|---|
| Drug-type cannabis (Cannabis sativa) | dried female inflorescence | ~4% (1995) → ~12% (2014); >10% in most recent seizures | as THCA before heating 11, |
| Drug-type cannabis | sugar leaf, trim | lower, trichome-density dependent | no systematic survey |
| Fibre hemp (Cannabis sativa) | dried inflorescence | <0.3% | statutory ceiling; met by industrial cultivars 16Reference 16Cannabinoids and terpenoids in hemp inflorescence and leaves of three varieties in Yunnan, ChinaView study → |
| Cannabis | seed, root, stem | negligible | no glandular trichomes |
Discovery & Synthesis
THC was isolated, structurally characterised and partly synthesised in a single 1964 paper by Yehiel Gaoni and Raphael Mechoulam, working on hashish at the Weizmann Institute 13Reference 13Isolation, structure, and partial synthesis of an active constituent of hashishView study →. That the principal psychoactive constituent of the world’s most-used illicit drug was unidentified until 1964 — sixty-five years after cannabinol had been characterised and twenty-four after cannabidiol — is a consequence of how hard the neutral cannabinoids were to separate before chromatography.
Manufacture today runs on both routes. Dronabinol is synthetic THC, made chemically and formulated in sesame oil, which is why it is a defined drug substance rather than a botanical. Nabiximols is extracted from purpose-grown chemotypes and standardised. Recreational and dispensary THC is neither: it is plant material, sold by potency rather than by dose.
Patents: not yet researched (future patent-loop pass).
Toxicity & Safety
Acute lethal toxicity is very low — there’s no established fatal dose — but THC’s risk profile follows from its CB1 activity. Acutely it impairs coordination, reaction time and judgment (impaired driving is one of its best-established harms) and can cause anxiety, paranoia or, at high doses, transient psychosis. With regular use it builds tolerance and dependence, and — the most important longer-term signal — heavier and higher-potency use is consistently associated with an increased risk of psychotic disorders, so it should be avoided by anyone with a personal or family history of psychosis or schizophrenia 10Reference 10Meta-analysisMeta-analysis of the association between the level of cannabis use and risk of psychosisView study →. That signal has to be read against a moving target: the THC content of seized cannabis roughly tripled between 1995 and 2014 while its CBD content fell by half 11Reference 11ObservationalChanges in cannabis potency over the last two decades (1995–2014): analysis of current data in the United States — observationalView study →, so contemporary exposure sits further along the same dose–response curve than the older epidemiology measured. THC also raises heart rate and can affect blood pressure, relevant in cardiovascular disease. Legal status varies widely (it remains federally Schedule I in the United States); the pharmaceutical form dronabinol is separately scheduled and prescription-only.
Dosage
The doses below are the studied pharmaceutical forms, not whole-flower use, and are not a recommendation — THC is psychoactive and, in most places, prescription-only or restricted. Whole-plant THC has no standardized dose; effects climb quickly with potency, so the practical rule for any THC-containing product is start low and go slow.
| Application | Form | Dose (studied) | Source |
|---|---|---|---|
| Chemotherapy nausea | Dronabinol (synthetic THC) | ~5 mg/m² per dose | 1Reference 1Systematic reviewCannabinoids for nausea and vomiting in adults with cancer receiving chemotherapy — Cochrane systematic reviewView study → |
| MS spasticity | Nabiximols spray (2.7 mg THC + 2.5 mg CBD/spray) | self-titrated, up to ~12 sprays/day | 2, |
References
- Smith LA, Azariah F, Lavender VT, et al. (2015). Cannabinoids for nausea and vomiting in adults with cancer receiving chemotherapy — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/26561338/
- Wade DT, Collin C, Stott C, Duncombe P (2010). Meta-analysis of the efficacy and safety of Sativex (nabiximols) on spasticity in people with multiple sclerosis. Multiple Sclerosis Journal. https://pubmed.ncbi.nlm.nih.gov/20558502/
- Filippini G, Minozzi S, Borrelli F, et al. (2022). Cannabis and cannabinoids for symptomatic treatment for people with multiple sclerosis — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/35510826/
- Mücke M, Weier M, Carter C, et al. (2018). Systematic review and meta-analysis of cannabinoids in palliative medicine. Journal of Cachexia, Sarcopenia and Muscle. https://pubmed.ncbi.nlm.nih.gov/29400010/
- Whiting PF, Wolff RF, Deshpande S, et al. (2015). Cannabinoids for Medical Use: A Systematic Review and Meta-analysis. JAMA. https://pubmed.ncbi.nlm.nih.gov/26103030/
- Ateş G, Welsch P, Klose P, et al. (2026). Cannabis-based medicines for chronic neuropathic pain in adults — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/41548880/
- Guzmán M, Duarte MJ, Blázquez C, et al. (2006). A pilot clinical study of delta-9-tetrahydrocannabinol in patients with recurrent glioblastoma multiforme — clinical trial. British Journal of Cancer. https://pubmed.ncbi.nlm.nih.gov/16804518/
- Tomida I, Pertwee RG, Azuara-Blanco A (2004). Cannabinoids and glaucoma — review. British Journal of Ophthalmology. https://pubmed.ncbi.nlm.nih.gov/15090428/
- Grotenhermen F (2003). Pharmacokinetics and Pharmacodynamics of Cannabinoids — review of human PK. Clinical Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/12648025/
- Marconi A, Di Forti M, Lewis CM, et al. (2016). Meta-analysis of the association between the level of cannabis use and risk of psychosis. Schizophrenia Bulletin. https://pubmed.ncbi.nlm.nih.gov/26884547/
- ElSohly MA, Mehmedic Z, Foster S, et al. (2016). Changes in cannabis potency over the last two decades (1995–2014): analysis of current data in the United States — observational. Biological Psychiatry. https://pubmed.ncbi.nlm.nih.gov/26903403/
- ElSohly MA, Majumdar CG, Chandra S, et al. (2024). A 10-year trend in cannabis potency (2013–2022) in different geographical regions of the United States of America — observational. Frontiers in Public Health. https://pubmed.ncbi.nlm.nih.gov/39421827/
- Gaoni Y, Mechoulam R (1964). Isolation, structure, and partial synthesis of an active constituent of hashish. Journal of the American Chemical Society. https://doi.org/10.1021/ja01062a046
- Sirikantaramas S, Morimoto S, Shoyama Y, et al. (2004). The gene controlling marijuana psychoactivity: molecular cloning and heterologous expression of Δ1-tetrahydrocannabinolic acid synthase from Cannabis sativa L. Journal of Biological Chemistry. https://pubmed.ncbi.nlm.nih.gov/15190053/
- Hanuš LO, Meyer SM, Muñoz E, et al. (2016). Phytocannabinoids: a unified critical inventory — review. Natural Product Reports. https://pubmed.ncbi.nlm.nih.gov/27722705/
- Jiang X, Cai Y, Teng Y, et al. (2026). Cannabinoids and terpenoids in hemp inflorescence and leaves of three varieties in Yunnan, China. Rapid Communications in Mass Spectrometry. https://pubmed.ncbi.nlm.nih.gov/42185735/
- Taura F, Morimoto S, Shoyama Y (1996). Purification and characterization of cannabidiolic-acid synthase from Cannabis sativa L.: biochemical analysis of a novel enzyme that catalyzes the oxidocyclization of cannabigerolic acid to cannabidiolic acid. Journal of Biological Chemistry. https://pubmed.ncbi.nlm.nih.gov/8663284/
- Fulvio F, Paris R, Montanari M, et al. (2021). Analysis of sequence variability and transcriptional profile of cannabinoid synthase genes in Cannabis sativa L. chemotypes with a focus on cannabichromenic acid synthase. Plants. https://pubmed.ncbi.nlm.nih.gov/34579390/



