
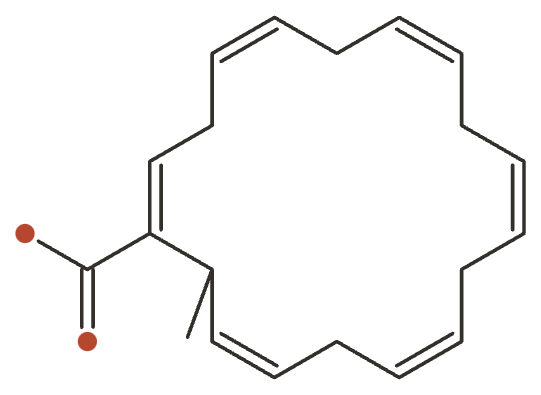

DHA (Docosahexaenoic acid) at a Glance
Docosahexaenoic acid (DHA) is a long-chain omega-3 polyunsaturated fatty acid and the single most abundant structural fat in the brain’s grey matter and the retinal photoreceptors. That structural role is not in dispute: DHA is genuinely required for building neural and retinal membranes, and a dietary supply matters most during the fetal and infant period of rapid neural growth.
The harder question is what supplementing DHA does on top of an already-adequate intake — and here the picture splits sharply. The best-replicated human benefits are in pregnancy (fewer preterm births) and in blood lipids (lower triglycerides). Several heavily-marketed adult uses — memory, Alzheimer’s, dry eye, macular degeneration — have produced large, high-quality null trials.
DHA is also rarely tested alone. Most products and trials combine it with EPA, and DHA’s own effect on some markers differs from EPA’s — notably LDL cholesterol, which DHA raises and EPA does not. So the companion fatty acid matters, and the two are not interchangeable.
What It’s Used For
- Preterm birth & gestation length — the clearest clinical benefit DHA has, from high-quality Cochrane evidence.
- Triglyceride reduction — robust, dose-dependent, and with an LDL-raising trade-off.
- Infant visual & neural development — the structural role is established; the supplementation trials are mixed.
- Childhood ADHD symptoms — a small effect, concentrated in children who start out deficient.
- Age-related cognitive decline — one positive memory trial against mixed broader data.
- Depression — where omega-3s help mood, the active component is EPA, not DHA.
Several endpoints people look for here — blood pressure, general cardiovascular prevention and liver fat in fatty liver disease — were studied as combined EPA+DHA rather than DHA alone, so they are covered on the fish oil page rather than duplicated here.
Three large, well-run trials came back essentially null, and they are the ones behind the biggest marketing claims. DHA did not slow decline in established Alzheimer’s disease. It did not relieve dry eye disease (DREAM). And omega-3s did not reduce progression of age-related macular degeneration (AREDS2). Routine fortification of term-infant formula also shows no consistent benefit.
How It Works
DHA’s primary mechanism is not pharmacological but architectural. It is incorporated directly into membrane phospholipids, and in neurons and photoreceptors it makes up an extraordinary share of them — its six double bonds give the membrane the fluidity that synaptic vesicle fusion and photoreceptor signalling depend on. This is why the developmental window matters so much: the fetal brain accumulates DHA rapidly in the third trimester, and the material has to come from somewhere.
In the liver, DHA suppresses triglyceride synthesis and VLDL secretion — the triglyceride mechanism. It also raises LDL cholesterol through effects on lipoprotein metabolism, a DHA-specific trade-off that EPA does not share.
Two secondary routes underpin the anti-inflammatory claims: DHA is the precursor to resolvins and protectins, the specialised pro-resolving mediators that actively terminate inflammation, and it competes with arachidonic acid for eicosanoid synthesis — which also produces the mild antiplatelet effect behind the bleeding caution.
The kinetics follow from the mechanism. Because the relevant pool is membrane-bound rather than circulating, tissue DHA turns over weeks, and the functionally meaningful measure is membrane enrichment (the Omega-3 Index), not a plasma level.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Docosahexaenoic acid (DHA, 22:6 n-3) is a long-chain omega-3 polyunsaturated fatty acid and the single most abundant structural fat in the brain’s grey matter and the retinal photoreceptors. That structural role is not in dispute: DHA is genuinely required for building neural and retinal membranes, and a dietary supply matters most during the fetal and infant period of rapid neural growth. The harder question is what supplementing DHA does on top of an already-adequate intake — and here the picture splits sharply. The best-replicated human benefit is in pregnancy (fewer preterm births) and in blood lipids (lower triglycerides), while several heavily-marketed adult uses — memory, Alzheimer’s, dry eye, macular degeneration — have produced large, high-quality null trials. DHA is also rarely tested alone: most products and trials combine it with EPA, and DHA’s own effect on some markers (notably LDL cholesterol, which it raises) differs from EPA’s, so form and companion fatty acid matter.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
In the 2018 Cochrane review of 70 RCTs (19,927 women), omega-3 LCPUFA during pregnancy — DHA being the fatty acid the fetal brain accumulates in the third trimester — lowered preterm birth before 37 weeks (13.4% against 11.9%; RR 0.89, 95% CI 0.81–0.97; 26 RCTs, 10,304 women) and early preterm birth before 34 weeks (4.6% against 2.7%; RR 0.58, 95% CI 0.44–0.77; 9 RCTs, 5,204 women), both rated high-quality evidence 1Reference 1Systematic reviewOmega-3 fatty acid addition during pregnancy — Cochrane systematic reviewView study →. Typical prenatal doses providing 200–300 mg/day DHA, or higher in dedicated trials, underlie this signal, and it is the most decision-relevant benefit of DHA supplementation.
Gap: the benefit is a modest absolute risk reduction and is strongest in women with low baseline omega-3 status; very high doses have not shown proportionally larger gains, and one high-dose neonatal trial found no lasting behavioural benefit at 5 years 15Reference 15RCTMaternal high-dose docosahexaenoic acid supplementation and neurodevelopment at 5 years in preterm children — randomized controlled trial follow-up. https://pubmed.ncbi.nlm.nih.gov/39396702/View study →.
DHA reliably lowers serum triglycerides. In a meta-analysis of monotherapy trials, both DHA and EPA reduced triglycerides, with a somewhat greater reduction by DHA in head-to-head comparisons — however, DHA also raised LDL cholesterol by about 7 mg/dL against placebo (and 4.6 mg/dL more than EPA) while raising HDL by about 4.5 mg/dL 3Reference 3Meta-analysisEffects of eicosapentaenoic acid versus docosahexaenoic acid on serum lipids: a systematic review and meta-analysisView study →.
Later meta-analyses in metabolic-syndrome populations confirm the triglyceride-lowering effect across doses 4Reference 4Meta-analysisEffects of dietary eicosapentaenoic acid and docosahexaenoic acid supplementation on metabolic syndrome: a systematic review and meta-analysis of 33 randomized controlled trialsView study →.
The magnitude is dose-dependent and clinically useful for hypertriglyceridemia.
Gap: DHA’s LDL-raising effect is a genuine trade-off that EPA does not share, so the two are not interchangeable; nearly all products combine EPA and DHA, and gram-level doses are needed for meaningful triglyceride change.
DHA is a structural requirement for the developing brain and retina, and a dietary supply is needed for optimal development 2Reference 2ReviewDocosahexaenoic acid and human brain development: evidence that a dietary supply is needed for optimal development — reviewView study →.
But supplementation trials are mixed. A Cochrane review of LCPUFA in term infants (15 RCTs, n≈1,889) found some benefit for visual-evoked-potential acuity at 12 months (MD −0.15 logMAR) but no consistent effect across methods and mostly null neurodevelopmental outcomes, concluding routine fortification of term-infant formula cannot be recommended 5Reference 5Systematic reviewLong chain polyunsaturated fatty acid supplementation in infants born at term — Cochrane systematic reviewView study →.
Earlier RCT reviews reported gains on some visual and cognitive measures in infants given DHA, usually with arachidonic acid 6Reference 6RCTToward optimizing vision and cognition in term infants by dietary DHA and arachidonic acid supplementation: a review of randomised controlled trialsView study →.
Gap: benefit appears real mainly where intake would otherwise be low — preterm infants, low-DHA diets. In term, adequately-fed infants the effect on lasting cognition is small and inconsistent.
A meta-analysis of RCTs in youths with ADHD found omega-3 supplementation modestly improved clinical symptom scores (7 RCTs, n=534; Hedges’ g=0.38, p<0.0001) and attention-related cognition (3 RCTs; g=1.09), with affected children showing lower omega-3 blood levels 7Reference 7Meta-analysisOmega-3 polyunsaturated fatty acids in youths with attention deficit hyperactivity disorder: a systematic review and meta-analysisView study →. A 2026 meta-analysis indicates the response is larger in children with low baseline omega-3 status — so the effect is partly a repletion effect 8Reference 8Meta-analysisBaseline omega-3 nutritional status and supplementation response in pediatric attention-deficit disorder — systematic review and meta-analysis. https://pubmed.ncbi.nlm.nih.gov/42433395/View study →.
Gap: the symptom effect is small and well below stimulant efficacy; benefit is concentrated in deficient children, the evidence base is only about seven RCTs, and DHA is usually given with EPA.
Where omega-3s help mood, the active component is predominantly EPA, not DHA; DHA-predominant formulations perform poorly. A Cochrane review of omega-3 supplementation for depression in children and adolescents rated the evidence very uncertain, with no clear benefit demonstrated 13Reference 13Systematic reviewOmega-3 fatty acid supplementation for depression in children and adolescents — Cochrane systematic reviewView study →.
Gap: DHA-specific antidepressant evidence is thin and largely negative; higher-EPA formulas are what the mood literature supports, so DHA-dominant products should not be sold as antidepressants.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Neuronal and retinal membrane phospholipids | Structural incorporation; supports membrane fluidity, synaptic and photoreceptor function | Infant and fetal developmentvisioncognition |
| Hepatic lipogenesis / VLDL secretion | ↓ triglyceride synthesis and secretion | Triglyceride reduction |
| LDL receptor / lipoprotein metabolism | ↑ LDL cholesterol — DHA-specific, unlike EPA | The lipid trade-off |
| Specialised pro-resolving mediators (resolvins, protectins) | ↑ resolution of inflammation | Proposed for moodeye and neuroinflammation (mostly preclinical) |
| Eicosanoid substrate competition (against arachidonic acid) | ↓ pro-inflammatory eicosanoids; mild antiplatelet effect | The bleeding-risk caveatanti-inflammatory claims |
Pharmacokinetics
DHA absorption is form-dependent. Natural triglyceride and re-esterified triglyceride forms, and phospholipid-bound DHA such as krill, are absorbed more efficiently than ethyl-ester forms — and absorption of ethyl esters in particular is markedly improved when taken with a fat-containing meal, a practical reason to dose with food. Algal-oil DHA (vegan) is bioequivalent to fish-derived DHA.
Once absorbed, DHA is incorporated into cell-membrane phospholipids throughout the body. Tissue and erythrocyte DHA turn over slowly, so the functionally relevant “half-life” is on the order of weeks, and steady-state membrane enrichment — the Omega-3 Index — takes weeks to months of consistent intake to reach, and as long to wash out. This slow tissue kinetics, not plasma levels, is what matters for the structural and developmental effects.
Clinical trials
DHA and omega-3s have an unusually large registered and completed trial base for a supplement, spanning pregnancy, cardiometabolic, ophthalmic, psychiatric and cognitive indications. Because DHA is off-patent and cheap, much of the highest-quality work — Cochrane reviews, publicly funded trials like DREAM and AREDS2 — is publicly rather than industry funded, which is part of why several null results reached publication.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| Hundreds | Dozens | Several | Extensive |
Last checked: August 2026.
Dietary Sources
DHA is a conditionally essential fatty acid: the body can make small amounts from the plant omega-3 alpha-linolenic acid (ALA), but conversion is very inefficient — typically well under 1% reaches DHA — so preformed DHA in the diet is the practical source. It comes almost entirely from marine foods and the algae at the base of the marine food chain.
| Source | Approx. DHA per serving | Notes |
|---|---|---|
| Salmon (farmed or wild), cooked (100 g) | ~1.0–1.4 g | Among the richest common sources |
| Mackerel, herring, sardines, anchovies (100 g) | ~0.7–1.5 g | Small oily fish; also low in mercury |
| Algal oil (vegan DHA) | 100–400+ mg per dose | Directly from microalgae — the original source of fish DHA |
| Tuna, canned light (100 g) | ~0.1–0.2 g | Albacore is higher but carries more mercury |
| Fish oil supplement (1 g capsule) | ~0.1–0.3 g | Varies widely — read the DHA line, not the “fish oil” total |
| Eggs (DHA-enriched) | ~50–150 mg each | Standard eggs contain far less |
| Plant foods (flax, chia, walnuts) | 0 mg preformed DHA | Provide ALA only; poor precursor conversion |
Purely plant-based diets provide essentially no preformed DHA — the main reason algal-oil supplements exist. Absorption improves when taken with a fatty meal, and re-esterified triglyceride or phospholipid forms are absorbed somewhat better than ethyl esters.
Per-serving figures are approximate and vary by species, season and preparation.
Intake & Dosage
These are doses studied in research, not a personal recommendation.
- No formal RDA for DHA. The Adequate Intake for total omega-3 is set as ALA (1.6 g/day for men, 1.1 g/day for women); most authorities additionally suggest roughly 250–500 mg/day combined EPA+DHA for general adult health, achievable with about two servings of oily fish per week.
- Pregnancy and lactation: commonly advised to add ~200 mg/day DHA on top of general intake. The preterm-birth trials used this range and higher 1Reference 1Systematic reviewOmega-3 fatty acid addition during pregnancy — Cochrane systematic reviewView study →.
- Triglyceride lowering: requires gram-level doses, often 2–4 g/day total EPA+DHA, typically as a combination product or prescription omega-3.
- Cognition and mood trials: commonly 900 mg–2 g/day DHA 9Reference 9RCTBeneficial effects of docosahexaenoic acid on cognition in age-related cognitive decline (MIDAS) — randomized controlled trialView study →.
- Read the label carefully. Dose the DHA number on the panel, not the total “fish oil,” and take it with food to aid absorption.
- No Upper Limit has been established — EFSA found the data insufficient, while regarding combined EPA+DHA up to about 5 g/day as not raising safety concerns in healthy adults 14Reference 14Scientific opinion on the tolerable upper intake level of EPA, DHA and DPAView study →. Absence of a UL does not mean unlimited intake is safe.
Safety
DHA is one of the better-tolerated supplements. The most common complaints are minor gastrointestinal effects — fishy aftertaste or burping, mild nausea, loose stools — which are dose-related and reduced by taking it with meals or using enteric-coated or algal products.
- Well tolerated. The common complaints are minor and gastrointestinal, and are reduced by taking it with food.
- Net benefit in pregnancy at typical prenatal doses — one of the few supplements with high-quality RCT support in this population 1Reference 1Systematic reviewOmega-3 fatty acid addition during pregnancy — Cochrane systematic reviewView study →.
- Bleeding risk at gram-level doses. Omega-3s have a mild antiplatelet effect and can modestly prolong bleeding time. Coordinate with a clinician on anticoagulants or antiplatelets, and pause high doses before surgery.
- DHA raises LDL cholesterol by roughly 3–7 mg/dL — a property EPA lacks, and relevant if you are supplementing for lipids 3Reference 3Meta-analysisEffects of eicosapentaenoic acid versus docosahexaenoic acid on serum lipids: a systematic review and meta-analysisView study →.
- No upper limit is set. EFSA regards combined EPA+DHA up to ~5 g/day as not raising concerns in healthy adults, but that is not a UL 14Reference 14Scientific opinion on the tolerable upper intake level of EPA, DHA and DPAView study →.
Full Safety & Interactions Detail
The dose-limiting effect is bleeding. At gram-level doses DHA and other omega-3s have a mild antiplatelet effect and can modestly prolong bleeding time. EFSA concluded that combined EPA+DHA up to about 5 g/day does not meaningfully increase spontaneous bleeding in healthy people 14Reference 14Scientific opinion on the tolerable upper intake level of EPA, DHA and DPAView study →, but caution is warranted at higher doses.
- LDL cholesterol: DHA specifically raises LDL by roughly 3–7 mg/dL, a property EPA lacks 3Reference 3Meta-analysisEffects of eicosapentaenoic acid versus docosahexaenoic acid on serum lipids: a systematic review and meta-analysisView study → — directly relevant for anyone supplementing for lipid reasons.
- Interactions: anticoagulants and antiplatelets — warfarin, DOACs, aspirin, clopidogrel — carry an additive bleeding risk. Coordinate timing and dose with a clinician, and pause high doses before surgery. No clinically significant CYP450 interactions are established.
- Who should be cautious: people on blood thinners, with bleeding disorders, or scheduled for surgery.
Scope disclosure. Interactions were assessed: the anticoagulant and antiplatelet class was reviewed for bleeding risk, and no significant CYP450 interactions were identified. Pregnancy and lactation were assessed, with net benefit at prenatal doses. No Upper Limit has been set — EFSA found the data insufficient for DHA or combined n-3 LCPUFA, while regarding up to ~5 g/day as not raising safety concerns in healthy adults 14Reference 14Scientific opinion on the tolerable upper intake level of EPA, DHA and DPAView study →. Absence of a UL does not mean unlimited intake is safe.
Beneficial and safe at typical prenatal doses. DHA is one of the few supplements with high-quality randomised evidence of benefit in pregnancy — the Cochrane review of 70 RCTs found reduced preterm and early preterm birth 1Reference 1Systematic reviewOmega-3 fatty acid addition during pregnancy — Cochrane systematic reviewView study →. Roughly 200 mg/day added to general intake is the commonly advised amount. Very high neonatal doses have not shown added long-term benefit 15Reference 15RCTMaternal high-dose docosahexaenoic acid supplementation and neurodevelopment at 5 years in preterm children — randomized controlled trial follow-up. https://pubmed.ncbi.nlm.nih.gov/39396702/View study →. Use a low-mercury source and coordinate the dose with prenatal care.
References
- Middleton P, Gomersall JC, Gould JF, Shepherd E, Olsen SF, Makrides M (2018). Omega-3 fatty acid addition during pregnancy — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/30480773/
- Brenna JT, Carlson SE (2014). Docosahexaenoic acid and human brain development: evidence that a dietary supply is needed for optimal development — review. Journal of Human Evolution. https://pubmed.ncbi.nlm.nih.gov/24780861/
- Wei MY, Jacobson TA (2011). Effects of eicosapentaenoic acid versus docosahexaenoic acid on serum lipids: a systematic review and meta-analysis. Current Atherosclerosis Reports. https://pubmed.ncbi.nlm.nih.gov/21975919/
- Zhang HJ, Gao X, et al. (2021). Effects of dietary eicosapentaenoic acid and docosahexaenoic acid supplementation on metabolic syndrome: a systematic review and meta-analysis of 33 randomized controlled trials. Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/34229258/
- Jasani B, Simmer K, Patole SK, Rao SC (2017). Long chain polyunsaturated fatty acid supplementation in infants born at term — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/28281303/
- Hoffman DR, Boettcher JA, Diersen-Schade DA (2009). Toward optimizing vision and cognition in term infants by dietary DHA and arachidonic acid supplementation: a review of randomised controlled trials. Prostaglandins, Leukotrienes and Essential Fatty Acids. https://pubmed.ncbi.nlm.nih.gov/19505812/
- Chang JP, Su KP, Mondelli V, Pariante CM (2018). Omega-3 polyunsaturated fatty acids in youths with attention deficit hyperactivity disorder: a systematic review and meta-analysis. Neuropsychopharmacology. https://pubmed.ncbi.nlm.nih.gov/28741625/
- Fu X, Feng L, Jiang M, et al. (2026). Baseline omega-3 nutritional status and supplementation response in pediatric attention-deficit disorder — systematic review and meta-analysis. https://pubmed.ncbi.nlm.nih.gov/42433395/
- Yurko-Mauro K, et al. (2010). Beneficial effects of docosahexaenoic acid on cognition in age-related cognitive decline (MIDAS) — randomized controlled trial. Alzheimer’s & Dementia. https://pubmed.ncbi.nlm.nih.gov/20434961/
- Quinn JF, et al. (2010). Docosahexaenoic acid supplementation and cognitive decline in Alzheimer disease — randomized trial. JAMA. https://pubmed.ncbi.nlm.nih.gov/21045096/
- Dry Eye Assessment and Management (DREAM) Research Group (2018). n-3 fatty acid supplementation for the treatment of dry eye disease — multicenter randomized controlled trial. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/29652551/
- Age-Related Eye Disease Study 2 (AREDS2) Research Group (2013). Lutein + zeaxanthin and omega-3 fatty acids for age-related macular degeneration — randomized clinical trial. JAMA. https://pubmed.ncbi.nlm.nih.gov/23644932/
- Campisi SC, Zasowski C, Bradley-Ridout G, et al. (2024). Omega-3 fatty acid supplementation for depression in children and adolescents — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/39564892/
- EFSA Panel on Dietetic Products, Nutrition and Allergies (2012). Scientific opinion on the tolerable upper intake level of EPA, DHA and DPA. EFSA Journal. https://pubmed.ncbi.nlm.nih.gov/42016086/
- Paquet SP, Pronovost E, Simonyan D, et al. (2024). Maternal high-dose docosahexaenoic acid supplementation and neurodevelopment at 5 years in preterm children — randomized controlled trial follow-up. https://pubmed.ncbi.nlm.nih.gov/39396702/



