
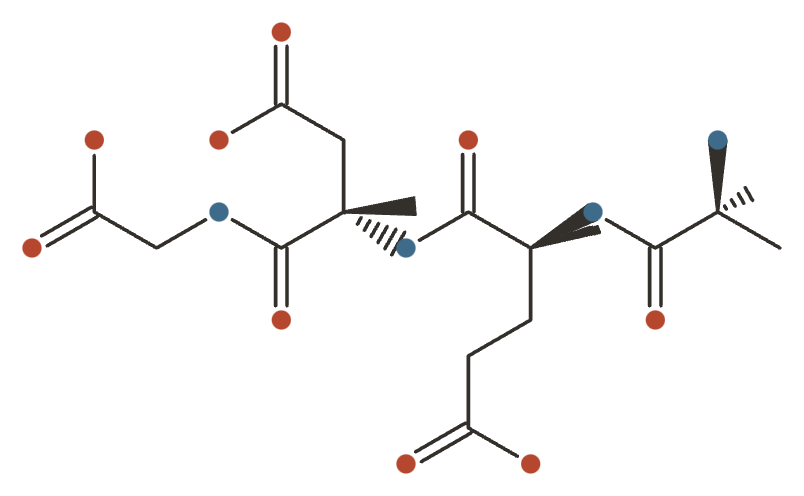
Epitalon
A synthetic pineal tetrapeptide marketed as an anti-aging / telomerase-activating injectable.

Epitalon at a Glance
Epitalon is a synthetic tetrapeptide based on a fraction of epithalamin, a pineal gland extract developed in the Soviet Union as an anti-ageing agent. It is marketed as a telomerase activator and injected in short courses for longevity. Its evidence base is unusual and worth understanding: it traces almost entirely to one research group in St Petersburg over several decades, with very little independent replication outside that network. It is unapproved everywhere.
History & Development
Epitalon comes from a Soviet anti-ageing programme built on the pineal gland, and almost its entire evidence base traces to a single research group.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | One research group in St Petersburg, over several decades |
| Origin | Synthetic tetrapeptide based on a fraction of epithalamin, a pineal gland extract |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Never approved anywhere; sold as a research chemical |
Discovery
The pineal gland’s association with ageing - through melatonin and circadian decline - made it a natural target for Soviet gerontology. Epithalamin was a crude pineal extract developed as an anti-ageing agent; epitalon is a synthetic tetrapeptide based on one fraction of it, the attempt to identify and reproduce the active component of a tissue extract.
That lineage puts it in the same tradition as thymalin - both are Soviet-era “bioregulator” preparations derived from glandular tissue, one from pineal and one from thymus.
Its headline claim is telomerase activation, which is what a compound needs in order to be marketed as genuinely anti-ageing rather than merely restorative.
Development & ownership
The provenance is the most important thing here. Epitalon’s research record traces almost entirely to one research group in St Petersburg, accumulated over several decades, with very little independent replication.
That does not make the findings wrong. It does mean the usual safeguard - independent groups reproducing a result with different methods, animals and assumptions - has largely not operated here, and for a claim as consequential as telomerase activation and lifespan extension, that safeguard is what the claim would need.
How it reached the market
Epitalon has never been approved by any regulator, anywhere. It is sold as an injectable research chemical for anti-ageing and telomere support - claims resting on a single-group literature, with no Western clinical trial and no established human dose.
What It's Used For
Epitalon (also spelled Epithalon or Epithalone; the “AEDG peptide”) is a synthetic tetrapeptide, Ala-Glu-Asp-Gly, designed by Vladimir Khavinson’s group in St. Petersburg from the amino-acid composition of epithalamin — a peptide extract of the bovine (calf) pineal gland — and later reported to occur within the natural pineal polypeptide complex. The honest headline is that the evidence base is preclinical and single-group dominated: the great majority of studies come from the Khavinson/Anisimov collaboration, are published in Russian-language or Russian in-house journals (Bulletin of Experimental Biology and Medicine, Advances in Gerontology), and use cell culture, invertebrates, and rodents. The one finding the internet repeats endlessly — that epitalon “activates telomerase and lengthens telomeres” — is an in-vitro result in cultured human fibroblasts (2003), and although a 2025 independent lab reproduced telomere lengthening in human cell lines, there is no in-vivo human telomere or lifespan data for the peptide at all 6,
Critically, the widely cited human “longevity / lower-mortality” studies in elderly patients used epithalamin, the injectable pineal extract — not the pure synthetic tetrapeptide; the two are routinely conflated in marketing but are not the same product 21,
The FDA has now stated this distinction in its own words — reviewing epitalon in 2026 it wrote that it “considers epitalon and epithalamin as different substances,” and found that of the articles the nominators filed in support of an epitalon nomination, seven were studies of epithalamin (see Sourcing, Route & Legal Status). Human studies of the peptide itself do exist but are very few — three, per FDA’s search, none of them addressing telomeres, lifespan or safety. Epitalon is an unapproved research chemical sold by unregulated vendors as a lyophilized powder for subcutaneous reconstitution, and there are zero registered clinical trials for it on ClinicalTrials.gov.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. For epitalon the ceiling is deliberately low — nothing here clears 35%, because every application rests on single-group animal or in-vitro data with no registered human trial of the peptide, and the human gap is stated out loud in each row. Each application links down to its write-up.
The strongest single-application signal, and it is entirely animal. In the Anisimov program, subcutaneous epitalon (typically 0.1 µg/animal, 5×/week) extended maximum lifespan and slowed the population aging rate in female rats and in several mouse strains (CBA, HER-2/neu transgenic, senescence-accelerated SAM), and suppressed the development of spontaneous tumors — with the effect strongest under disruptive lighting (constant or natural-Arctic light) and near-absent in animals already on a standard 12-hour light regimen 1,
A single larval dose altered lipid-peroxidation trajectories across the Drosophila lifespan, and the peptide extended fly lifespan 4,
Effects are dose- and condition-dependent and, tellingly, largest when the circadian system is stressed — consistent with a melatonin-axis mechanism rather than a general “youth” effect.
Gap: No human lifespan or healthspan trial of the peptide exists. All in-vivo lifespan data are from one research group; the human “lower-mortality” studies people cite used epithalamin extract, not epitalon (see application 2). Independent Western in-vivo replication is essentially absent.
Epitalon was built to mimic the pineal extract, and its most reproducible physiological action is on the melatonin / circadian axis. In aged (20–27 yr) rhesus monkeys, epitalon raised the depressed night-time melatonin peak and normalized glucose/insulin dynamics, with no effect in young animals — i.e. it corrected an age-related deficit rather than pushing a normal system 8Reference 8Pineal peptides restore the age-related disturbances in hormonal functions of the pineal gland and the pancreas (rhesus monkey) — animalView study →.
In elderly humans, course treatment with epithalamin (the extract) modulated the melatonin rhythm — raising nocturnal melatonin in subjects whose pineal output was low — and restored the circadian coupling between pineal and thymic endocrine function 9,
These small human studies test the extract, are single-group, and are not blinded RCTs.
There is, however, one small placebo-controlled human study of the peptide itself, surfaced by FDA’s 2026 review: Ivko et al. (2021) gave 40 women aged 40–50 working night shifts, all with low melatonin output, either placebo or sublingual AEDG spray at 0.5 mg/day for 20 days. Urinary 6-sulfatoxymelatonin (a melatonin metabolite) rose 1.7-fold in the peptide arm and did not move on placebo. FDA’s own read of it is deflationary and worth carrying: the study did not measure any sleep outcome, blinding was not specified, it was short and small, and it used the sublingual route rather than the subcutaneous one people actually inject. A companion paper (Khavinson 2021) reported clock-gene expression changes in the same setting. Both are Khavinson-group publications.
Cutting the other way, an independent in-vitro test failed to reproduce the mechanism: Djeridane et al. (2003), with the French chronobiologist Touitou, superfused pineal glands from young and old rats with epitalon at 1, 10 and 100 µM and saw no increase in melatonin release — i.e. the peptide may not act directly on the pineal at all. FDA states plainly that “the mechanisms by which epitalon regulates serum levels of melatonin in vivo remain unknown.”
Gap: The strong human melatonin/circadian data are for epithalamin extract, not the synthetic tetrapeptide. The one placebo-controlled peptide study is small, short, unblinded-as-reported, by the originating group, uses a different route, and measured a metabolite rather than sleep. No modern controlled trial of the peptide for any clinical endpoint.
Across the same rodent program, epitalon reduced the incidence of malignant tumors and prevented metastasis. In female C3H/He mice, 6.5 months of low-dose epitalon (0.1 µg, 5×/week) decreased the number of mice bearing malignant tumors and blocked metastasis from spontaneous reproductive-organ tumors, with no observed toxicity 11Reference 11AnimalEffect of the synthetic pineal peptide epitalon on spontaneous carcinogenesis in female C3H/He mice — animalView study →.
In rats under disruptive lighting, the peptide significantly slowed spontaneous tumor development 3Reference 3AnimalGeroprotective effect of Ala-Glu-Asp-Gly peptide in male rats exposed to different illumination regimens — animalView study →.
The proposed mechanism links back to melatonin restoration and antioxidant defense rather than direct cytotoxicity.
Gap: Spontaneous-carcinogenesis models in one lab; no human oncology data. This is an anti-promotion / prevention signal in rodents, not a cancer-treatment claim — and note that epitalon’s telomerase action cuts the other way (application 4).
The internet-famous claim, and the one with a genuine independent replication — though still only in cell culture. The 2003 origin study added epithalon to telomerase-negative human fetal fibroblasts and reported induction of the telomerase catalytic subunit (hTERT), telomerase enzyme activity, and telomere elongation 6Reference 6In vitroEpithalon peptide induces telomerase activity and telomere elongation in human somatic cells — in vitroView study →.
In 2025 an independent group reproduced dose-dependent telomere lengthening in normal human epithelial/fibroblast cells (via hTERT/telomerase up-regulation) and in breast-cancer lines (via the alternative-lengthening-of-telomeres, ALT, pathway) 7Reference 7In vitroEpitalon increases telomere length in human cell lines through telomerase up-regulation or ALT activity — in vitroView study →.
A separate 2025 study reported that epitalon-activated telomerase enhanced bovine oocyte maturation and post-thaw embryo development in vitro 26Reference 26In vitroEpitalon-activated telomerase enhances bovine oocyte maturation rate and post-thawed embryo development — in vitro / animalView study →.
The proposed mechanism is that the peptide binds histone/promoter regions and epigenetically de-represses telomerase and other genes 12Reference 12In vitroAEDG peptide (Epitalon) stimulates gene expression and protein synthesis during neurogenesis: possible epigenetic mechanism — in vitroView study →.
Gap: In-vitro only. No study has measured telomere length or telomerase activity in a living human given epitalon. Re-activating telomerase — including the ALT pathway in cancer cells, as the 2025 paper showed — is not self-evidently benign; the oncology framing cuts both ways.
Epitalon originates partly from a Soviet ophthalmology lineage (paired with the retinal extract “retinalamin”). In Campbell rats — a hereditary retinal-degeneration model — epitalon given during development preserved retinal structure and function roughly twice as long as in controls 13Reference 13AnimalRetinoprotective effect of Epithalon in Campbell rats of various ages — animalView study →.
In vitro, AEDG stimulates differentiation of retinal and pigment-epithelial cells 14Reference 14In vitroPeptidergic regulation of differentiation of embryonic retinal cells — in vitroView study →, and a 2025 study found it improved wound healing and suppressed EMT/fibrosis in high-glucose-injured human ARPE-19 retinal cells (a diabetic-retinopathy model) 15Reference 15In vitroThe antioxidant tetrapeptide Epitalon enhances delayed wound healing in an in-vitro model of diabetic retinopathy — in vitroView study →.
Older Russian clinical reports combined epithalamin with other bioregulators for diabetic retinopathy, so they cannot isolate epitalon’s contribution.
Gap: Rat degeneration model plus in-vitro human retinal cells; no controlled human trial of the peptide for retinitis pigmentosa or diabetic retinopathy. The human ophthalmology reports use the extract in combination therapy.
A recurring proposed mechanism underlying the geroprotective claims. In aged rats, epitalon (and the epithalamin extract) raised total antioxidant/antiradical activity and induced antioxidant enzymes (SOD, glutathione peroxidase, glutathione-S-transferase) in serum, liver and brain, with effects in some assays exceeding melatonin itself 16Reference 16Antioxidant properties of geroprotective peptides of the pineal gland — animalView study →.
In Drosophila subcellular fractions the peptide modulated reactive-oxygen-species generation and lipid peroxidation 4,
Gap: Aged-rodent and invertebrate biochemistry from one group; this is mechanistic support for the geroprotection story, not an independent clinical endpoint, and there is no human antioxidant-outcome study.
A more recent in-vitro theme. AEDG promotes neuronal differentiation and up-regulates neurogenic markers (Nestin, GAP43, β-tubulin III, doublecortin) in human gingival/periodontal stem cells, proposed to work by binding histones H1/3 and H1/6 to de-repress differentiation genes 12Reference 12In vitroAEDG peptide (Epitalon) stimulates gene expression and protein synthesis during neurogenesis: possible epigenetic mechanism — in vitroView study →.
In aged human oral stem cells it lowered senescence markers p16/p21 17Reference 17In vitroShort peptides protect oral stem cells from ageing — in vitroView study →, and in fibroblast-derived induced neurons from elderly donors it promoted dendrite outgrowth 18Reference 18In vitroShort peptides protect fibroblast-derived induced neurons from age-related changes — in vitroView study →.
Intranasal epitalon (30 ng) acutely increased spontaneous neuron firing in rat neocortex, offered as a non-invasive CNS-delivery proof of concept 19Reference 19AnimalEffects of intranasal administration of epitalon on neuron activity in the rat neocortex — animalView study →.
Gap: In-vitro human cells and acute rat electrophysiology; no cognitive or neurological human study. The intranasal-delivery data are a single acute-firing experiment, not an efficacy result.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Pineal melatonin synthesis | ↑ (restores blunted night-time peak in aged animals/humans) | anti-agingcircadianoncostatic |
| hTERT / telomerase | ↑ (in-vitro human cells); ALT pathway ↑ in cancer lines | telomere lengtheninganti-aging |
| Histone H1/3, H1/6 binding → gene promoters | epigenetic de-repression (telomerase, neurogenic, retinal genes) | telomeraseneurogenesisretinoprotection |
| Antioxidant enzymes (SOD, GPx, GST) | ↑ expression + direct radical scavenging | antioxidantgeroprotection |
| Senescence markers p16 / p21 | ↓ (in-vitro human stem cells) | anti-agingneuroprotection |
| Immune / thymic endocrine function | modulation (restores circadian coupling) | anti-agingimmune |
Pharmacokinetics
Formal human pharmacokinetics are unpublished — FDA’s 2026 review states flatly that “no pharmacokinetic data were found” for either epitalon free base or epitalon acetate, and identified no toxicokinetic study in any species either. Epitalon is a small (≈390 Da) linear tetrapeptide with no oral bioavailability worth counting on — like other short peptides it is expected to be rapidly degraded by peptidases in the gut and plasma, which is why it is supplied as a powder for subcutaneous (or intramuscular) injection after reconstitution. Its half-life is presumed short (minutes, by analogy to comparable peptides — not directly measured), which underlies the vendor practice of daily dosing in short “courses.” Two non-injectable routes appear only in the research literature: intranasal delivery was used to reach the CNS in rats (bypassing the blood–brain barrier) 19Reference 19AnimalEffects of intranasal administration of epitalon on neuron activity in the rat neocortex — animalView study →, and 2025 work proposed ophthalmic formulations for retinal delivery 15Reference 15In vitroThe antioxidant tetrapeptide Epitalon enhances delayed wound healing in an in-vitro model of diabetic retinopathy — in vitroView study → — neither is a validated human product. The proposed mechanism (direct nuclear entry, histone/DNA binding) implies the intact peptide reaches the nucleus in cultured cells, but whether meaningful intact peptide survives to reach target tissues after injection in a human has not been demonstrated.
Clinical & regulatory status
Epitalon is an unapproved research chemical. It is not approved as a drug or dietary supplement by the FDA, EMA, TGA or any comparable regulator, and it is sold “for research use only / not for human consumption” by gray-market peptide vendors. A 2015 forensic-chemistry paper documented epitalon being found in illegal pharmaceutical preparations marketed for cancer, aging and retinitis pigmentosa, underscoring its status as an unregulated, sometimes-counterfeit product 20Reference 20Identification of the small research tetrapeptide Epitalon in two illegal pharmaceutical preparations — forensic analysisView study →. There are no registered clinical trials for epitalon on ClinicalTrials.gov (searches for epitalon / epithalon / epithalamin / AEDG return zero studies). FDA’s 2026 review found only three published studies in which epitalon was given to humans — two sublingual studies in night-shift workers measuring melatonin metabolites and clock-gene expression, and one parabulbar injection study in congenital retinitis pigmentosa (Khavinson 2002) — and none assessing safety. The much larger and more-cited human literature is for epithalamin, the injectable bovine-pineal extract — including single-group Russian studies reporting reduced mortality over 12–15-year follow-up in elderly patients 21,
Two regulatory facts are worth stating precisely. Epitalon received an FDA orphan-drug designation for retinitis pigmentosa on 2 September 2010, which was withdrawn/revoked on 6 January 2016; an orphan designation is a development incentive, not an approval, and it no longer stands. And in 2026 FDA formally evaluated epitalon for the section 503A compounding bulks list and proposed not to add it — the detail is in Sourcing, Route & Legal Status below. Modern interest is largely secondary: epitalon appears in 2025–2026 narrative reviews of therapeutic peptides in aging and orthopedics, always flagged as preclinical with a clinical-trial gap 23,
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 0registered. Three small published human studies of the peptide exist (2 sublingual, 1 parabulbar), none assessing safety; the mortality/longevity studies are for the extract (epithalamin) 21, | 0registered | 0 | ~200+records (mostly single-group, animal/in-vitro, 2000–2026) |
Last checked: 18 July 2026.
Sourcing, Route & Legal Status
Regulatory status — unapproved research chemical. Epitalon has never been approved as a drug or authorized as a dietary supplement by the FDA, EMA, TGA, PMDA or any comparable regulator, and it holds no marketing authorization anywhere for any indication. It is sold “for research use only” / “not for human consumption” by gray-market peptide vendors. It is not a controlled/scheduled substance, but its sale for human use is unlawful in most jurisdictions precisely because it is unapproved — a 2015 forensic-toxicology study documented epitalon turning up in illegal pharmaceutical preparations advertised for cancer, old age and retinitis pigmentosa 20Reference 20Identification of the small research tetrapeptide Epitalon in two illegal pharmaceutical preparations — forensic analysisView study →. Note the frequent conflation with epithalamin (or “epithalamine”), the injectable bovine-pineal extract used in older Russian clinical studies and once produced as a pharmacy preparation there; the pure synthetic tetrapeptide sold online today is not that product and carries none of its (already limited, single-group) human record 21,
FDA’s 2026 evaluation — the most thorough regulatory read of epitalon that exists (decision pending). FDA’s briefing document for the 23–24 July 2026 Pharmacy Compounding Advisory Committee meeting, signed 12 May 2026, evaluates epitalon (free base) and epitalon acetate for the section 503A Bulks List — the list of substances licensed pharmacies may legally compound with. Its conclusion, published ahead of the meeting, is that “a balancing of the criteria weighs against” listing either substance, and that FDA “propose[s] not adding epitalon (free base) or epitalon acetate to the 503A Bulks List.” The committee has not yet voted, and FDA states it will not issue a final determination until the advisory-committee process concludes and all reviews are finalized. Treat what follows as the Agency’s published evaluation, not a settled outcome. Two nominations — from Wells Pharmacy Network and from LDT Health Solutions on behalf of the International Peptide Society, proposing 10 mg/mL and 3,000 µg/mL subcutaneous injections — were withdrawn; FDA chose to evaluate the substances anyway on its own initiative.
FDA independently makes the same central distinction. In a footnote the Agency writes that although the nominators offered “epithalamin(e)” as another name for epitalon, “FDA considers epitalon and epithalamin as different substances” — epithalamin being a polypeptide complex extracted from cattle pineal gland, epitalon a tetrapeptide synthesized from the study of its amino-acid content. It then documents the substitution directly: of the 23 usable articles the nominators submitted, “[n]one of the articles submitted discussed the use of epitalon,” and seven of them “discussed the use of epithalamin; however, we note that epitalon and epithalamin are different substances.” The nominators’ own attached monograph illustrates the problem exactly — it is titled Epithalon, calls the peptide “the synthetic version of the tetrapeptide epithalamin,” and offers as evidence the 12-year study showing “a 28% decrease in overall mortality with those treated with epithalamin.” A regulator that ran the systematic search reached the same conclusion: the famous mortality data belongs to the extract.
What FDA found to be absent. No pharmacokinetic data of any kind, in humans or animals (only an uninterpretable 2005 fluorescent-label study in pregnant rabbits). No acute toxicity study. No repeat-dose toxicity study. No developmental or reproductive toxicity study. No 2-year carcinogenicity study. No clinical study assessing the safety of epitalon in humans, by any route. No study of immunogenicity or aggregation. Searching FAERS through 8 December 2025 retrieved no adverse-event reports, and the Human Foods Complaint System through 5 December 2025 retrieved no cases — an empty file for a barely-surveilled compound, which is an absence of data, not evidence of safety. No outsourcing facility has ever reported compounding epitalon to FDA, and a Google search identified no pharmacy that compounds it; the only documented compounding is a Nicholasville, Kentucky pharmacy that compounded and distributed epitalon products from 25 October 2018 to 1 April 2020 and whose owner pleaded guilty to unlawful distribution.
Recognition and quality. There is no USP or NF monograph for either form, and epitalon is recognized in neither the European (11.8) nor the Japanese (18th) Pharmacopoeia. There are no approved epitalon products in Canada, Australia, the UK, Belgium, Ireland, France, Norway, Germany, Spain or Italy, and no EMA authorization. (One nominator asserted recognition in the Russian Pharmacopoeia; FDA’s evaluation does not corroborate it.) FDA judged both forms “not well-characterized” physically and chemically, citing naming conventions that follow no recognized standard (epitalon is a common name, not a USAN or INN) and missing critical quality data. The nomination paperwork demonstrates the hazard: the certificates of analysis named one substance in the title and a different one by molecular weight, and the two forms carry distinct CAS numbers (free base 307297-39-8, acetate 307297-40-1) that were used inconsistently. No CoA carried bioburden or bacterial-endotoxin testing — for an injectable, FDA calls endotoxin a critical quality attribute — and none characterized individual impurities, which may run to 1% each. FDA could not rule out immunogenicity from aggregation and peptide impurities, noting the subcutaneous route carries the highest immunogenicity risk of the parenteral routes. It also notes epitalon’s limited water solubility may make a 3 mg/mL aqueous injection impossible to compound as proposed.
On efficacy, and on the carcinogenicity question. FDA evaluated epitalon only for insomnia — the anti-aging, longevity, telomere-lengthening, dementia-prevention, skin, muscle-healing and stress-resilience uses were all proposed by the nominators but FDA declined to evaluate them because the nominations “did not include sufficient information.” On insomnia it found a “lack of evidence to support the effectiveness” of either form, noting no study has evaluated epitalon in insomnia patients at all and that “the potential therapeutic effect of changes in melatonin levels induced by these substances is unclear without a corresponding evaluation of clinical outcomes.” Most consequentially for anyone taking this compound, FDA turns epitalon’s own selling point into its safety concern: “epitalon has the potential to be carcinogenic. Specifically, epitalon has been shown to activate telomerase and lengthen telomeres, and longer telomeres are generally associated with increased risk for cancer.” It adds that while intermittent dosing suppressed tumors in the Russian mouse studies, continuous lifelong exposure “could enable cells to evade senescence and become cancerous” — and observes that the rodent studies exposed animals for at most ~5.5 months, far too short to detect carcinogenicity.
A data-integrity note. FDA flags that the Khavinson group appears to have reused the chromosome-aberration data from four saline-treated mice as historical control data across studies of different peptides — the same control figures appear in a study of a different compound entirely — with no analysis validating the practice, and warns the results “should be interpreted with caution.”
How it’s supplied & administered. Epitalon is supplied as a lyophilized (freeze-dried) white powder, typically in 10–100 mg vials, requiring reconstitution with bacteriostatic or sterile water before use. Because it is a small linear peptide with negligible oral bioavailability, it is administered by subcutaneous or intramuscular injection; vendors and community protocols run it in short daily “courses” rather than continuously. Reconstituted peptide must be refrigerated and is chemically less stable than the dry powder. Two non-injectable routes appear only in the research literature (intranasal in rats; proposed ophthalmic drops for retinal delivery) and are not commercial human products.
Sourcing reality (this is a safety issue, not a footnote). Every gram of epitalon in human hands comes from an unregulated supply chain with no manufacturing oversight, no pharmacopoeial standard, and no regulatory accountability. Documented, real risks include: mislabeled or under-/over-dosed vials; peptide degradation or wrong sequence; bacterial endotoxin and sterility failures (directly dangerous for an injected product); heavy-metal or solvent residues; and outright counterfeits (as the forensic literature confirms) 20Reference 20Identification of the small research tetrapeptide Epitalon in two illegal pharmaceutical preparations — forensic analysisView study →. A genuine third-party certificate of analysis (COA) — identity by mass spec/HPLC, purity, and endotoxin testing — is the minimum a buyer would need to have any idea what is in the vial, and most vendors do not provide independently verifiable ones. For an injectable sold outside any regulatory system, sourcing is the primary safety exposure. This page does not recommend, rank, or link any vendor; purity and identity are unverifiable in this market.
Safety
Formal human safety data for epitalon do not exist — FDA confirmed in 2026 that there is no clinical safety study, no pharmacokinetics in any species, and no toxicology program at all. Its signature mechanism is also the concern: FDA has stated in writing that epitalon “has the potential to be carcinogenic” because it activates telomerase.
- FDA states it has the potential to be carcinogenic. Telomerase and ALT activation is exactly what many cancers exploit, and continuous lifelong exposure is the specific worry.
- No human safety study of any kind exists. No clinical safety data, no pharmacokinetics, and no acute, repeat-dose, reproductive or carcinogenicity study in any species.
- Never assessed in pregnancy or breastfeeding. The gap is total — see the box below.
- Active or prior malignancy. A specific mechanistic reason for concern, given the telomerase and ALT findings.
- Rodent reassurance does not transfer. The lifespan work used microgram doses; people self-administer milligrams, roughly a 10,000-fold difference.
- Injection and sourcing risks dominate the near term. Injection-site reactions, infection, abscess and endotoxin exposure from unverified product.
Full Safety & Interactions Detail
Overall posture. Formal human safety data for epitalon do not exist — a point now established by a regulator rather than merely asserted here. Reviewing the compound in 2026, FDA found no clinical study assessing epitalon’s safety in humans by any route, no pharmacokinetic data in any species, and no acute, repeat-dose, developmental/reproductive or 2-year carcinogenicity study whatsoever (see Sourcing, Route & Legal Status). There is likewise no pharmacovigilance system and no regulator monitoring adverse events in the gray market. What can be said is drawn from rodent studies and from mechanism/class reasoning, and is labeled as such. Do not read the absence of reported harms in a sparse, single-group, gray-market literature as evidence of safety.
Animal tolerability. In the Khavinson/Anisimov rodent lifespan work, microgram-range subcutaneous doses (e.g. 0.1 µg 5×/week for months) were reported to produce no overt toxicity and, if anything, reduced tumor incidence 11Reference 11AnimalEffect of the synthetic pineal peptide epitalon on spontaneous carcinogenesis in female C3H/He mice — animalView study →. This is reassuring only within that dose range and species — it does not translate to the milligram doses humans self-administer, a roughly 10,000-fold difference.
Mechanism-based theoretical concerns (unstudied in vivo). Epitalon’s signature action is telomerase activation, and the 2025 replication showed it can also switch on the ALT (alternative lengthening of telomeres) pathway in cancer cells 7Reference 7In vitroEpitalon increases telomere length in human cell lines through telomerase up-regulation or ALT activity — in vitroView study →. Re-activating telomere-maintenance machinery is exactly what many cancers exploit; whether chronic telomerase up-regulation across a whole human is net-protective (the anti-aging pitch) or net-risky (pro-tumor) is genuinely unknown and unmeasured in humans. FDA has now put this in writing: its 2026 evaluation states that “epitalon has the potential to be carcinogenic,” precisely because it activates telomerase and lengthens telomeres, and warns that continuous lifelong exposure — as opposed to the intermittent, ~5.5-month dosing used in the rodent tumor studies — “could enable cells to evade senescence and become cancerous.” This ambiguity should temper any “harmless longevity booster” framing.
Injection-specific risks. As an injected, non-sterile-by-default gray-market product, the dominant near-term risks are injection-site reactions, infection, abscess, and reactions to endotoxin/contaminants from poor-quality product — i.e. sourcing risks, not intrinsic pharmacology.
Dose-limiting effect. None established in humans (no dose-finding trial has ever been run).
Interactions. Not assessed — no controlled interaction data exist. The peptide’s mechanistic overlap with the melatonin/circadian axis implies a theoretical (unstudied) interaction with melatonin and other sleep/circadian agents; do not treat this as characterized.
Who should avoid it. Anyone with an active or prior malignancy (telomerase/ALT concern), pregnant or breastfeeding individuals (no data), and anyone unable to verify product identity/sterility — which, given the supply chain, is nearly everyone. The conservative position is that it should not be self-administered outside a supervised clinical trial.
Scope disclosure (what has and hasn’t been assessed):
- Human data? Almost none for the peptide — three small published studies, none assessing safety (FDA, 2026); otherwise preclinical (animal/in-vitro) only. The large human longevity literature is for the epithalamin extract, a different product.
- Interactions assessed? No — no controlled interaction data; only a theoretical melatonin-axis overlap.
- Pregnancy/lactation assessed? No — no data; avoid.
- Long-term safety established? No. There is no long-term human safety data, and the absence of reported harms in a sparse, single-group, gray-market context must not be read as evidence of safety.
Never imply safety from silence. Where epitalon hasn’t been studied in humans — which is everywhere — the honest statement is “not assessed,” not “safe.”
Not assessed / not established. There are no human pregnancy or lactation data for epitalon, and FDA’s 2026 review confirmed it could identify no nonclinical developmental or reproductive toxicity study of either form — so the gap is total rather than merely unexamined here. It should be avoided in pregnancy and breastfeeding on the basis of absent safety data.
Dosage
There is no established human dose for epitalon, and none is recommended here. It has no approved indication and no human trial of the peptide to define a safe or effective dose, so no dose is recommended.
For reference only, the animal literature dosed epitalon in micrograms — commonly 0.1 µg per animal, 5×/week subcutaneously in the rodent lifespan studies 1,
References
- Anisimov VN, Khavinson VKh, et al. (2004). Stressors and antistressors: how do they influence life span in HER-2/neu transgenic mice? — animal. Exp Gerontol. https://pubmed.ncbi.nlm.nih.gov/15501020/
- Anisimov VN, et al. (2005). Effect of epitalon and melatonin on life span and spontaneous carcinogenesis in senescence-accelerated mice (SAM) — animal. Vopr Onkol. https://pubmed.ncbi.nlm.nih.gov/15909815/
- Anisimov VN, Khavinson VKh, et al. (2008). Geroprotective effect of Ala-Glu-Asp-Gly peptide in male rats exposed to different illumination regimens — animal. Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/19110597/
- Khavinson VKh, et al. (2001). Effects of peptides on generation of reactive oxygen species in subcellular fractions of Drosophila melanogaster — animal / in vitro. Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/11687853/
- Khavinson VKh, et al. (2000). Effect of the Ala-Glu-Asp-Gly peptide on lifespan in Drosophila melanogaster — animal. Dokl Biol Sci. https://pubmed.ncbi.nlm.nih.gov/11103316/
- Khavinson VKh, Bondarev IE, Butyugov AA (2003). Epithalon peptide induces telomerase activity and telomere elongation in human somatic cells — in vitro. Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/12937682/
- Al-Dulaimi S, Thomas R, Matta S, et al. (2025). Epitalon increases telomere length in human cell lines through telomerase up-regulation or ALT activity — in vitro. Biogerontology. https://pubmed.ncbi.nlm.nih.gov/40908429/
- Khavinson VKh, et al. (2005). Pineal peptides restore the age-related disturbances in hormonal functions of the pineal gland and the pancreas (rhesus monkey) — animal. Exp Gerontol. https://pubmed.ncbi.nlm.nih.gov/15664732/
- Korkushko OV, et al. (2004). Effect of peptide preparation epithalamin on circadian rhythm of epiphyseal melatonin-producing function in elderly people — human, uncontrolled (extract). Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/15452611/
- Korkushko OV, et al. (2004). Effect of epithalamin on circadian relationship between endocrine function of the thymus and melatonin-producing function of the pineal gland in elderly people — human, uncontrolled (extract). Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/15455130/
- Kossoy G, Anisimov VN, Ben-Hur H, et al. (2006). Effect of the synthetic pineal peptide epitalon on spontaneous carcinogenesis in female C3H/He mice — animal. In Vivo. https://pubmed.ncbi.nlm.nih.gov/16634527/
- Khavinson VKh, et al. (2020). AEDG peptide (Epitalon) stimulates gene expression and protein synthesis during neurogenesis: possible epigenetic mechanism — in vitro. Molecules. https://pubmed.ncbi.nlm.nih.gov/32019204/
- Khavinson VKh, et al. (2003). Retinoprotective effect of Epithalon in Campbell rats of various ages — animal. Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/12910293/
- Khavinson VKh, et al. (2013). Peptidergic regulation of differentiation of embryonic retinal cells — in vitro. Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/23667897/
- Gatta M, Dovizio M, Milillo C, et al. (2025). The antioxidant tetrapeptide Epitalon enhances delayed wound healing in an in-vitro model of diabetic retinopathy — in vitro. Stem Cell Rev Rep. https://pubmed.ncbi.nlm.nih.gov/40493162/
- Kozina LS, et al. (2007). Antioxidant properties of geroprotective peptides of the pineal gland — animal. Arch Gerontol Geriatr. https://pubmed.ncbi.nlm.nih.gov/17317455/
- Khavinson VKh, et al. (2020). Short peptides protect oral stem cells from ageing — in vitro. Stem Cell Rev Rep. https://pubmed.ncbi.nlm.nih.gov/31677028/
- Kraskovskaya N, Linkova N, Sakhenberg E, et al. (2024). Short peptides protect fibroblast-derived induced neurons from age-related changes — in vitro. Int J Mol Sci. https://pubmed.ncbi.nlm.nih.gov/39518916/
- Sibarov DA, et al. (2007). Effects of intranasal administration of epitalon on neuron activity in the rat neocortex — animal. Neurosci Behav Physiol. https://pubmed.ncbi.nlm.nih.gov/17955380/
- Vanhee C, Moens G, Van Hoeck E, et al. (2015). Identification of the small research tetrapeptide Epitalon in two illegal pharmaceutical preparations — forensic analysis. Drug Test Anal. https://pubmed.ncbi.nlm.nih.gov/25535022/
- Korkushko OV, Khavinson VKh, Shatilo VB, et al. (2011). Pineal peptide preparation [epithalamin extract] inhibits rapid aging of elderly people: results of 15-year follow-up — human, controlled, single-group (extract). Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/22451889/
- Korkushko OV, Khavinson VKh, et al. (2006). Geroprotective effect of epithalamine (pineal gland peptide preparation) in elderly subjects with accelerated aging — human, controlled, single-group (extract). Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/17426848/
- Araj SK, Brzezik J, Mądra-Gackowska K, et al. (2025). Overview of Epitalon — a highly bioactive pineal tetrapeptide with promising properties — review. Int J Mol Sci. https://pubmed.ncbi.nlm.nih.gov/40141333/
- Mavrych V, Shypilova I, Bolgova O (2026). Therapeutic peptides in gerontology: mechanisms and applications for healthy aging — review. Front Aging. https://pubmed.ncbi.nlm.nih.gov/42021992/
- Rahman OF, Lee SJ, Seeds WA (2026). Therapeutic peptides in orthopaedics: applications, challenges, and future directions — review. JAAOS Glob Res Rev. https://pubmed.ncbi.nlm.nih.gov/41490200/
- Ullah S, Haider Z, Perera CD, et al. (2025). Epitalon-activated telomerase enhances bovine oocyte maturation rate and post-thawed embryo development — in vitro / animal. Life Sci. https://pubmed.ncbi.nlm.nih.gov/39788414/



