
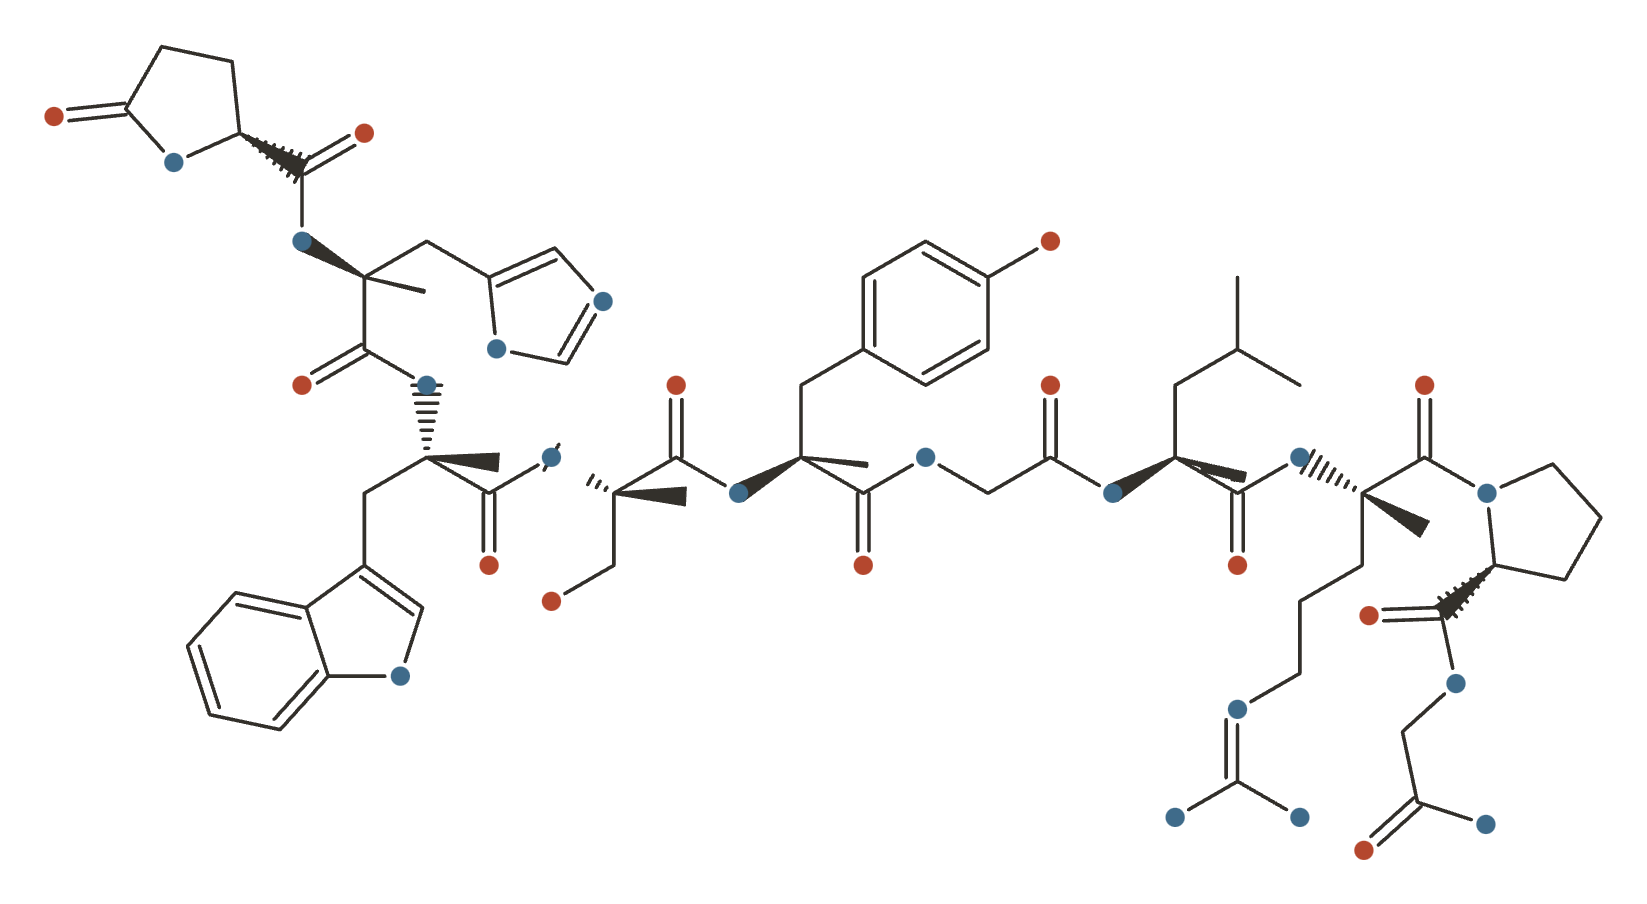
Gonadorelin (GnRH)
Synthetic GnRH, a decapeptide identical to the body's own — formerly approved for pituitary testing and pulsatile fertility therapy, both now discontinued.

Gonadorelin (GnRH) at a Glance
Gonadorelin is synthetic GnRH, a decapeptide identical to the hormone the hypothalamus releases in pulses to drive LH and FSH from the pituitary. That pulsatility is the whole mechanism: delivered in pulses it stimulates the reproductive axis, while delivered continuously it shuts it down — the basis of an entire class of hormone-suppressing drugs. It was approved for pituitary function testing and for inducing ovulation, and those products have largely been discontinued; it is now used mainly in compounded fertility and testosterone-support protocols.
History & Development
Gonadorelin is the body’s own GnRH, synthesised. It was approved twice, for two quite different jobs, and both products have since been discontinued - which is why a molecule with a genuine regulatory history now has no approved form at all.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Not established in the sources consulted for this section |
| Origin | Synthetic decapeptide identical to endogenous gonadotropin-releasing hormone (GnRH / LHRH) |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Formerly approved - marketed as Factrel (diagnostic) and Lutrepulse (pulsatile fertility therapy); both discontinued |
Discovery
GnRH sits at the top of the reproductive hormone cascade. The hypothalamus releases it in pulses, the pituitary answers with LH and FSH, and the gonads answer those with testosterone or estrogen. Gonadorelin is that decapeptide made synthetically - not an analogue, but the identical molecule.
The pulsatility is the whole pharmacology, and it cuts both ways. Delivered in pulses, GnRH drives the axis. Delivered continuously, it shuts the axis down, because the pituitary receptors desensitise - which is the basis of the long-acting GnRH agonists used to suppress sex hormones in prostate cancer and endometriosis. Same molecule, opposite outcome, decided entirely by timing.
Development & ownership
Gonadorelin reached the market in two forms. Factrel was the diagnostic product: a single intravenous bolus of roughly 100 µg provokes an LH and FSH rise, and the shape of that response distinguishes pituitary from hypothalamic causes of reproductive failure. Lutrepulse was the therapeutic one - a pump delivering micro-doses at roughly 90-minute intervals to reproduce natural pulsatility and induce ovulation in hypothalamic amenorrhoea.
Lutrepulse worked, and it was displaced anyway. Injectable gonadotropins achieve ovulation induction without requiring a patient to wear an infusion pump for weeks, and the diagnostic test was superseded by better assays. Both products were discontinued for practical and commercial reasons rather than safety ones.
How it reached the market
There is now no approved gonadorelin product. It reaches people through compounding pharmacies, prescribed mainly in men’s-health clinics on the theory that pulsatile GnRH maintains testicular function during testosterone therapy - a use that is mechanistically coherent and was never the indication either approved product carried.
What It's Used For
Gonadorelin is synthetic gonadotropin-releasing hormone — a decapeptide (pyroGlu-His-Trp-Ser-Tyr-Gly-Leu-Arg-Pro-Gly-NH₂, ~1,182 Da) with a sequence identical to the hormone the hypothalamus itself uses to drive the pituitary. It is not a gray-market research chemical and never was: it held two genuine US new drug approvals — Factrel (gonadorelin hydrochloride, NDA 018123, now held by Hikma, 0.1/0.2/0.5 mg base per vial) for pituitary-gonadal stimulation testing, and Lutrepulse Kit (gonadorelin acetate, NDA 019687, Ferring, 0.8 and 3.2 mg per vial) for pump-delivered pulsatile ovulation induction. Both are listed in Drugs@FDA with marketing status Discontinued. So the evidence here is real human clinical data, but it is old, mostly cohort- and case-series-grade rather than modern RCT, and it belongs to two narrow jobs — a diagnostic test and a pump-delivered fertility therapy — neither of which is what gonadorelin is mostly sold for today.
One fact governs this entire page, and it is a genuine safety issue rather than a curiosity. GnRH-receptor signaling is pattern-dependent, not dose-dependent in the ordinary sense. Delivered in brief pulses roughly every 90 minutes — the hypothalamus’s own rhythm — gonadorelin stimulates the axis, raising LH and FSH and driving the gonads. Delivered continuously, or at sustained high exposure, the identical molecule at the identical receptor does the opposite: the pituitary gonadotroph desensitizes and downregulates, and LH/FSH output collapses. That inversion is not a theoretical edge case — it is the exact mechanism by which the long-acting GnRH agonists leuprolide, goserelin, triptorelin and nafarelin achieve medical castration in prostate cancer, endometriosis and central precocious puberty. Same receptor, opposite clinical outcome, decided entirely by administration pattern. A badly-timed self-administered protocol can therefore suppress the very axis it was intended to support.
That inversion also makes the literature treacherous. A ClinicalTrials.gov search for “gonadorelin” returns overwhelmingly leuprolide, goserelin and triptorelin androgen-deprivation and ovarian-suppression trials — studies of suppression, not stimulation. Where evidence is cited, it is evidence generated with native GnRH/gonadorelin delivered pulsatilely, and where a source pools broader “LHRH” preparations that distinction is called out in the toggle rather than glossed. Route and pattern are load-bearing throughout: gonadorelin has negligible oral bioavailability, must be injected, and clears within minutes 11,
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Two readings of this table need care. The cryptorchidism 30% is not absence of evidence — that indication was tested at RCT level, found to work modestly, and then deliberately discontinued in favor of surgery 10Reference 10ReviewEfficacy and safety of hormonal treatment of cryptorchidism: current state of the art — reviewView study →. And the TRT-adjunct row carries no bar on purpose: it is the most common current use of gonadorelin and it has no controlled data at all, so scoring it — even low — would misrepresent vendor and clinic practice as a weak evidence base rather than an absent one.
Human, and a former FDA-approved indication. The GnRH (gonadorelin) stimulation test is the long-standing gold standard for probing the hypothalamic-pituitary-gonadal axis: a single intravenous dose is given and the LH/FSH rise is measured to separate central from peripheral causes of pubertal and gonadal disorders. It is validated in substantial pediatric series. In 584 GnRH stimulation tests, a single sample at 40 minutes gave 98% sensitivity and 100% specificity for diagnosing central precocious puberty against a 5 IU/L LH cut-off, simplifying a costly and uncomfortable multi-sample protocol 8Reference 8GnRH stimulation test in precocious puberty: single sample is adequate for diagnosis and dose adjustment — human (diagnostic study, 584 tests)View study →; a 2024 study in 76 girls found an averaged peak-LH cut-off of 4.25 IU/L discriminated central precocious puberty from premature thelarche with 94.7% sensitivity and 97.4% specificity 7Reference 7Diagnostic utility of the average peak LH levels measured during GnRH stimulation test — human (diagnostic accuracy, n=76 girls)View study →. This was the clinical basis of Factrel (NDA 018123).
Two caveats matter. First, the second half of Kandemir’s finding — that a 20-minute sample suffices for “dose adjustment” — refers to monitoring pubertal suppression in children already on long-acting GnRH-agonist therapy 8Reference 8GnRH stimulation test in precocious puberty: single sample is adequate for diagnosis and dose adjustment — human (diagnostic study, 584 tests)View study →.
That is the test being used to check that a suppressive drug is working; it is not a gonadorelin dosing finding, and it should not be read as one. Second, modern practice increasingly substitutes a GnRH analogue (triptorelin or leuprolide) for native gonadorelin as the stimulating agent, or relies on basal ultrasensitive LH assays — so part of this literature validates the test concept more than the specific molecule.
Gap: genuinely human-validated, but this is diagnostic accuracy rather than therapeutic benefit; the approved product is discontinued in the US; and some of the modern “GnRH stimulation test” literature uses analogues rather than gonadorelin itself.
Human, and the former Lutrepulse indication. In women with hypothalamic amenorrhea — functional, or from congenital GnRH deficiency and Kallmann syndrome — gonadorelin delivered by pump at physiological intervals restores ovulation and fertility. A 2014 practice synthesis reports cumulative pregnancy rates estimated at 70–100% after six cycles, with low complication and multiple-pregnancy rates compared with gonadotropin injection, and an average of only 2.8 cycles to conception — while noting the method is underused 5Reference 5ReviewOvulation induction by pulsatile GnRH therapy in 2014: literature review and synthesis of current practice — reviewView study →. A 2017 series treated 12 women (1 Kallmann, 4 normosmic isolated hypogonadotropic hypogonadism, 7 functional hypothalamic amenorrhea) at 5 µg/pulse intravenously or 15 µg/pulse subcutaneously every 90 minutes: all patients ovulated, single ovulation occurred in 30 of 33 cycles, and 10 pregnancies resulted across 7 patients 6Reference 6The induction of ovulation by pulsatile administration of GnRH: an appropriate method in hypothalamic amenorrhea — human (clinical series, n=12 women, 33 cycles)View study →. Notably, the one PCOS patient treated the same way showed a premature LH surge without ovulation — the method is specific to hypothalamic-origin amenorrhea, not a general fertility treatment.
The formal trial is NCT01976728 (Ferring): a multicenter, double-blind, randomized, placebo-controlled Phase 3 of subcutaneous pulsatile gonadorelin acetate at 10, 15 or 20 µg/pulse via OmniPod pump in primary amenorrhea with hypogonadotropic hypogonadism, completed with results posted, n=39. A second Ferring study, NCT00796289, took a different route entirely — a Phase 2 randomized, double-blind, double-dummy, placebo-controlled trial of pulsatile GnRH delivered by an iontophoretic transdermal patch (“Lutrepatch”) against clomiphene citrate in anovulatory or oligo-ovulatory infertile women, n=350, completed January 2010 — with no results ever posted. That is a substantial completed trial whose findings have never entered the literature, and the patch never reached market.
Gap: effective in humans, but the evidence is largely observational, the pivotal Phase 3 is small (n=39), a larger Phase 2 remains unreported, and the approved pump product has left the US market — a treatment that works and is hard to obtain.
Human cohorts, all retrospective. In congenital hypogonadotropic hypogonadism (CHH), the defect is absent pulsatile GnRH secretion, so replacing the pulses is the most physiological therapy available — and expert management reviews recognize it as a fertility-induction option alongside gonadotropin regimens 1Reference 1ReviewClinical management of congenital hypogonadotropic hypogonadism — reviewView study →. A 2024 retrospective series of 45 CHH men treated with pulsatile gonadorelin (7–15 µg per pulse every 90 minutes, mean follow-up 19.1 months) reported significantly raised FSH, LH and testosterone, improved external genitalia and secondary sexual characteristics, and spermatogenesis in 33 of 45 (73.3%), with 8 achieving natural fertility and 3 more via assisted reproduction 2Reference 2ObservationalEffect and safety of pulsatile GnRH therapy for male congenital hypogonadotropic hypogonadism — human (retrospective cohort, n=45 men)View study →. A 2025 retrospective study in 54 adult male CHH patients tracked pump therapy to 24 months, with mean testicular volume rising from 6.22 to 9.73 mL and testosterone from 234 to 381 ng/dL 3Reference 3ObservationalTherapeutic effects of a pulsatile GnRH pump on adult male patients with congenital hypogonadotropic hypogonadism (CHH): a retrospective study — human (retrospective cohort, n=54 men)View study →. The classic 1993 work induced testicular growth in 21 males and pubertal development in adolescent boys and girls with idiopathic hypogonadotropic hypogonadism, with spermatozoa ultimately developing in 15 of 19 patients 4Reference 4Clinical trialPulsatile GnRH treatment in boys and girls with idiopathic hypogonadotrophic hypogonadism — human (clinical study, n=21 males plus 5 adolescents)View study →.
Two honest qualifications. Response is not uniform: in the 2024 cohort, the 6 patients with cryptorchidism failed to reach normal testosterone even after 18 months 2Reference 2ObservationalEffect and safety of pulsatile GnRH therapy for male congenital hypogonadotropic hypogonadism — human (retrospective cohort, n=45 men)View study →. And none of these are randomized — they are single-center retrospective series, and in routine practice pulsatile GnRH is frequently bypassed for simpler hCG ± FSH injection regimens.
Gap: consistent human efficacy across independent cohorts, but no RCT, no long-term comparative data against gonadotropin therapy, and outcomes are worse in patients with cryptorchidism.
Human RCT-level evidence — for an indication the field then abandoned. Historically, LHRH/GnRH (given intranasally or by injection) was used to bring down undescended testes in boys, and the evidence quality is unusually good for a peptide. A 1995 meta-analysis of 33 studies covering 3,282 boys — 872 of them in randomized trials — found LHRH more effective than placebo, risk ratio 3.21 (95% CI 1.83–5.64), and 2.57 when retractile testes were excluded. In the combined randomized trials, success was 21% with LHRH, 19% with hCG and 4% with placebo, and the authors noted that non-randomized trials had overestimated the effect 9Reference 9Meta-analysisA review and meta-analysis of hormonal treatment of cryptorchidism — human (meta-analysis, 33 studies, 3,282 boys)View study →. A 2007 state-of-the-art review put overall efficacy at about 20% — less again if retractile testes are excluded — and, citing a number of potentially serious reported side effects, concluded that general use of hCG and GnRH for cryptorchidism “cannot be further recommended” 10Reference 10ReviewEfficacy and safety of hormonal treatment of cryptorchidism: current state of the art — reviewView study →.
An important attribution caveat: these trials pooled “LHRH” preparations broadly, including intranasal GnRH analogues such as buserelin, not solely native gonadorelin. Read this as class-level evidence for GnRH-receptor stimulation in cryptorchidism rather than a gonadorelin-specific result.
Gap: the strongest study design here attached to a use that has been superseded by orchidopexy. This is a finding about a discarded indication, not a current one — and it is class-level rather than molecule-specific.
This is the most common current use of gonadorelin, and it is deliberately not scored, because there is nothing to score. Telehealth and men’s-health clinics widely sell gonadorelin alongside testosterone replacement as a substitute for hCG, intended to keep the testes signaled and preserve testicular volume and fertility that suppressive TRT would otherwise shut down. Searching both PubMed and ClinicalTrials.gov for this indication returns no controlled trial of gonadorelin for it — not a small one, not a negative one, none. The use rests on three things, none of which is evidence: the mechanism (GnRH → LH/FSH → intratesticular support), analogy to hCG (which does have a genuine cryptorchidism trial record 9,
Two specific problems go beyond “untested.” First, the substitution rationale is supply-driven, not equivalence-driven. Gonadorelin displaced hCG in this niche largely because hCG’s regulatory and compounding status in the US became restrictive, making gonadorelin the more available compounded peptide — availability is not evidence of interchangeability, and hCG acts below the pituitary directly on the gonad, a different point in the axis entirely.
Second, the pharmacokinetics argue against the protocols actually used. Gonadorelin clears in minutes 11,
Gap: zero controlled data in the indication that accounts for most real-world use. A head-to-head against hCG measuring intratesticular testosterone, testicular volume and sperm parameters would settle it; none is registered.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Pituitary GnRH receptor — pulsatile exposure (~90 min) | ↑ LH and FSH release → ↑ gonadal steroid and gamete production | Ovulation induction; puberty/spermatogenesis in CHH; the diagnostic test |
| Same receptor — continuous or sustained exposure | Desensitization and downregulation → ↓ LH/FSH (medical castration) | Why leuprolide/goserelin/triptorelin suppress the axis; why a mis-timed protocol can invert its own intent |
| Initial-dose flare | Transient ↑ LH/FSH and sex steroids before any suppression | Safety on initiation; hormone-sensitive conditions |
| Downstream HPG axis | LH → Leydig-cell testosterone; FSH → Sertoli-cell spermatogenesis; in women, follicular development and ovulation | All therapeutic applications |
| Rapid peptidase cleavage | Clearance in minutes; measured human metabolic clearance ~455 mL/min in men 12Reference 12Metabolism of GnRH in man: influence of estrogens — human (PK / metabolic clearance, n=9 men, 7 women)View study → | Why a pump is required; why bolus injection cannot mimic pulsatility |
| GnRH neurons beyond reproduction (emerging) | Proposed roles in myelination, synaptic plasticity and cognition 13Reference 13ReviewGnRH and cognition — reviewView study → | Preliminary research only — not a therapeutic use |
The pulsatile-versus-continuous inversion is the single most important entry in this table. It is the reason two drug classes with directly opposite clinical purposes act at the same receptor, and it is the reason dosing pattern — not dose — is the safety-critical variable for anyone using this compound outside a supervised protocol.
Pharmacokinetics
Gonadorelin has negligible oral bioavailability — a decapeptide is digested rather than absorbed, so any oral product is pharmacologically inert regardless of its label. It must be given parenterally: intravenously or subcutaneously for pulsatile pump therapy, intravenously as a bolus for the diagnostic test; intranasal delivery was used historically in the cryptorchidism work 9Reference 9Meta-analysisA review and meta-analysis of hormonal treatment of cryptorchidism — human (meta-analysis, 33 studies, 3,282 boys)View study →.
Its defining property is an extremely short half-life, on the order of minutes — commonly cited as 2–10 minutes, reflecting rapid enzymatic cleavage. The canonical pharmacokinetic review of GnRH and its analogues is the reference point here 11Reference 11ReviewPharmacokinetics of gonadotropin-releasing hormone and its analogs — review (PK)View study →, and what has been measured directly in humans is metabolic clearance rate rather than a clean elimination half-life: continuous infusion studies put GnRH clearance at roughly 455 mL/min in men and ~1,769 mL/min in women (the latter varying cyclically), with estrogen status modulating it 12Reference 12Metabolism of GnRH in man: influence of estrogens — human (PK / metabolic clearance, n=9 men, 7 women)View study →. A single definitive human elimination half-life figure is not established in the accessible literature, and the widely-quoted “2–10 minutes” should be read as a well-supported approximation rather than a measured constant.
That brevity is the load-bearing PK fact, and it cuts both ways. It is what makes pulsatile delivery necessary — each pulse must clear before the next for the rhythm to register as a rhythm — and what makes it possible, since a pump can shape an exposure profile that a syringe cannot. It is equally why an every-few-days bolus schedule is a poor pharmacological match for the pump protocols that generated the evidence here. The approved products were supplied as lyophilized powder requiring reconstitution for pump loading; stability once reconstituted is limited, and stability parameters for compounded and gray-market material are not independently documented.
Clinical & regulatory status
Gonadorelin is a prescription drug that has essentially exited the US market. Per Drugs@FDA, two human products hold US new drug applications and both are listed with marketing status “Discontinued”: Factrel (gonadorelin hydrochloride, NDA 018123, Hikma; EQ 0.1, 0.2 and 0.5 mg base per vial, injectable) for pituitary-gonadal stimulation testing, and Lutrepulse Kit (gonadorelin acetate, NDA 019687, Ferring; 0.8 and 3.2 mg per vial, injectable) for pulsatile ovulation induction.
A precise distinction is worth drawing here, because it differs from the neighboring case of sermorelin. Sermorelin’s approvals were formally withdrawn by FDA in 2009, and FDA later published a determination that this was not for reasons of safety or effectiveness. For gonadorelin, a search of the Federal Register returns no withdrawal-of-approval notice and no safety-or-effectiveness determination for either NDA — the only Federal Register entries mentioning “Factrel” concern the veterinary product and horse-racing anti-doping rules. So the accurate statement is that these are approved applications that are no longer marketed, not applications whose approval has been revoked, and no published FDA finding characterizes why marketing stopped. This page will not infer a reason that no primary source states.
One identity trap follows from that veterinary listing: “Factrel” today is most visibly a cattle product (gonadorelin injection, Zoetis, regulated as an animal drug under 21 CFR 522.1077). A search on the brand name will surface veterinary labeling, which is not the human NDA 018123 product and carries different formulation and quality expectations.
Registered-trial activity is sparse and easy to misread. A ClinicalTrials.gov search for “gonadorelin” returns mostly leuprolide, goserelin and triptorelin trials — long-acting GnRH agonists used for androgen deprivation and ovarian suppression, which are pharmacologically opposite in effect. Filtering to genuine pulsatile-gonadorelin studies leaves the completed Phase 3 NCT01976728 (n=39, results posted) and the completed Phase 2 NCT00796289 (Lutrepatch iontophoretic patch, n=350, completed 2010 with no results posted). There are no registered controlled trials of gonadorelin as a TRT or testicular-preservation adjunct.
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 2registered (Phase 3 n=39 with results; Phase 2 n=350 unreported) + decades of older diagnostic and fertility studies | 0gonadorelin-specific | 0 | Extensive(GnRH physiology since the 1970s) |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. Gonadorelin is a genuine prescription pharmaceutical — not a research chemical, and not a dietary supplement. It held two US approvals (Factrel, NDA 018123; Lutrepulse Kit, NDA 019687), both now listed as Discontinued in Drugs@FDA, meaning there is no currently marketed FDA-approved human gonadorelin product in the United States. It remains registered in some other jurisdictions. The limits of that credential deserve stating plainly, because the marketing leans on it: the approvals covered a diagnostic pituitary test and pump-delivered pulsatile fertility therapy. They did not cover testosterone-replacement support, testicular preservation, libido, or any anti-aging use, and an approval never transfers from the indication and population it was granted for. Gonadorelin is not a scheduled or controlled substance.
How it’s supplied and administered. Lyophilized powder requiring reconstitution, given by injection — subcutaneous or intravenous. Clinical fertility use is delivered by a programmable pulsatile infusion pump at roughly 90-minute intervals; the diagnostic use was a single intravenous bolus. Oral routes do not work at all. The pump is not a convenience: it is the delivery mechanism under which the fertility evidence was generated, and the minutes-long half-life means the pattern it produces cannot be approximated by injections spaced days apart.
Sourcing reality (this is a safety issue, not a footnote). Because the approved products have left the US market, virtually all gonadorelin reaching consumers now comes through compounding pharmacies or unregulated research-chemical vendors. Compounded preparations are not FDA-approved products — they are not reviewed for safety, efficacy or manufacturing quality the way an approved drug is, and FDA has been actively scrutinizing the bulk-substance pathway that peptide compounding depends on, so availability is not stable. Gray-market powder has no oversight at all: uncertain identity and peptide content, mislabeling, under- or over-concentration, bacterial endotoxin, and no sterility guarantee. Self-reconstitution and self-injection add technique and contamination risk on top, and a peptide this labile degrades readily if mishandled or stored improperly. A vendor’s own certificate of analysis is not independent verification and can be falsified. None of the human efficacy data here were generated with compounded or gray-market material. This page does not recommend or link vendors.
Safety
Gonadorelin’s direct toxicity is low — it is a molecule the body already makes, given in micrograms. The hazard is pharmacological rather than toxicological: the same receptor stimulates under pulsatile dosing and shuts down under continuous dosing, so a mis-timed protocol can achieve the exact opposite of what was intended.
- The dosing pattern decides the direction. Continuous or overly frequent exposure suppresses the axis — the same mechanism used to produce chemical castration.
- Initiation can cause a gonadotropin flare. In hormone-sensitive conditions that is the main starting consideration, and why it is a supervised event.
- Every positive result came from a pump. Nothing establishes that ad-hoc injection schedules reproduce 90-minute pulses.
- Sex-steroid drugs confound it. Concurrent testosterone or estrogen blunts the response and invalidates the diagnostic test.
- Long-term pump therapy has real adverse effects. Gynecomastia in 8 of 45 men and subcutaneous induration in 6.
- No marketed US product. Supply is compounded or gray-market, adding identity, purity and endotoxin risk on an injected route.
Full Safety & Interactions Detail
Overall posture. Direct toxicity is low, and that is the least interesting thing about gonadorelin’s safety. It is a molecule the body already makes, given in microgram amounts, and the approved uses were either a single diagnostic dose or short cyclic therapy under supervision. Reported adverse effects in clinical use are mostly mild — injection-site reactions, headache, nausea, abdominal discomfort, and rare hypersensitivity. The largest modern cohort gives concrete figures: among 45 CHH men on long-term pump therapy, gynecomastia occurred in 8 and subcutaneous induration in 6, alongside allergic reactions 2Reference 2ObservationalEffect and safety of pulsatile GnRH therapy for male congenital hypogonadotropic hypogonadism — human (retrospective cohort, n=45 men)View study →. With pump therapy, catheter and infusion-site infection and mechanical failure are practical concerns.
The dominant hazard is pharmacological, not toxicological — and it is specific. Because the GnRH receptor stimulates under pulsatile exposure and desensitizes under continuous or sustained exposure, the direction of gonadorelin’s effect is determined by the administration pattern rather than by the molecule or the dose. This is not a theoretical concern: continuous GnRH-agonist exposure is precisely how leuprolide, goserelin, triptorelin and nafarelin produce chemical castration. The practical consequence for anyone self-administering is blunt — a mis-timed or overly frequent protocol can suppress the hypothalamic-pituitary-gonadal axis rather than support it, achieving the opposite of the intended effect. Every positive finding here was produced by pump-delivered pulses at roughly 90-minute intervals. Nothing establishes that ad-hoc injection schedules reproduce that, and the pharmacology gives specific reason to doubt it.
The flare. Initiation can produce a transient rise in gonadotropins and sex steroids before any suppression develops. In hormone-sensitive conditions this is the main consideration on starting, and it is why initiation of GnRH-receptor agonists in that setting is a supervised event.
Interactions. No comprehensive modern interaction assessment exists for off-label protocols. Recognized in the prescribing literature: drugs that alter pituitary function or sex-hormone levels — other GnRH analogues, androgens and estrogens, and dopaminergic or antipsychotic agents affecting prolactin — can blunt or confound the response, and the diagnostic test is invalidated by concurrent sex-steroid therapy. Concurrent exogenous testosterone is the norm in the off-label TRT setting and is itself axis-suppressing, so the interaction that matters most in practice is also the least studied.
Who should avoid it. Anyone with a hormone-sensitive malignancy or condition in which a gonadotropin flare would be harmful; anyone pregnant, breastfeeding or trying to conceive outside a supervised fertility protocol; children outside a diagnosed and supervised indication; and anyone unwilling to accept a non-approved compounded or gray-market product of unverified composition on an injected route. Because gonadorelin’s effect direction depends on delivery pattern, self-administration without monitoring of LH, FSH and testosterone means there is no way to know which direction the axis is actually moving.
Scope disclosure (honesty, not a claim):
- Human data? Yes — decades of it, from two formerly approved indications. But it is concentrated in diagnostic testing and pump-delivered fertility therapy, is largely cohort- and case-series-grade, and includes one completed Phase 2 (n=350) whose results were never posted. There is no human data of any kind for the TRT-adjunct use that now dominates real-world consumption.
- Interactions assessed? Partially — sex-steroid and pituitary-acting drug classes are recognized in the prescribing literature. No modern interaction screen covers off-label protocols, including the near-universal combination with exogenous testosterone.
- Pregnancy/lactation assessed? Not for chronic use; see the verdict above.
- Long-term safety established? No. Approved use was a single diagnostic dose or cyclic fertility therapy. The longest human follow-up here is CHH pump therapy to about two years 2,
3Reference 2ObservationalEffect and safety of pulsatile GnRH therapy for male congenital hypogonadotropic hypogonadism — human (retrospective cohort, n=45 men)View study →Reference 3ObservationalTherapeutic effects of a pulsatile GnRH pump on adult male patients with congenital hypogonadotropic hypogonadism (CHH): a retrospective study — human (retrospective cohort, n=54 men)View study → . Indefinite off-label injection has not been studied, and absence of reports is not evidence of safety. - Does the former approval make current use safe? No — and this is the specific misreading to guard against. Two narrow indications, delivered by pump or in a clinic, with products that are no longer marketed, say nothing about ongoing self-administered use for a different purpose entirely.
Never imply safety from silence. Where gonadorelin has not been studied — the TRT-adjunct use, long-term dosing, interactions with exogenous testosterone, and compounded or gray-market product quality — the correct statement is “not assessed,” not “safe.”
Used to achieve pregnancy, not continued through it. In pulsatile ovulation induction the goal is conception, and gonadorelin is not required to sustain an established pregnancy; any use in pregnancy should be specialist-directed only. Lactation data are not established. Off-label use during pregnancy or breastfeeding is not assessed and not advised.
Dosage
There is no consumer or oral dose for gonadorelin, and none is recommended here. Every figure below is a clinical or approved-era dose reported as data, not a protocol — and each is inseparable from the delivery method that produced it.
The diagnostic dose was a single intravenous bolus of about 100 µg in adults, with LH and FSH sampled afterward; a single sample at 40 minutes is sufficient for diagnosis 8Reference 8GnRH stimulation test in precocious puberty: single sample is adequate for diagnosis and dose adjustment — human (diagnostic study, 584 tests)View study →. For pulsatile ovulation induction, the studied regimens are 5 µg per pulse intravenously or 15 µg per pulse subcutaneously every ~90 minutes by pump 6Reference 6The induction of ovulation by pulsatile administration of GnRH: an appropriate method in hypothalamic amenorrhea — human (clinical series, n=12 women, 33 cycles)View study →, with the Ferring Phase 3 testing fixed subcutaneous doses of 10, 15 and 20 µg per pulse (NCT01976728). For pulsatile therapy in congenital hypogonadotropic hypogonadism, cohorts used 7–15 µg per pulse every 90 minutes by microinfusion pump, continued over months to years 2,
The pattern in every one of those figures is the point: a dose only means something paired with a pulse interval and a pump. A microgram figure lifted out of a 90-minute pulsatile protocol and delivered as a bolus twice a week is not the same intervention, and given the receptor’s pulsatile-versus-continuous inversion it may not even act in the same direction. Off-label TRT-adjunct doses are not listed here, because there is nothing to source them from except clinic and vendor practice, and this site does not launder those into dose figures. Oral products cannot deliver intact peptide whatever the label claims.
References
- Young J, et al. (2019). Clinical management of congenital hypogonadotropic hypogonadism — review. Endocrine Reviews. https://pubmed.ncbi.nlm.nih.gov/30698671/
- Niu YH, et al. (2024). Effect and safety of pulsatile GnRH therapy for male congenital hypogonadotropic hypogonadism — human (retrospective cohort, n=45 men). Zhonghua Nan Ke Xue (National Journal of Andrology). https://pubmed.ncbi.nlm.nih.gov/39210488/
- Jiang H, et al. (2025). Therapeutic effects of a pulsatile GnRH pump on adult male patients with congenital hypogonadotropic hypogonadism (CHH): a retrospective study — human (retrospective cohort, n=54 men). Translational Andrology and Urology. https://pubmed.ncbi.nlm.nih.gov/40800099/
- Delemarre-Van de Waal HA. (1993). Pulsatile GnRH treatment in boys and girls with idiopathic hypogonadotrophic hypogonadism — human (clinical study, n=21 males plus 5 adolescents). Human Reproduction. https://pubmed.ncbi.nlm.nih.gov/8276956/
- Gronier H, et al. (2014). Ovulation induction by pulsatile GnRH therapy in 2014: literature review and synthesis of current practice — review. Gynécologie Obstétrique & Fertilité. https://pubmed.ncbi.nlm.nih.gov/25245838/
- Christou F, et al. (2017). The induction of ovulation by pulsatile administration of GnRH: an appropriate method in hypothalamic amenorrhea — human (clinical series, n=12 women, 33 cycles). Gynecological Endocrinology. https://pubmed.ncbi.nlm.nih.gov/28277105/
- Koca SB, et al. (2024). Diagnostic utility of the average peak LH levels measured during GnRH stimulation test — human (diagnostic accuracy, n=76 girls). Journal of Pediatric Endocrinology and Metabolism. https://pubmed.ncbi.nlm.nih.gov/39163851/
- Kandemir N, et al. (2011). GnRH stimulation test in precocious puberty: single sample is adequate for diagnosis and dose adjustment — human (diagnostic study, 584 tests). Journal of Clinical Research in Pediatric Endocrinology. https://pubmed.ncbi.nlm.nih.gov/21448328/
- Pyörälä S, et al. (1995). A review and meta-analysis of hormonal treatment of cryptorchidism — human (meta-analysis, 33 studies, 3,282 boys). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/7673426/
- Thorsson AV, et al. (2007). Efficacy and safety of hormonal treatment of cryptorchidism: current state of the art — review. Acta Paediatrica. https://pubmed.ncbi.nlm.nih.gov/17462056/
- Handelsman DJ, Swerdloff RS. (1986). Pharmacokinetics of gonadotropin-releasing hormone and its analogs — review (PK). Endocrine Reviews. https://pubmed.ncbi.nlm.nih.gov/3007081/
- Cissewski K, et al. (1987). Metabolism of GnRH in man: influence of estrogens — human (PK / metabolic clearance, n=9 men, 7 women). Hormone Research. https://pubmed.ncbi.nlm.nih.gov/3108133/
- Kacimi L, Prévot V. (2025). GnRH and cognition — review. Endocrinology. https://pubmed.ncbi.nlm.nih.gov/39996304/



