
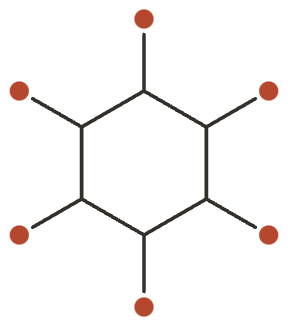
Inositol
A sugar-alcohol "pseudovitamin" and cellular second-messenger precursor used for mood, anxiety, PCOS and insulin sensitivity.

Inositol at a Glance
Inositol is a sugar alcohol the body makes from glucose and also gets from food, mainly fruit, beans and grains. The two forms that matter are myo-inositol and D-chiro-inositol, and they are usually supplemented together in the 40:1 ratio found in healthy tissue.
Its role is as a second messenger: inositol forms the backbone of the signalling molecules that relay instructions from insulin, FSH and serotonin receptors into the cell. That places it at the centre of both metabolic and mood pharmacology.
What It’s Used For
- PCOS — menstrual regularity & ovulation — restores ovulation and cycle regularity in polycystic ovary syndrome.
- Insulin sensitivity & metabolic syndrome — improves insulin sensitivity.
- Gestational diabetes prevention — reduces gestational diabetes incidence.
- Panic disorder & anxiety — reduces panic attacks and anxiety at high doses.
- Obsessive-compulsive disorder — studied in OCD.
- Depression — used for depressive symptoms.
- Bipolar depression (adjunct) — as an adjunct in bipolar depression.
How It Works
Inositol is the parent of the phosphoinositides — membrane lipids that receptors cleave to release second messengers inside the cell. When a receptor fires, IP3 is released and calcium follows, which is the step that turns an outside signal into an inside response.
Insulin signalling depends on inositol-containing mediators, which is the basis of the PCOS and metabolic results: restoring supply improves how strongly the cell answers insulin, and in PCOS that lowers androgen production and lets ovulation resume. Serotonin and noradrenaline receptors use the same second-messenger route, which is why the psychiatric doses are so much higher — 12–18 g/day against 2–4 g for metabolic use.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Inositol is a naturally occurring sugar alcohol (a cyclitol) — a six-carbon carbocyclic polyol that the body makes from glucose and also obtains from the diet, historically miscalled “vitamin B8.” Its most abundant form is myo-inositol (MI); a stereoisomer, D-chiro-inositol (DCI), is made from MI by an insulin-dependent epimerase and matters for the metabolic uses. Inositol is not a vitamin — humans synthesize several grams a day — so it is a conditional/pseudo-nutrient rather than a compound with a deficiency disease, and the benefits below are pharmacological (multi-gram dosing) rather than repletion of a shortfall. The evidence is strongest and best-replicated in the reproductive-metabolic space (PCOS, gestational-diabetes prevention), and weaker in psychiatry, where most trials are small, decades old, and come from a single Israeli research group. Because MI and DCI behave differently — and marketed products vary in form and MI:DCI ratio — form is a real caveat, not a footnote.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Meta-analyses of RCTs in which pregnant women (often overweight, obese, or with a family history of diabetes) took myo-inositol 2–4 g/day from the first/early second trimester report a lower incidence of gestational diabetes. A 2019 meta of 5 RCTs (n≈965) found roughly halved odds (OR ≈0.49) plus a lower preterm-delivery rate 4Reference 4Meta-analysisInositol for the prevention of gestational diabetes: a systematic review and meta-analysis of randomized controlled trials — meta-analysisView study →; a 2022 meta reached the same direction 5Reference 5Meta-analysisMyo-inositol supplementation for the prevention of gestational diabetes: a meta-analysis of randomized controlled trials — meta-analysisView study →; and the 2023 Cochrane review of seven studies concluded supplementation “may reduce” gestational diabetes, hypertensive disorders and preterm birth 3Reference 3Meta-analysisAntenatal dietary supplementation with myo-inositol for preventing gestational diabetes — Cochrane systematic review/meta-analysisView study →.
All of it is myo-inositol at gram doses started early, not a treatment once diabetes is established.
Gap: most trials are small, single-center (heavily Italian) and not powered for hard neonatal outcomes; Cochrane rates the certainty low and calls for large multi-center confirmation.
In polycystic ovary syndrome, inositol (MI alone, or MI+DCI, typically ~2–4 g MI/day) is used as an insulin-sensitizer to restore ovulatory cycles. A 2023 systematic review of 26 RCTs (1691 women) found the chance of a regular menstrual cycle about 1.8× higher than placebo (RR 1.79, 95% CI 1.13–2.85) and non-inferiority to metformin on most endpoints, with better tolerability 2Reference 2Meta-analysisInositol is an effective and safe treatment in polycystic ovary syndrome: a systematic review and meta-analysis — meta-analysisView study →.
A separate RCT showed MI+DCI (3.6:1) regularized cycles and improved insulin resistance 20Reference 20RCTEfficacy of myo-inositol and d-chiro-inositol combination on menstrual cycle regulation and improving insulin resistance in young women with polycystic ovary syndrome — randomized controlled trialView study →, and another trial found adding MI to metformin further improved cycle regularity and quality of life versus metformin alone 21Reference 21RCTA randomized controlled trial comparing myoinositol with metformin versus metformin monotherapy in polycystic ovary syndrome — randomized controlled trialView study →.
Countering this, the 2024 meta-analysis commissioned for the international PCOS guideline pooled 30 trials and judged the evidence “limited and inconclusive,” benefits confined to some metabolic measures 1Reference 1Meta-analysisInositol for Polycystic Ovary Syndrome: A Systematic Review and Meta-analysis to Inform the 2023 Update of the International Evidence-based PCOS Guidelines — meta-analysisView study →.
Gap: heterogeneous forms, doses and MI:DCI ratios across trials; the highest-rigor guideline synthesis downgrades the reproductive claims, so the honest read is “reasonable, better-tolerated option — not established first-line.”
Beyond PCOS, MI improves insulin signaling markers in insulin-resistant states. In postmenopausal women with metabolic syndrome, MI 2 g twice daily improved HOMA-IR, triglycerides, HDL and blood pressure versus diet alone in a 6-month RCT 17Reference 17RCTEffects of myo-inositol supplementation in postmenopausal women with metabolic syndrome — randomized controlled trialView study →, with benefits maintained at one year 18Reference 18RCTOne-year effects of myo-inositol supplementation in postmenopausal women with metabolic syndrome — randomized controlled trialView study →.
Mechanistically MI (and DCI) act as insulin second-messenger mediators, which is the throughline linking the PCOS, gestational-diabetes and metabolic-syndrome signals.
Gap: trials are modest in size and largely from overlapping Italian groups; effects are on surrogate metabolic markers rather than hard outcomes like incident diabetes.
Two small double-blind crossover RCTs support a genuine anxiolytic effect at high dose. Inositol 12–18 g/day reduced the frequency and severity of panic attacks and agoraphobia more than placebo, with minimal side effects 7Reference 7RCTDouble-blind, placebo-controlled, crossover trial of inositol treatment for panic disorder — randomized controlled trialView study →, and a second crossover trial found inositol not inferior to fluvoxamine over one month 8Reference 8RCTDouble-blind, controlled, crossover trial of inositol versus fluvoxamine for the treatment of panic disorder — randomized controlled trialView study →. A 2014 meta-analysis of inositol across anxiety/depression pooled these with other small trials 11Reference 11Meta-analysisA meta-analysis of inositol for depression and anxiety disorders — meta-analysisView study →.
Gap: total randomized n is small, crossover designs, all from one research group, and no modern replication — enough for a “cautiously promising” label, not a recommendation.
A 1995 double-blind crossover RCT found inositol 12 g/day produced significantly greater improvement on the Hamilton Depression Rating Scale than placebo by week 4, with no changes in blood, kidney or liver measures 10Reference 10RCTDouble-blind, controlled trial of inositol treatment of depression — randomized controlled trialView study →; the authors explicitly flagged that replication was crucial. A small 2014 meta-analysis suggested possible benefit, “especially” in premenstrual dysphoric disorder, while cautioning that few studies were available 11Reference 11Meta-analysisA meta-analysis of inositol for depression and anxiety disorders — meta-analysisView study →.
Gap: the anchor trial was never convincingly replicated in three decades; the effect rests on one small crossover study, so confidence is low despite the clean tolerability.
A single small double-blind crossover RCT found inositol 18 g/day lowered Yale-Brown Obsessive-Compulsive Scale scores versus placebo 9Reference 9RCTInositol treatment of obsessive-compulsive disorder — randomized controlled trialView study →. A later open-label trial adding inositol to SSRIs in treatment-refractory OCD was not persuasive.
Gap: one positive small crossover trial and an unconvincing augmentation study; nowhere near the evidence base for established OCD pharmacotherapy.
Inositol has been tried as an add-on for the depressive phase of bipolar disorder. A pilot RCT suggested a larger controlled study was warranted 13Reference 13RCTInositol as an add-on treatment for bipolar depression — randomized pilot trialView study →, and in the STEP-BD equipoize randomized trial inositol was one of three add-on options for treatment-resistant bipolar depression without emerging as clearly effective 14Reference 14RCTTreatment-resistant bipolar depression: a STEP-BD equipoise randomized effectiveness trial — randomized controlled trialView study →. The 2022 nutraceutical clinician guidelines gave inositol only weak/provisional endorsement in psychiatry overall 15Reference 15ReviewClinician guidelines for the treatment of psychiatric disorders with nutraceuticals and phytoceuticals — review/guidelineView study →.
Gap: underpowered and inconclusive; used adjunctively at best, and mania-switch risk in bipolar illness means it should not be self-directed.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Phosphatidylinositol / PIP2 → IP3 + DAG second-messenger cycle | Precursor supply; replenishes the intracellular signaling pool | PanicdepressionOCD (serotonergic/muscarinic receptor coupling) |
| Insulin signal transduction (MI- and DCI-phosphoglycan mediators) | Improves insulin sensitivity downstream of the receptor | PCOSgestational diabetesmetabolic syndrome |
| MI→DCI epimerase (insulin-dependent) | Tissue-specific MI:DCI balance; ovary favors high MI | Rationale for MI-predominant (e.g. 40:1) PCOS formulas |
| Surfactant phospholipid synthesis | Substrate for phosphatidylinositol in lung surfactant | Historical preterm-RDS rationale (not borne out in RCTs) |
Pharmacokinetics
Inositol is absorbed in the small intestine via sodium-dependent transporters and enters the body’s phosphoinositide pool; the endogenous synthesis rate (several grams/day, mainly kidney) dwarfs typical dietary intake (~1 g/day), which is why supplemental effects require gram-scale dosing. Oral myo-inositol raises plasma levels dose-dependently and is cleared over hours (elimination half-life on the order of a few hours), so studied psychiatric regimens split the large daily dose. High intestinal-transporter involvement means absorption is saturable, and co-ingested competitors (e.g. glucose) and certain milk proteins modulate uptake. There is no meaningful accumulation at steady state.
Clinical trials
Inositol is an inexpensive, off-patent dietary molecule, so industry-sponsored trial activity is limited; most randomized evidence comes from academic groups in reproductive medicine (Italy) and psychiatry (Israel). Registered and completed activity is concentrated in PCOS and gestational-diabetes prevention.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~60+RCTs | Several(PCOS, GDM, IVF) | Few | Extensive |
Last checked: July 2026.
Dietary Sources
Myo-inositol is widespread in food, but much of it in grains and legumes is bound as phytate (phytic acid, inositol hexaphosphate), which is poorly bioavailable and largely broken down by gut/plant phytases rather than absorbed as free inositol. Free myo-inositol is highest in fresh fruits, beans, whole grains and nuts; refining grains strips much of it. Typical mixed-diet intake is roughly 0.5–1 g/day — one to two orders of magnitude below the multi-gram doses used in the trials above, which is why food alone cannot reproduce the supplemental effects. The body’s own synthesis (mainly in the kidney, several grams/day) is the dominant source 19Reference 19Myo-inositol content of common foods: development of a high-myo-inositol diet — researchView study →.
| Food group | Relative myo-inositol content | Notes |
|---|---|---|
| Fresh fruits (esp. cantaloupe, citrus) | High (free form) | Oranges/melon among the richest per serving |
| Beans / legumes | High | Substantial fraction bound as phytate |
| Whole grains, bran | High but largely phytate-bound | Refining to white flour removes most |
| Nuts & seeds | Moderate–high | Also phytate-associated |
| Meat, dairy | Low–moderate | Human milk supplies inositol to infants |
Content values are from the classic Clements & Darnell food survey 19Reference 19Myo-inositol content of common foods: development of a high-myo-inositol diet — researchView study →; exact figures vary by cultivar and processing.
Dosage
Not an essential nutrient — there is no RDA/AI and no Tolerable Upper Intake Level. Doses below are those studied in research, not a personal recommendation.
- General / mood-supportive: 0.5–2 g/day myo-inositol.
- PCOS and gestational-diabetes prevention: myo-inositol 2–4 g/day, often as MI + DCI in a 40:1 ratio (the physiological plasma ratio), commonly with folic acid; started early in pregnancy for the GDM-prevention signal.
- Psychiatric (panic, OCD, depression) — research doses: 12–18 g/day, split across the day; these are high and were used under study conditions.
- Form note: most oral products are myo-inositol powder/capsules; MI is water-soluble with a mildly sweet taste and dissolves easily. MI and DCI are not interchangeable — DCI-heavy or high-DCI ratios have been associated with worse oocyte quality in PCOS (“DCI paradox”), so MI-predominant formulas are preferred for ovarian endpoints. Because intestinal transport is saturable, very large doses are split.
Safety
Inositol has an unusually clean safety profile for a supplement — it is a normal dietary and endogenous molecule, and the dose-limiting effect is gastrointestinal rather than systemic, even at the 12–18 g/day used in psychiatric trials.
- Unusually clean tolerability. Adverse effects were minimal across trials running up to 12–18 g/day.
- No blood, kidney or liver changes. Those measures were unchanged in the depression RCT.
- GI upset is the dose limit. Nausea, flatulence and loose stools appear at gram doses — start low if sensitive.
- Not self-directed in bipolar illness. Adjunctive use carries a theoretical mania-switch concern.
- Pregnancy use should be supervised. The evidence rests on specific regimens — see the box below.
Full Safety & Interactions Detail
Inositol has an unusually clean safety profile for a supplement. Across trials up to 12–18 g/day, adverse effects were minimal and limited mainly to mild gastrointestinal upset — nausea, flatulence, loose stools — which is the dose-limiting effect at the high psychiatric doses; blood counts and kidney/liver function were unchanged in the depression RCT 10Reference 10RCTDouble-blind, controlled trial of inositol treatment of depression — randomized controlled trialView study →.
It is a normal dietary and endogenous molecule, which underlies its tolerability.
- Bipolar disorder: because inositol has been used adjunctively for bipolar depression, there is a theoretical mania-switch concern; it should not be self-directed in bipolar illness 13,
14Reference 13RCTInositol as an add-on treatment for bipolar depression — randomized pilot trialView study →Reference 14RCTTreatment-resistant bipolar depression: a STEP-BD equipoise randomized effectiveness trial — randomized controlled trialView study → . - Pregnancy formulas: the GDM/PCOS evidence uses specific MI (±DCI/folate) regimens; pregnant users should use it under obstetric guidance rather than improvising doses 3,
4Reference 3Meta-analysisAntenatal dietary supplementation with myo-inositol for preventing gestational diabetes — Cochrane systematic review/meta-analysisView study →Reference 4Meta-analysisInositol for the prevention of gestational diabetes: a systematic review and meta-analysis of randomized controlled trials — meta-analysisView study → . - GI-sensitive individuals: start low; the sugar-alcohol nature can loosen stools at gram doses.
Verdict: studied and apparently well-tolerated at 2–4 g/day myo-inositol in pregnancy, with a signal for reduced gestational diabetes — but use under medical supervision. Multiple RCTs and a 2023 Cochrane review administered myo-inositol from early pregnancy specifically to prevent gestational diabetes and reported it appears safe, while cautioning the trials were small and not powered for hard neonatal outcomes 3,
References
- Fitz, V., Graca, S., Mahalingaiah, S., et al. (2024). Inositol for Polycystic Ovary Syndrome: A Systematic Review and Meta-analysis to Inform the 2023 Update of the International Evidence-based PCOS Guidelines — meta-analysis. J Clin Endocrinol Metab. https://pubmed.ncbi.nlm.nih.gov/38163998/
- Greff, D., Juhász, A. E., Váncsa, S., et al. (2023). Inositol is an effective and safe treatment in polycystic ovary syndrome: a systematic review and meta-analysis — meta-analysis. Reprod Biol Endocrinol. https://pubmed.ncbi.nlm.nih.gov/36703143/
- Motuhifonua, S. K., Lin, L., Alsweiler, J., et al. (2023). Antenatal dietary supplementation with myo-inositol for preventing gestational diabetes — Cochrane systematic review/meta-analysis. Cochrane Database Syst Rev. https://pubmed.ncbi.nlm.nih.gov/36790138/
- Vitagliano, A., Saccone, G., Cosmi, E., et al. (2019). Inositol for the prevention of gestational diabetes: a systematic review and meta-analysis of randomized controlled trials — meta-analysis. Arch Gynecol Obstet. https://pubmed.ncbi.nlm.nih.gov/30564926/
- Li, L., et al. (2022). Myo-inositol supplementation for the prevention of gestational diabetes: a meta-analysis of randomized controlled trials — meta-analysis. Eur J Obstet Gynecol Reprod Biol. https://pubmed.ncbi.nlm.nih.gov/35460931/
- Howlett, A., Ohlsson, A., Plakkal, N. (2015). Inositol in preterm infants at risk for or having respiratory distress syndrome — Cochrane systematic review. Cochrane Database Syst Rev. https://pubmed.ncbi.nlm.nih.gov/25927089/
- Benjamin, J., Levine, J., Fux, M., et al. (1995). Double-blind, placebo-controlled, crossover trial of inositol treatment for panic disorder — randomized controlled trial. Am J Psychiatry. https://pubmed.ncbi.nlm.nih.gov/7793450/
- Palatnik, A., Frolov, K., Fux, M., Benjamin, J. (2001). Double-blind, controlled, crossover trial of inositol versus fluvoxamine for the treatment of panic disorder — randomized controlled trial. J Clin Psychopharmacol. https://pubmed.ncbi.nlm.nih.gov/11386498/
- Fux, M., Levine, J., Aviv, A., Belmaker, R. H. (1996). Inositol treatment of obsessive-compulsive disorder — randomized controlled trial. Am J Psychiatry. https://pubmed.ncbi.nlm.nih.gov/8780431/
- Levine, J., Barak, Y., Gonzalves, M., et al. (1995). Double-blind, controlled trial of inositol treatment of depression — randomized controlled trial. Am J Psychiatry. https://pubmed.ncbi.nlm.nih.gov/7726322/
- Mukai, T., Kishi, T., Matsuda, Y., Iwata, N. (2014). A meta-analysis of inositol for depression and anxiety disorders — meta-analysis. Hum Psychopharmacol. https://pubmed.ncbi.nlm.nih.gov/24424706/
- Nemets, B., Talesnick, B., Belmaker, R. H., Levine, J. (2002). Myo-inositol has no beneficial effect on premenstrual dysphoric disorder — randomized controlled trial. World J Biol Psychiatry. https://pubmed.ncbi.nlm.nih.gov/12478879/
- Chengappa, K. N., Levine, J., Gershon, S., et al. (2000). Inositol as an add-on treatment for bipolar depression — randomized pilot trial. Bipolar Disord. https://pubmed.ncbi.nlm.nih.gov/11254020/
- Nierenberg, A. A., Ostacher, M. J., Calabrese, J. R., et al. (2006). Treatment-resistant bipolar depression: a STEP-BD equipoise randomized effectiveness trial — randomized controlled trial. Am J Psychiatry. https://pubmed.ncbi.nlm.nih.gov/16449473/
- Sarris, J., Ravindran, A., Yatham, L. N., et al. (2022). Clinician guidelines for the treatment of psychiatric disorders with nutraceuticals and phytoceuticals — review/guideline. World J Biol Psychiatry. https://pubmed.ncbi.nlm.nih.gov/35311615/
- Howlett, A., Ohlsson, A., Plakkal, N. (2019). Inositol in preterm infants at risk for or having respiratory distress syndrome — Cochrane systematic review (updated). Cochrane Database Syst Rev. https://pubmed.ncbi.nlm.nih.gov/31283839/
- Giordano, D., Corrado, F., Santamaria, A., et al. (2011). Effects of myo-inositol supplementation in postmenopausal women with metabolic syndrome — randomized controlled trial. Menopause. https://pubmed.ncbi.nlm.nih.gov/20811299/
- Santamaria, A., Giordano, D., Corrado, F., et al. (2012). One-year effects of myo-inositol supplementation in postmenopausal women with metabolic syndrome — randomized controlled trial. Climacteric. https://pubmed.ncbi.nlm.nih.gov/22192068/
- Clements, R. S. Jr., Darnell, B. (1980). Myo-inositol content of common foods: development of a high-myo-inositol diet — research. Am J Clin Nutr. https://pubmed.ncbi.nlm.nih.gov/7416064/
- Kachhawa, G., Senthil Kumar, K. V., Kulshrestha, V., et al. (2022). Efficacy of myo-inositol and d-chiro-inositol combination on menstrual cycle regulation and improving insulin resistance in young women with polycystic ovary syndrome — randomized controlled trial. Int J Gynaecol Obstet. https://pubmed.ncbi.nlm.nih.gov/34624138/
- Nazirudeen, R., Sridhar, S., Priyanka, R., et al. (2023). A randomized controlled trial comparing myoinositol with metformin versus metformin monotherapy in polycystic ovary syndrome — randomized controlled trial. Clin Endocrinol (Oxf). https://pubmed.ncbi.nlm.nih.gov/37265016/



