
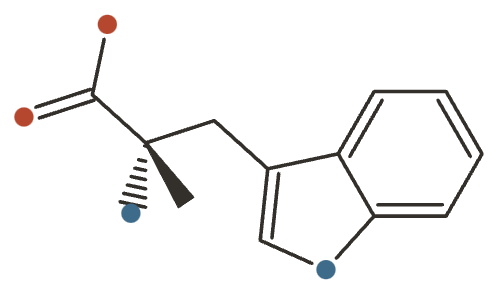
L-Tryptophan
The essential amino-acid precursor to serotonin and melatonin, taken mainly for sleep onset.

L-Tryptophan at a Glance
L-tryptophan is an essential amino acid — the body cannot make it — found in protein-rich foods such as turkey, eggs, cheese and oats. It is the rarest of the essential amino acids in the diet.
Its interest comes from being the sole precursor to serotonin, and from there to melatonin. That single pathway makes tryptophan the raw material for both mood and sleep chemistry, and it is why depleting it experimentally is a standard way to study serotonin’s role in the brain.
What It’s Used For
- Sleep onset — shortens the time taken to fall asleep.
- Depression treatment — raises serotonin for low mood.
- Mood / serotonin mechanism — the underlying pathway behind its mood effects.
- Premenstrual dysphoria — eases premenstrual mood symptoms.
- Seasonal affective disorder — used in seasonal low mood.
How It Works
Tryptophan is converted to 5-HTP by tryptophan hydroxylase, and 5-HTP to serotonin. That first step is the rate-limiting one and is tightly regulated, which is the key difference between tryptophan and 5-HTP: tryptophan feeds a controlled pathway, so the rise in serotonin is gentler and more physiological.
Getting into the brain is the other constraint. Tryptophan shares a transporter with the other large neutral amino acids, so it competes with everything else in a protein meal — which is why a carbohydrate snack raises brain tryptophan (insulin clears the competitors) and why supplements are taken away from protein. Most dietary tryptophan is diverted down the kynurenine pathway instead, leaving only a small fraction for serotonin.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Tryptophan is an essential amino acid and the rate-limiting dietary precursor to serotonin and, downstream, melatonin — which is why it is sold chiefly for sleep and mood. Its evidence posture is unusual: the mechanism is textbook-solid (raising plasma tryptophan relative to competing large neutral amino acids raises brain serotonin synthesis), but the clinical record is thin, old, and dominated by small trials, because tryptophan is an off-patent commodity with little modern trial funding. The most important distinction for a reader is between correcting low serotonergic tone (where tryptophan and its depletion studies show clear, reproducible effects on mood and sleep) and adding it on top of an already-adequate protein diet (where benefits are smaller and less certain). Form matters less here than for minerals — L-tryptophan is well absorbed — but timing relative to protein matters a great deal, since dietary amino acids compete with it for brain uptake. A safety history (the 1989 eosinophilia–myalgia outbreak) shaped its regulation and is addressed below.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the oldest and most direct part of tryptophan’s record. Early controlled work found that 1 g reduced sleep latency, with doses within the normal dietary range shortening the time to fall asleep 1Reference 1Sleep induced by L-tryptophan: effect of dosages within the normal dietary intake — controlled trialView study →, and a double-blind trial in chronic sleep-onset insomniacs reported a reduction in latency that appeared only after several nights of repeated use rather than on the first dose 2Reference 2RCTL-tryptophan administered to chronic sleep-onset insomniacs: late-appearing reduction of sleep latency — double-blind randomised trialView study →.
A double-blind cross-over study in severe chronic insomnia likewise reported improved sleep during treatment that partly reversed after withdrawal 3Reference 3RCTTreatment of severe chronic insomnia with L-tryptophan: double-blind cross-over studyView study →.
A 2025 systematic review and meta-analysis of dietary-supplement sleep interventions places tryptophan among the agents with a measurable effect on sleep quality, though it groups it with other supplements and the underlying tryptophan trials remain small 4Reference 4Meta-analysisDietary supplement interventions and sleep quality improvement: a systematic review and meta-analysis. https://pubmed.ncbi.nlm.nih.gov/41470897/View study →.
Effects are clearest for mild, sleep-onset difficulty at ~1 g and above; the free amino acid (not protein-bound) taken away from a protein meal is what was studied.
Gap: trials are small, decades old, and mostly in selected insomniacs — there is no large modern RCT confirming a durable benefit in the general population.
A placebo-controlled randomized trial dosed L-tryptophan (6 g/day) during the luteal phase (ovulation to menses) in women with premenstrual dysphoria and found significant improvement in mood symptoms — dysphoria, irritability, and mood swings — versus placebo 5Reference 5RCTA placebo-controlled clinical trial of L-tryptophan in premenstrual dysphoria — randomised controlled trialView study →. The result is mechanistically coherent, since luteal-phase mood symptoms are linked to serotonergic function, and it targets a defined at-risk window rather than continuous use.
Gap: it rests on essentially a single good trial at a high (6 g) dose; it has not been replicated at scale, and the dose is well above the sleep range.
The strongest human evidence that tryptophan matters for mood comes, paradoxically, from removing it: acute tryptophan depletion — a drink that transiently lowers plasma tryptophan — reliably induces a temporary lowering of mood in people with a personal or family history of depression, and to a lesser degree in healthy volunteers, confirming that brain serotonin synthesis is substrate-dependent 6Reference 6Meta-analysisMood is indirectly related to serotonin, norepinephrine and dopamine levels in humans: a meta-analysis of monoamine depletion studiesView study →.
Reviews of tryptophan loading (the reverse manipulation) report effects on mood, cognition, and sleep consistent with this pathway 7Reference 7ReviewEffects of tryptophan loading on human cognition, mood, and sleep — reviewView study →.
A within-day social-behavior study found that raising versus lowering tryptophan shifted mood and agreeable/quarrelsome behavior, again showing the pathway is responsive to dietary tryptophan 10Reference 10ReviewThe effect of raising and lowering tryptophan levels on human mood and social behaviour — reviewView study →.
This is proof of mechanism, not proof that supplementation treats a disorder.
Gap: depletion effects show the pathway is real but are the opposite manipulation from supplementation; they do not establish that adding tryptophan above adequacy improves mood in healthy people.
A meta-analysis of tryptophan and 5-hydroxytryptophan for depression found the pooled data suggestive of benefit over placebo but concluded that the evidence was of insufficient quality — trials were small, heterogeneous, and at risk of bias — so the authors did not recommend clinical use 8Reference 8Meta-analysisAre tryptophan and 5-hydroxytryptophan effective treatments for depression? A meta-analysis. https://pubmed.ncbi.nlm.nih.gov/12169147/View study →, a caution echoed in the associated systematic review 9Reference 9Systematic reviewTryptophan and 5-hydroxytryptophan for depression — systematic reviewView study →. A small preliminary RCT combining tryptophan with fluoxetine reported a faster antidepressant onset, but it is exploratory and carries the serotonin-syndrome caution of combining serotonergic agents 11Reference 11RCTPreliminary randomized double-blind placebo-controlled trial of tryptophan combined with fluoxetine — randomised controlled trial. https://pubmed.ncbi.nlm.nih.gov/11022398/View study →.
Gap: as a stand-alone antidepressant, tryptophan is unproven; the meta-analytic signal is too fragile and the trials too small and dated to support it, and combination use with SSRIs is a safety question, not an endorsement.
A randomized trial compared L-tryptophan against light therapy in seasonal affective disorder and found tryptophan produced improvement broadly comparable to light in the studied group, positioning it as a possible adjunct or alternative 12Reference 12RCTEfficacy of light versus tryptophan therapy in seasonal affective disorder — randomised controlled trialView study →. Other work in this area is largely mechanistic (serotonergic polymorphisms and seasonality) rather than interventional.
Gap: the interventional trials are few, small, and underpowered, and light therapy remains the better-evidenced first-line option; tryptophan for SAD should be regarded as preliminary.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Tryptophan → 5-HTP → serotonin (via tryptophan hydroxylase, TPH2) | ↑ central serotonin synthesis (substrate-limited) | SleepmoodPMSSAD |
| Serotonin → melatonin (pineal, at night) | ↑ melatonin | Sleep onset |
| Competition with large neutral amino acids (LNAA) at blood–brain barrier | tryptophan/LNAA ratio sets brain uptake | Why timing vs protein meals matters |
| Kynurenine pathway (>90% of tryptophan metabolism; IDO/TDO enzymes) | diverts tryptophan to kynurenine, away from serotonin | Inflammation/mood link; niacin synthesis |
Pharmacokinetics
Oral L-tryptophan (free amino acid) is well absorbed from the small intestine. Its rate-limiting behavior for brain serotonin is not about gut absorption but about transport across the blood–brain barrier, where tryptophan competes with other large neutral amino acids (leucine, isoleucine, valine, phenylalanine, tyrosine) for the same carrier — so the tryptophan-to-LNAA ratio, not the absolute dose, governs how much reaches the brain. This is why taking it with a high-protein meal blunts the effect (the meal supplies competing amino acids) while taking it with carbohydrate, or apart from protein, raises the ratio. Only a small fraction of dietary tryptophan is used for serotonin; more than 90% enters the kynurenine pathway, which also produces a modest amount of niacin (vitamin B3). Plasma tryptophan has a half-life on the order of a few hours; effects on sleep in the older trials sometimes appeared only after several nights of dosing rather than acutely.
Clinical trials
Registered and published trial activity is modest and heavily weighted toward older, small studies; as an off-patent amino acid, tryptophan attracts little industry-funded trial investment, and most recent literature is mechanistic (kynurenine pathway, gut–brain axis) rather than new efficacy trials.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~15–20(mostly small, older) | Few | Rare | Extensive(metabolism, depletion) |
Last checked: July 2026.
Dietary Sources
L-Tryptophan is the least abundant essential amino acid in the diet, which is part of why brain serotonin is substrate-limited. It is present in virtually all protein-containing foods; a typical mixed diet supplies roughly 0.7–1.5 g/day, far above the requirement. The paradox worth understanding: eating a tryptophan-rich, high-protein food (turkey being the folk example) does not reliably raise brain tryptophan, because the same meal delivers a flood of competing large neutral amino acids that crowd tryptophan out at the blood–brain barrier. Carbohydrate, by triggering insulin that clears competing amino acids into muscle, does more to raise the brain tryptophan ratio than a protein meal does.
| Food (per ~100 g) | Approx. tryptophan |
|---|---|
| Egg | ~0.15–0.20 g |
| Chicken / turkey | ~0.25–0.35 g |
| Cheese (hard) | ~0.30–0.55 g |
| Soybeans / tofu | ~0.30–0.55 g |
| Pumpkin / sesame seeds | ~0.30–0.55 g |
| Oats | ~0.18 g |
| Milk | ~0.04 g |
Refining and processing that strip protein reduce tryptophan content. Because dietary supply comfortably exceeds requirement in anyone eating adequate protein, deficiency is rare outside of malnutrition, malabsorption, or specific metabolic disorders (e.g. Hartnup disease). (Food values approximate; cross-check NIH ODS / USDA food-composition data.)
Dosage
Requirement. Tryptophan is an essential amino acid; the estimated adult requirement is on the order of 4 mg/kg/day (about 280 mg for a 70 kg adult) by indicator-amino-acid-oxidation methods 13Reference 13Tryptophan requirement in young adult women determined by indicator amino acid oxidationView study →. Ordinary protein intake supplies several times this, so supplementation is about pharmacological serotonergic effect, not correcting a dietary shortfall.
Studied supplemental ranges (doses used in research, not a personal recommendation):
- Sleep onset: ~1–3 g taken at bedtime, away from a protein meal 1,
2, .3Reference 1Sleep induced by L-tryptophan: effect of dosages within the normal dietary intake — controlled trialView study →Reference 2RCTL-tryptophan administered to chronic sleep-onset insomniacs: late-appearing reduction of sleep latency — double-blind randomised trialView study →Reference 3RCTTreatment of severe chronic insomnia with L-tryptophan: double-blind cross-over studyView study → - Premenstrual dysphoria: 6 g/day during the luteal phase in the one positive RCT 5Reference 5RCTA placebo-controlled clinical trial of L-tryptophan in premenstrual dysphoria — randomised controlled trialView study →.
- Mood/depression research: typically 1–3 g/day, though efficacy is unproven 8Reference 8Meta-analysisAre tryptophan and 5-hydroxytryptophan effective treatments for depression? A meta-analysis. https://pubmed.ncbi.nlm.nih.gov/12169147/View study →.
Timing note (the practical headline): take it away from high-protein meals — ideally with a small carbohydrate snack — to maximize the tryptophan-to-LNAA ratio that governs brain uptake. Vitamin B6 is a cofactor in the serotonin-synthesis step. There is no established Tolerable Upper Intake Level; higher chronic doses have not been formally characterized for safety.
Safety
L-tryptophan’s intrinsic toxicity is low, and the dose-limiting concern is drug interaction rather than the amino acid itself — it raises serotonergic tone, so stacking it with serotonergic medication is the one thing that can genuinely go wrong.
- Low intrinsic toxicity. Generally well tolerated at the studied gram-level doses.
- Do not combine with serotonergic drugs. SSRIs, SNRIs, MAOIs, triptans and tramadol carry a real serotonin-syndrome risk.
- Avoid supplemental doses in pregnancy and breastfeeding. Not established — see the box below.
- Product purity genuinely matters here. The 1989 EMS outbreak traced to contaminants in one manufacturer’s batch, not to tryptophan itself.
- Mild expected effects. Drowsiness, nausea or light-headedness; no upper limit has been set.
Full Safety & Interactions Detail
At the studied gram-level doses, L-tryptophan is generally well tolerated; the most common adverse effects are mild — drowsiness (expected), nausea, or light-headedness. Intrinsic toxicity is low.
The dose-limiting concern is not toxicity but drug interaction. Tryptophan raises serotonergic tone, so combining it with SSRIs, SNRIs, MAOIs, triptans, tramadol, or other serotonergic agents carries a real risk of serotonin syndrome and should not be done without medical supervision. This is the single most important caution on the page.
The eosinophilia–myalgia syndrome (EMS) outbreak of 1989 — which caused tryptophan to be pulled from the US market for years — was traced to contaminants in a single manufacturer’s production batch, not to tryptophan itself 14Reference 14ReviewSafety concerns regarding impurities in L-tryptophan associated with eosinophilia–myalgia syndrome — review. https://pubmed.ncbi.nlm.nih.gov/37453474/View study →.
Modern pharmaceutical-grade tryptophan is not implicated, but it is the reason product purity and reputable sourcing genuinely matter here. There is no established Upper Limit — absence of a UL is not evidence that unlimited intake is safe.
Avoid supplemental doses unless directed by a clinician. Dietary tryptophan is essential and safe, but supplemental gram-level doses have not been established as safe in pregnancy or lactation, and the serotonergic activity is a theoretical concern. Not adequately studied — treat as not established.
References
- Hartmann E, Spinweber CL. (1979). Sleep induced by L-tryptophan: effect of dosages within the normal dietary intake — controlled trial. J Nerv Ment Dis. https://pubmed.ncbi.nlm.nih.gov/469515/
- Spinweber CL (1986). L-tryptophan administered to chronic sleep-onset insomniacs: late-appearing reduction of sleep latency — double-blind randomised trial. Psychopharmacology. https://pubmed.ncbi.nlm.nih.gov/3097693/
- Demisch K, et al. (1987). Treatment of severe chronic insomnia with L-tryptophan: double-blind cross-over study. Pharmacopsychiatry. https://pubmed.ncbi.nlm.nih.gov/3432357/
- Mei M, Zhou Q, Gu W, et al. (2025). Dietary supplement interventions and sleep quality improvement: a systematic review and meta-analysis. https://pubmed.ncbi.nlm.nih.gov/41470897/
- Steinberg S, et al. (1999). A placebo-controlled clinical trial of L-tryptophan in premenstrual dysphoria — randomised controlled trial. Biol Psychiatry. https://pubmed.ncbi.nlm.nih.gov/10023508/
- Ruhé HG, Mason NS, Schene AH. (2007). Mood is indirectly related to serotonin, norepinephrine and dopamine levels in humans: a meta-analysis of monoamine depletion studies. Mol Psychiatry. https://pubmed.ncbi.nlm.nih.gov/17389902/
- Silber BY, Schmitt JAJ. (2010). Effects of tryptophan loading on human cognition, mood, and sleep — review. Neurosci Biobehav Rev. https://pubmed.ncbi.nlm.nih.gov/19715722/
- Shaw K, Turner J, Del Mar C. (2002). Are tryptophan and 5-hydroxytryptophan effective treatments for depression? A meta-analysis. https://pubmed.ncbi.nlm.nih.gov/12169147/
- Shaw K, Turner J, Del Mar C. (2002). Tryptophan and 5-hydroxytryptophan for depression — systematic review. Cochrane Database Syst Rev. https://pubmed.ncbi.nlm.nih.gov/11869656/
- Young SN. (2013). The effect of raising and lowering tryptophan levels on human mood and social behaviour — review. Philos Trans R Soc Lond B. https://pubmed.ncbi.nlm.nih.gov/23440461/
- Levitan RD, Shen JH, Jindal R, et al. (2000). Preliminary randomized double-blind placebo-controlled trial of tryptophan combined with fluoxetine — randomised controlled trial. https://pubmed.ncbi.nlm.nih.gov/11022398/
- Ghadirian AM, et al. (1998). Efficacy of light versus tryptophan therapy in seasonal affective disorder — randomised controlled trial. J Affect Disord. https://pubmed.ncbi.nlm.nih.gov/9716275/
- Lazaris-Brunner G, et al. (1998). Tryptophan requirement in young adult women determined by indicator amino acid oxidation. Am J Clin Nutr. https://pubmed.ncbi.nlm.nih.gov/9701187/
- Ko SM, Park JE, Heo IK, et al. (2023). Safety concerns regarding impurities in L-tryptophan associated with eosinophilia–myalgia syndrome — review. https://pubmed.ncbi.nlm.nih.gov/37453474/



