
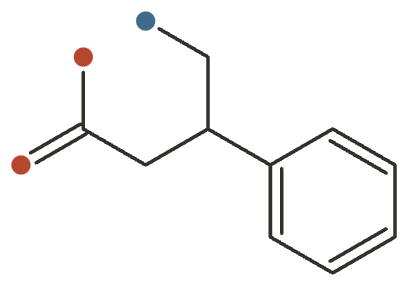
Phenibut
A synthetic GABA-B agonist used for anxiety and sleep, with a genuine, well-documented liability for tolerance, dependence and severe withdrawal.

Phenibut at a Glance
Phenibut (β-phenyl-γ-aminobutyric acid) is a synthetic GABA analogue — GABA with a phenyl ring bolted onto the backbone so that, unlike GABA itself, it crosses the blood–brain barrier. It was developed in the Soviet Union in the 1960s and is still prescribed as an anxiolytic and sleep aid in Russia and neighbouring states under names like Noofen and Anvifen. Everywhere else it is unapproved, and sold gray-market online as a “nootropic.”
This page is one of the site’s clearer cases where the honest headline is a warning rather than a benefit. The efficacy evidence is weak: no modern randomised placebo-controlled trial exists, and the human data that support its anxiolytic use are old, non-blinded and almost entirely Eastern-European. What is extensively documented — across multiple systematic reviews — is harm: physical dependence, a withdrawal syndrome that can escalate to psychosis, delirium and seizures, and acute intoxication requiring hospitalisation. That asymmetry is the whole story, so it is stated up front rather than buried.
The reconciling detail is dose. Used at 0.25–2 g/day in Russian clinical practice, phenibut appears reasonably tolerated. Nearly every Western casualty comes from self-dosing gram quantities of unregulated powder — a range from roughly 0.5 g to, in the worst reports, 100 g/day. It is not a nutrient; there is no deficiency to correct and no dietary requirement, so any effect is a drug effect on an otherwise-intact system.
What It’s Used For
- Anxiety and adjustment disorder — the best-supported use, but “best-supported” here means decades of Russian clinical use plus small non-blinded and observational studies, not controlled trials 6,
7, .8Reference 6Systematic reviewSafety and tolerability of the anxiolytic and nootropic drug phenibut — systematic reviewView study →Reference 7ObservationalEfficacy of Noofen 250 mg capsules for the management of anxious-neurotic symptoms in adjustment disorder — observational studyView study →Reference 8RCTPharmacotherapy of anxiety disorders in patients with chronic cerebral ischaemia — randomized trialView study → - Sleep and insomnia — widely taken for it and mechanistically plausible given the sedation, but with essentially no controlled efficacy data; regular use for sleep is a common route into dependence 7Reference 7ObservationalEfficacy of Noofen 250 mg capsules for the management of anxious-neurotic symptoms in adjustment disorder — observational studyView study →.
- Tension-type headache — a single small open-label paediatric study, probably reflecting anxiolysis rather than a specific effect 16Reference 16Clinical trialPreventive treatment of tension headache in children and adolescents — clinical trialView study →.
- “Nootropic” cognitive enhancement — the marketing angle, resting on almost no controlled human data 1,
3Reference 1ReviewPhenibut: a drug with one too many “buts” — reviewView study →Reference 3ReviewPhenibut (β-phenyl-γ-aminobutyric acid): an easily obtainable “dietary supplement” with propensities for physical dependence and addiction — reviewView study → .
The through-line: for every use, the efficacy evidence is thin and low-quality, while the dependence and withdrawal risk is well established. Anyone reaching for phenibut for calm or sleep has far better-characterised options.
How It Works
Phenibut is a GABA-B receptor agonist, but a strikingly weak one — its EC50 (~1362 µM) is more than two hundred times higher than baclofen’s (~6 µM) 9,
The pharmacology is stereospecific: the R-enantiomer carries almost all the activity, while S-phenibut is largely inert at GABA-B — which is why the racemate is comparatively weak and why the fluorinated analogue “F-phenibut” (sold separately online, and correspondingly more potent and more dangerous) exists at all 11,
Pharmacology & Research
Phenibut (β-phenyl-γ-aminobutyric acid) is a synthetic GABA analogue and low-potency GABA-B receptor agonist, developed in the Soviet Union in the 1960s and still prescribed as an anxiolytic and sleep aid in Russia and neighbouring states — while sold gray-market elsewhere as a “nootropic” dietary supplement it is not an approved medicine or supplement 1,
Unusually for a compound here, the decision-relevant literature is not about efficacy: robust modern randomised evidence for anxiety, sleep or cognition is essentially absent, and what human data exist are old, non-blinded, and almost entirely Eastern-European 1,
What is well documented — across multiple systematic reviews — is harm: physical dependence, a severe withdrawal syndrome, and acute intoxication, overwhelmingly in people self-dosing gram quantities bought online 2,
The pivotal distinction here is not deficiency-vs-repletion (phenibut is not a nutrient) but therapeutic dose (0.25–2 g/day, apparently tolerable) versus the supraphysiologic self-dosing (0.5–100 g/day) that generates nearly every reported casualty 6Reference 6Systematic reviewSafety and tolerability of the anxiolytic and nootropic drug phenibut — systematic reviewView study →.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Phenibut has been prescribed as an anxiolytic in Russia and Eastern Europe for more than half a century, and a 2020 systematic review pooled 11 clinical trials (583 patients) — though these were assembled mainly to gauge safety, and reported adverse events in only 5.66% of patients at therapeutic doses (0.25–2 g/day) 6Reference 6Systematic reviewSafety and tolerability of the anxiolytic and nootropic drug phenibut — systematic reviewView study →.
The most recent data are a 2025 Latvian non-interventional observational study of 90 adults with adjustment disorder given Noofen (phenibut) 250 mg three times daily: ADNM-20 symptom scores fell by a mean of 14.8 ± 11.3 points over three weeks (p < 0.001), with the high-severity proportion dropping 2.5-fold 7Reference 7ObservationalEfficacy of Noofen 250 mg capsules for the management of anxious-neurotic symptoms in adjustment disorder — observational studyView study →.
Older Russian work reports comparable anxiolytic effect to reference agents in anxiety-spectrum disorders 8Reference 8RCTPharmacotherapy of anxiety disorders in patients with chronic cerebral ischaemia — randomized trialView study →.
All of this is open-label, observational or non-Western with high risk of bias — there is no modern randomised, placebo-controlled trial, and reviewers repeatedly note this gap 1,
Gap: no blinded placebo-controlled RCT exists; every supporting study is observational or open-label, so effect size and placebo contribution are unquantified.
A small open-label study treated 30 children and adolescents (aged 8–16) with noophen (phenibut) 15–20 mg/kg/day for two months for tension-type-headache prevention, reporting significant reductions in headache frequency, duration and intensity alongside lower anxiety and improved sleep 16Reference 16Clinical trialPreventive treatment of tension headache in children and adolescents — clinical trialView study →. The signal is consistent with phenibut’s anxiolytic action but the design is weak — no control group, no blinding, small n, single centre — and it has not been replicated in adults or in controlled conditions.
Gap: one small uncontrolled paediatric trial; no randomised or adult data, and benefit may simply reflect anxiolysis/sedation rather than a specific antimigraine effect.
Phenibut is widely taken — and historically prescribed in Russia — as a sleep aid, and a 1980s Soviet study examined its effect on nocturnal sleep during alcohol-abstinence syndrome. Its sedating GABA-B agonism makes a hypnotic effect mechanistically plausible, and sleep improvement appears as a secondary outcome in the anxiety studies above 7Reference 7ObservationalEfficacy of Noofen 250 mg capsules for the management of anxious-neurotic symptoms in adjustment disorder — observational studyView study →.
But there is essentially no modern controlled trial isolating phenibut’s efficacy as a hypnotic, and high or late doses are associated with next-day sedation and, with repetition, tolerance.
Gap: no controlled efficacy data for insomnia as a primary endpoint; reported benefit is anecdotal or secondary, and regular use for sleep is a common route into dependence.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| GABA-B receptor | Agonist, but low potency — EC50 ≈ 1362 µM vs baclofen 6 µM | Anxiolysissedationdependence & withdrawal |
| α2δ subunit of voltage-gated Ca²⁺ channels | Binding (R-phenibut Ki ≈ 23 µM, gabapentinoid-like) | Analgesiapossible anxiolytic contribution |
| GABA-A receptor | Weak activity | Sedation |
| Dopamine receptors / β-phenethylamine | Stimulates dopamine; antagonises anxiogenic PEA | Mild activating/mood effect at low dose |
| Stereochemistry | R-phenibut carries the activity; S-phenibut is largely inactive at GABA-B | Explains racemate potency; basis of “F-phenibut” analogues |
Phenibut’s very low GABA-B potency is the mechanistic key to its risk profile: because it takes gram-level doses to achieve effect, the margin between an active dose and a sedative-overdose or dependence-inducing dose is narrow, and its dual gabapentinoid-like α2δ action mirrors baclofen — which is why baclofen tapers are used to manage its withdrawal 9,
Pharmacokinetics
Human pharmacokinetic data are sparse. Phenibut is hydrophilic yet readily crosses the blood–brain barrier; oral onset is typically 2–4 hours, and at high doses effects can persist much longer (contributing to next-day sedation). It is thought to be excreted largely unchanged by the kidney, so renal impairment prolongs exposure. A validated human half-life is not well established in the peer-reviewed literature; most quantitative PK work is in rodents on Russian phenibut-salt derivatives rather than on the drug itself in humans 17Reference 17Study of the absolute bioavailability of citrocard, a new GABA derivative — animal studyView study →. Practically, the combination of low receptor potency, slow onset and long tail is what drives users to re-dose — the pattern that precedes tolerance and dependence.
Clinical trials
Phenibut is off-patent and unapproved in the West, and a search of ClinicalTrials.gov returns no registered trials — there is no Western industry or academic trial activity. The human evidence base is instead Eastern-European clinical use and observational studies (≈11 trials, 583 patients, per the 2020 safety review), plus a recent Latvian observational study; preclinical pharmacology is comparatively extensive 6,
| Completed (registered, Western) | Planned | Terminated | Preclinical |
|---|---|---|---|
| 0 | 0 | 0 | ~many |
Last checked: August 2026.
Dietary Sources
Phenibut is not found in food — it is a wholly synthetic GABA analogue, first made in the Soviet Union in the 1960s, produced by chemical synthesis (the phenyl ring is added at the β-position of the GABA backbone; the racemate is used clinically, and its pharmacological activity resides almost entirely in the R-enantiomer) 9,
Intake & Dosage
These are doses drawn from the literature, not a personal recommendation. Because phenibut is not a nutrient, there is no RDA/AI and no established Tolerable Upper Intake Level. The doses that appear in the literature fall into two very different bands:
| Context | Typical dose | Notes |
|---|---|---|
| Therapeutic (Russia/E. Europe) | 0.25–2 g/day | Divided doses; the range at which the 2020 safety review found adverse events in ~5.7% 6Reference 6Systematic reviewSafety and tolerability of the anxiolytic and nootropic drug phenibut — systematic reviewView study → |
| Reported supplement use | 250–1000 mg per dose | Drawn from case literature and user reports, not validated dosing |
| Misuse / case reports | 0.5–100 g/day | The range from which nearly all dependence, intoxication and hospitalisation reports arise 6Reference 6Systematic reviewSafety and tolerability of the anxiolytic and nootropic drug phenibut — systematic reviewView study → |
Onset is slow (2–4 hours), which tempts re-dosing before the first dose is felt — a common route into escalation. Tolerance builds quickly with daily use, and the gap between an effective dose and a sedating-overdose or dependence-inducing dose is narrow because the drug is a low-potency GABA-B agonist (it takes gram quantities to act) 10,
Safety
Phenibut’s safety profile is the reason it belongs in the “handle with caution” category rather than the supplement aisle. The dominant, best-evidenced findings are its liability, not its benefit.
- Physical dependence and severe withdrawal. Daily gram-level use produces dependence; abrupt cessation can escalate from rebound anxiety and insomnia to agitation, hallucinations, psychosis, delirium, seizures and autonomic instability, sometimes needing intensive care 2,
4, .5, 12, 18Reference 2ReviewPhenibut: review and pharmacologic approaches to treating withdrawal — reviewView study →Reference 4Systematic reviewClinical presentations and treatment of phenibut toxicity and withdrawal — systematic reviewView study →Reference 5Systematic reviewA systematic review of phenibut withdrawal focusing on complications, therapy and outcomes — systematic reviewView study →Reference 12Systematic reviewA systematic review of phenibut withdrawals — systematic reviewView study →Reference 18Case reportAcute phenibut withdrawal: a comprehensive literature review and illustrative case report — review/case reportView study → - Acute intoxication / overdose — altered mental status, profound somnolence or coma, agitated delirium; one systematic review found ~49% of toxicity cases required intubation 4Reference 4Systematic reviewClinical presentations and treatment of phenibut toxicity and withdrawal — systematic reviewView study →. Poison-centre calls have risen sharply over the last decade 13,
14Reference 13ObservationalPhenibut exposures and clinical effects reported to a regional poison center — observational studyView study →Reference 14Phenibut (4-amino-3-phenyl-butyric acid): availability, prevalence of use, desired effects and acute toxicityView study → . - Do not combine with CNS depressants — additive with alcohol, benzodiazepines, opioids and gabapentinoids (baclofen, gabapentin, pregabalin); these combinations recur in the serious-outcome reports 2,
4Reference 2ReviewPhenibut: review and pharmacologic approaches to treating withdrawal — reviewView study →Reference 4Systematic reviewClinical presentations and treatment of phenibut toxicity and withdrawal — systematic reviewView study → . - Avoid in pregnancy and lactation — neonatal withdrawal reported; see the box below.
- Efficacy is weak/observational while harm is systematic-review-grade — the risk–benefit is lopsided.
- Product quality is unreliable — independent assays show label amounts variously at 0 mg or 250–500 mg per serving, before and after FDA warnings 15Reference 15Quantity of phenibut in dietary supplements before and after FDA warningsView study →.
Full Safety & Interactions Detail
- Dependence & withdrawal (dose-limiting). Regular use — especially daily and at gram-level doses — produces physical dependence. Abrupt cessation can trigger a withdrawal syndrome ranging from rebound anxiety and insomnia to agitation, hallucinations, psychosis, delirium, seizures and autonomic instability, sometimes requiring intensive care 2,
4, . Across systematic reviews, cases skew heavily male (≈80–100%), median age ~30, with frequent concurrent substance use 4,5, 12, 18Reference 2ReviewPhenibut: review and pharmacologic approaches to treating withdrawal — reviewView study →Reference 4Systematic reviewClinical presentations and treatment of phenibut toxicity and withdrawal — systematic reviewView study →Reference 5Systematic reviewA systematic review of phenibut withdrawal focusing on complications, therapy and outcomes — systematic reviewView study →Reference 12Systematic reviewA systematic review of phenibut withdrawals — systematic reviewView study →Reference 18Case reportAcute phenibut withdrawal: a comprehensive literature review and illustrative case report — review/case reportView study → 5, . Management typically uses baclofen, benzodiazepine or phenobarbital tapers 2Reference 2ReviewPhenibut: review and pharmacologic approaches to treating withdrawal — reviewView study →.12Reference 4Systematic reviewClinical presentations and treatment of phenibut toxicity and withdrawal — systematic reviewView study →Reference 5Systematic reviewA systematic review of phenibut withdrawal focusing on complications, therapy and outcomes — systematic reviewView study →Reference 12Systematic reviewA systematic review of phenibut withdrawals — systematic reviewView study → - Acute intoxication / overdose. Presentations include altered mental status, profound somnolence or coma, psychosis, agitated delirium and movement disorders; in one systematic review ~49% of toxicity cases required intubation 4Reference 4Systematic reviewClinical presentations and treatment of phenibut toxicity and withdrawal — systematic reviewView study →. Poison-centre data show sharply rising exposure calls over the last decade 13,
14Reference 13ObservationalPhenibut exposures and clinical effects reported to a regional poison center — observational studyView study →Reference 14Phenibut (4-amino-3-phenyl-butyric acid): availability, prevalence of use, desired effects and acute toxicityView study → . - Interactions. Additive CNS depression with alcohol, benzodiazepines, opioids, gabapentinoids (baclofen, gabapentin, pregabalin) and other sedatives — combinations that recur in the serious-outcome case reports 2,
4Reference 2ReviewPhenibut: review and pharmacologic approaches to treating withdrawal — reviewView study →Reference 4Systematic reviewClinical presentations and treatment of phenibut toxicity and withdrawal — systematic reviewView study → . It should not be combined with these. - Who should avoid it. Anyone with a history of substance use disorder (the most common background in withdrawal cases), and — given renal excretion — caution is warranted in renal impairment. It is not an approved dietary supplement in most countries.
Scope disclosure (honesty statement, not a claim): interactions were assessed — CNS depressants (alcohol, benzodiazepines, opioids, gabapentinoids, other sedatives) are contraindicated combinations. Pregnancy/lactation were assessed — no adequate data, and neonatal withdrawal has been reported, so the verdict is avoid. No Upper Limit exists, and that absence does not mean higher doses are safe: the harm literature clusters precisely at high, repeated doses. Never infer safety from an absence of reports — phenibut’s low-dose tolerability in Russian practice does not transfer to unregulated, self-titrated gram-level supplement use.
Avoid. There are no adequate safety data in pregnancy or lactation, and neonatal phenibut withdrawal has been reported after maternal use — a clear signal that it crosses the placenta and causes dependence in the fetus. Do not use while pregnant or breastfeeding.
Related compounds
- GABA — the parent neurotransmitter phenibut is modelled on; unlike GABA, phenibut crosses the blood–brain barrier.
- Baclofen — the p-chloro derivative of phenibut, a licensed GABA-B agonist and the drug most often used to manage phenibut withdrawal.
- Gabapentin / pregabalin — share the α2δ calcium-channel binding site, so gabapentinoid cross-tolerance and combined CNS depression are relevant.
- F-phenibut — a more potent fluorinated analogue also sold online, with correspondingly greater intoxication risk 19Reference 19F-phenibut (β-(4-fluorophenyl)-GABA), a potent GABA-B receptor agonist — comparative studyView study →.
References
- Gurley BJ, Koturbash I (2024). Phenibut: a drug with one too many “buts” — review. Basic Clin Pharmacol Toxicol. https://pubmed.ncbi.nlm.nih.gov/39197876/
- Penzak SR, et al. (2024). Phenibut: review and pharmacologic approaches to treating withdrawal — review. J Clin Pharmacol. https://pubmed.ncbi.nlm.nih.gov/38339875/
- Jouney EA (2019). Phenibut (β-phenyl-γ-aminobutyric acid): an easily obtainable “dietary supplement” with propensities for physical dependence and addiction — review. Curr Psychiatry Rep. https://pubmed.ncbi.nlm.nih.gov/30852710/
- Weleff J, et al. (2023). Clinical presentations and treatment of phenibut toxicity and withdrawal — systematic review. J Addict Med. https://pubmed.ncbi.nlm.nih.gov/37579098/
- Feldman R, et al. (2023). A systematic review of phenibut withdrawal focusing on complications, therapy and outcomes — systematic review. Clin Toxicol (Phila). https://pubmed.ncbi.nlm.nih.gov/38112312/
- Kupats E, et al. (2020). Safety and tolerability of the anxiolytic and nootropic drug phenibut — systematic review. Pharmacopsychiatry. https://pubmed.ncbi.nlm.nih.gov/32340063/
- Tērauds E, et al. (2025). Efficacy of Noofen 250 mg capsules for the management of anxious-neurotic symptoms in adjustment disorder — observational study. J Clin Med. https://pubmed.ncbi.nlm.nih.gov/40807194/
- Vorob’eva OV, et al. (2016). Pharmacotherapy of anxiety disorders in patients with chronic cerebral ischaemia — randomized trial. Zh Nevrol Psikhiatr Im S S Korsakova. https://pubmed.ncbi.nlm.nih.gov/28300804/
- Lapin I (2001). Phenibut (beta-phenyl-GABA): a tranquilizer and nootropic drug — review. CNS Drug Rev. https://pubmed.ncbi.nlm.nih.gov/11830761/
- Zvejniece L, et al. (2015). R-phenibut binds to the α2-δ subunit of voltage-dependent calcium channels and exerts gabapentin-like anti-nociceptive effects — in vitro/animal study. Pharmacol Biochem Behav. https://pubmed.ncbi.nlm.nih.gov/26234470/
- Dambrova M, et al. (2008). Comparative pharmacological activity of optical isomers of phenibut — comparative study. Eur J Pharmacol. https://pubmed.ncbi.nlm.nih.gov/18275958/
- Stewart C, et al. (2024). A systematic review of phenibut withdrawals — systematic review. Cureus. https://pubmed.ncbi.nlm.nih.gov/39376891/
- McCabe DJ, et al. (2019). Phenibut exposures and clinical effects reported to a regional poison center — observational study. Am J Emerg Med. https://pubmed.ncbi.nlm.nih.gov/30878413/
- Owen DR, et al. (2016). Phenibut (4-amino-3-phenyl-butyric acid): availability, prevalence of use, desired effects and acute toxicity. Drug Alcohol Rev. https://pubmed.ncbi.nlm.nih.gov/26693960/
- Cohen PA, et al. (2022). Quantity of phenibut in dietary supplements before and after FDA warnings. Clin Toxicol (Phila). https://pubmed.ncbi.nlm.nih.gov/34550038/
- Shypilova EM, et al. (2017). Preventive treatment of tension headache in children and adolescents — clinical trial. Zh Nevrol Psikhiatr Im S S Korsakova. https://pubmed.ncbi.nlm.nih.gov/28805758/
- Smirnova LA, et al. (2013). Study of the absolute bioavailability of citrocard, a new GABA derivative — animal study. Bull Exp Biol Med. https://pubmed.ncbi.nlm.nih.gov/24143367/
- Hardman MI, et al. (2019). Acute phenibut withdrawal: a comprehensive literature review and illustrative case report — review/case report. Bosn J Basic Med Sci. https://pubmed.ncbi.nlm.nih.gov/30501608/
- Irie T, et al. (2020). F-phenibut (β-(4-fluorophenyl)-GABA), a potent GABA-B receptor agonist — comparative study. Eur J Pharmacol. https://pubmed.ncbi.nlm.nih.gov/32735986/



