
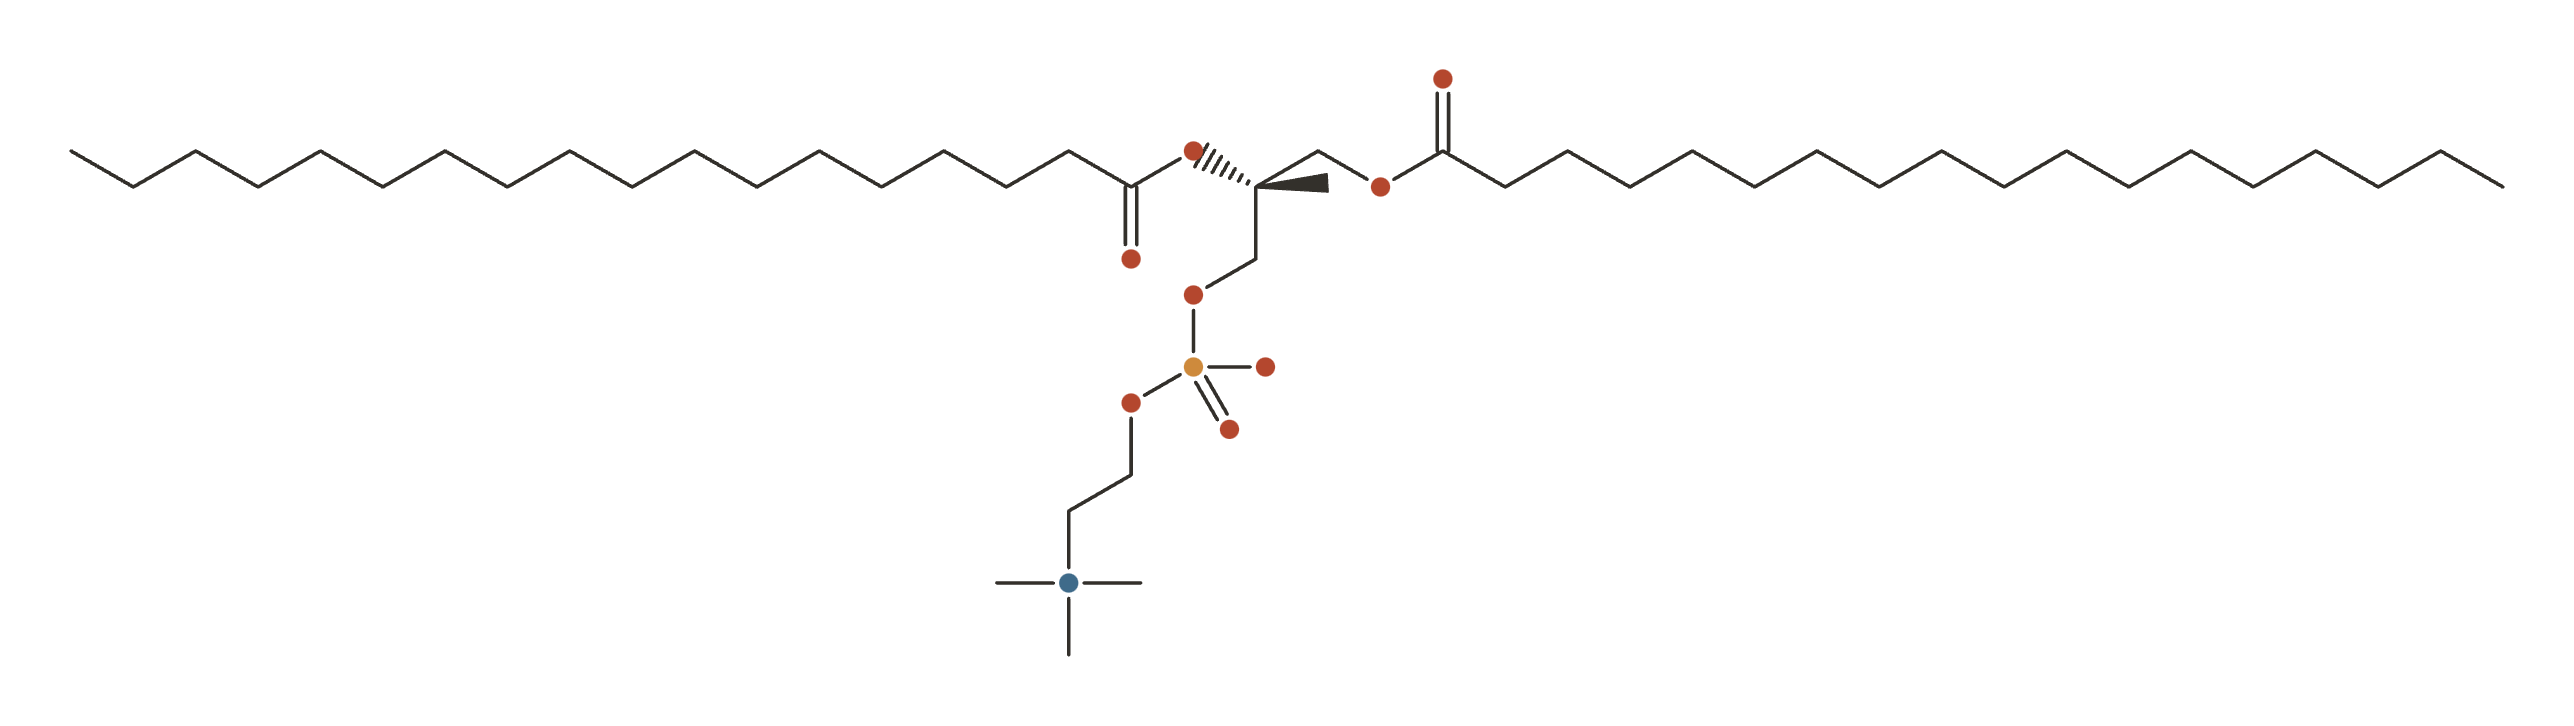
Phosphatidylcholine
The major membrane phospholipid and a dietary source of choline for acetylcholine, membranes, and methyl metabolism.

Phosphatidylcholine at a Glance
Phosphatidylcholine is the most abundant phospholipid in cell membranes and the main form choline takes in food — egg yolk, liver and soy are the richest sources. It is also what most lecithin supplements largely consist of.
It serves two purposes at once: a structural membrane component, and the body’s principal reservoir of choline for making acetylcholine. Its most established medical use is in the liver, which depends on it to package and export fat.
What It’s Used For
- Choline repletion & liver support — restores choline status and supports liver fat export.
- Alcoholic / NAFLD liver disease (PPC) — polyenylphosphatidylcholine used in fatty liver disease.
- Ulcerative colitis (delayed-release PC) — a delayed-release form used to restore the colonic mucus barrier.
- Prenatal neurodevelopment — supports fetal brain development in pregnancy.
How It Works
The liver cannot export fat without phosphatidylcholine: triglycerides leave hepatocytes packaged in VLDL particles whose outer shell is built from it. When choline runs short, that export stalls and fat accumulates — which is why choline deficiency produces fatty liver, and why the liver indications are the best-established ones.
In the colon, phosphatidylcholine is a structural component of the protective mucus layer, and the delayed-release form exists to deliver it past the small intestine to where that layer is thin in ulcerative colitis. Elsewhere it is hydrolysed to free choline, feeding acetylcholine synthesis and the methyl-donor pathway through betaine.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Phosphatidylcholine (PC) is the most abundant glycerophospholipid in animal cell membranes and the principal choline-bearing component of dietary lecithin. As a supplement it does two distinct jobs, and the evidence tracks each separately: it is a dietary source of choline — the essential nutrient the body uses to build acetylcholine, membranes, and methyl donors — and it is a structural phospholipid delivered locally or systemically for tissue repair. The most important interpretive line runs through the difference between correcting a choline deficit (where effects are real and mechanistically grounded) and adding PC on top of an already adequate diet (where benefits are mostly marginal or unproven). Form and delivery dominate: a delayed-release colonic PC and a soybean polyunsaturated PC (PPC) fraction behave nothing like ordinary lecithin capsules, and the biggest, best-controlled trials in both liver disease and ulcerative colitis were negative, tempering an otherwise encouraging small-trial literature.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Choline was formally recognized as an essential nutrient by the US Institute of Medicine in 1998, and PC is the major dietary carrier of it 1Reference 1ReviewCholine: an essential nutrient for public health — [review]View study →.
Controlled human depletion–repletion studies show that when adults are deprived of choline, most men and postmenopausal women develop fatty liver and liver or muscle-cell damage that resolves on repletion; premenopausal women are partly protected because estrogen drives endogenous PC synthesis via the PEMT pathway 14Reference 14ReviewGene response elements, genetic polymorphisms and epigenetics influence the human dietary requirement for choline — [review]View study →.
This is the strongest, most mechanistically secure use — but it is explicitly a repletion effect: it demonstrates that adequate choline (from PC or other sources) is needed, not that extra PC benefits people who already eat enough.
Gap: the benefit is deficiency-dependent; there is no good evidence that supplemental PC improves liver function in choline-replete, otherwise-healthy people.
Colonic mucus in ulcerative colitis is intrinsically depleted of PC, motivating topical repletion with a delayed-intestinal-release formulation. Three single-center, double-blind RCTs from Heidelberg were positive: retarded-release PC at 6 g/day induced clinical remission in 53% vs 10% on placebo (n=60, phase IIA) 4Reference 4RCTRetarded release phosphatidylcholine benefits patients with chronic active ulcerative colitis — [randomised controlled trial]View study →, and 2 g/day enabled steroid withdrawal in 80% vs 10% of steroid-refractory patients 5Reference 5RCTPhosphatidylcholine for steroid-refractory chronic ulcerative colitis — [randomised trial]View study →.
A meta-analysis of three RCTs (160 patients) using a 30%-PC lecithin reported large odds ratios for remission and endoscopic improvement, with a placebo-like adverse-event profile 6Reference 6Meta-analysisDelayed-release phosphatidylcholine is effective for treatment of ulcerative colitis — [meta-analysis]View study →.
Effects were seen with delayed-release, colon-targeted delivery — not ordinary oral lecithin.
Gap: the definitive multicenter LT-02 program was negative — its 12-week induction trial (PCG-2, 466 patients) was terminated early for futility at a prespecified interim analysis, and the separate 48-week maintenance trial (PCG-4, 150 patients) showed no significant remission difference over placebo added to mesalamine 8Reference 8RCTModified-release phosphatidylcholine (LT-02) for ulcerative colitis: two double-blind, randomized, placebo-controlled trials — [randomised controlled trial]View study → — so the earlier single-center signal has not replicated at scale, and PC is not an approved UC therapy.
Choline is essential for fetal brain development, and habitual intakes in pregnancy are frequently below the recommended level. Systematic reviews of the first 1000 days conclude that adequate maternal/child choline supports normal brain development and buffers against insults such as prenatal alcohol 2Reference 2Systematic reviewCholine, neurological development and brain function: a systematic review focusing on the first 1000 days — [systematic review]View study →, and clinical reviews highlight roles in neurodevelopment and reduced neural-tube-defect risk while flagging the gap between habitual intake and recommendations 3Reference 3Systematic reviewCholine in pregnancy and lactation: essential knowledge for clinical practice — [systematic review]View study →.
However, the one direct RCT giving pregnant women 750 mg/day supplemental PC — in women already eating ~360 mg choline/day — found no improvement in infant memory, language, or global development at 10–12 months 15Reference 15RCTPhosphatidylcholine supplementation in pregnant women consuming moderate-choline diets does not enhance infant cognitive function — [randomised controlled trial]View study →.
Gap: the case rests on choline adequacy, not on PC supplementation above adequacy; the direct PC-supplement trial in reasonably-replete women was null, so this is a “meet the requirement,” not “megadose,” story.
Soybean polyenylphosphatidylcholine (PPC) — a polyunsaturated PC fraction (the active in products like “Essentiale”) — has extensive animal and mechanistic support: it downregulates CYP2E1, attenuates oxidative stress and steatosis, shifts Kupffer cells toward an anti-inflammatory phenotype, and prevented alcoholic fibrosis in baboons 16Reference 16ReviewSoybean polyenylphosphatidylcholine (PPC) is beneficial in liver and extrahepatic tissue injury: an update — [review]View study →.
The definitive human test, however, was negative: a 789-patient, 2-year VA Cooperative RCT in heavy drinkers found PPC no better than placebo at preventing progression of liver fibrosis (22.8% vs 20.0% progressed) 9,
Interpretation is complicated because alcohol intake fell sharply in both arms, but the primary endpoint was unambiguously null. Small recent NAFLD trials (often PPC combined with other agents) remain preliminary.
Gap: the strongest human evidence is a large null RCT; enthusiasm rests largely on preclinical models, and no adequately-powered trial shows PPC alters hard liver outcomes in people.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Choline → acetylcholine synthesis | Supplies substrate for cholinergic neurotransmission | Cognition (proposed)cholinergic support |
| Membrane phospholipid pool | Structural component; restores membrane fluidity/integrity | Liver repaircolonic mucus barriercell repair |
| PEMT pathway (hepatic PC synthesis) | Endogenous PC/choline production; estrogen-inducible | Deficiency susceptibilitysex differences |
| Betaine / one-carbon metabolism | Methyl-group donation (homocysteine → methionine) | Methylationfetal development |
| Gut microbiota → TMA → hepatic FMO → TMAO | Pro-atherogenic metabolite from PC’s choline moiety | Cardiovascular risk (adverse) |
| Kupffer-cell / macrophage polarization (PPC) | Shift toward anti-inflammatory M2 phenotype | Experimental liver injury |
Pharmacokinetics
Dietary PC is largely hydrolyzed by pancreatic phospholipase A2 in the gut to lyso-PC and free fatty acids, absorbed, and re-esterified — so much oral PC enters the body as its breakdown products rather than intact PC, and its practical value is often as a choline delivery vehicle (PC is roughly 13% choline by weight). A substantial fraction of the choline released reaches the colon, where gut bacteria generate trimethylamine that the liver oxidizes to TMAO — the basis of the cardiovascular signal below. Therapeutic uses exploit delivery rather than raw dose: delayed/colonic-release formulations keep PC intact to reach inflamed mucosa in UC, while PPC is a defined polyunsaturated fraction, not the mixed-species PC of ordinary lecithin. As with other nutrients, meeting the choline requirement is what matters metabolically; there is no evidence that saturating intake confers extra benefit.
Clinical trials
Registered-trial activity is modest and concentrated in the ulcerative-colitis (LT-02 program) and NAFLD spaces; PC/lecithin is off-patent and generic, so large industry-funded trials are uncommon outside the proprietary delayed-release and PPC formulations. Much of the supporting literature is small, single-center, or preclinical.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~15(UC, liver, cognition, pregnancy) | few | 1(LT-02 UC, futility) | many(PPC liver models) |
Last checked: July 2026.
Dietary Sources
Phosphatidylcholine is present in every cell membrane, so it is abundant across the diet — and because PC carries choline, food PC is a principal way people meet their choline requirement. Eggs, liver and other organ meats, red meat, fish, soybeans, and sunflower are the richest sources; commercial lecithin (used as a food emulsifier and sold as a supplement) is extracted mostly from soy and sunflower. Eggs and meats supply up to ~430 mg choline per 100 g, and a single large egg provides a meaningful share of the daily requirement. Refining and processing (e.g. stripping the germ from grains) lowers phospholipid content, and choline intakes in older children, men, women, and pregnant women are commonly below the IOM Adequate Intake. Absorption of dietary PC is efficient but largely proceeds via hydrolysis to lyso-PC and free choline rather than intact PC.
| Food | Approx. choline (per 100 g) |
|---|---|
| Beef/chicken liver | very high (~300–430 mg) |
| Egg (whole, esp. yolk) | high (~250 mg; ~125 mg per large egg) |
| Soybeans / soy lecithin | moderate–high |
| Red meat, poultry, fish | moderate |
| Sunflower lecithin | moderate (supplement source) |
Values are approximate; see the NIH Office of Dietary Supplements choline fact sheet for a full food list.
Dosage & Intake
There is no RDA or Upper Limit for phosphatidylcholine itself. Because its supplemental rationale is largely as a choline source, the relevant reference values are for choline (IOM Adequate Intake, since data were insufficient for a full RDA): 550 mg/day for men, 425 mg/day for women, 450 mg/day in pregnancy, and 550 mg/day during lactation; the choline Tolerable Upper Intake Level is 3,500 mg/day for adults, set on the basis of hypotension and fishy body odor. PC is roughly 13% choline by weight, so a 1 g PC dose contributes on the order of ~130 mg choline.
Supplemental ranges studied in research (not personal recommendations):
- As a choline source / general use: ~1–2 g PC (lecithin) per day.
- Ulcerative colitis (investigational): 2–6 g/day of a delayed/colonic-release PC formulation — ordinary lecithin capsules do not reproduce this delivery.
- Liver formulations (PPC): ~1.8 g/day of soybean polyenylphosphatidylcholine.
These are doses used in clinical studies, not a personal recommendation; the choline UL counts supplemental intake and is a practical ceiling.
Safety
PC is well tolerated at ordinary supplement doses, and the argument against megadosing is metabolic rather than acute — gut bacteria convert its choline to TMAO, a metabolite tied in observational cohorts to higher cardiovascular risk.
- Well tolerated at typical supplement doses. No major drug-interaction hazard is well established.
- TMAO is the reason not to megadose. Higher dietary PC intake tracks with higher cardiovascular and all-cause mortality in cohort data — observational, but it argues against high habitual intakes.
- High intakes cause GI upset, sweating and a fishy body odor. The choline Upper Limit of 3,500 mg/day is the practical ceiling.
- Stacking choline sources compounds it. Combining PC with racetams or other cholinergics theoretically raises both TMAO and cholinergic side effects.
- Care with anticoagulants or trimethylaminuria. Interaction assessment for PC specifically is limited.
Full Safety & Interactions Detail
PC/lecithin is well tolerated at typical supplement doses. The dose-limiting adverse effects at high intakes are gastrointestinal upset (nausea, diarrhea), sweating, hypersalivation, and a fishy body odor (from trimethylamine) — the same effects that anchor the choline Upper Limit of 3,500 mg/day. The most discussed longer-term consideration is metabolic rather than acute: gut bacteria convert the choline moiety of PC to trimethylamine, which the liver oxidizes to TMAO, a metabolite associated in human cohorts with higher risk of major adverse cardiovascular events and, in one large prospective analysis, higher all-cause and cardiovascular mortality with greater dietary PC intake (HR ~1.11 all-cause, ~1.26 CVD, top vs bottom quintile; stronger in people with diabetes) 11,
This is observational and mechanistic, not proof that PC supplements cause cardiovascular disease, but it argues against high habitual megadosing.
Interactions
No major drug-interaction hazard is well established. As a choline donor, PC is combined with racetam nootropics and other cholinergic agents; theoretically, stacking multiple choline sources raises TMAO and cholinergic side effects. People on anticoagulants or with trimethylaminuria (fish-odor syndrome) should be cautious. Interaction assessment for PC specifically is limited.
Scope of this safety review (for honesty, not a claim):
- Interactions assessed? Partially — cholinergic/choline-donor stacking and TMAO considerations reviewed; comprehensive drug-interaction screening for PC specifically was not performed.
- Pregnancy/lactation assessed? Yes — choline requirements plus the direct PC-supplement RCT summarized above.
- Upper Limit? No UL for PC; the choline UL of 3,500 mg/day applies and should be treated as the practical ceiling. Absence of a PC-specific UL does not imply high intakes are safe.
Verdict: adequate choline intake is important in pregnancy and lactation, but routine high-dose PC supplementation is not established as beneficial. Meeting the choline Adequate Intake (450 mg/day pregnancy, 550 mg/day lactation) supports fetal brain development; however, a randomized trial giving 750 mg/day supplemental PC to women already eating moderate choline showed no infant cognitive benefit 15Reference 15RCTPhosphatidylcholine supplementation in pregnant women consuming moderate-choline diets does not enhance infant cognitive function — [randomised controlled trial]View study →. Food-first choline adequacy is the sound goal; supplement decisions in pregnancy should be individualized with a clinician.
References
- Zeisel, S. H., & da Costa, K.-A. (2009). Choline: an essential nutrient for public health — [review]. Nutrition Reviews. https://pubmed.ncbi.nlm.nih.gov/19906248/
- Derbyshire, E., & Obeid, R. (2020). Choline, neurological development and brain function: a systematic review focusing on the first 1000 days — [systematic review]. Nutrients. https://pubmed.ncbi.nlm.nih.gov/32531929/
- Derbyshire, E., et al. (2025). Choline in pregnancy and lactation: essential knowledge for clinical practice — [systematic review]. Nutrients. https://pubmed.ncbi.nlm.nih.gov/40362867/
- Stremmel, W., et al. (2005). Retarded release phosphatidylcholine benefits patients with chronic active ulcerative colitis — [randomised controlled trial]. Gut. https://pubmed.ncbi.nlm.nih.gov/15951544/
- Stremmel, W., et al. (2007). Phosphatidylcholine for steroid-refractory chronic ulcerative colitis — [randomised trial]. Annals of Internal Medicine. https://pubmed.ncbi.nlm.nih.gov/17975182/
- Review authors (2021). Delayed-release phosphatidylcholine is effective for treatment of ulcerative colitis — [meta-analysis]. Digestive Diseases. https://pubmed.ncbi.nlm.nih.gov/33440385/
- Higgins, J. P. T., & Flicker, L. (2003). Lecithin for dementia and cognitive impairment — [meta-analysis / systematic review]. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/12917896/
- Stremmel, W., et al. (2024). Modified-release phosphatidylcholine (LT-02) for ulcerative colitis: two double-blind, randomized, placebo-controlled trials — [randomised controlled trial]. Clinical Gastroenterology and Hepatology. https://pubmed.ncbi.nlm.nih.gov/37806372/
- Lieber, C. S., et al. (2003). VA Cooperative Study of polyenylphosphatidylcholine in alcoholic liver disease: effects on drinking and liver injury (Part I) — [randomised controlled trial]. Alcoholism: Clinical and Experimental Research. https://pubmed.ncbi.nlm.nih.gov/14634491/
- Lieber, C. S., et al. (2003). VA Cooperative Study of polyenylphosphatidylcholine in alcoholic liver disease (Part II) — [randomised controlled trial]. Alcoholism: Clinical and Experimental Research. https://pubmed.ncbi.nlm.nih.gov/14634492/
- Wang, Z., et al. (2011). Gut flora metabolism of phosphatidylcholine promotes cardiovascular disease — [mechanistic + human]. Nature. https://pubmed.ncbi.nlm.nih.gov/21475195/
- Tang, W. H. W., et al. (2013). Intestinal microbial metabolism of phosphatidylcholine and cardiovascular risk — [cohort]. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/23614584/
- Zheng, Y., et al. (2016). Dietary phosphatidylcholine and risk of all-cause and cardiovascular-specific mortality among US women and men — [cohort]. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/27281307/
- Zeisel, S. H. (2007). Gene response elements, genetic polymorphisms and epigenetics influence the human dietary requirement for choline — [review]. IUBMB Life. https://pubmed.ncbi.nlm.nih.gov/17613168/
- Cheatham, C. L., et al. (2012). Phosphatidylcholine supplementation in pregnant women consuming moderate-choline diets does not enhance infant cognitive function — [randomised controlled trial]. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/23134891/
- Mak, K. M., Shekhar, A. C., et al. (2024). Soybean polyenylphosphatidylcholine (PPC) is beneficial in liver and extrahepatic tissue injury: an update — [review]. The Anatomical Record. https://pubmed.ncbi.nlm.nih.gov/37814787/



