
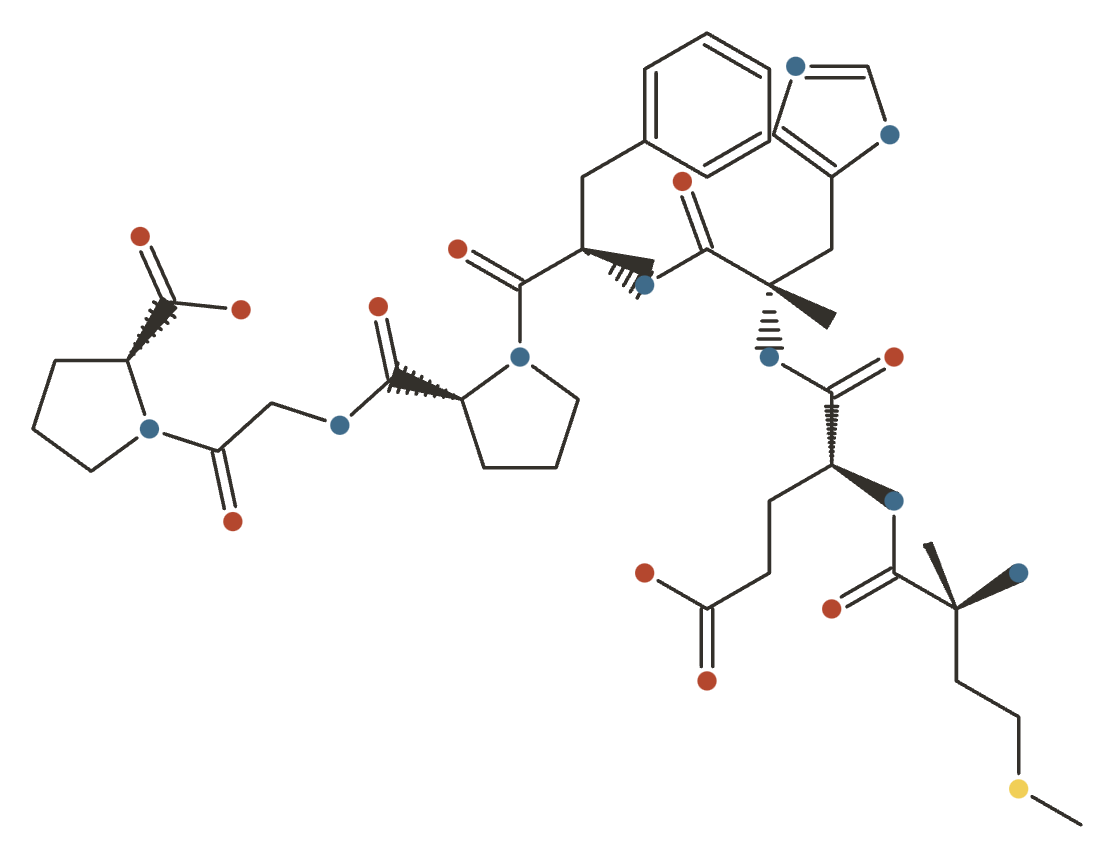
Semax
A synthetic ACTH(4-10)-derived heptapeptide given intranasally as a nootropic/neuroprotective drug.

Semax at a Glance
Semax is a heptapeptide derived from ACTH(4-10) — the fragment of adrenocorticotropic hormone that carries its behavioural effects without its hormonal ones, extended with a proline-glycine-proline tail that protects it from breakdown. It is given intranasally and is a registered medicine in Russia for stroke, cognitive disorders and optic nerve conditions, with no approval elsewhere. Its best-characterised action is raising BDNF, the brain’s main growth factor. Nearly all of its literature is Russian-language.
History & Development
Semax is a fragment of ACTH with the hormonal part removed. What remains is the behavioural effect without the stress-axis one - a Soviet-era design that became a registered Russian medicine.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Not established in the sources consulted for this section |
| Origin | Synthetic heptapeptide Met-Glu-His-Phe-Pro-Gly-Pro (MEHFPGP) - the ACTH(4-7) fragment extended with Pro-Gly-Pro |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Prescription medicine in Russia; unapproved research chemical elsewhere |
Discovery
ACTH drives cortisol release, but fragments of it have effects on attention and memory that are independent of that hormonal action. Semax isolates the second: it takes ACTH(4-7) - four residues carrying the behavioural activity but not the steroidogenic one - and extends it with Pro-Gly-Pro.
That tripeptide tail is the practical invention. Short peptides are destroyed within minutes by plasma exopeptidases; the Pro-Gly-Pro extension resists that degradation, turning a fragment with interesting properties into something that survives long enough to be given as a drug. The same strategy appears in selank.
Development & ownership
Semax is registered in Russia and given intranasally - avoiding both injection and first-pass metabolism, and offering a plausible route toward the brain.
Its principal clinical use is ischaemic stroke, and the Russian protocol is specific: 6,000 µg per day intranasally, in two 10-day courses. It is also prescribed for cognitive and neuroprotective indications.
The literature is almost entirely Russian, much of it not indexed in Western databases and little of it placebo-controlled - which is the reason a compound with a genuine regulatory approval and decades of clinical use still has thin standing outside Russia.
How it reached the market
Semax is prescription-only in Russia and an unregulated research chemical everywhere else. It reaches Western consumers as a nootropic nasal spray, dosed in micrograms per application rather than by the milligram-scale stroke protocol that the clinical evidence describes.
What It's Used For
Semax is a synthetic heptapeptide — Met-Glu-His-Phe-Pro-Gly-Pro (MEHFPGP) — built from the ACTH(4-7) fragment of adrenocorticotropic hormone with a C-terminal Pro-Gly-Pro tail added to slow its breakdown; it carries none of the parent hormone’s steroid-releasing (corticotropic) activity. The evidence base is overwhelmingly preclinical: dozens of rodent and in-vitro studies, most from a small cluster of Russian laboratories, support a brain-derived neurotrophic factor (BDNF)/TrkB mechanism and neuroprotection in stroke, Parkinsonian, and stress models. The strongest human signal is a single Russian clinical trial in ischemic-stroke patients plus a pair of healthy-volunteer brain-imaging studies — there is no FDA/EMA-grade randomized controlled trial, and no trial of Semax is registered on ClinicalTrials.gov. Route is load-bearing: Semax is given intranasally because, like most peptides, its oral bioavailability is negligible, and it is degraded within minutes to the tripeptide Pro-Gly-Pro. It is an approved prescription drug in Russia but an unapproved research chemical everywhere else, so every finding below should be read as “promising in animals, largely unverified in humans.”
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the only application with direct human data. In a Russian clinical trial, 110 post-ischemic-stroke patients (43 men, 67 women, mean age 58) received Semax intranasally (two 10-day courses at 6000 µg/day) during early or late rehabilitation; the peptide raised plasma BDNF, accelerated improvement, and improved final Barthel-index (daily-function) and motor scores versus untreated subgroups 1Reference 1Clinical trialThe efficacy of Semax in the treatment of patients at different stages of ischemic stroke — human clinical trialView study →.
This is a modest, single-center study reported in Russian, not an FDA/EMA registration trial. It sits on a solid rodent foundation: intranasal Semax reduced cortical infarct volume and preserved memory in a rat photothrombotic-ischemia model 2Reference 2AnimalNeuroprotective and antiamnesic effects of Semax during experimental ischemic infarction of the cerebral cortex — animal (rat)View study →, and genome-wide studies in rat middle-cerebral-artery-occlusion brains show Semax predominantly upregulates immune- and vascular-system genes, a proposed neuroprotective route 3,
Gap: No blinded, adequately powered Western RCT and no ClinicalTrials.gov registration; the human evidence is a single Russian trial supported by rodent stroke models.
The mechanistic core of Semax’s “nootropic” reputation is well-replicated in rodents. A single intranasal dose raised hippocampal BDNF protein and TrkB receptor expression and improved conditioned-avoidance learning in rats 5Reference 5AnimalSemax, an analog of ACTH(4-10) with cognitive effects, regulates BDNF and trkB expression in the rat hippocampus — animal (rat)View study →.
Semax binds specifically in rat basal forebrain and raises BDNF there 6Reference 6AnimalSemax, an analogue of adrenocorticotropin (4-10), binds specifically and increases levels of brain-derived neurotrophic factor protein in rat basal forebrain — animal (rat)View study →.
It stimulates BDNF (and NGF) gene expression across multiple rat brain regions in vivo 7,
The human evidence is thin and indirect: in healthy volunteers, a single intranasal 1% dose changed resting-state fMRI networks — expanding the default-mode network’s frontal component 9Reference 9Effects of Semax on the default mode network of the brain — human (fMRI, healthy volunteers)View study → and altering amygdala/prefrontal functional connectivity 10Reference 10Functional connectomic approach to studying Selank and Semax effects — human (fMRI, healthy volunteers)View study →.
These are brain-activity changes in healthy people, not demonstrated cognitive improvement in a clinical population.
Gap: No human cognition-endpoint RCT. The learning/memory effects are rodent-only; the human data show network changes without a measured cognitive outcome.
Semax modulates monoaminergic systems and protects dopaminergic neurons in rodent toxin models only. Daily intranasal Semax (0.2 mg/kg) reduced behavioral deficits in rats lesioned with the Parkinsonism toxin MPTP 11Reference 11AnimalThe neuroprotective effects of Semax in conditions of MPTP-induced lesions of the brain dopaminergic system — animal (rat)View study →.
In a 6-OHDA rat model, by contrast, Semax did not change motor activity or passive-defensive behavior (only the analog Selank reduced anxiety), so the behavioral benefit is model-dependent, not uniform 12Reference 12AnimalPeptides Semax and Selank affect the behavior of rats with 6-OHDA-induced PD-like parkinsonism — animal (rat)View study →.
Mechanistically, Semax raised striatal serotonin turnover and strongly potentiated amphetamine-evoked dopamine release without itself changing baseline dopamine 13,
Gap: Entirely animal (two toxin models, one lab lineage); no human Parkinson’s-disease data of any kind.
Semax shows antidepressant-like and anti-stress effects in rodent models of depression: in a chronic-unpredictable-stress paradigm in male rats, Semax (and the melanocortin agonist Melanotan II) attenuated stress-induced behavioral changes, framed around HPA-axis regulation 15Reference 15AnimalAntidepressant-like and antistress effects of the ACTH(4-10) synthetic analogs Semax and Melanotan II on male rats in a model of chronic unpredictable stress — animal (rat)View study →; an earlier rat study reported similar attenuation of chronic-stress effects 16Reference 16AnimalHeptapeptide Semax attenuates the effects of chronic unpredictable stress in rats — animal (rat)View study →. The only human reference is a case letter suggesting therapeutic possibility for depression 17Reference 17Therapeutic possibility of “Semax” for depression — human case letterView study → — an observation, not a trial.
Gap: Rodent-only efficacy plus a single uncontrolled human letter; no depression trial exists.
A 2025 study reported that Semax improved functional recovery (Basso locomotor scores, footprint and inclined-plane tests) in a mouse spinal-cord-injury model, acting through the µ-opioid-receptor gene Oprm1 to promote deubiquitination and limit lysosomal-membrane-driven neuronal death 18Reference 18AnimalSemax peptide targets the µ-opioid receptor gene Oprm1 to promote deubiquitination and functional recovery after spinal cord injury in female mice — animal (mouse)View study →. This is a mechanistically novel result but a single study, single lab, single species.
Gap: One mouse study, no replication and no human data; the SCI application is at the earliest preclinical stage.
Semax binds Cu(II) with high affinity, and this chemistry has been explored in vitro as an anti-Alzheimer’s angle. In cell-free and cell-based systems Semax strips Cu(II) from the Cu-amyloid-β complex and silences the copper redox cycling that generates reactive oxygen species, protecting SH-SY5Y cells from oxidative stress 19Reference 19In vitroSemax, a copper chelator peptide, decreases the Cu(II)-catalyzed ROS production and cytotoxicity of Aβ by metal ion stripping and redox silencing — in vitroView study →; it also alters copper-induced Aβ aggregation and amyloid formation in artificial-membrane models 20Reference 20In vitroSemax, a synthetic regulatory peptide, affects copper-induced Aβ aggregation and amyloid formation in artificial membrane models — in vitroView study →; and its high Cu(II) affinity and protection against metal-induced cell toxicity are characterized biophysically 21Reference 21In vitroSemax, an ACTH(4-10) peptide analog with high affinity for copper(II) ion and protective ability against metal-induced cell toxicity — in vitroView study →.
Gap: In-vitro/cell-line only. No animal-model or human evidence that copper chelation by Semax translates to any anti-dementia effect in vivo.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| BDNF / TrkB signaling | ↑ BDNF protein & TrkB expression (rodent brain) | Cognitionstrokeneuroprotection |
| NGF / neurotrophin genes | ↑ NGF & BDNF gene expression (rodent, in vivo) | Cognitionneuroprotection |
| Dopaminergic system | Potentiates evoked dopamine release; modulatory, not direct | Parkinsonian modelsnootropic |
| Serotonergic system | ↑ striatal serotonin (5-HIAA) turnover | Moodnootropic |
| Immune / vascular gene networks | ↑ immune- & vascular-system gene expression after ischemia | Stroke neuroprotection |
| Cu(II) chelation / redox silencing | Strips Cu(II) from Cu-Aβ; ↓ ROS | Anti-amyloid (in vitro) |
| µ-opioid receptor (Oprm1) / deubiquitination | Promotes deubiquitination, limits lysosomal-membrane permeabilization | Spinal cord injury (mouse) |
| Antioxidant / anti-toxicant | Counteracts heavy-metal-induced learning deficits (rat) | Neuroprotection |
Pharmacokinetics
Semax is administered intranasally (as a 0.1% or 1% aqueous solution), which is the decision-relevant fact for the whole page: oral dosing is not used because peptides of this size are digested rather than absorbed, and intranasal delivery provides a partial nose-to-brain route. In tritium-labeled rat studies, Semax reaches the brain within ~2 minutes of intranasal dosing, but it is degraded rapidly by peptidases, with the tripeptide Pro-Gly-Pro (PGP) becoming the predominant species in blood and brain — meaning much of the “Semax” effect in vivo may be carried by its PGP metabolite 22,
Clinical & regulatory status
Semax is an approved prescription drug in Russia, where it is included on the state list of Vital and Essential Medicines and marketed for indications such as ischemic-stroke recovery and cognitive/attention disorders (intranasal formulation). It is not approved by the FDA, EMA, or TGA, and it is not a recognized dietary supplement in the US, UK, or EU. A ClinicalTrials.gov search returns no registered Semax trials — the human evidence is confined to Russian-conducted studies (the stroke trial 1Reference 1Clinical trialThe efficacy of Semax in the treatment of patients at different stages of ischemic stroke — human clinical trialView study → and healthy-volunteer imaging studies 9,
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 1(Russian, unregistered) | 0registered | 0 | ~200+(PubMed) |
A US regulatory evaluation is now on the record, and it is pending rather than final. FDA evaluated semax free base and semax acetate for the section 503A Bulk Drug Substances List and, in a briefing document published ahead of the Pharmacy Compounding Advisory Committee meeting of 23–24 July 2026, concluded that a balancing of the criteria weighs against listing either — finding insufficient characterization, unclear compounding history, insufficient evidence of effectiveness, and an uncharacterizable safety profile. The committee has not yet voted and FDA has issued no final determination. Two points bear directly on the counts above: FDA excluded the Russian-language clinical literature (including the Gusev 2018 stroke trial cited here as 1Reference 1Clinical trialThe efficacy of Semax in the treatment of patients at different stages of ischemic stroke — human clinical trialView study →) because no verified English translation was available, so its effectiveness finding rests on only two English-accessible clinical references; and it treats Russia’s registration purely as a fact of foreign marketing — noted, but carrying no weight in the assessment. See Sourcing, Route & Legal Status for the full evaluation.
Last checked: 18 July 2026.
Sourcing, Route & Legal Status
Regulatory status. Semax is a prescription drug in Russia, where it is registered as an intranasal neuropeptide and is included on the Russian state List of Vital and Essential Medicines; it is marketed there for ischemic-stroke recovery and cognitive/attention disorders. It has never been approved by the FDA, EMA, or TGA, is not a recognized dietary supplement in the US, UK, or EU, and no Semax product carries Western marketing authorization. Outside Russia it is sold as an unapproved research chemical — labeled “for research use only / not for human consumption” — which is the legally accurate frame for anyone acquiring it internationally. It is not a scheduled/controlled substance in the US, but “not scheduled” is not “approved”: possession-for-research is a regulatory gray zone, and marketing it for human use is unlawful in most Western jurisdictions.
A US regulator has now assessed Semax — and the assessment is published but not yet final. Semax-related bulk drug substances (semax free base and semax acetate, treated as two chemically distinct substances) were nominated by two compounding pharmacies — LDT Health Solutions and Wells Pharmacy Network — for the section 503A Bulk Drug Substances List, the list of substances US pharmacies may lawfully compound with. Both nominations were withdrawn; FDA elected to evaluate the substances on its own initiative anyway. The proposed uses were cerebral ischemia, migraine and trigeminal neuralgia, in intranasal spray or subcutaneous injection at 1,000 µg/mL or 7,500 µg/mL. (Semax was also nominated for “ADHD” and “nootropic”: FDA declined to evaluate ADHD because “supporting literature for this use was not found,” and folded “nootropic” into the cerebral-ischemia assessment because it has no ICD-10 code and no professional-society guideline.) FDA’s briefing document for the Pharmacy Compounding Advisory Committee meeting of 23–24 July 2026 (signed 11 May 2026) concludes that “a balancing of the criteria weighs against semax (free base) or semax acetate being placed on that list” and proposes not adding either. The committee has not yet voted — FDA states it will not issue a final determination until the advisory-committee process has been considered and all reviews are finalized. FDA found against on all four criteria:
- Not well characterized. Both forms fail on inconsistent naming that does not follow INN/IUPAC/USAN standards — and the nominations demonstrate the risk, since the certificate of analysis submitted was titled for semax acetate while its CAS number, molecular formula and molecular weight all matched the free base. No USP or NF monograph exists for either form; no impurity, aggregate, microbial-bioburden or bacterial-endotoxin testing data was found in the literature or the nominations (endotoxin being a critical control for an injectable). No water-solubility data exists for semax acetate at all. FDA also flagged that no information exists about the nasal-spray container/closure and pump — the components that determine dose delivery — and said it “would have strong concerns” about the proposed nasal-spray product for that reason.
- Historical compounding use unclear, and vanishingly small. No outsourcing facility has reported compounding any semax product since 2019. A Google search identified no pharmacy marketing semax; the one documented instance is a Kentucky compounding pharmacy that made and distributed semax products between 25 October 2018 and 1 April 2020, known through a US Attorney press release about a conviction for unlawful distribution. Meanwhile US wellness clinics and online retailers market semax injections and nasal sprays (and semax/Selank combinations) for anxiety, depression, memory, stroke, diabetic neuropathy, ADHD, opioid withdrawal, ALS, Parkinson’s, Alzheimer’s, optic-nerve atrophy, pain and gastric protection — none of which FDA found evidence for, and none of which state which chemical form they contain.
- Insufficient evidence of effectiveness — for every nominated use. Only two English-accessible clinical references existed, and FDA reports that “the available references demonstrated lack of effectiveness.” For cerebral ischemia the sole reference was a meeting abstract (Cherkasova 2002) with an unstated number of subjects and no clinical endpoints. For migraine and trigeminal neuralgia, a single unblinded, uncontrolled study of 37 adults (Koroleva 1996) found no change in pain, sensory thresholds or evoked potentials in typical trigeminal neuralgia, and its own authors concluded that “semax does not exhibit analgesic activity by itself.” Professional-society guidelines for all three conditions do not mention semax, and FDA-approved treatments exist for each.
- Safety cannot be characterized. See below.
How FDA handled the Russian registration — and the Russian literature. FDA acknowledges the registration as a bare fact and gives it no evidentiary weight. It searched the Russian state medicines register directly and reports, in the same words in both the body and the conclusions, that “Semax is a registered drug in Russia and is available as 0.1% and 1% nasal drops.” That is the entire treatment: the registration does not appear in the balancing, does not offset any of the four adverse findings, and is stated alongside the absence of a semax monograph in the European (11.8), Japanese (18th) and International (12th) Pharmacopoeias, the absence of a USP/NF monograph, and the fact that semax is not a component of any FDA-approved drug. FDA also found “no additional safety information from other regulatory agencies.” More consequential is what FDA did with the Russian literature: it excluded it. The references it located on semax for cerebral ischemia “were articles published in Russian, some of which had English abstracts. Because the full references were not available in English, these references were not considered as part of this evaluation” — citing 21 CFR 10.20(c)(2), which requires a verified English translation. Among the papers excluded on that basis is Gusev et al. 2018 — reference 1Reference 1Clinical trialThe efficacy of Semax in the treatment of patients at different stages of ischemic stroke — human clinical trialView study → here, the single human clinical trial that anchors the stroke application. This page’s standing caveat that the Russian clinical literature cannot be independently verified is therefore not a stylistic hedge: a regulator that ran the systematic search reached the same conclusion and acted on it, and published an effectiveness finding built on the two English-accessible references alone.
What FDA says does not exist. The absences are the most decision-relevant part of the document, because they define the outer edge of what is known about this molecule:
| Data type | FDA’s finding |
|---|---|
| Human pharmacokinetics | ”We were not able to find pharmacokinetic studies in humans following exposure to semax (free base) or semax acetate via any ROA.” |
| Acute toxicity (any species) | None identified |
| Repeat-dose toxicity (any species) | None identified |
| Genotoxicity | None identified |
| Developmental & reproductive toxicity | None identified |
| Carcinogenicity | No 2-year study and no weight-of-evidence analysis. The only relevant work is a single late-life study in tumor-bearing female SHK mice (Meshavkin 2013) in which semax reduced mammary-tumor size and extended mean lifespan by ~68% — which FDA states is “not adequately designed to assess the carcinogenic potential of semax” (one dose, one sex, treatment lasting under 3 months) |
| Subcutaneous route — the route half the nominated products use | No PK study in any species, and no clinical data of any kind; the only route discussed anywhere in the literature is intranasal |
| Immunogenicity / aggregation | No clinical studies; FDA “cannot rule out” immunogenicity from peptide-related impurities and aggregates, a concern it says is heightened by the subcutaneous and nasal routes |
| Abuse potential | No nonclinical study of reinforcing or addictive properties |
Adverse-event reporting. FDA’s Office of Surveillance and Epidemiology searched FAERS through 3 December 2025 and retrieved one report (#25343150): a consumer who reported ocular pain and eye burning in May 2024 after using Semax 0.1% nasal drops purchased online, with hospitalization, and the eye pain still unresolved when she reported it a year later. Two PubMed searches (through 27 February 2024, and 27 February 2024 to 3 December 2025) found no published case reports of adverse events. Total documented human exposure across all eight references FDA identified is 33–47 healthy adults, 69 adults with medical conditions, and 451 children (120 aged 12–14 treated for depression, 331 with tics/Tourette syndrome) — all intranasal; seven of the eight references do not discuss adverse events at all, and in several, semax was given alongside other drugs, making any attribution impossible.
Two safety signals not previously carried. First, bleeding. FDA takes the reported antithrombotic/anticoagulant activity of semax seriously as a risk: rodent work shows increased fibrinolytic activity, raised tissue plasminogen activator and ~35% reduced platelet aggregation, and FDA warns this “raises concern about the risk of bleeding, particularly in certain populations at risk for bleeding or if combined with other medications that increase bleeding risk” — noting that compounded drugs carry no labeling to warn of it. It further observes that semax-treated rats were hypocoagulant relative to unstressed controls, and that with no dose-response data it is unclear whether a dose could be titrated “without creating a condition that could favor the development of a bleeding event.” Second, abuse potential. FDA calls the finding that semax potentiates amphetamine-induced striatal dopamine release “concerning”, explicitly because raised striatal dopaminergic tone “is a response typically induced by drugs of abuse such as cocaine” — and no study of semax’s reinforcing properties exists.
Source: FDA briefing document, Pharmacy Compounding Advisory Committee meeting, 23–24 July 2026 — “Evaluation of Semax-related Bulk Drug Substances for Inclusion on the 503A Bulk Drug Substances List,” signed 11 May 2026. https://www.fda.gov/media/193348/download
How it’s supplied & administered. Pharmaceutical Semax in Russia is an intranasal aqueous solution (commonly 0.1% or 1%), dosed in micrograms per application. Gray-market international material is typically sold as lyophilized (freeze-dried) powder requiring reconstitution — usually with bacteriostatic or sterile water — into a nasal spray or dropper. The intranasal route is not incidental: peptides of this size have negligible oral bioavailability (they are digested), so oral “Semax” products cannot deliver intact peptide, and intranasal dosing is used to exploit partial nose-to-brain transfer. Lyophilized peptide is generally stored refrigerated/frozen and is unstable in solution; reconstituted material has a short shelf life.
Sourcing reality (this is a safety issue, not a footnote). International Semax comes from unregulated vendors with no manufacturing oversight. There is no assurance of identity, purity, correct sequence, or absence of bacterial endotoxin, and mislabeled or under-/over-concentrated product is a documented risk across the research-peptide market. Because dosing is in micrograms and the product is self-reconstituted, small errors in concentration or contamination during handling carry real risk. Third-party certificates of analysis (COAs) — independent HPLC identity/purity and endotoxin testing — are the only partial mitigation, and even those can be falsified. This page does not recommend or link vendors; the honest position is that gray-market peptide identity and purity cannot be assumed.
Safety
Documented human safety data are limited to a small Russian clinical literature and a near-empty Western adverse-event file, which is not a safety finding — FDA’s own conclusion is that there is insufficient clinical information to characterize the profile. The one substantive signal is bleeding, and it is the reason this is not a neutral unknown.
- Bleeding risk. Rodent anticoagulant, fibrinolytic and antiplatelet effects; FDA treats this as genuine, with no dose-response data to say whether any dose avoids it.
- Avoid on anticoagulants or antiplatelet drugs, or with a bleeding disorder. That combination is a reason to avoid Semax, not a footnote.
- Contraindicated in pregnancy and breastfeeding by default. No human or animal reproductive data — see the box below.
- Interactions not assessed. Rodent data suggest potentiation of stimulant, dopaminergic and serotonergic drugs — mechanism reasoning, not a tested finding.
- Route and product risks dominate. Nasal-mucosa irritation, plus sterility failure, endotoxin and dosing error from gray-market lyophilized powder.
- Not for children. The pediatric uses appear only in meeting abstracts reporting no adverse-event data at all.
Full Safety & Interactions Detail
Overall posture. Documented human safety data are limited to the small Russian clinical literature; in the ischemic-stroke trial, intranasal Semax was administered in repeated 10-day courses without a reported serious-adverse-event signal, but that study was not designed or powered as a safety trial. Western pharmacovigilance has now been searched, and it is close to empty: FDA’s FAERS search through 3 December 2025 returned one report — hospitalization for ocular pain and eye burning after online-purchased 0.1% nasal drops, unresolved a year later — and no published case reports. An almost-empty adverse-event file for a substance almost nobody reports using is not a safety finding; FDA’s own conclusion is that there is “insufficient clinical information to characterize the safety profile” (see Sourcing, Route & Legal Status). Where controlled human data are absent, the expected adverse-effect profile is inferred from mechanism and route (labeled as such, not as a finding): as an intranasal peptide with BDNF/monoaminergic activity, plausible effects include local nasal irritation and, theoretically, over-stimulation/agitation or headache — none of these is established from trials.
Dose-limiting / route-specific risks. The dominant practical risks are not classical drug toxicity but delivery and product risks: nasal-mucosa irritation from repeated intranasal dosing; and, for gray-market lyophilized product, contamination and sterility failure during reconstitution, endotoxin exposure, and dosing error from self-mixed concentrations. If sourced or used via injection (off-label to the pharmaceutical intranasal route), injection-site reactions and sterility/contamination risks apply.
Interactions. No controlled human drug-interaction studies exist. A mechanistic caution (not a demonstrated interaction): rodent data show Semax potentiates amphetamine-evoked dopamine release and modulates serotonergic tone, so co-use with stimulants, dopaminergic, or serotonergic drugs is a theoretical interaction worth flagging — this is class/mechanism reasoning, not an assessed interaction. A second, better-grounded caution: bleeding. Rodent studies report anticoagulant, fibrinolytic and antiplatelet effects (raised tissue plasminogen activator, ~35% reduced platelet aggregation), and FDA’s 2026 evaluation treats this as a genuine risk — flagging concern about bleeding “particularly in certain populations at risk for bleeding or if combined with other medications that increase bleeding risk,” and noting that no dose-response data exists to say whether a dose could avoid it. Anyone on anticoagulants or antiplatelet drugs, or with a bleeding disorder, should treat that as a reason to avoid Semax rather than a footnote.
Who should avoid it. Anyone who is pregnant, breastfeeding, or trying to conceive; children (the ADHD/Rett-syndrome ideas are hypothesis only — FDA looked for supporting literature for the ADHD use and found none; the 451 children FDA documents as having received intranasal Semax in Russian practice, for depression and for tics/Tourette syndrome, appear only in meeting abstracts that report no adverse-event data at all); and anyone unwilling to accept an unapproved, unregulated product of unverified purity. Because it is prescription-only where it is approved at all, self-administration outside medical supervision is off-label by definition.
Scope disclosure (honesty, not a claim):
- Human data? Minimal — one Russian ischemic-stroke clinical trial (n=110) and two healthy-volunteer fMRI studies. No FDA/EMA-grade RCT; no dedicated human safety trial.
- Interactions assessed? No. Only mechanism/class-level cautions (stimulant / dopaminergic / serotonergic drugs) are noted, and those are inferred, not tested.
- Pregnancy/lactation assessed? No — no human or animal reproductive data located.
- Long-term safety established? No. There is no long-term human safety data; do not infer safety from the absence of reported harm.
Never imply safety from silence. Where Semax has not been studied — interactions, pregnancy, long-term use, gray-market product purity — the correct statement is “not assessed,” not “safe.”
Not assessed / not established. There are no human pregnancy or lactation data and no animal reproductive-toxicity data in the accessible literature. Treat as contraindicated by default in pregnancy and breastfeeding.
Dosage
There is no established Western human dose for Semax, and none is recommended here. It is not an approved supplement or drug outside Russia, and every figure below is data reported for context, not a personal recommendation — do not read it as a protocol.
The best-documented human regimen comes from the Russian ischemic-stroke trial, where Semax was given intranasally at 6000 µg/day in two 10-day courses during rehabilitation 1Reference 1Clinical trialThe efficacy of Semax in the treatment of patients at different stages of ischemic stroke — human clinical trialView study →. Russian pharmaceutical Semax is supplied as a 0.1% or 1% intranasal solution dosed in micrograms per application; gray-market international use follows the same intranasal, microgram-per-application pattern, but those amounts derive from vendor copy and community practice, not from controlled human dose-finding. There is no validated Western human dose, no established maintenance schedule, and no verified human bioavailability figure to anchor one. Oral “Semax” products cannot deliver intact peptide (see Pharmacokinetics), so any oral dose is pharmacologically inert regardless of the number on the label. This entry is informational only.
References
- Gusev EI, et al. (2018). The efficacy of Semax in the treatment of patients at different stages of ischemic stroke — human clinical trial. Zhurnal Nevrologii i Psikhiatrii imeni S.S. Korsakova. https://pubmed.ncbi.nlm.nih.gov/29798983/
- Romanova GA, et al. (2006). Neuroprotective and antiamnesic effects of Semax during experimental ischemic infarction of the cerebral cortex — animal (rat). Bulletin of Experimental Biology and Medicine. https://pubmed.ncbi.nlm.nih.gov/17603664/
- Medvedeva EV, et al. (2014). The peptide Semax affects the expression of genes related to the immune and vascular systems in rat brain focal ischemia: genome-wide transcriptional analysis — animal (rat). BMC Genomics. https://pubmed.ncbi.nlm.nih.gov/24661604/
- Medvedeva EV, et al. (2017). Semax, an analog of ACTH(4-7), regulates expression of immune response genes during ischemic brain injury in rats — animal (rat). Molecular Genetics and Genomics. https://pubmed.ncbi.nlm.nih.gov/28255762/
- Dolotov OV, et al. (2006). Semax, an analog of ACTH(4-10) with cognitive effects, regulates BDNF and trkB expression in the rat hippocampus — animal (rat). Brain Research. https://pubmed.ncbi.nlm.nih.gov/16996037/
- Dolotov OV, et al. (2006). Semax, an analogue of adrenocorticotropin (4-10), binds specifically and increases levels of brain-derived neurotrophic factor protein in rat basal forebrain — animal (rat). Journal of Neurochemistry. https://pubmed.ncbi.nlm.nih.gov/16635254/
- Dolotov OV, et al. (2003). The heptapeptide Semax stimulates BDNF expression in different areas of the rat brain in vivo — animal (rat). Doklady Biological Sciences. https://pubmed.ncbi.nlm.nih.gov/14556513/
- Agapova TY, et al. (2007). Neurotrophin gene expression in rat brain under the action of Semax, an analogue of ACTH(4-10) — animal (rat). Neuroscience Letters. https://pubmed.ncbi.nlm.nih.gov/17353092/
- Lebedeva IS, et al. (2018). Effects of Semax on the default mode network of the brain — human (fMRI, healthy volunteers). Bulletin of Experimental Biology and Medicine. https://pubmed.ncbi.nlm.nih.gov/30225715/
- Panikratova YR, et al. (2020). Functional connectomic approach to studying Selank and Semax effects — human (fMRI, healthy volunteers). Doklady Biological Sciences. https://pubmed.ncbi.nlm.nih.gov/32342318/
- Levitskaya NG, et al. (2004). The neuroprotective effects of Semax in conditions of MPTP-induced lesions of the brain dopaminergic system — animal (rat). Neuroscience and Behavioral Physiology. https://pubmed.ncbi.nlm.nih.gov/15341218/
- Slominsky PA, et al. (2017). Peptides Semax and Selank affect the behavior of rats with 6-OHDA-induced PD-like parkinsonism — animal (rat). Doklady Biological Sciences. https://pubmed.ncbi.nlm.nih.gov/28702721/
- Eremin KO, et al. (2005). Semax, an ACTH(4-10) analogue with nootropic properties, activates dopaminergic and serotoninergic brain systems in rodents — animal (rodent). Neurochemical Research. https://pubmed.ncbi.nlm.nih.gov/16362768/
- Eremin KO, et al. (2004). Effects of Semax on dopaminergic and serotoninergic systems of the brain — animal (rodent). Doklady Biological Sciences. https://pubmed.ncbi.nlm.nih.gov/15088389/
- Inozemtseva LS, et al. (2024). Antidepressant-like and antistress effects of the ACTH(4-10) synthetic analogs Semax and Melanotan II on male rats in a model of chronic unpredictable stress — animal (rat). European Journal of Pharmacology. https://pubmed.ncbi.nlm.nih.gov/39442746/
- Yatsenko KA, et al. (2013). Heptapeptide Semax attenuates the effects of chronic unpredictable stress in rats — animal (rat). Doklady Biological Sciences. https://pubmed.ncbi.nlm.nih.gov/24385169/
- Pae CU, et al. (2008). Therapeutic possibility of “Semax” for depression — human case letter. CNS Spectrums. https://pubmed.ncbi.nlm.nih.gov/18204410/
- Liu R, et al. (2025). Semax peptide targets the µ-opioid receptor gene Oprm1 to promote deubiquitination and functional recovery after spinal cord injury in female mice — animal (mouse). British Journal of Pharmacology. https://pubmed.ncbi.nlm.nih.gov/40692165/
- Tomasello MF, et al. (2025). Semax, a copper chelator peptide, decreases the Cu(II)-catalyzed ROS production and cytotoxicity of Aβ by metal ion stripping and redox silencing — in vitro. Bioinorganic Chemistry and Applications. https://pubmed.ncbi.nlm.nih.gov/40496623/
- Sciacca MFM, et al. (2022). Semax, a synthetic regulatory peptide, affects copper-induced Aβ aggregation and amyloid formation in artificial membrane models — in vitro. ACS Chemical Neuroscience. https://pubmed.ncbi.nlm.nih.gov/35080861/
- Tabbì G, et al. (2015). Semax, an ACTH(4-10) peptide analog with high affinity for copper(II) ion and protective ability against metal-induced cell toxicity — in vitro. Journal of Inorganic Biochemistry. https://pubmed.ncbi.nlm.nih.gov/25310602/
- Shevchenko KV, et al. (2006). Kinetics of Semax penetration into the brain and blood of rats after its intranasal administration — animal (rat, PK). Russian Journal of Bioorganic Chemistry (Bioorganicheskaia Khimiia). https://pubmed.ncbi.nlm.nih.gov/16523722/
- Shevchenko KV, et al. (2013). Stability of Semax acetyl to proteolysis in various biological media — in vitro / stability. Doklady Biological Sciences. https://pubmed.ncbi.nlm.nih.gov/23652441/
- Levitskaya NG, et al. (2000). Study on the neurotropic activity of the products of Semax enzymatic degradation — animal (rat). Doklady Biological Sciences. https://pubmed.ncbi.nlm.nih.gov/10944712/
- Inozemtsev AN, et al. (2016). Semax prevents learning and memory inhibition by heavy metals — animal (rat). Doklady Biological Sciences. https://pubmed.ncbi.nlm.nih.gov/27411820/
- Tsai SJ, et al. (2007). Semax, an analogue of adrenocorticotropin (4-10), is a potential agent for the treatment of attention-deficit hyperactivity disorder and Rett syndrome — hypothesis / proposal. Medical Hypotheses. https://pubmed.ncbi.nlm.nih.gov/16996699/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.



