
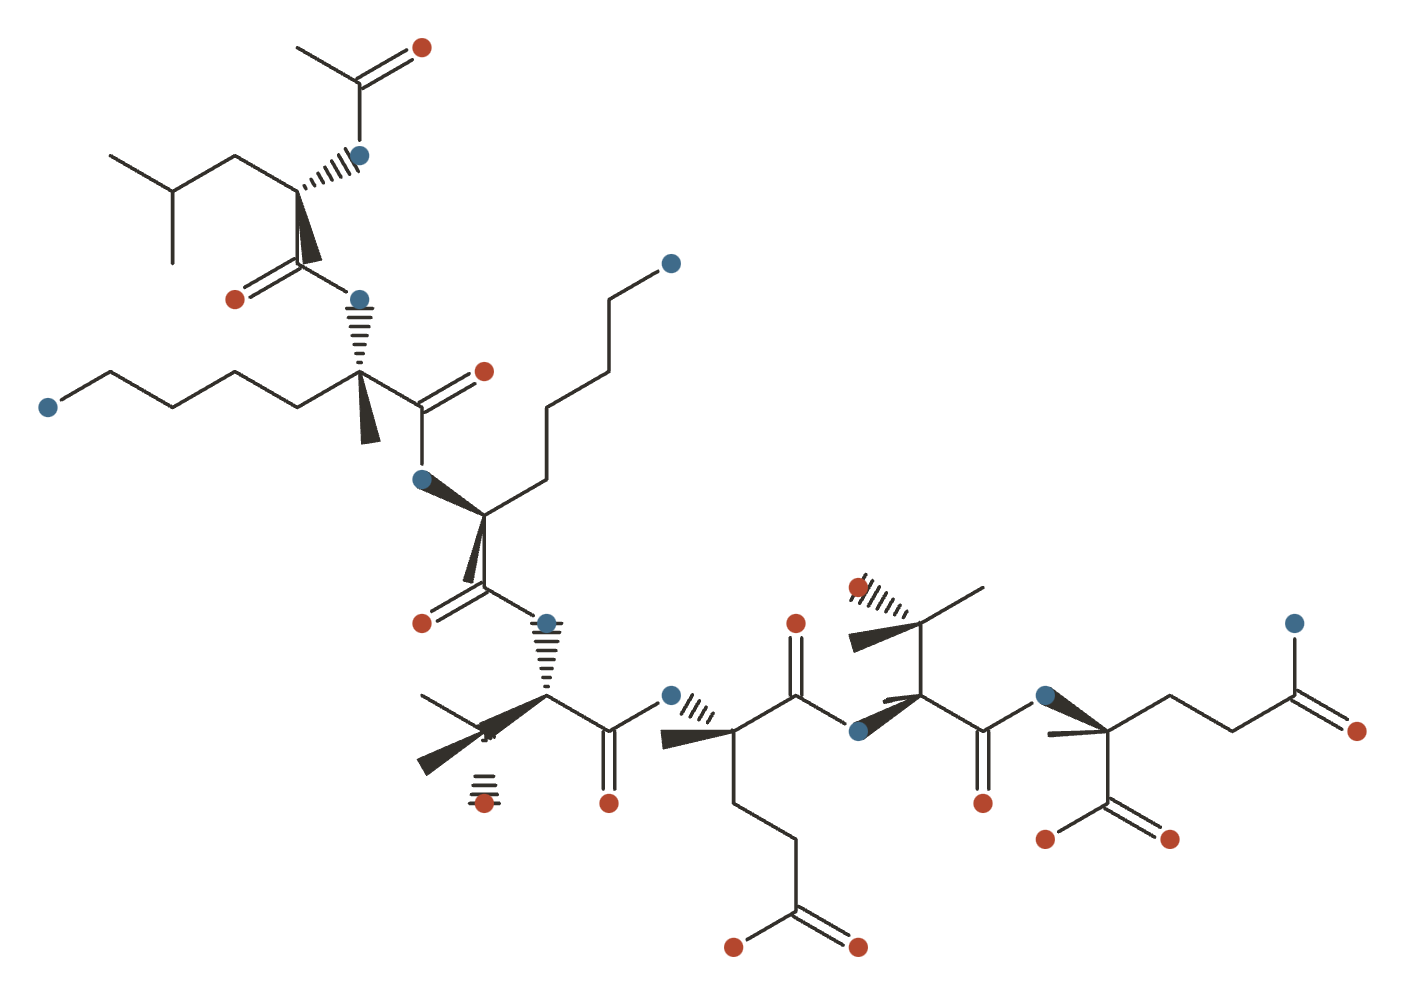
TB-500 (Thymosin β4 fragment)
Ac-LKKTETQ, the synthetic actin-binding fragment of thymosin β4 — an injected research peptide marketed for healing, with no human trial.

TB-500 (Thymosin β4 fragment) at a Glance
TB-500 is Ac-LKKTETQ, a short synthetic fragment of the actin-binding region of thymosin β4. It is sold as an injectable repair peptide, usually alongside BPC-157. The distinction that matters most is the one its name obscures: TB-500 is not thymosin β4 — it is a seven-amino-acid piece of a 43-residue protein, and the clinical development programme belongs to the full protein, not to this fragment. It is an unapproved research chemical and is prohibited in sport.
History & Development
TB-500 is not thymosin beta 4, though it is sold as though it were. It is a seven-amino-acid fragment of it, and the distinction decides which evidence applies.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Not established in the sources consulted for this section |
| Origin | Synthetic N-terminally acetylated heptapeptide Ac-LKKTETQ - residues 17-23 of the 43-residue endogenous protein thymosin beta 4 |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Research chemical - no human trial; never approved anywhere |
Discovery
Thymosin beta 4’s principal function is binding actin, and that activity localises to a short stretch of the molecule. TB-500 is that stretch synthesised alone: Ac-LKKTETQ, the actin-binding “active site,” acetylated at the N-terminus for stability.
The parent has a real clinical programme; the fragment does not. Thymosin beta 4 reached three Phase 3 trials as an ophthalmic solution. TB-500 has no human trial of any kind - and the two are routinely conflated in marketing, so the parent’s trial record is used to sell the fragment.
Development & ownership
There is no development programme. Beyond the absence of human data, the gaps are unusually complete: no toxicology of any kind, in any species, and no human pharmacokinetics. Such PK as exists is equine and subcutaneous - there is no intramuscular data at all, despite that being a common route of use.
It is also prohibited in sport under WADA S2.3, and US federal compounding records show no outsourcing facility has ever reported compounding it - which contradicts the “available from compounding pharmacies” framing the grey market often uses.
How it reached the market
TB-500 originated in veterinary and research supply, particularly around horses, and moved into human use through the injury-recovery market. It is sold for tendon, ligament and muscle repair on the strength of rodent work on the full-length protein - a different molecule, with a different length and a different evidence base.
What It's Used For
TB-500 is a synthetic, N-terminally acetylated seven-amino-acid peptide, Ac-LKKTETQ, corresponding to residues 17–23 of thymosin β4 (Tβ4) — the actin-binding “active site” of that 43-residue endogenous protein. Its identity was established not by a developer but by anti-doping chemists, who isolated and re-synthesized the fragment from marketed TB-500 product 1,
The single most important fact here is a molecular one: TB-500 is the fragment, not the protein — and the literature routinely conflates them. Every human trial in this field (dry-eye, venous ulcer, post-infarction) used full-length Tβ4 or its recombinant forms, developed pharmaceutically as RGN-259 and NL005 6,
No controlled human trial of the TB-500 fragment has ever been completed. A Tβ4 result is therefore not a TB-500 result, and the efficacy case for TB-500 is built almost entirely on animal and in-vitro work on the parent protein plus a mechanistic read-across from the shared LKKTETQ motif 3Reference 3ReviewBiological activities of thymosin beta4 defined by active sites in short peptide sequences — reviewView study →.
Route is load-bearing: like virtually all peptides it is oral-inactive and is injected (SC/IM), and its own pharmacokinetics are unstudied. It is an unapproved research chemical, sold “not for human consumption,” and prohibited in sport. The site’s separate Thymosin Beta-4 entry covers the parent protein, which is where all genuine human evidence lives.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up. Every score here is capped low for the same reason: none of the human or animal efficacy data is for the TB-500 fragment — it is for full-length thymosin β4.
Full-length Tβ4 accelerated closure of full-thickness wounds across multiple rodent models — normal, steroid-treated, diabetic and aged mice and rats, plus burn models — acting through keratinocyte and endothelial migration, angiogenesis and collagen deposition 4,
The human data are two small Phase 2, placebo-controlled trials. The venous-stasis-ulcer study randomized 73 patients across eight European sites to escalating doses of topically applied Tβ4; safety was comparable to placebo, and the 0.03% dose suggested accelerated healing, with complete closure within three months in roughly a quarter of patients — concentrated in those with small-to-moderate ulcers 6Reference 6RCTThe effect of thymosin treatment of venous ulcers — human (RCT, Phase 2, n=73, topical full-length Tβ4)View study →.
A companion pressure-ulcer study is reported in the same review literature 4Reference 4Clinical trialThe regenerative peptide thymosin β4 accelerates the rate of dermal healing in preclinical animal models and in patients — review (animal + Phase 2)View study →.
These are hypothesis-generating Phase 2 signals, not approval-grade efficacy — and critically, every one used the topical 43-residue protein, not the injected TB-500 heptapeptide.
Gap: No human trial and no controlled animal wound study of the TB-500 (17–23) fragment specifically — a point FDA confirms independently, finding no in-vivo pharmacology study of either TB-500 form for wound healing. The one in-vitro test of the fragment was negative (see Sourcing). The human ulcer data belong to a different molecule, delivered by a different route, and showed only a modest dose-dependent signal.
This is the deepest preclinical signal for the parent protein. In mouse myocardial-infarction models, full-length Tβ4 (and prothymosin α) promoted cardiomyocyte survival, epicardial activation, angiogenesis and measurable cardiomyocyte proliferation after injury 7Reference 7AnimalThymosin β4 and prothymosin α promote cardiac regeneration post-ischaemic injury in mice — animal (mouse)View study →.
A 2025 study extended this to recombinant human Tβ4 (rhTB4) in mouse ischemia-reperfusion and permanent-ligation models — preventing cardiac dysfunction and fibrosis, reducing infarct size, and mapping the effect to ErbB2/Raf1 signaling (abolished by ErbB2 inhibition) 8Reference 8RCTRecombinant human thymosin beta 4 improves ischemic cardiac dysfunction in mice and patients with acute ST-segment elevation myocardial infarction after reperfusion — animal (mouse) + human (RCT, n=96; overall endpoint not significant)View study →.
That same paper carried the field’s most substantial human result: a randomized, placebo-controlled, double-blind trial in 96 STEMI patients post-PCI. Read it carefully — the overall comparison of infarct area between rhTB4 and placebo was not statistically significant; only the pre-specified early-dosing subgroup (first dose within 8 hours of PCI, n=43) showed a significant reduction at 90 days 8Reference 8RCTRecombinant human thymosin beta 4 improves ischemic cardiac dysfunction in mice and patients with acute ST-segment elevation myocardial infarction after reperfusion — animal (mouse) + human (RCT, n=96; overall endpoint not significant)View study →.
The authors themselves call for further rigorous trials. Note also that the study was co-authored by employees of the manufacturer.
Gap: Efficacy remains rodent-based; the one human RCT is a full-protein, intravenous, subgroup-positive/overall-null result, not a fragment result. TB-500 has no cardiac data of its own — animal or human.
This is why TB-500 is actually bought — soft-tissue “recovery” and “flexibility” in athletic and gym communities — and it is the weakest-evidenced application on the page. There is no human trial and no dedicated animal tendon- or ligament-injury study of the fragment. The claim rests on three indirect things: the shared actin-binding motif’s established role in cell migration and angiogenesis 3Reference 3ReviewBiological activities of thymosin beta4 defined by active sites in short peptide sequences — reviewView study →; tissue-engineering work loading full-length Tβ4 into electrospun tendon scaffolds, which is materials science rather than injury treatment 18Reference 18In vitroElectrospun thymosin beta-4 loaded PLGA/PLA nanofiber/microfiber hybrid yarns for tendon tissue engineering — in vitro / materialsView study →; and 2026 sports-medicine and orthopedic reviews that catalogue TB-500 precisely as an unapproved, gray-market peptide with no efficacy data — that is, they cite it as a problem, not as a therapy 14,
The most direct in-vivo test of the parent protein points the wrong way: in the study that identified Tβ4 as a human exercise-released factor, treating mice with it did not enhance muscle regeneration and did not improve diet-induced metabolic disruption 9Reference 9In vitroDiscovery of thymosin β4 as a human exerkine and growth factor (no enhancement of muscle regeneration in vivo) — in vitro + animal (mouse)View study →.
Gap: Human evidence is entirely absent. The flagship marketed use is supported only by mechanism and review-level extrapolation, and the closest in-vivo muscle test of the parent protein was negative. Community and vendor testimonials are not evidence and are not scored here.
Full-length Tβ4 stimulates hair growth in rats and mice by activating and mobilizing hair-follicle bulge stem cells and promoting their migration and differentiation 10Reference 10AnimalThymosin beta4 increases hair growth by activation of hair follicle stem cells — animal (rat)View study →; a mouse study replicated the effect and implicated VEGF and MAPK/AKT signaling 11Reference 11AnimalThymosin beta-4 induces mouse hair growth — animal (mouse)View study →. Overexpression and knockout mouse work supports a developmental role in the follicle.
Gap: Entirely rodent-based, and entirely for the full protein. There is no human hair-growth trial of either Tβ4 or the TB-500 fragment, and no topical-versus-injected comparison that would make the route relevant to how TB-500 is actually used.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| G-actin sequestration (LKKTETQ motif — the TB-500 sequence itself) | Buffers monomeric actin; regulates cytoskeletal dynamics and cell migration | The one mechanism genuinely attributable to the fragment |
| Angiogenesis / endothelial & keratinocyte migration | ↑ new vessel formation, ↑ re-epithelialization | Wound healingcardiachair |
| ErbB2 / Raf1 signaling | ↓ cardiomyocyte apoptosis; effect abolished by ErbB2 inhibition (mouse) | Cardiac repair |
| Anti-inflammatory / anti-fibrotic via the Ac-SDKP metabolite | ↓ inflammatory infiltrate, ↓ TGF-β-driven fibrosis | Cardiacrenaldermal — but this maps to the N-terminal Ac-SDKP sitea different fragment of Tβ4not to the 17–23 TB-500 sequence |
| Hair-follicle stem-cell activation (VEGF, P38/ERK/AKT) | ↑ follicle stem-cell migration & differentiation | Hair growth (rodent) |
The anti-fibrotic row is worth dwelling on, because it is the most common way TB-500 marketing overstates itself: a large share of Tβ4’s anti-inflammatory reputation traces to Ac-SDKP, the tetrapeptide released from the protein’s N-terminus 16,
Pharmacokinetics
TB-500 is supplied as a lyophilized powder requiring reconstitution and is given by subcutaneous or intramuscular injection. Oral dosing is not viable: gut proteases and near-zero oral bioavailability apply to peptides of this size, so any oral “TB-500” product is pharmacologically inert regardless of the label. The pharmacokinetics of Ac-LKKTETQ itself are essentially unstudied — there are no published human PK data for the fragment, and no verified human half-life, bioavailability, or tissue-distribution figure. The only in-vivo PK of the fragment itself is equine and incidental to doping detection: thoroughbred geldings given 10 mg SC reached plasma concentrations of just 0.05–0.08 ng/mL at 60–120 minutes, falling below quantification by 6–10 hours; because no intravenous arm was run, absolute bioavailability could not be established, and FDA notes no PK study exists by the intramuscular route at all — one of the two routes TB-500 is actually injected by. Metabolism is sequential C-terminal trimming to N-acetylated LKKTET, LKKTE, LKKT, LKK and LK, confirmed in equine liver, rat urine, and human serum, liver and kidney preparations. What else exists belongs to the parent protein: a first-in-human Phase 1 study of recombinant human Tβ4 (NL005) gave single and multiple intravenous doses of 0.05–25 µg/kg to healthy volunteers, reporting good tolerability, dose-proportional exposure and a plasma half-life on the order of hours 13Reference 13RCTA first-in-human, randomized, double-blind, single- and multiple-dose, phase I study of recombinant human thymosin β4 in healthy volunteers (NL005) — human (RCT, Phase 1, IV PK, full-length Tβ4)View study →. Small linear peptides such as Ac-LKKTETQ would be expected to be cleared and proteolysed rapidly; the N-terminal acetylation is a stability modification, not a depot mechanism. Reconstituted-peptide stability, sterility and actual concentration depend entirely on unregulated vendor quality (see Sourcing). Anti-doping laboratories have published LC-MS methods that detect the intact fragment and its metabolites in human and equine urine and plasma — indirect evidence that it survives injection in measurable form, and the reason it is testable in sport 1,
Clinical & regulatory status
TB-500 is an unapproved research chemical: not approved by the FDA, EMA, TGA, PMDA or any other major regulator as a drug or a dietary supplement, sold labeled “for research use only / not for human consumption.” FDA has evaluated it directly for pharmacy compounding and proposes rejecting it: the agency’s briefing document for the 23–24 July 2026 Pharmacy Compounding Advisory Committee meeting concludes that the criteria weigh against placing TB-500 (free base) or TB-500 acetate on the section 503A bulk-substances list, finding against on characterization, historical use, effectiveness and safety alike. That evaluation was published ahead of the meeting; the committee has not yet voted and no final determination has issued — see Sourcing, Route & Legal Status for the detail, including FDA’s own finding that all three references submitted in support of the TB-500 nomination were studies of thymosin β4 rather than of TB-500. It is prohibited in sport — thymosin β4 and its active fragments fall under the World Anti-Doping Agency’s prohibited list (S2, growth factors), a category banned at all times, in and out of competition; TB-500 has been the specific subject of published doping-detection method development in both human and equine samples 1,
No registered human trial of the TB-500 fragment has been completed. One recruiting ClinicalTrials.gov record (NCT07487363, “TB-500 (Thymosin Beta 4 17-23 Fragment) for Cardiovascular Biomarkers in Stable ASCVD”) exists, but its own brief summary states in its opening line that it is a fictional example record; I verified this directly against the ClinicalTrials.gov API in July 2026. It carries no evidentiary weight and should not be read as a fragment trial — it is flagged here specifically so a future reader does not mistake it for one. Every genuine registered trial counted below is for full-length thymosin β4 / RGN-259 / NL005, a distinct molecule: dry-eye and neurotrophic-keratopathy Phase 2/3, venous-stasis and pressure-ulcer Phase 2, acute-MI Phase 2, and healthy-volunteer Phase 1 PK, with several Phase 1–2 records withdrawn or terminated.
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 11(full protein only) | 2(full protein only) | 4(withdrawn/terminated, full protein) | Dozens for the protein; fragment: identity/mechanism work only |
Last checked: 18 July 2026.
Sourcing, Route & Legal Status
Regulatory status. TB-500 has no marketing approval from any major regulator — FDA, EMA, TGA, PMDA — as either a drug or a dietary supplement, and it is not a lawful dietary-supplement ingredient in the US, UK or EU. It is sold as a research chemical labeled “not for human consumption,” which is the legally accurate frame for anyone acquiring it. It is not a scheduled/controlled substance in the US, but “not scheduled” is not “approved”: marketing it for human use is unlawful in most Western jurisdictions. Regulatory status does not transfer from the parent protein — full-length Tβ4’s investigational program (RGN-259, NL005) gives TB-500 no standing whatsoever.
FDA has now evaluated TB-500 directly — and independently reached the same conclusion. In FDA’s briefing document for the Pharmacy Compounding Advisory Committee meeting of 23–24 July 2026, the agency evaluated TB-500 (free base) and TB-500 acetate — treated as two chemically distinct bulk drug substances — for the section 503A list of substances pharmacies may compound from. Its conclusion: “a balancing of the criteria weighs against TB-500 (free base) and TB-500 acetate being placed on that list.” FDA found against on all four criteria — characterization, historical use in compounding, effectiveness, and safety — and proposes not adding either substance. Read this as pending, not settled: the document was published ahead of the meeting, the committee has not yet voted, and FDA states explicitly that it will not issue a final determination until the advisory-committee process is complete and all reviews are finalized. The original nomination (Wells Pharmacy Network, for a 3 mg/mL lyophilized powder for SC/IM injection in wound healing) was withdrawn; FDA continued the evaluation on its own initiative.
The fragment-versus-protein substitution, documented by a regulator. This is the finding that matters most here, because it is the central point. FDA states in a footnote that websites “state that TB-500 is a synthetic version of thymosin beta-4 and often use the terms interchangeably. However… thymosin beta-4 and TB-500 are not the same substance.” And it records what the nomination actually contained: the nominator cited three references in support of the TB-500 nomination, and all three are studies of thymosin β4, not of TB-500 — “none of the articles discussed the use of a compounded formulation of TB-500,” and none was a study of TB-500 administered in humans. FDA goes a step finer: two of those three (Philp 2003, Shah 2018) tested the non-acetylated heptapeptide LKKTETQ, and because acetylation “irreversibly alters” a peptide’s charge, hydrophobicity and size, FDA holds that “the pharmacological profile of the non-acetylated heptapeptide LKKTETQ cannot be directly extrapolated to the N-acetylated heptapeptide TB-500.” So there are three distinct molecules in play — the 43-residue protein, the bare heptapeptide, and the acetylated heptapeptide actually sold as TB-500 — and the evidence attaches to the first two.
What FDA searched for and did not find. “After conducting a literature search, no articles were found in which TB-500 was administered to humans.” No clinical studies or human exposure data by any route; no human PK or PD; and, in animals, no acute toxicity, no repeat-dose toxicity, no genotoxicity, no developmental or reproductive toxicity, and no carcinogenicity study — none submitted, none identified, in any species. A FAERS search through 26 March 2025 returned zero reports. The Human Foods Complaint System, searched 1 January 2004 – 10 March 2025, returned two cases, both for a “blended TB-500 and BPC-157” product and neither containing a safety assessment. No outsourcing facility has ever reported compounding a TB-500 product to FDA, and FDA found no pharmacy marketing one — so the “compounding pharmacy” framing used by some sellers is unsupported. There is no USP/NF monograph, no European or Japanese Pharmacopoeia recognition, no EMA authorization, and no approved product in Canada, Australia, the UK, Belgium, Ireland, France, Norway, Germany, Spain or Italy.
FDA also found the one fragment-specific efficacy test — and it was negative. With no in-vivo pharmacology study of the fragment in existence, the closest datapoint is an in-vitro scratch-wound assay in which TB-500 (free base) at 50 µg/mL did not close fibroblast wounds any better than vehicle, while its metabolite N-acetylated LKKTE produced a small but significant effect (Rahaman et al. 2024). FDA’s summary is that “nonclinical pharmacological evidence is currently lacking to support the potential for TB-500 to promote wound healing.”
Quality and identity — the sourcing problem, in a regulator’s words. FDA concluded that neither TB-500 (free base) nor TB-500 acetate is “physically and chemically well characterized.” TB-500 is a common name, not a USAN or INN, and FDA reports encountering “multiple salts, and derivatives, including different active moieties, sold commercially under the same common name” — a patient-safety risk, since a buyer may receive a different substance than intended. Supplier sites reuse the free-base CAS number (885340-08-9) for the acetate salt; the nomination package itself gave a molecular formula and an “AKA CAS #” that matched neither form, and attached a certificate of analysis for the acetate to a nomination naming the free base. The publicly available CoAs FDA examined test appearance, identity and purity but do not control impurities, aggregates, microbiological quality, or bacterial endotoxin — the last of which matters directly because the product is injected. On that basis FDA states it “cannot rule out the potential for immunogenicity” from peptide-related impurities and aggregates, and notes that injectable routes present a particular immunogenicity risk. FDA confirms TB-500 is prohibited in sport under WADA section S2.3, and cites forum analysis finding it among the two most-discussed peptides in doping communities.
Banned in sport — state this plainly. Thymosin β4 and its active fragments sit under WADA’s prohibited list as S2 growth factors — FDA cites TB-500 specifically under section S2.3 — prohibited at all times, in and out of competition. Detection is not theoretical: validated LC-MS methods for Ac-LKKTETQ and its metabolites in urine and plasma have been published since 2012 1,
How it’s supplied & administered. Vials of lyophilized (freeze-dried) powder, reconstituted by the user with bacteriostatic or sterile water and injected subcutaneously or intramuscularly. Oral routes do not deliver intact peptide. Reconstituted material is chemically unstable over time and is typically refrigerated; the N-terminal acetylation improves the parent peptide’s proteolytic stability but says nothing about the finished product’s quality.
Sourcing reality (this is a safety issue, not a footnote). Because TB-500 is unapproved, it is supplied entirely by unregulated vendors with no manufacturing oversight. Identity, actual peptide content, correct sequence, and freedom from bacterial endotoxin are not guaranteed; mislabeling, under- and over-concentration, endotoxin contamination and non-sterile fill are documented risks across the research-peptide market — and every one of them is amplified because this product is injected rather than swallowed. Third-party certificates of analysis (independent HPLC identity/purity plus endotoxin testing) are a partial mitigation and can themselves be falsified. No independent assay of marketed TB-500 product purity was located in this pass. This page does not recommend, rank, or link any vendor.
Safety
Human safety data for the TB-500 fragment do not exist — and that is a genuinely empty file, not a clean one. There is no completed controlled human trial, zero FAERS reports, and no toxicology study in any species by any route, so the honest statement is “unknown,” not “well tolerated.”
- Nothing has been measured. No acute, repeat-dose, genotoxicity, reproductive or carcinogenicity study of TB-500 exists in any species.
- Pro-angiogenic mechanism is a cancer caution. The biology that supports wound repair could in principle support unwanted tissue or vascular growth.
- Contraindicated in pregnancy and breastfeeding by default. No reproductive data — see the box below.
- Product and technique are the dominant real-world hazard. Non-sterile vials, endotoxin, injection-site abscess, and dosing error from self-reconstituted powder.
- Interactions not assessed for any drug class. And none should be inferred from the parent protein.
- Bannable in sport. Anyone subject to anti-doping testing should avoid it.
Full Safety & Interactions Detail
Human safety data for the TB-500 fragment do not exist. No completed controlled human trial of Ac-LKKTETQ means its adverse-effect profile, dose-limiting toxicity, and interaction risks in people are genuinely unknown — not “well tolerated,” which is a finding, not a default. FDA’s 2026 review makes this concrete rather than rhetorical: zero FAERS reports through 26 March 2025, and no acute, repeat-dose, genotoxicity, reproductive/developmental or carcinogenicity study of TB-500 in any species by any route — an empty file for a compound nobody has tested, not a clean one. The limited human tolerability data in this area belong to full-length thymosin β4: across Phase 1–2 trials the topical ophthalmic and ulcer formulations were reported as generally well tolerated with a safety profile comparable to placebo 6,
Expected adverse effects (inferred from mechanism and route — labeled as such, not observed for TB-500). Injection-site pain, bruising and reactions are the near-certain practical effects. Beyond that, the general caution attaching to any pro-angiogenic, pro-migratory agent applies: the same biology that supports wound repair could in principle support unwanted tissue or vascular growth. This is mechanistic reasoning, not a trial finding — but it is the reason people with a personal or family history of cancer are routinely cautioned against this class.
Dose-limiting / route-specific risks. For a gray-market injectable, the dominant real-world hazard is not classical drug toxicity but product and technique: non-sterile or contaminated vials, endotoxin exposure, abscess or infection at the injection site, and dosing error from self-reconstituted concentrations of unverified potency.
Interactions. Not assessed. There are no controlled interaction data for the fragment with any drug class, and none should be inferred from the parent protein.
Who should avoid it. There is no established safe-use population, so the honest answer is everyone — but the specific flags are: anyone with a current or prior cancer diagnosis or strong family history (pro-angiogenic mechanism); anyone pregnant, breastfeeding or trying to conceive; children and adolescents; anyone subject to anti-doping testing (this is a bannable substance); and anyone unwilling to inject a product of unverified identity and sterility.
Scope disclosure (honesty, not a claim):
- Human data? None for the fragment. Every human trial cited here tested full-length thymosin β4 or its recombinant form — a different molecule, usually by a different route.
- Interactions assessed? No — none, for any drug class.
- Pregnancy/lactation assessed? No — no human or animal reproductive data located.
- Long-term safety established? No. There is no long-term human safety data for the fragment; the absence of adverse reports reflects the absence of study, not evidence of safety.
Never imply safety from silence. Where TB-500 has not been studied — which is nearly everywhere — the correct statement is “not assessed,” not “safe.”
Not assessed / not established. There are no human pregnancy or lactation data and no reproductive-toxicity data for the TB-500 fragment in the accessible literature. Treat as contraindicated by default in pregnancy and breastfeeding.
Dosage
There is no established human dose for TB-500, and none is recommended here. No controlled human trial of Ac-LKKTETQ has ever been run, so there is no dose-finding data, no maintenance schedule, and no bioavailability figure from which one could be derived. Milligram “loading and maintenance” protocols circulate in vendor copy and forum posts; those are not dose data, they have no experimental basis, and reproducing them would launder marketing as evidence, so they are not given.
For context only, and explicitly not as a substitute: the human doses that do exist in this literature belong to the parent protein and are not transferable. Topical full-length Tβ4 was studied in venous ulcers at concentrations up to 0.03% 6Reference 6RCTThe effect of thymosin treatment of venous ulcers — human (RCT, Phase 2, n=73, topical full-length Tβ4)View study →, and recombinant human Tβ4 was given intravenously at 0.05–25 µg/kg in a healthy-volunteer Phase 1 study 13Reference 13RCTA first-in-human, randomized, double-blind, single- and multiple-dose, phase I study of recombinant human thymosin β4 in healthy volunteers (NL005) — human (RCT, Phase 1, IV PK, full-length Tβ4)View study →. Different molecule, different route, different formulation. Oral TB-500 products cannot deliver intact peptide at all (see Pharmacokinetics). This entry is informational only and is not an endorsement of use.
References
- Esposito S, et al. (2012). Synthesis and characterization of the N-terminal acetylated 17-23 fragment of thymosin beta 4 identified in TB-500, a product suspected to possess doping potential — in vitro (analytical / identity). Drug Testing and Analysis. https://pubmed.ncbi.nlm.nih.gov/22962027/
- Ho ENM, et al. (2012). Doping control analysis of TB-500, a synthetic version of an active region of thymosin β4, in equine urine and plasma — in vitro (analytical / identity). Journal of Chromatography A. https://pubmed.ncbi.nlm.nih.gov/23084823/
- Goldstein AL, et al. (2010). Biological activities of thymosin beta4 defined by active sites in short peptide sequences — review. FASEB Journal. https://pubmed.ncbi.nlm.nih.gov/20179146/
- Kleinman HK, et al. (2012). The regenerative peptide thymosin β4 accelerates the rate of dermal healing in preclinical animal models and in patients — review (animal + Phase 2). Annals of the New York Academy of Sciences. https://pubmed.ncbi.nlm.nih.gov/23050815/
- Kleinman HK, Sosne G (2016). Thymosin β4 promotes dermal healing — review. Vitamins and Hormones. https://pubmed.ncbi.nlm.nih.gov/27450738/
- Guarnera G, et al. (2010). The effect of thymosin treatment of venous ulcers — human (RCT, Phase 2, n=73, topical full-length Tβ4). Annals of the New York Academy of Sciences. https://pubmed.ncbi.nlm.nih.gov/20536470/
- Gladka MM, Johansen AKZ, van Kampen SJ, et al. (2023). Thymosin β4 and prothymosin α promote cardiac regeneration post-ischaemic injury in mice — animal (mouse). Cardiovascular Research. https://pubmed.ncbi.nlm.nih.gov/36125329/
- Zhang Y, et al. (2025). Recombinant human thymosin beta 4 improves ischemic cardiac dysfunction in mice and patients with acute ST-segment elevation myocardial infarction after reperfusion — animal (mouse) + human (RCT, n=96; overall endpoint not significant). Cardiovascular Research. https://pubmed.ncbi.nlm.nih.gov/41229390/
- Gonzalez-Franquesa A, et al. (2021). Discovery of thymosin β4 as a human exerkine and growth factor (no enhancement of muscle regeneration in vivo) — in vitro + animal (mouse). American Journal of Physiology — Cell Physiology. https://pubmed.ncbi.nlm.nih.gov/34495765/
- Philp D, et al. (2004). Thymosin beta4 increases hair growth by activation of hair follicle stem cells — animal (rat). FASEB Journal. https://pubmed.ncbi.nlm.nih.gov/14657002/
- Gao X, et al. (2015). Thymosin beta-4 induces mouse hair growth — animal (mouse). PLoS One. https://pubmed.ncbi.nlm.nih.gov/26083021/
- Sosne G, et al. (2015). Thymosin β4 significantly improves signs and symptoms of severe dry eye in a phase 2 randomized trial (RGN-259) — human (RCT, Phase 2, full-length Tβ4). Cornea. https://pubmed.ncbi.nlm.nih.gov/25826322/
- Wang X, Liu L, Qi L, et al. (2021). A first-in-human, randomized, double-blind, single- and multiple-dose, phase I study of recombinant human thymosin β4 in healthy volunteers (NL005) — human (RCT, Phase 1, IV PK, full-length Tβ4). Journal of Cellular and Molecular Medicine. https://pubmed.ncbi.nlm.nih.gov/34346165/
- Mendias CL, Awan TM (2026). Safety and efficacy of approved and unapproved peptide therapies for musculoskeletal injuries and athletic performance — review. Sports Medicine. https://pubmed.ncbi.nlm.nih.gov/41966639/
- Mayfield CK, Bolia IK, Feingold CL, et al. (2026). Injectable peptide therapy: a primer for orthopaedic and sports medicine physicians — review. The American Journal of Sports Medicine. https://pubmed.ncbi.nlm.nih.gov/41476424/
- Kleinman HK, Kulik V, Goldstein AL (2023). Thymosin β4 and the anti-fibrotic switch — mechanism / review. International Immunopharmacology. https://pubmed.ncbi.nlm.nih.gov/36580759/
- Di H, Huang J, Zhang D, et al. (2026). Thymosin beta 4: an emerging therapeutic candidate for kidney diseases (Tβ4–Ac-SDKP axis) — review. Peptides. https://pubmed.ncbi.nlm.nih.gov/41570941/
- Wu S, Zhou R, Zhou F, et al. (2020). Electrospun thymosin beta-4 loaded PLGA/PLA nanofiber/microfiber hybrid yarns for tendon tissue engineering — in vitro / materials. Materials Science & Engineering C. https://pubmed.ncbi.nlm.nih.gov/31753373/



