
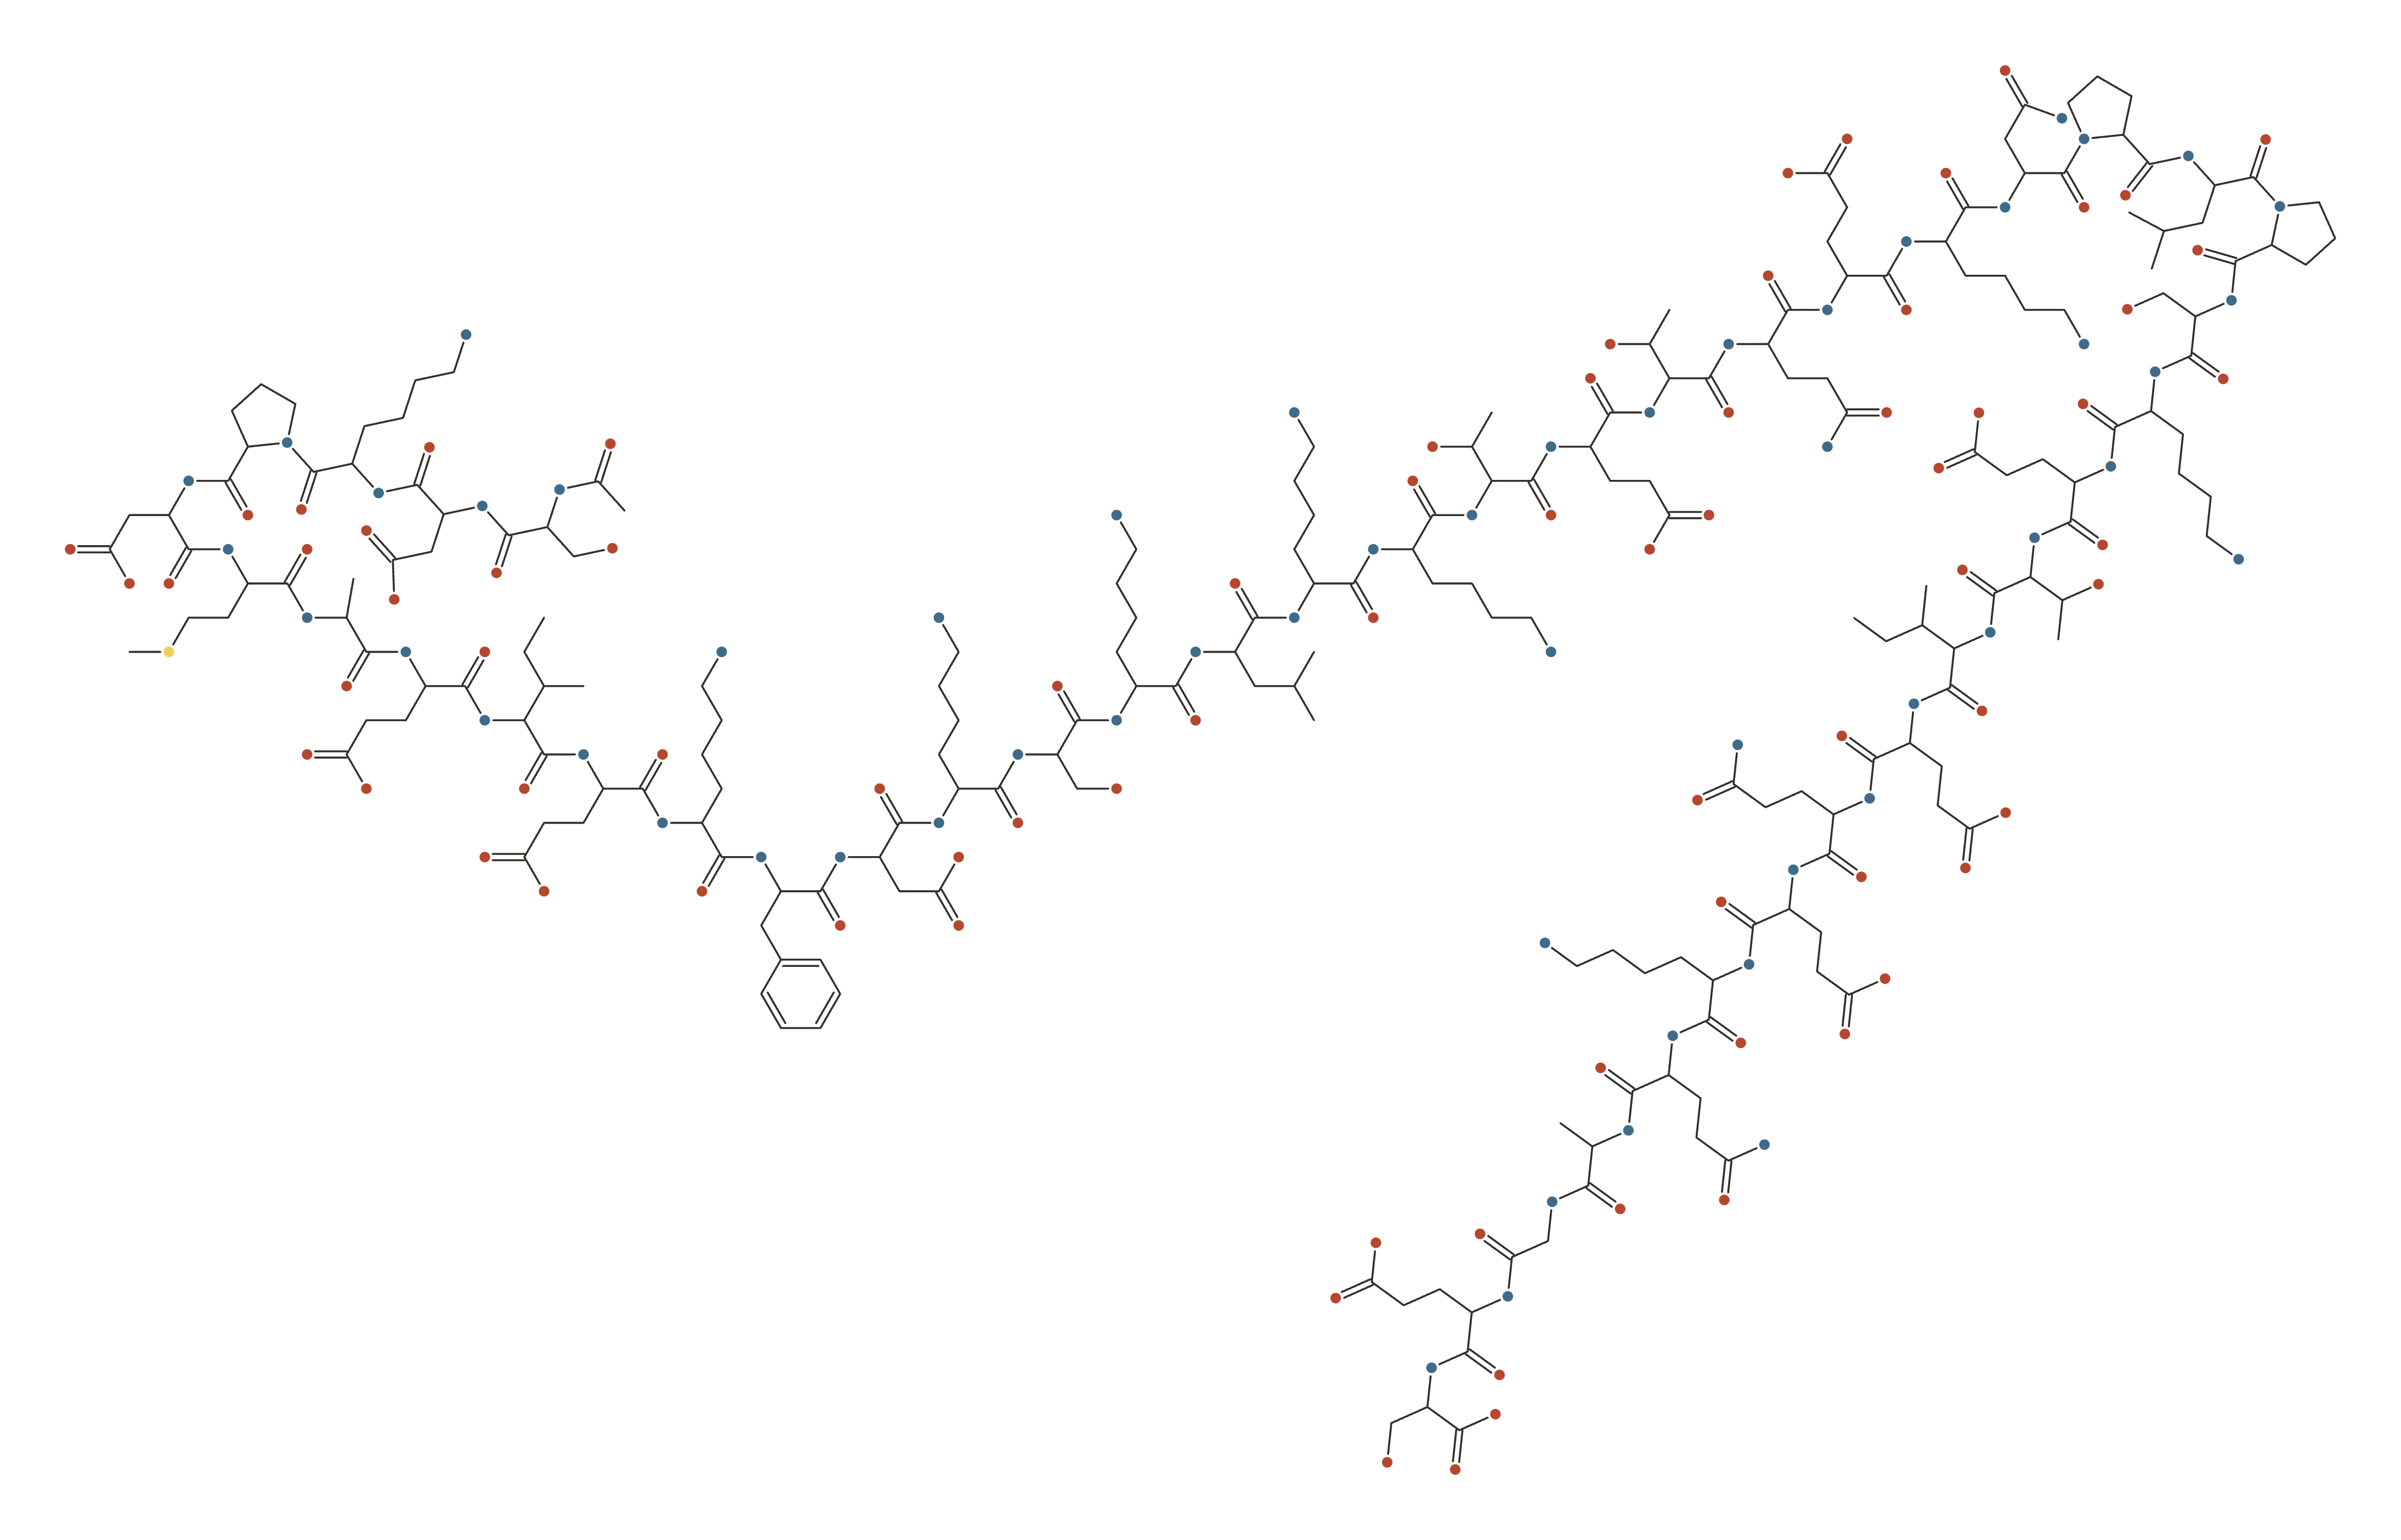
Thymosin Beta-4 (full-length)
The endogenous 43-amino-acid actin-sequestering protein — an investigational drug (eye drops, injectable) with an unconvincing Phase 3 record so far.

Thymosin Beta-4 (full-length) at a Glance
Thymosin β4 is a real endogenous protein — 43 amino acids, present in most human cells, where it sequesters actin monomers and regulates cytoskeletal assembly during tissue repair. Unlike most compounds in this category it entered genuine clinical development, reaching trials as eye drops for corneal injury and as an injectable for cardiac and wound repair. It is investigational rather than approved, and it is the parent molecule that the widely sold fragment TB-500 is derived from and frequently confused with.
History & Development
Thymosin beta 4 is one of the few compounds in this category that entered genuine clinical development - three Phase 3 trials in eye disease. It is also one of the few where those trials have largely not delivered.
| First described | Endogenous protein; clinical development as the ophthalmic solution RGN-259 25Reference 25NCT03937882 - Assessment of the safety and efficacy of RGN-259 ophthalmic solutions for dry eye syndrome: ARISE-3View study → |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Not established in the sources consulted for this section |
| Origin | Endogenous 43-amino-acid regulatory protein (~4.9 kDa, N-terminally acetylated), present in essentially every human cell and in circulating plasma |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Investigational - Phase 3 completed in dry eye (ARISE-3, NCT03937882); not approved 25Reference 25NCT03937882 - Assessment of the safety and efficacy of RGN-259 ophthalmic solutions for dry eye syndrome: ARISE-3View study → |
Discovery
Thymosin beta 4 is not a designed drug. It is a protein the body already makes, in nearly every cell, whose primary job is to bind and sequester monomeric G-actin - controlling the pool of actin available for building the cytoskeleton. Because cell migration depends on actin remodelling, that single function touches wound healing, corneal repair and tissue regeneration.
The endogenous protein and the peptide sold as TB-500 are not the same thing, and the distinction matters commercially: TB-500 is a synthetic fragment, not full-length thymosin beta 4. Claims made for one are routinely transferred to the other.
Development & ownership
Clinical development has centred on the eye, as the 0.1% ophthalmic solution RGN-259, and it is the most substantial trial programme of any compound on this hub.
Two positive small Phase 2 trials in dry eye disease - reporting a 35.1% reduction in ocular discomfort and a 59.1% reduction in total corneal fluorescein staining against vehicle 2Reference 2RCTThymosin beta 4 ophthalmic solution for dry eye: a randomized, placebo-controlled, Phase II clinical trial conducted using the controlled adverse environment (CAE) model — human (RCT, Phase 2, n=72, topical)View study → - led to three large Phase 3 trials: ARISE-1, ARISE-2 and ARISE-3 (n=317, 601 and 700). ARISE-3 (NCT03937882) completed in October 2021 25Reference 25NCT03937882 - Assessment of the safety and efficacy of RGN-259 ophthalmic solutions for dry eye syndrome: ARISE-3View study →. The programme has not produced an approval.
A parallel Phase 3 in neurotrophic keratopathy reported a genuinely positive result - 6 of 10 healed against 1 of 8 on placebo - but from a trial of only 18 patients, which the registry lists as terminated 26Reference 26RCTSosne, G., Kleinman, H. K., Springs, C., et al. (2022). 0.1% RGN-259 (thymosin beta4) ophthalmic solution promotes healing and improves comfort in neurotrophic keratopathy patients in a randomized, placebo-controlled, double-masked Phase III clinical trial. International Journal of Molecular Sciences. https://pmc.ncbi.nlm.nih.gov/articles/PMC9820614/View study →.
How it reached the market
Thymosin beta 4 has not been approved anywhere. Meanwhile the injectable peptide market sells it, and more often TB-500, for injury repair and recovery - applications supported by rodent work rather than by the human programme, which tested eye drops and reported mixed results.
What It's Used For
Thymosin β4 (Tβ4) is an endogenous, 43-amino-acid regulatory protein (~4.9 kDa, N-terminally acetylated) present in essentially every human cell and in circulating plasma, whose primary job is to bind and sequester monomeric G-actin — giving it broad, upstream roles in cytoskeletal dynamics, cell migration, angiogenesis and tissue repair. It is not the same molecule as the peptide sold to consumers. The gray-market product marketed as TB-500 is a synthetic seven-residue fragment (Ac-LKKTETQ, residues 17–23) of Tβ4’s actin-binding site; the subject here is the full-length protein, and it is the full-length side that has genuinely reached human clinical trials. That distinction runs both ways: the trial data below do not transfer to the fragment, and the fragment’s unregulated-vendor reputation does not attach to the protein. Route is load-bearing — Tβ4 has negligible oral bioavailability, so the ophthalmic drug RGN-259 (timbetasin) is a 0.1% topical eye drop, wound trials applied it topically to the ulcer bed, and systemic work is intravenous or (in rodents) intraperitoneal. Its clinical record is the honest headline: three Phase 3 dry-eye trials and a European Phase 3 in neurotrophic keratopathy have read out without meeting their primary endpoints, so despite a decade of development Tβ4 remains investigational and unapproved in every market, and is prohibited in sport under WADA’s S2 growth-factor category.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up. Note that scores here reflect evidence volume and quality, not success: dry eye scores highest because it has by far the most human data, even though that data is largely negative on its primary endpoints.
This is where the human evidence is deepest — and where it has most clearly failed to close. Two Phase 2 RCTs were positive. A small multicenter, randomized, double-masked, placebo-controlled 56-day trial in 9 patients with severe dry eye (including graft-versus-host disease) found 0.1% Tβ4 drops six times daily improved ocular discomfort (OSDI) and corneal fluorescein staining versus vehicle, with good tolerability 1Reference 1RCTThymosin β4 significantly improves signs and symptoms of severe dry eye in a phase 2 randomized trial — human (RCT, Phase 2, n=9, topical)View study →.
A single-center randomized placebo-controlled Phase 2 in 72 subjects with moderate-to-severe dry eye, using the controlled adverse environment (CAE) model over 28 days, tested the same 0.1% formulation against discomfort and staining endpoints 2Reference 2RCTThymosin beta 4 ophthalmic solution for dry eye: a randomized, placebo-controlled, Phase II clinical trial conducted using the controlled adverse environment (CAE) model — human (RCT, Phase 2, n=72, topical)View study →.
The bench-to-bedside case for the ocular surface — corneal epithelial migration, reduced inflammation and apoptosis — is set out in review by the program’s principal clinical investigator 4Reference 4ReviewThymosin beta 4 and the eye: the journey from bench to bedside — reviewView study →.
The Phase 3 program is the part most write-ups on this molecule omit. ReGenTree (the RegeneRx/HLB Therapeutics joint venture) ran three Phase 3 trials — ARISE-1 (NCT02597803, n=317), ARISE-2 (NCT02974907, n=601) and ARISE-3 (NCT03937882, n=700). Per the sponsor’s own 2021 announcements, ARISE-3 did not meet its primary outcome measures. What it did report was a pre-specified secondary symptom endpoint — ocular grittiness, significantly improved at one and two weeks and post-CAE exposure (p=0.0104, 0.0307, 0.0046) — and a post-hoc analysis showing significant central corneal fluorescein staining improvement in an ARISE-3 subpopulation and in the pooled ARISE-1/-2/-3 population. Safety was consistently unremarkable across all three. A post-hoc pooled sign endpoint after a missed primary is hypothesis-generating; it is not a demonstration of efficacy, and no regulator has approved the drug on it. (These are sponsor press releases, not indexed papers, so they are attributed inline rather than cited.)
Gap: ~1,600 patients randomized across three Phase 3 trials with no met primary endpoint and no approval. This is not “promising human evidence pending confirmation” — it is a confirmatory program that has largely read out, negatively, on its stated endpoints.
Tβ4 accelerates full-thickness dermal wound closure across a wide range of rodent models — normal, steroid-treated, diabetic and aged mice and rats, plus burn models — by promoting keratinocyte and endothelial migration, angiogenesis, collagen deposition and reduced inflammation 5,
In humans, a double-blind, placebo-controlled, dose-escalation Phase 2 trial randomized 73 patients with venous stasis ulcers across eight European sites to escalating concentrations of topical Tβ4 or placebo; safety was acceptable at all doses and the 0.03% dose suggested accelerated healing, concentrated in patients with small-to-moderate ulcers 6Reference 6RCTThe effect of thymosin treatment of venous ulcers — human (RCT, Phase 2, n=73, topical)View study →.
A companion Phase 2 pressure-ulcer trial (NCT00382174, n=72) is reported alongside it in the review literature. Pooling the two, Treadwell and colleagues report Tβ4 accelerated healing by close to a month among those patients who healed — a responder-subset effect rather than a uniform benefit 5Reference 5Clinical trialThe regenerative peptide thymosin β4 accelerates the rate of dermal healing in preclinical animal models and in patients — review (animal + Phase 2 human)View study →.
Chronic wounds in epidermolysis bullosa were also pursued, but that Phase 2 (NCT00311766) was terminated 7Reference 7ReviewThymosin β4: potential to treat epidermolysis bullosa and other severe dermal injuries — reviewView study →.
Gap: Replicated and convincing in animals; in humans it stops at small Phase 2 trials with a subset-only signal. No pivotal trial was ever run, no wound indication is approved, and every human dose was topical to the wound bed — not injected.
A randomized, placebo-controlled, double-masked Phase 3 trial (SEER-1) tested 0.1% RGN-259 drops for persistent epithelial defects in Stage 2–3 neurotrophic keratopathy: complete healing at 4 weeks in 6 of 10 Tβ4-treated patients versus 1 of 8 on placebo 3Reference 3RCTSosne G, et al. (2022). 0.1% RGN-259 (thymosin β4) ophthalmic solution promotes healing and improves comfort in neurotrophic keratopathy patients in a randomized, placebo-controlled, double-masked Phase III clinical trial — human (RCT, Phase 3, n=18, topical). International Journal of Molecular Sciences. https://pubmed.ncbi.nlm.nih.gov/36613994/View study →. That is a genuine positive human RCT and the cleanest efficacy result the molecule has produced — but with n=18, and the ClinicalTrials.gov record (NCT02600429) is listed as terminated, so it is a small, early-stopped trial rather than a completed pivotal one.
What followed matters more than what people usually quote. The European Phase 3 SEER-3 trial reported by HLB Therapeutics missed its primary endpoint, showing no statistically significant difference in complete corneal healing at 4 weeks versus placebo; the company attributed the result to an unusually strong placebo response. A further Phase 3, SEER-2 (NCT05555589, n=70), remains recruiting with primary completion estimated in 2026. Orphan-drug interest exists for the indication; approval does not. (SEER-3 has no PubMed record — that result is attributed to the sponsor announcement, not cited.)
Gap: One small positive Phase 3 that was terminated early, one Phase 3 that failed its primary endpoint, and one still enrolling. Nothing here is settled, and a null result belongs on the ledger just as much as the positive one.
The preclinical case is strong and replicated. In mouse myocardial-infarction models, systemic Tβ4 (e.g. 1.6 mg/kg/day intraperitoneally by osmotic minipump) reduced cardiac rupture, limited adverse remodeling and improved function through anti-inflammatory, pro-survival and pro-angiogenic actions 8Reference 8AnimalThymosin-β4 prevents cardiac rupture and improves cardiac function in mice with myocardial infarction — animal (mouse)View study →.
The wider cardiac rationale, including epicardial activation and coronary vessel growth, is developed extensively in review 9Reference 9ReviewThymosin β4-mediated protective effects in the heart — reviewView study →.
A 2025 study extended this to recombinant human Tβ4 in mouse ischemia-reperfusion and permanent-ligation models, mapping the protective effect to ErbB2/Raf1 signaling 10Reference 10RCTRecombinant human thymosin beta 4 improves ischemic cardiac dysfunction in mice and patients with acute ST-segment elevation myocardial infarction after reperfusion — animal (mouse) + human (RCT, n=96; overall endpoint not significant)View study →.
The same paper carried the field’s only substantial human cardiac result: a randomized, double-blind, placebo-controlled trial in 96 STEMI patients after PCI. Read it carefully — the overall comparison of infarct area between recombinant Tβ4 and placebo was not statistically significant; only the pre-specified early-dosing subgroup (first dose within 8 hours of PCI, n=43) showed a significant reduction at 90 days 10Reference 10RCTRecombinant human thymosin beta 4 improves ischemic cardiac dysfunction in mice and patients with acute ST-segment elevation myocardial infarction after reperfusion — animal (mouse) + human (RCT, n=96; overall endpoint not significant)View study →.
The authors call for further rigorous trials, and the study was co-authored by manufacturer employees. Two further Phase 2 acute-MI trials (NCT05485818, n=62; NCT05984134, n=90) are listed as completed with no results posted, and a Phase 2 of the NL005 recombinant injectable (NCT07586865, n=189) is not yet recruiting. Earlier injectable cardiac trials (NCT01311518, NCT00743769) were withdrawn before enrolling.
Gap: Efficacy is rodent-based. The single human RCT is overall null with a positive subgroup, from a manufacturer-linked study; two completed Phase 2 trials have never posted outcomes, which is itself an evidence gap worth naming.
Tβ4 improves neurological outcome in rat embolic middle-cerebral-artery-occlusion models. A dose-response study in male Wistar rats (2, 12 or 18 mg/kg intraperitoneally starting 24 h post-stroke, then every three days) identified an effective dose range and functional improvement 12Reference 12AnimalA dose-response study of thymosin β4 for the treatment of acute stroke — animal (rat)View study →, and the benefit was reproduced in an aged-rat embolic-stroke model at 12 mg/kg 13Reference 13AnimalThymosin β4 for the treatment of acute stroke in aged rats — animal (rat)View study →.
The proposed mechanism is neurorestorative — oligodendrogenesis, axonal remodeling and angiogenesis — rather than acute neuroprotection, which is why the effective dosing window opens a full day after the insult.
Gap: Entirely rodent. There is no human stroke trial of Tβ4 and no registration; dose, timing and route are defined only in rats, by intraperitoneal injection that has no human equivalent.
In rats subjected to controlled cortical impact, Tβ4 given intraperitoneally starting 6 h post-injury (6 or 30 mg/kg, repeated at 24 and 48 h) reduced lesion volume and hippocampal cell loss and improved sensorimotor and spatial-learning recovery versus saline 14Reference 14AnimalNeuroprotective and neurorestorative effects of thymosin β4 treatment initiated 6 hours after traumatic brain injury in rats — animal (rat)View study →. The effect is attributed to neurorestorative and anti-apoptotic actions, and the delayed-start design is the clinically attractive part.
Gap: A single species and a single model, with no independent human work. No TBI trial of Tβ4 exists.
Tβ4 suppressed LPS-induced lung fibrosis in mice by attenuating oxidative injury and inflammation 15Reference 15AnimalThymosin β4 suppresses LPS-induced murine lung fibrosis by attenuating oxidative injury and alleviating inflammation — animal (mouse)View study →.
A broader anti-fibrotic case is made in review for the heart, kidney and liver 16,
The important caveat is mechanistic: a large share of this activity is attributable to Ac-SDKP, the anti-fibrotic tetrapeptide released from Tβ4’s N-terminus — a distinct research entity in its own right 16,
That also means the anti-fibrotic story belongs to full-length Tβ4 and not to the TB-500 (17–23) fragment, which does not contain the N-terminal sequence.
Gap: Animal and in-vitro only, with no human anti-fibrotic trial in any organ, and an active question over how much of the effect is Tβ4 itself versus its Ac-SDKP metabolite.
Tβ4 increases hair growth in rats by activating and mobilizing hair-follicle bulge stem cells and promoting their migration and differentiation 18Reference 18AnimalThymosin beta4 increases hair growth by activation of hair follicle stem cells — animal (rat)View study →, and the effect was replicated in mice with VEGF and MAPK/AKT signaling implicated 19Reference 19AnimalThymosin beta-4 induces mouse hair growth — animal (mouse)View study →. The only human-tissue evidence is a single ex-vivo study in which thymic peptides including Tβ4 differentially modulated cultured human hair-follicle growth — a mixed rather than uniformly stimulatory effect 20Reference 20Thymic peptides differentially modulate human hair follicle growth — human tissue (ex-vivo organ culture)View study →.
Gap: No in-vivo human trial of any kind. One human organ-culture study with a mixed result does not support the marketing claim, and no topical-versus-systemic comparison exists in people.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| G-actin sequestration (LKKTETQ motif, residues 17–23) | Buffers monomeric actin; regulates cytoskeletal dynamics and cell migration | The core mechanism — underlies keratinocyteendothelialcorneal and cardiac cell migration |
| Angiogenesis (endothelial migration, VEGF-associated signaling) | ↑ new vessel formation | Wound healingcardiac repairstroke/TBI recovery |
| Inflammatory signaling (NF-κB-linked) | ↓ inflammatory infiltrate and cytokine drive | Ocular-surface repaircardiac rupture preventionlung fibrosis |
| Apoptosis / cell survival (incl. ErbB2–Raf1 in the heart) | ↓ apoptosis, ↑ survival | Cardiac repair (effect abolished by ErbB2 inhibition in mice)neurorestoration |
| Ac-SDKP N-terminal tetrapeptide fragment | Anti-fibrotic, anti-inflammatory | Cardiac remodelingrenal and hepatic fibrosis — a distinct fragmentnot present in TB-500 |
| Stem/progenitor cell mobilization & differentiation | ↑ migration and differentiation | Dermal repairepicardial cardiac repairhair-follicle bulge cells |
Pharmacokinetics
Tβ4 is a small (~4.9 kDa), highly water-soluble 43-residue peptide with negligible oral bioavailability — it is degraded in the gastrointestinal tract like any peptide of its size, and no oral formulation exists clinically or could work if it did. All dosing is therefore local or parenteral, and matched to the indication: the ophthalmic drug RGN-259 is a 0.1% topical solution applied to the eye surface (six times daily in the Phase 2 trials), wound studies applied it topically to the ulcer bed, and systemic studies used intravenous (human) or intraperitoneal (rodent) injection. The first-in-human study of recombinant human Tβ4 (NL005) gave single and multiple IV doses of 0.05–25 µg/kg to healthy volunteers, reporting good tolerability and dose-proportional exposure 11Reference 11RCTA first-in-human, randomized, double-blind, single- and multiple-dose, phase I study of recombinant human thymosin β4 in healthy volunteers (NL005) — human (RCT, Phase 1, IV PK)View study →. Circulating Tβ4 has a short plasma half-life — on the order of a couple of hours after systemic dosing — which is the acknowledged limitation driving work on longer-acting engineered analogues such as a tandem dual-domain Tβ4 23Reference 23In vitroEngineered tandem thymosin peptide promotes corneal wound healing — in vitro + animalView study →. Two dedicated Phase 1a/1b PK studies (NCT04555824, n=54; NCT04555850, n=30) are listed as completed, but detailed human half-life and clearance parameters have not been publicly posted — a genuine and slightly surprising PK gap for a molecule this far into development. Reconstituted peptide is chemically labile in solution and requires refrigeration.
Clinical & regulatory status
Full-length thymosin β4 is an unapproved, investigational drug — not an approved medicine or dietary supplement in the US, EU, UK, Japan, Australia or any other major market. Its most advanced program is the ophthalmic formulation RGN-259 (timbetasin), developed by RegeneRx Biopharmaceuticals and its joint venture ReGenTree with HLB Therapeutics. That program has completed three Phase 3 dry-eye trials (ARISE-1/-2/-3) without meeting primary endpoints, produced one positive but terminated Phase 3 in neurotrophic keratopathy (SEER-1) and one European Phase 3 that missed its primary endpoint (SEER-3), and has a third NK Phase 3 (SEER-2) still recruiting. Orphan-drug interest attaches to some ocular indications; no approval or BLA clearance has been granted. Injectable Tβ4 has completed Phase 1 safety/PK studies in healthy volunteers and Phase 2 trials in chronic wounds and acute MI — the latter completed without posting results — while earlier injectable cardiac trials were withdrawn. There are no completed registered human trials for the musculoskeletal, tendon, “recovery” or anti-aging uses the molecule is marketed for. Tβ4 and its active fragments are prohibited in sport under the World Anti-Doping Agency’s S2 (growth factors) category, banned at all times, in and out of competition.
One caution for anyone searching the registry: a recruiting record titled “TB-500 (Thymosin Beta 4 17-23 Fragment) for Cardiovascular Biomarkers in Stable ASCVD” (NCT07487363) states in its own brief summary that it is a fictional example record. I verified this directly against the ClinicalTrials.gov API in July 2026. It is excluded from every count below and carries no evidentiary weight.
| Completed | Ongoing | Terminated / Withdrawn | Preclinical |
|---|---|---|---|
| 11 | 2 | 5 | ~50+ |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. Full-length thymosin β4 has no marketing approval from any major regulator — FDA, EMA, MHRA, TGA, PMDA — as either a drug or a dietary supplement, and it is not a lawful dietary-supplement ingredient in the US, UK or EU. It is a genuine investigational pharmaceutical (RGN-259 topical, NL005 recombinant injectable) that has not cleared its confirmatory trials. “Investigational” is not a softer word for “nearly approved”: three Phase 3 dry-eye trials and a Phase 3 neurotrophic-keratopathy trial have read out without meeting primary endpoints. It is not a scheduled or controlled substance in the US, but marketing it for human use is unlawful in most Western jurisdictions.
Banned in sport. Tβ4 sits on the WADA Prohibited List under S2, growth factors affecting tissue repair, angiogenesis and muscle/tendon/ligament regeneration — prohibited at all times, in and out of competition, and detectable: validated LC-MS anti-doping methods exist for both the protein and its fragments. A 2026 sports-medicine review of peptide therapies for musculoskeletal injury classes Tβ4 and “TB-500” among unapproved gray-market peptides with no efficacy data, citing them as a clinical problem rather than a treatment 22Reference 22ReviewSafety and efficacy of approved and unapproved peptide therapies for musculoskeletal injuries and athletic performance — reviewView study →.
How it’s supplied & administered. The clinical drug is formulated by route to the indication: a 0.1% topical ophthalmic solution for the eye, direct topical application for ulcers, and intravenous injection in systemic studies. Oral products cannot deliver intact peptide and are pharmacologically inert regardless of the label. The consumer market is a different supply chain entirely — lyophilized powder in vials, reconstituted by the user with bacteriostatic water and self-injected subcutaneously or intramuscularly.
Sourcing reality (this is a safety issue, not a footnote). Any Tβ4 bought online comes from unregulated research-chemical vendors with no manufacturing oversight, and the single most common problem is identity: the 43-residue protein and the 7-residue TB-500 fragment are routinely sold under each other’s names, so a vial labeled “thymosin beta-4” may contain either, both, or neither. Beyond mislabeling, the documented risks across this market are under- and over-potency, bacterial endotoxin contamination (serious for an injectable), residual synthesis solvents and non-sterile fill — every one of them amplified because the product is injected rather than swallowed. Third-party certificates of analysis (independent HPLC identity/purity plus endotoxin testing) are the minimum a buyer would look for, cannot substitute for GMP manufacturing, and can themselves be falsified. No independent assay of marketed product was located in this pass. This page does not recommend, rank or link any vendor.
Safety
Short-term trial tolerability has been good, but almost all of that record is topical, weeks long, and in eye or wound patients — chronic systemic injection, the way the molecule is actually used off-label, has no safety dataset at all.
- Good short-term tolerability in trials. No serious adverse events in the ophthalmic program and no dose-limiting toxicity in the wound and IV studies.
- Pregnancy and lactation not assessed. No reproductive data of any kind; treated as contraindicated by default — see the box below.
- Cancer-history caution. Tβ4 is pro-angiogenic and pro-migratory, and over-expressed in several human cancers.
- Chronic systemic injection is unstudied. No safety dataset exists for repeated off-label injection, or for use in healthy people.
- Gray-market product is its own hazard. Non-sterile or endotoxin-contaminated vials, injection-site infection, and dosing error from self-reconstitution.
- Interactions not assessed. No controlled drug-interaction studies exist for any formulation.
Full Safety & Interactions Detail
Short-term tolerability in trials has been good; that is not the same as an established safety profile. In the ophthalmic Phase 2 and Phase 3 studies, topical RGN-259 was well tolerated, with no serious adverse events and only mild-to-moderate events reported in both active and placebo arms across the full ARISE program 1,
What has not been assessed. Chronic and repeated systemic injection — the way the molecule is actually used off-label — has no safety dataset at all. Neither does use in any healthy person for “recovery” or anti-aging.
Theoretical mechanism-based caution. Tβ4 is pro-angiogenic and pro-migratory, and it is over-expressed in several human cancers, including hepatocellular and colorectal carcinoma, where expression has been examined alongside thymosin β10 24Reference 24Thymosin beta 4 and thymosin beta 10 expression in hepatocellular carcinoma — human tissue (expression study)View study →. No causal human harm has been demonstrated, and expression in a tumor is not the same as a drug causing one — but the biology that supports wound repair is the biology tumors co-opt, which is why anyone with a personal history of malignancy is routinely cautioned against this class.
Route-specific risks. For injected gray-market material, the dominant real-world hazard is not the peptide but the product and the technique: non-sterile or endotoxin-contaminated vials, injection-site infection or abscess, and dosing error from self-reconstituted solutions of unverified potency.
Interactions. Not assessed. No controlled drug-interaction studies exist for any formulation.
Who should avoid it. Anyone with a current or prior cancer diagnosis or strong family history; anyone pregnant, breastfeeding or trying to conceive; children and adolescents; anyone subject to anti-doping testing (this is a bannable substance); and anyone unwilling to inject a product whose identity and sterility cannot be verified.
Scope disclosure (honesty, not a claim):
- Human data? Yes, and unusually so for this hub — small positive Phase 2 RCTs and three large Phase 3 trials in dry eye, a Phase 3 in neurotrophic keratopathy, Phase 2 trials in venous-stasis and pressure ulcers, one Phase 2 cardiac RCT, and Phase 1 systemic PK studies. But almost all of it is topical, and the Phase 3 endpoints were not met. No human data exist for musculoskeletal “recovery,” anti-aging, stroke, TBI, fibrosis or hair growth.
- Interactions assessed? No — none, for any drug class.
- Pregnancy/lactation assessed? No — no human or animal reproductive data located.
- Long-term safety established? No. Only short-term, mostly topical trial tolerability is documented; chronic and repeated-injection safety is unstudied.
Never imply safety from silence. Where Tβ4 has not been studied, the correct statement is “not assessed,” not “safe.”
Not assessed / not established. No human pregnancy or lactation data and no reproductive-toxicity data for Tβ4 in any formulation were located. Treat as contraindicated by default in pregnancy and breastfeeding.
Dosage
There is no established human dose for thymosin β4, and none is recommended here. It is an investigational drug with no approved indication, so there is no label, no maintenance schedule and no over-the-counter dose to report.
For context only, and explicitly not as a substitute for medical direction: the doses that exist in the literature are formulation- and indication-specific. The ophthalmic trials used a 0.1% topical solution instilled in the eye, six times daily in the Phase 2 studies 1,
References
- Sosne G, et al. (2015). Thymosin β4 significantly improves signs and symptoms of severe dry eye in a phase 2 randomized trial — human (RCT, Phase 2, n=9, topical). Cornea. https://pubmed.ncbi.nlm.nih.gov/25826322/
- Sosne G, et al. (2015). Thymosin beta 4 ophthalmic solution for dry eye: a randomized, placebo-controlled, Phase II clinical trial conducted using the controlled adverse environment (CAE) model — human (RCT, Phase 2, n=72, topical). Clinical Ophthalmology. https://pubmed.ncbi.nlm.nih.gov/26056426/
- Sosne G, et al. (2022). 0.1% RGN-259 (thymosin β4) ophthalmic solution promotes healing and improves comfort in neurotrophic keratopathy patients in a randomized, placebo-controlled, double-masked Phase III clinical trial — human (RCT, Phase 3, n=18, topical). International Journal of Molecular Sciences. https://pubmed.ncbi.nlm.nih.gov/36613994/
- Sosne G (2018). Thymosin beta 4 and the eye: the journey from bench to bedside — review. Expert Opinion on Biological Therapy. https://pubmed.ncbi.nlm.nih.gov/30063853/
- Treadwell T, et al. (2012). The regenerative peptide thymosin β4 accelerates the rate of dermal healing in preclinical animal models and in patients — review (animal + Phase 2 human). Annals of the New York Academy of Sciences. https://pubmed.ncbi.nlm.nih.gov/23050815/
- Guarnera G, et al. (2010). The effect of thymosin treatment of venous ulcers — human (RCT, Phase 2, n=73, topical). Annals of the New York Academy of Sciences. https://pubmed.ncbi.nlm.nih.gov/20536470/
- Yang WS, et al. (2019). Thymosin β4: potential to treat epidermolysis bullosa and other severe dermal injuries — review. European Journal of Dermatology. https://pubmed.ncbi.nlm.nih.gov/31649007/
- Peng H, et al. (2014). Thymosin-β4 prevents cardiac rupture and improves cardiac function in mice with myocardial infarction — animal (mouse). American Journal of Physiology — Heart and Circulatory Physiology. https://pubmed.ncbi.nlm.nih.gov/25015963/
- Hinkel R, et al. (2018). Thymosin β4-mediated protective effects in the heart — review. Expert Opinion on Biological Therapy. https://pubmed.ncbi.nlm.nih.gov/30063857/
- Zhang Y, et al. (2025). Recombinant human thymosin beta 4 improves ischemic cardiac dysfunction in mice and patients with acute ST-segment elevation myocardial infarction after reperfusion — animal (mouse) + human (RCT, n=96; overall endpoint not significant). Cardiovascular Research. https://pubmed.ncbi.nlm.nih.gov/41229390/
- Wang X, et al. (2021). A first-in-human, randomized, double-blind, single- and multiple-dose, phase I study of recombinant human thymosin β4 in healthy volunteers (NL005) — human (RCT, Phase 1, IV PK). Journal of Cellular and Molecular Medicine. https://pubmed.ncbi.nlm.nih.gov/34346165/
- Morris DC, et al. (2014). A dose-response study of thymosin β4 for the treatment of acute stroke — animal (rat). Journal of the Neurological Sciences. https://pubmed.ncbi.nlm.nih.gov/25060418/
- Morris DC, et al. (2017). Thymosin β4 for the treatment of acute stroke in aged rats — animal (rat). Neuroscience Letters. https://pubmed.ncbi.nlm.nih.gov/28864242/
- Xiong Y, et al. (2012). Neuroprotective and neurorestorative effects of thymosin β4 treatment initiated 6 hours after traumatic brain injury in rats — animal (rat). Journal of Neurosurgery. https://pubmed.ncbi.nlm.nih.gov/22324420/
- Tian Z, et al. (2022). Thymosin β4 suppresses LPS-induced murine lung fibrosis by attenuating oxidative injury and alleviating inflammation — animal (mouse). Inflammation. https://pubmed.ncbi.nlm.nih.gov/34414534/
- Kleinman HK, et al. (2023). Thymosin β4 and the anti-fibrotic switch — review (mechanism). International Immunopharmacology. https://pubmed.ncbi.nlm.nih.gov/36580759/
- Di H, et al. (2026). Thymosin beta 4: an emerging therapeutic candidate for kidney diseases (Tβ4–Ac-SDKP axis) — review. Peptides. https://pubmed.ncbi.nlm.nih.gov/41570941/
- Philp D, et al. (2004). Thymosin beta4 increases hair growth by activation of hair follicle stem cells — animal (rat). FASEB Journal. https://pubmed.ncbi.nlm.nih.gov/14657002/
- Gao X, et al. (2015). Thymosin beta-4 induces mouse hair growth — animal (mouse). PLoS One. https://pubmed.ncbi.nlm.nih.gov/26083021/
- Meier N, et al. (2012). Thymic peptides differentially modulate human hair follicle growth — human tissue (ex-vivo organ culture). Journal of Investigative Dermatology. https://pubmed.ncbi.nlm.nih.gov/22402437/
- Bock-Marquette I, et al. (2023). Thymosin beta-4 denotes new directions towards developing prosperous anti-aging regenerative therapies — review. International Immunopharmacology. https://pubmed.ncbi.nlm.nih.gov/36709593/
- Mendias CL, et al. (2026). Safety and efficacy of approved and unapproved peptide therapies for musculoskeletal injuries and athletic performance — review. Sports Medicine. https://pubmed.ncbi.nlm.nih.gov/41966639/
- Nguyen J, et al. (2025). Engineered tandem thymosin peptide promotes corneal wound healing — in vitro + animal. Investigative Ophthalmology & Visual Science. https://pubmed.ncbi.nlm.nih.gov/41235866/
- Theunissen W, et al. (2014). Thymosin beta 4 and thymosin beta 10 expression in hepatocellular carcinoma — human tissue (expression study). European Journal of Histochemistry. https://pubmed.ncbi.nlm.nih.gov/24704991/
- ClinicalTrials.gov. NCT03937882 - Assessment of the safety and efficacy of RGN-259 ophthalmic solutions for dry eye syndrome: ARISE-3. https://clinicaltrials.gov/study/NCT03937882
- Sosne, G., Kleinman, H. K., Springs, C., et al. (2022). 0.1% RGN-259 (thymosin beta4) ophthalmic solution promotes healing and improves comfort in neurotrophic keratopathy patients in a randomized, placebo-controlled, double-masked Phase III clinical trial. International Journal of Molecular Sciences. https://pmc.ncbi.nlm.nih.gov/articles/PMC9820614/



