
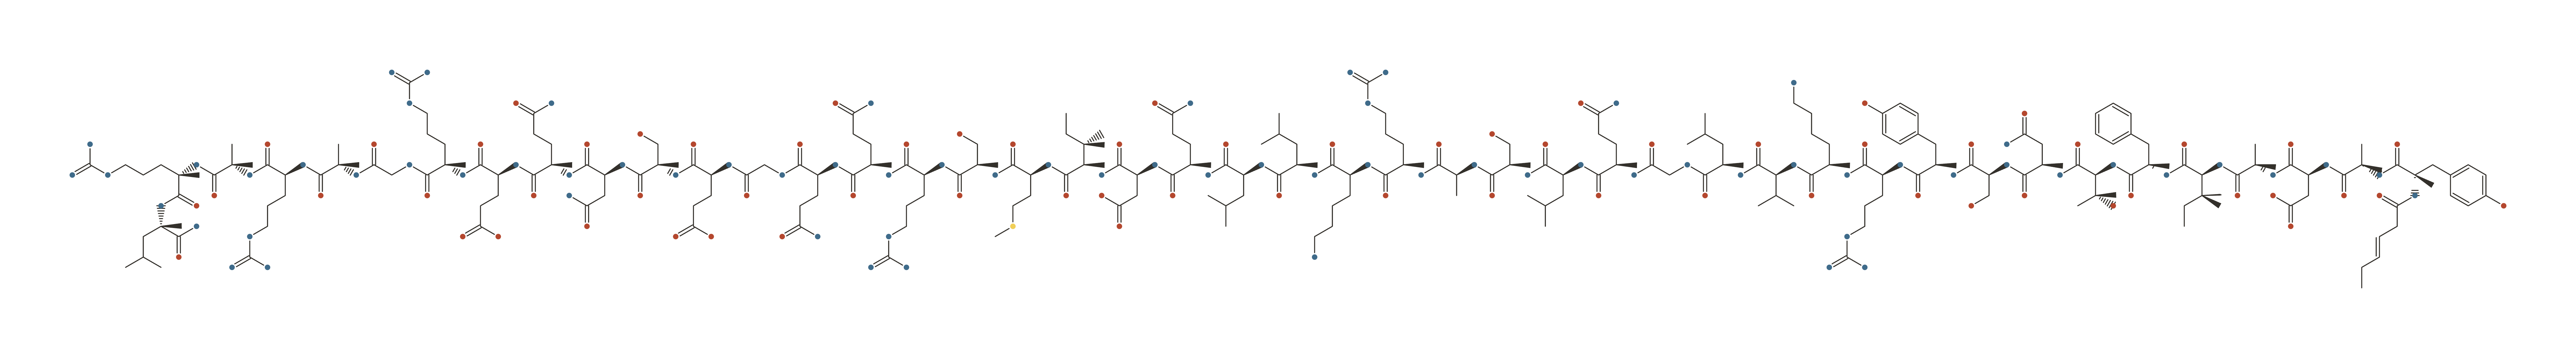

Tesamorelin at a Glance
Tesamorelin is a stabilised GHRH analogue, modified at one end so it survives in circulation long enough to be given once daily. It is the most rigorously evidenced peptide in this class: approved by the FDA as Egrifta specifically to reduce the excess visceral fat that develops in HIV-associated lipodystrophy, on the strength of full phase 3 trials with imaging endpoints. That indication is narrow and it matters — the trials measured visceral adipose tissue in a defined patient population, not general fat loss in healthy people. It remains a prescription medicine.
History & Development
Tesamorelin is the only GHRH-class peptide holding a current FDA approval, and it earned it for a narrow, specific problem: the abnormal visceral fat that accumulates in people on long-term HIV therapy.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Developed by Theratechnologies Inc. (Montreal, Canada) 23, |
| Origin | Synthetic 44-amino-acid analogue of human growth-hormone-releasing hormone, stabilised against enzymatic breakdown |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Theratechnologies Inc. |
| Development status | Approved - FDA, 10 November 2010, as EGRIFTA; reformulated as EGRIFTA SV and EGRIFTA WR 23, |
Discovery
Tesamorelin is a synthetic analogue of GHRH(1-44) - the full-length releasing hormone rather than the shortened fragment used by sermorelin - modified to resist the enzymatic degradation that clears native GHRH within minutes 24Reference 24EGRIFTA SV (tesamorelin) for injection - full prescribing informationView study →. That stabilisation is what makes once-daily dosing possible.
The clinical problem it was developed for is specific and was, at the time, untreatable. Antiretroviral therapy transformed HIV into a manageable condition, but a proportion of patients developed lipodystrophy - a redistribution of body fat that includes excess visceral adipose tissue, which carries genuine cardiometabolic risk and is not addressed by diet or by switching regimens. No treatment existed 23Reference 23FDA approves EGRIFTA (tesamorelin for injection) for reduction of excess abdominal fat in HIV-infected patients with lipodystrophy. https://www.fiercebiotech.com/biotech/fda-approves-egrifta%E2%84%A2-tesamorelin-for-injection-first-and-only-treatment-for-reduction-ofView study →.
Because tesamorelin works by prompting the pituitary to release the body’s own growth hormone rather than supplying it directly, output remains under normal feedback control - the argument for this class over injected growth hormone.
Development & ownership
Theratechnologies, a Montreal company, took tesamorelin through its full development programme.
Pivotal trials measured visceral adipose tissue on imaging rather than weight or waist
circumference, reporting reductions of roughly 15-18% over 26 weeks 23,
The FDA approved it on 10 November 2010 as EGRIFTA, the first and only treatment indicated to
reduce excess abdominal fat in HIV-infected patients with lipodystrophy 23,
How it reached the market
Tesamorelin is a prescription medicine dispensed for a labelled indication, and it is also sold outside that channel: because it is the one GHRH analogue with an approval behind it, it circulates in research-peptide supply for body-composition and anti-ageing use. That use has no trial support - the evidence base measures visceral fat in a defined patient population with a specific antiretroviral-associated condition, not fat loss in healthy people.
What It's Used For
Tesamorelin is a synthetic 44-amino-acid analogue of human growth hormone-releasing hormone (GHRH, also called growth hormone-releasing factor / GRF), stabilized against enzymatic breakdown by a trans-3-hexenoyl group on the N-terminal tyrosine. It binds the pituitary GHRH receptor and raises the body’s own pulsatile growth hormone (GH) and, downstream, IGF-1 1,
Unlike almost every other compound on this hub, it is not a research chemical — it is an FDA-approved prescription medicine (Egrifta, reformulated as EGRIFTA SV and EGRIFTA WR) for one narrow indication: reducing excess visceral abdominal fat in adults with HIV who have lipodystrophy, backed by adequately powered phase 3 randomized controlled trials and a 2026 meta-analysis 1,
That approved use is genuinely human-RCT-grade. Everything else it is marketed or discussed for — general fat loss, “anti-aging”, cognition, muscle-building, liver disease outside HIV — is either preclinical, a small or null human trial, or straight off-label extrapolation, and must be read that way. It is injected subcutaneously once daily because it is a peptide with an ~8-minute plasma half-life and negligible oral bioavailability 19Reference 19Population pharmacokinetic analysis of tesamorelin in HIV-infected patients and healthy subjects — human (population PK)View study →.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the approved indication and the only application with approval-grade backing — all human, all in adults with HIV and abdominal fat accumulation. In the pivotal 26-week phase 3 RCT, 412 adults received 2 mg subcutaneous tesamorelin daily or placebo, and CT-measured VAT fell significantly against placebo 1Reference 1RCTMetabolic effects of a growth hormone-releasing factor in patients with HIV — human (phase 3 RCT)View study →; an earlier dose-ranging trial established the effect 5Reference 5RCTA placebo-controlled, dose-ranging study of a growth hormone-releasing factor in HIV-infected patients with abdominal fat accumulation — human (RCT)View study →.
A second 12-month phase 3 trial (n=404) reduced VAT by roughly 18% relative to placebo, improved body-image distress, and did not clinically perturb glucose 2Reference 2RCTEffects of tesamorelin, a growth hormone-releasing factor, in HIV-infected patients with abdominal fat accumulation — human (RCT with safety extension)View study →, and a pooled analysis of the two phase 3 trials (n=806) confirmed a ~15% treatment effect on VAT with subcutaneous fat preserved 3Reference 3Effects of tesamorelin (TH9507), a growth hormone-releasing factor analog, in HIV-infected patients with excess abdominal fat — human (pooled analysis of two phase 3 RCTs)View study →.
Efficacy also held in the modern integrase-inhibitor era in a smaller randomized trial 18Reference 18RCTEfficacy and safety of tesamorelin in people with HIV on integrase inhibitors — human (randomised double-blind trial)View study →, and a 2026 meta-analysis of 5 RCTs put the pooled VAT effect at −27.7 cm² versus placebo 7Reference 7Meta-analysisBody composition, hepatic fat, metabolic, and safety outcomes of tesamorelin in HIV-associated lipodystrophy — meta-analysis of human RCTsView study →.
The 52-week safety extension showed the effect is sustained on continued dosing — and that VAT re-accumulates after discontinuation 4Reference 4RCTLong-term safety and effects of tesamorelin in HIV patients with abdominal fat accumulation — human (52-week randomised extension)View study →, so this is suppression while dosed, not a durable body-composition change.
Gap: Strong human RCT evidence, but confined to people with HIV and lipohypertrophy. There are no efficacy RCTs for cosmetic or general visceral-fat loss in people without HIV, and the label states the drug is weight-neutral and not indicated for weight management. Nothing here supports the bodybuilding or anti-aging use it is sold for.
In a 12-month randomized, double-blind, multicenter human trial of 61 people with HIV and a hepatic fat fraction ≥5% by MR spectroscopy, 2 mg daily tesamorelin produced a greater reduction in liver fat than placebo and reduced progression to fibrosis — the first agent shown effective against NAFLD in this population 6,
Gap: A single modest-sized RCT in an HIV-specific NAFLD population, with no confirmatory trial and no data in non-HIV MASLD/NASH (a phase 2 trial in general fatty-liver disease, NCT07481734, only began recruiting in 2026). This is not an approved liver indication.
Across the human HIV RCTs, tesamorelin improved triglycerides and the total-cholesterol/HDL ratio as secondary endpoints, without clinically significant average glucose worsening over 52 weeks 3,
Gap: These are secondary metabolic outcomes measured inside HIV lipodystrophy trials, not primary endpoints in metabolic disease. Set against them, glucose intolerance and new or worsening diabetes are labeled risks requiring monitoring — so the metabolic profile is favorable-but-watched, not a demonstrated metabolic therapy.
All human, and genuinely inconsistent. The positive signal comes from a non-HIV setting: a 20-week randomized, double-blind, placebo-controlled trial of GHRH (tesamorelin, 1 mg/day SC) in 152 older adults — 66 of them with mild cognitive impairment — reported favorable effects on cognition 14Reference 14RCTEffects of growth hormone-releasing hormone on cognitive function in adults with mild cognitive impairment and healthy older adults — human (RCT)View study →, with a magnetic-resonance-spectroscopy sub-study linking the effect to changes in brain GABA 15Reference 15RCTGrowth hormone-releasing hormone effects on brain GABA levels in mild cognitive impairment and healthy aging — human (randomised sub-study)View study →.
It has not replicated. In people with HIV, a 6-month phase 2 RCT (n=73) found only a non-significant trend toward improved neurocognition and no between-group difference 16Reference 16RCTEffects of tesamorelin on neurocognitive impairment in persons with HIV and abdominal obesity — human (phase 2 RCT)View study →, and a 10-week low-dose placebo-controlled pilot (n=22) found no significant effect on standard measures 17Reference 17RCTThe effect of growth hormone-releasing hormone on cognition and brain connectivity in adults with cognition rated normal to mildly impaired — human (placebo-controlled pilot trial). eNeurologicalSci. https://pubmed.ncbi.nlm.nih.gov/42382101/View study →.
Gap: One positive single-center RCT against two null or underpowered trials. The cognitive benefit is not established, is not an approved use, and an adequately powered confirmatory trial does not exist.
Evidence here is secondary and exploratory, not from trials designed with muscle endpoints — and all of it sits in the human HIV trial population. Exploratory secondary analyses found tesamorelin increased trunk-muscle area and decreased muscle fat in VAT responders 12Reference 12RCTThe growth hormone-releasing hormone analogue tesamorelin decreases muscle fat and increases muscle area in adults with HIV — human (exploratory analysis of randomised trials)View study →, and the 2026 meta-analysis reported a lean-body-mass increase of roughly 1.4 kg versus placebo 7Reference 7Meta-analysisBody composition, hepatic fat, metabolic, and safety outcomes of tesamorelin in HIV-associated lipodystrophy — meta-analysis of human RCTsView study →.
A separate mechanistic RCT in obese adults with reduced GH linked the IGF-1 rise to improved mitochondrial function measured by phosphocreatine recovery 13Reference 13RCTThe effects of tesamorelin on phosphocreatine recovery in obese subjects with reduced growth hormone — human (RCT)View study →.
Gap: No RCT with muscle strength or physical function as a primary endpoint has reported (TRIUMPH, NCT06554717, is designed to test exactly this and is still recruiting) 21Reference 21Clinical trialTesamorelin as an adjunct to exercise for improving physical function in HIV (TRIUMPH) — human (clinical trial protocol)View study →. Community muscle-building use in healthy athletes has no controlled support at all.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Pituitary GHRH receptor | Agonist → ↑ endogenous pulsatile GH secretion | All applications |
| GH → hepatic IGF-1 | ↑ IGF-1, dose-related (label requires monitoring) | Fatmusclecognitionmetabolic |
| Visceral adipose tissue | ↓ VAT via GH-driven lipolysis; subcutaneous fat preserved | HIV lipodystrophy |
| Hepatic lipid & gene expression | ↓ liver fat; ↑ oxidative phosphorylation, ↓ inflammation/fibrogenesis gene sets | NAFLD in HIV |
| Circulating immune markers | ↓ chemokines, cytokines, T-cell activation proteins | Inflammationliver |
| Dipeptidyl-peptidase-IV | Resistant (hexenoyl modification) → longer-acting than native GHRH | Pharmacokinetics |
| Glucose homeostasis | GH-mediated insulin resistance — a labeled risk, not a benefit | Safety / monitoring |
Pharmacokinetics
Tesamorelin is a peptide given by subcutaneous injection into the abdomen, once daily — oral dosing is not viable, because a peptide of this size is degraded in the gut rather than absorbed intact. The stabilizing trans-3-hexenoyl group on Tyr1 makes it resistant to dipeptidyl-aminopeptidase-IV, slowing degradation relative to native GHRH 20Reference 20AnimalNon-clinical pharmacology and safety evaluation of TH9507, a human growth hormone-releasing factor analogue — animal (rat/dog/pig)View study →. Even so, the parent peptide clears fast: population pharmacokinetic work reports a mean elimination half-life of roughly 8 minutes after subcutaneous dosing, with a large volume of distribution, described by a one-compartment model with combined first- and zero-order absorption; age, body size, and race did not materially affect the PK 19Reference 19Population pharmacokinetic analysis of tesamorelin in HIV-infected patients and healthy subjects — human (population PK)View study →. The clinically relevant point is the mismatch between the peptide and its effect: a molecule that is gone in minutes triggers a GH pulse and a sustained IGF-1 elevation lasting far longer, which is why once-daily dosing works and why IGF-1 — not tesamorelin levels — is the monitored parameter. It is supplied as a lyophilized powder requiring reconstitution with the supplied diluent before injection, and the formulations differ in vial strength, dose, reconstitution and storage (EGRIFTA 1 mg/vial dosed at 2 mg daily; EGRIFTA SV 2 mg/vial dosed at 1.4 mg daily; EGRIFTA WR a later reformulation) — they are not interchangeable. PK in renal or hepatic impairment, in pediatric patients, and in the elderly is not established.
Clinical & regulatory status
Tesamorelin is an FDA-approved prescription drug — approved in 2010 as Egrifta and marketed by Theratechnologies, later reformulated as EGRIFTA SV and EGRIFTA WR — indicated solely for the reduction of excess abdominal fat in adults with HIV who have lipodystrophy 22Reference 22ReviewTesamorelin: a review of its use in the management of HIV-associated lipodystrophy — reviewView study →. It is a prescription medicine, not a dietary supplement, and is explicitly not indicated for weight-loss management or for cosmetic/anti-aging use. Registered-trial activity continues beyond the approved indication: phase 2 trials are recruiting in general (non-HIV) fatty-liver disease (NCT07481734) and for physical function and frailty in older people with HIV (TRIUMPH, NCT06554717) 21Reference 21Clinical trialTesamorelin as an adjunct to exercise for improving physical function in HIV (TRIUMPH) — human (clinical trial protocol)View study →; earlier trials in COPD, diabetic retinopathy, and traumatic-brain-injury sleep were terminated or withdrawn. Sale of tesamorelin powder by research-chemical vendors “for research use only” sits entirely outside the approved prescription channel. Counts below reflect what is findable and verifiable in PubMed and ClinicalTrials.gov this pass.
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| ~14 | 3(2 recruiting phase 2 + protocol) | 4(+3 withdrawn) | Small(rat/dog/pig toxicology) |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. Tesamorelin is an FDA-approved prescription medicine, first approved in 2010 as Egrifta and since reformulated (EGRIFTA SV; EGRIFTA WR). Its sole approved indication is reduction of excess abdominal fat in adults with HIV-associated lipodystrophy. The label is explicit about the limits: it is not indicated for weight-loss management (the drug is weight-neutral), and long-term cardiovascular safety has not been established. It is not a controlled or scheduled substance, but lawful human use is by prescription only — it is not a dietary supplement, not an over-the-counter product, and not approved for cosmetic, athletic, or general anti-aging use anywhere. The approval is for one indication in one population; it does not extend credibility to any other use.
How it’s supplied & administered. As an approved drug it is dispensed as a lyophilized (freeze-dried) powder that must be reconstituted with the sterile diluent provided before injection. The route is subcutaneous, into the abdomen with site rotation, once daily; peptides of this size are not orally bioavailable, so any oral “tesamorelin” product is pharmacologically inert regardless of the label. The formulations are not interchangeable: EGRIFTA SV (2 mg/vial) is dosed at 1.4 mg daily, while the original EGRIFTA (1 mg/vial) used 2 mg daily with different reconstitution and storage, and EGRIFTA WR is a later reformulation with its own handling requirements. Vial strength, number of vials, diluent volume and storage all differ between them — a real dosing-error hazard when people switch or self-source.
Sourcing reality (a safety issue, not a footnote). Alongside the legitimate prescription product, tesamorelin powder is widely sold by research-chemical vendors labeled “for research use only / not for human consumption,” bought for bodybuilding and anti-aging self-experimentation entirely outside a prescription. That gray-market supply carries the usual unregulated-peptide risks: no manufacturing oversight, uncertain purity and actual peptide content, mislabeling, possible bacterial endotoxin contamination, and reconstitution or sterility errors by the end user. A vendor certificate of analysis is not regulatory oversight and can be falsified. None of the human efficacy data above were generated with such material. This page does not recommend or link vendors.
Safety
Tesamorelin is one of the few compounds here whose safety section can state findings rather than infer them — the profile is characterized by phase 3 trials and an FDA label. The monitoring is part of the drug: because it raises IGF-1, the label requires IGF-1 surveillance and contraindicates active malignancy, which is the strongest argument against unsupervized use.
- Contraindicated in pregnancy. Per the FDA label — see the box below.
- Active malignancy is a contraindication. Any pre-existing malignancy must be inactive and treatment complete before starting; stop on evidence of recurrence.
- Also contraindicated with a disrupted hypothalamic-pituitary axis or known hypersensitivity to tesamorelin or mannitol.
- Long-term cardiovascular safety is not established. Per the label; safety beyond roughly one to two years, and in any non-HIV population, is unknown.
- New or worsening glucose intolerance can develop and must be monitored, despite an unchanged group average at 52 weeks.
- GH-excess effects are dose-limiting in practice. Injection-site reactions, arthralgia, fluid retention, myalgia and carpal-tunnel symptoms.
Full Safety & Interactions Detail
Overall posture. Tesamorelin’s adverse-effect profile is well characterized from its HIV trials and its FDA label — a genuine advantage over almost every other compound on this hub, and the reason its safety section can state findings rather than infer them. The most common adverse events are injection-site reactions (erythema, pruritus, pain), arthralgia and musculoskeletal pain, peripheral edema and fluid retention, myalgia, and paraesthesia or carpal-tunnel symptoms — all consistent with growth-hormone excess, and all dose-limiting in practice.
IGF-1 and the neoplasia question. Because tesamorelin raises GH and therefore IGF-1, the label directs prescribers to monitor IGF-1 and to consider discontinuation if it remains persistently elevated. The consequences of long-term elevated IGF-1 are unknown, and the concern is explicitly theoretical-but-taken-seriously: active malignancy is a contraindication, any pre-existing malignancy must be inactive with treatment complete before starting, and the drug should be stopped on any evidence of recurrent malignancy. This is the single strongest reason self-administration outside medical supervision is a bad idea — the monitoring is part of the drug.
Glucose. New or worsening glucose intolerance and diabetes can develop and must be monitored, even though 52-week trial data showed no clinically significant average glucose change 4Reference 4RCTLong-term safety and effects of tesamorelin in HIV patients with abdominal fat accumulation — human (52-week randomised extension)View study →. GH-mediated insulin resistance is the mechanism; an unchanged group average does not mean no individual risk.
Contraindications (from the label): active malignancy; disruption of the hypothalamic-pituitary axis (hypophysectomy, hypopituitarism, pituitary tumor or surgery, head irradiation or trauma); known hypersensitivity to tesamorelin or to mannitol; and pregnancy.
Interactions. In healthy volunteers, tesamorelin had no significant effect on levels of simvastatin, a CYP3A substrate 24Reference 24EGRIFTA SV (tesamorelin) for injection - full prescribing informationView study →. The growth hormone it releases may alter the clearance of drugs metabolised by CYP450 enzymes, such as corticosteroids, sex steroids, anticonvulsants and cyclosporine, so these combinations are monitored 24Reference 24EGRIFTA SV (tesamorelin) for injection - full prescribing informationView study →. Broader interaction screening in off-label populations has not been done. Injection-specific risks — site reactions, sterility failure, contamination — apply doubly to gray-market reconstituted powder.
Long-term safety. The FDA label states that long-term cardiovascular safety is not established. Safety beyond roughly one to two years, and in any non-HIV population, is unknown.
Scope disclosure (honesty, not a claim):
- Human data? Yes — approval-grade phase 3 RCTs in the HIV lipodystrophy indication, plus smaller RCTs for liver fat and cognition. No efficacy data in healthy adults.
- Interactions assessed? Partially — the label carries a simvastatin (CYP3A) interaction study and a general CYP450 caution; broader interaction screening in off-label populations has not been done.
- Pregnancy/lactation assessed? Pregnancy yes — contraindicated per label. Lactation not established.
- Long-term safety established? No. The FDA label states long-term cardiovascular safety is not established; safety beyond ~1–2 years and in non-HIV populations is unknown.
Never imply safety from silence. Where tesamorelin has not been studied — healthy-adult cosmetic use, multi-year dosing, gray-market product purity — the correct statement is “not assessed,” not “safe.”
Contraindicated in pregnancy per the FDA label — the effects of elevated GH and IGF-1 on the fetus are a real concern, and there is no fetal benefit to weigh against them. Lactation: not established — no adequate human data; avoid.
Dosage
The doses below are the approved and studied doses in the HIV lipodystrophy indication, reported as data — they are not a recommendation, and none of this is medical advice. Tesamorelin is a prescription medicine; the appropriate dose, the IGF-1 and glucose monitoring that accompany it, and the decision to use it at all belong to a prescriber.
The approved regimen is subcutaneous, once daily, into the abdomen. EGRIFTA SV (2 mg/vial) is dosed at 1.4 mg daily; the original EGRIFTA (1 mg/vial) was dosed at 2 mg daily with different reconstitution and storage, and EGRIFTA WR is a later reformulation with its own handling. These are not interchangeable — matching a dose number to the wrong vial strength is a real error. The phase 3 efficacy trials used 2 mg SC daily over 26 and 52 weeks 1,
There is no established dose for any off-label use — not for cosmetic fat loss, muscle, or anti-aging, because no trial has established efficacy for those uses to dose toward. Benefit is also maintenance-dependent: visceral fat re-accumulates after discontinuation 4Reference 4RCTLong-term safety and effects of tesamorelin in HIV patients with abdominal fat accumulation — human (52-week randomised extension)View study →, so the trial results describe continuous dosing, not a course. Oral products cannot deliver intact peptide (see Pharmacokinetics), whatever the label claims.
References
- Falutz J, et al. (2007). Metabolic effects of a growth hormone-releasing factor in patients with HIV — human (phase 3 RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/18057338/
- Falutz J, et al. (2010). Effects of tesamorelin, a growth hormone-releasing factor, in HIV-infected patients with abdominal fat accumulation — human (RCT with safety extension). J Acquir Immune Defic Syndr. https://pubmed.ncbi.nlm.nih.gov/20101189/
- Falutz J, et al. (2010). Effects of tesamorelin (TH9507), a growth hormone-releasing factor analog, in HIV-infected patients with excess abdominal fat — human (pooled analysis of two phase 3 RCTs). J Clin Endocrinol Metab. https://pubmed.ncbi.nlm.nih.gov/20554713/
- Falutz J, et al. (2008). Long-term safety and effects of tesamorelin in HIV patients with abdominal fat accumulation — human (52-week randomised extension). AIDS. https://pubmed.ncbi.nlm.nih.gov/18690162/
- Falutz J, et al. (2005). A placebo-controlled, dose-ranging study of a growth hormone-releasing factor in HIV-infected patients with abdominal fat accumulation — human (RCT). AIDS. https://pubmed.ncbi.nlm.nih.gov/16052083/
- Stanley TL, et al. (2014). Effect of tesamorelin on visceral fat and liver fat in HIV-infected patients with abdominal fat accumulation — human (RCT). JAMA. https://pubmed.ncbi.nlm.nih.gov/25038357/
- Badran AS, et al. (2026). Body composition, hepatic fat, metabolic, and safety outcomes of tesamorelin in HIV-associated lipodystrophy — meta-analysis of human RCTs. Obesity Research & Clinical Practice. https://pubmed.ncbi.nlm.nih.gov/41545261/
- Stanley TL, et al. (2019). Effects of tesamorelin on non-alcoholic fatty liver disease in HIV — human (randomised, double-blind, multicentre trial). Lancet HIV. https://pubmed.ncbi.nlm.nih.gov/31611038/
- Fourman LT, et al. (2020). Effects of tesamorelin on hepatic transcriptomic signatures in HIV-associated NAFLD — human (RCT biopsy sub-study). JCI Insight. https://pubmed.ncbi.nlm.nih.gov/32701508/
- Stanley TL, et al. (2021). Growth hormone-releasing hormone reduces circulating markers of immune activation in parallel with effects on hepatic immune pathways — human (RCT proteomic sub-study). Clinical Infectious Diseases. https://pubmed.ncbi.nlm.nih.gov/33852720/
- Lake JE, et al. (2021). Tesamorelin improves fat quality independent of changes in fat quantity — human (analysis of two randomised trials). AIDS. https://pubmed.ncbi.nlm.nih.gov/33756511/
- Adrian S, et al. (2019). The growth hormone-releasing hormone analogue tesamorelin decreases muscle fat and increases muscle area in adults with HIV — human (exploratory analysis of randomised trials). Journal of Frailty & Aging. https://pubmed.ncbi.nlm.nih.gov/31237318/
- Makimura H, et al. (2014). The effects of tesamorelin on phosphocreatine recovery in obese subjects with reduced growth hormone — human (RCT). J Clin Endocrinol Metab. https://pubmed.ncbi.nlm.nih.gov/24178787/
- Baker LD, et al. (2012). Effects of growth hormone-releasing hormone on cognitive function in adults with mild cognitive impairment and healthy older adults — human (RCT). Archives of Neurology. https://pubmed.ncbi.nlm.nih.gov/22869065/
- Friedman SD, et al. (2013). Growth hormone-releasing hormone effects on brain GABA levels in mild cognitive impairment and healthy aging — human (randomised sub-study). JAMA Neurology. https://pubmed.ncbi.nlm.nih.gov/23689947/
- Ellis RJ, et al. (2025). Effects of tesamorelin on neurocognitive impairment in persons with HIV and abdominal obesity — human (phase 2 RCT). Journal of Infectious Diseases. https://pubmed.ncbi.nlm.nih.gov/39813152/
- Stewart CE, et al. (2026). The effect of growth hormone-releasing hormone on cognition and brain connectivity in adults with cognition rated normal to mildly impaired — human (placebo-controlled pilot trial). eNeurologicalSci. https://pubmed.ncbi.nlm.nih.gov/42382101/
- Russo SC, et al. (2024). Efficacy and safety of tesamorelin in people with HIV on integrase inhibitors — human (randomised double-blind trial). AIDS. https://pubmed.ncbi.nlm.nih.gov/38905488/
- González-Sales M, et al. (2015). Population pharmacokinetic analysis of tesamorelin in HIV-infected patients and healthy subjects — human (population PK). Clinical Pharmacokinetics. https://pubmed.ncbi.nlm.nih.gov/25358450/
- Ferdinandi ES, et al. (2007). Non-clinical pharmacology and safety evaluation of TH9507, a human growth hormone-releasing factor analogue — animal (rat/dog/pig). Basic & Clinical Pharmacology & Toxicology. https://pubmed.ncbi.nlm.nih.gov/17214611/
- Erlandson KM, et al. (2026). Tesamorelin as an adjunct to exercise for improving physical function in HIV (TRIUMPH) — human (clinical trial protocol). BMJ Open. https://pubmed.ncbi.nlm.nih.gov/42419889/
- Dhillon S. (2011). Tesamorelin: a review of its use in the management of HIV-associated lipodystrophy — review. Drugs. https://pubmed.ncbi.nlm.nih.gov/21668043/
- Theratechnologies / FDA (2010). FDA approves EGRIFTA (tesamorelin for injection) for reduction of excess abdominal fat in HIV-infected patients with lipodystrophy. https://www.fiercebiotech.com/biotech/fda-approves-egrifta%E2%84%A2-tesamorelin-for-injection-first-and-only-treatment-for-reduction-of
- DailyMed / FDA. EGRIFTA SV (tesamorelin) for injection - full prescribing information. Initial U.S. approval 2010. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=3d783378-b02d-4f19-99dd-0fc91a042224



