
Sources · 10
Where Does It Come From?
 Principal source Barberry Berberis spp. Herb monograph →
 Source Abuta Cissampelos pareira Herb monograph →
 Source California Poppy Eschscholzia californica Herb monograph →
 Source Coptis Coptis chinensis Herb monograph →
 Source Goldenseal Hydrastis canadensis Herb monograph →
 Source Greater Celandine Chelidonium majus Herb monograph →
Concentration
Content by Source
Reported concentrations across the plants that contain berberine — the bar marks the typical level, the line shows the reported range.
Literature figures for varying plant parts and preparations. Read them as a comparative guide, not exact assays.
Berberine at a Glance
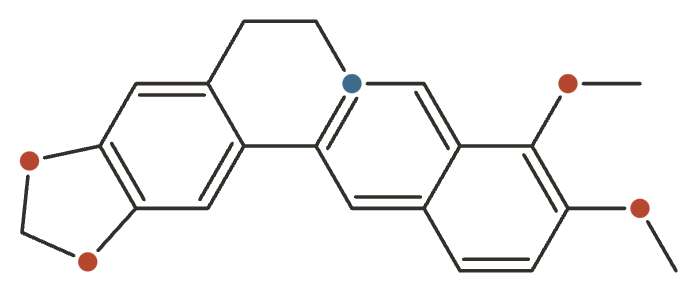
Berberine is a bright yellow isoquinoline alkaloid found in goldenseal, Oregon grape, barberry and Coptis, used for centuries in Chinese and Ayurvedic medicine and long recognisable as a dye.
Its modern interest is metabolic. Berberine activates AMPK, the cell’s energy sensor — the same target as metformin — which is why it is one of the few plant compounds with genuine glucose-lowering and lipid-lowering activity rather than a purely traditional reputation.
What It’s Used For
- Glycemic control — lowers blood glucose and HbA1c.
- Cholesterol & triglycerides — lowers LDL cholesterol and triglycerides.
- Polycystic ovary syndrome (PCOS) — improves insulin resistance and ovulation in PCOS.
- Fatty liver (NAFLD) — improves liver fat and enzymes.
- Gut antimicrobial & antidiarrheal — its traditional use, against bacterial diarrhea.
How It Works
Berberine’s central action is AMPK activation, achieved indirectly by mildly inhibiting mitochondrial complex I — the cell reads the resulting dip in energy charge as scarcity and switches on glucose uptake and fatty-acid oxidation while switching off synthesis. That single lever explains the glucose, lipid, liver and PCOS effects together.
Two further routes matter. It upregulates the LDL receptor through a mechanism distinct from statins, which is why the cholesterol effect is additive with them. And because oral bioavailability is very low, much of what berberine does happens in the gut — altering the microbiome and acting directly on gut bacteria, which is both its traditional antimicrobial use and part of its metabolic effect.
The full detail is in Pharmacology & Research below.
Pharmacology & Research
Berberine is a quaternary isoquinoline (protoberberine) alkaloid — the bright-yellow pigment of barberry, goldthread and goldenseal roots. For a single plant molecule it has an unusually large clinical literature, and almost all of it is on the isolated compound: multiple randomized trials and meta-analyses support modest metabolic benefits (blood sugar, cholesterol, fatty liver), while its classic antimicrobial activity is largely in vitro. One fact frames everything else — oral bioavailability is under ~1%, so most of what berberine does happens in the gut and liver rather than through high blood levels 9Reference 9ReviewApproaching strategy to increase the oral bioavailability of berberine, a quaternary isoquinoline alkaloid — reviewView study →.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume, tempered for isolate-vs-plant match and bioavailability. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric, and I’ll keep honing it. Each application links down to its write-up.
Berberine’s strongest evidence. A 2008 double-blind RCT (n=116, 1 g/day, 3 months) lowered HbA1c and fasting and post-prandial glucose versus placebo 1Reference 1RCTTreatment of type 2 diabetes and dyslipidemia with the natural plant alkaloid berberine — randomised controlled trialView study →.
A separate 2008 trial ran berberine 0.5 g three times daily head-to-head with metformin in newly diagnosed type 2 diabetes and found a similar glucose-lowering effect, with HbA1c falling roughly 2 percentage points 2Reference 2RCTEfficacy of berberine in patients with type 2 diabetes mellitus — randomised trial (head-to-head vs metformin)View study →.
A 2015 meta-analysis of 27 trials (2,569 patients) concluded berberine performed comparably to standard oral hypoglycemics with no serious adverse events 3Reference 3Meta-analysisMeta-analysis of the effect and safety of berberine in the treatment of type 2 diabetes mellitus, hyperlipemia and hypertension — meta-analysis (27 trials, n=2,569)View study →.
All used the isolated molecule.
Gap: the trials are overwhelmingly small, short and single-region with high risk of bias — “comparable to metformin” is a short-term signal, not established equivalence 3Reference 3Meta-analysisMeta-analysis of the effect and safety of berberine in the treatment of type 2 diabetes mellitus, hyperlipemia and hypertension — meta-analysis (27 trials, n=2,569)View study →.
A 2023 systematic review and meta-analysis of 18 placebo-controlled RCTs (n=1,788, 0.9–1.5 g/day) found berberine reduced LDL cholesterol by about 0.46 mmol/L, with similar falls in total cholesterol and triglycerides, a small sex-specific HDL rise, and no serious adverse events 4Reference 4Meta-analysisOverall and sex-specific effect of berberine for the treatment of dyslipidemia in adults — systematic review and meta-analysis of randomised placebo-controlled trials (18 RCTs, n=1,788)View study →.
Gap: the effect sizes are modest (LDL ≈ 18 mg/dL) and heterogeneity across trials is high — berberine reads as an adjunct, not a statin substitute 4Reference 4Meta-analysisOverall and sex-specific effect of berberine for the treatment of dyslipidemia in adults — systematic review and meta-analysis of randomised placebo-controlled trials (18 RCTs, n=1,788)View study →.
A multicenter RCT (n=184, 0.5 g three times daily plus lifestyle, 16 weeks) cut hepatic fat significantly more than lifestyle alone and beat pioglitazone on weight and lipids 5Reference 5RCTEfficacy of berberine in patients with non-alcoholic fatty liver disease — randomised controlled trial (n=184)View study →. A meta-analysis of 6 RCTs (n=501) likewise found improvements in liver enzymes, lipids and glucose versus controls 6Reference 6Meta-analysisThe therapeutic effect of berberine in the treatment of nonalcoholic fatty liver disease — meta-analysis (6 RCTs, n=501)View study →.
Gap: the trials are few and of limited quality, and imaging endpoints (liver-fat fraction) carry more weight than the enzyme changes often reported 6Reference 6Meta-analysisThe therapeutic effect of berberine in the treatment of nonalcoholic fatty liver disease — meta-analysis (6 RCTs, n=501)View study →.
A 2019 meta-analysis of 12 RCTs found berberine may improve insulin resistance, androgen levels and the LH/FSH ratio in women with PCOS, sometimes comparably to metformin 7Reference 7Meta-analysisThe effect of berberine on reproduction and metabolism in women with polycystic ovary syndrome — systematic review and meta-analysis of randomised controlled trials (12 RCTs)View study →.
Gap: the evidence is smaller and more heterogeneous than for diabetes, and there is no solid evidence berberine improves live birth or other hard reproductive outcomes 7Reference 7Meta-analysisThe effect of berberine on reproduction and metabolism in women with polycystic ovary syndrome — systematic review and meta-analysis of randomised controlled trials (12 RCTs)View study →.
Berberine is a traditional remedy for infectious diarrhea and has broad in-vitro activity against bacteria (including drug-resistant strains), fungi and protozoa; genetic work shows one key antibacterial mechanism is inhibition of the bacterial cell-division protein FtsZ, rather than DNA binding 8Reference 8In vitroGenetic evidence for inhibition of bacterial division protein FtsZ by berberine — in vitroView study →. Because oral berberine concentrates in the gut lumen rather than the bloodstream, any real effect is plausibly enteric.
Gap: robust human trials for infection are lacking, and systemic antimicrobial use is precluded by <1% bioavailability 8,
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| AMPK activation | ↑ glucose uptake, ↓ hepatic gluconeogenesis & lipogenesis | glycemic controlcholesterolfatty liver |
| Hepatic LDL-receptor upregulation | ↑ LDL clearance from blood | cholesterol & triglycerides |
| Gut-microbiota modulation | altered bile-acid & short-chain-fatty-acid signaling | glycemic controlfatty liver |
| Bacterial FtsZ inhibition | blocks cell division (bacteriostatic) | gut antimicrobial |
Pharmacokinetics
Berberine’s defining pharmacological fact is poor oral bioavailability — under ~1% (reported as low as ~0.4% in animals) — the result of low solubility, self-aggregation, extensive first-pass metabolism and active efflux back into the gut by P-glycoprotein 9Reference 9ReviewApproaching strategy to increase the oral bioavailability of berberine, a quaternary isoquinoline alkaloid — reviewView study →. It is metabolized to several active or semi-active metabolites (berberrubine, thalifendine, demethyleneberberine, jatrorrhizine), and the gut microbiota convert some berberine to dihydroberberine, a reduced form that is absorbed far better 9,
Clinical trials
Berberine has been tested in many investigator-led randomized trials — chiefly in type 2 diabetes, dyslipidemia, NAFLD and PCOS — but as an off-patent natural product it attracts little registered industry-sponsored trial activity.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| Many(metabolic) | Several | — | Extensive |
Last checked: July 2026.
Monoamine oxidase (MAO) inhibition
Berberine is also a weak monoamine oxidase inhibitor — a reported IC50 around 126 µM for MAO-A, with similarly high (weak) MAO-B values 18Reference 18Monoamine oxidase inhibitors from rhizoma of Coptis chinensisView study → — i.e. concentrations far higher than those at which it acts on its metabolic targets. MAO inhibition is therefore a minor footnote in berberine’s pharmacology rather than a primary mechanism, and it is comfortably outclassed by the flavonoid and β-carboline inhibitors covered in the natural MAO inhibitors guide.
Isolate vs. Plant Studies
Almost all of berberine’s clinical evidence comes from the isolated molecule — the diabetes, lipid, NAFLD and PCOS trials used purified berberine (typically the hydrochloride salt), not whole-plant preparations 1,
Prevalence in Nature
Berberine is made by plants across at least five families — Ranunculaceae (Coptis, Hydrastis/goldenseal, Xanthorhiza), Berberidaceae (Berberis, Mahonia, Nandina), Rutaceae (Phellodendron, Zanthoxylum), Papaveraceae (Argemone, Eschscholzia/California poppy, Sanguinaria) and Menispermaceae 11Reference 11ReviewBerberine: botanical occurrence, traditional uses, extraction methods, and relevance in cardiovascular, metabolic, hepatic, and renal disorders — reviewView study →. It concentrates in roots, rhizomes and bark rather than leaves: the richest sources are the rhizomes of Coptis species and the inner bark of Phellodendron amurense (Amur cork tree), reported from the low single digits up to roughly 8% of dry weight, with Berberis stem/bark and goldenseal rhizome lower 11Reference 11ReviewBerberine: botanical occurrence, traditional uses, extraction methods, and relevance in cardiovascular, metabolic, hepatic, and renal disorders — reviewView study →.
Biosynthetically it is a benzylisoquinoline alkaloid built from two molecules of the amino acid tyrosine. The pathway runs through (S)-reticuline — the branch-point of this whole alkaloid family — to (S)-scoulerine in the committed step, catalyzed by the berberine bridge enzyme, a flavin-dependent oxidase that forms the characteristic “berberine bridge” carbon, and then on through canadine to berberine 12Reference 12Berberine bridge enzyme, converting (S)-reticuline to (S)-scoulerine in benzylisoquinoline alkaloid biosynthesis — plant biochemistryView study →. Berberine is essentially a plant product, with no established natural animal, fungal or bacterial source; recent work has both shown the pathway can evolve convergently (Phellodendron forms the bridge with a different, cytochrome-P450 enzyme) and reconstructed the full route in engineered yeast 13Reference 13Convergent evolution of berberine biosynthesis — plant genomicsView study →.
Discovery & Synthesis
Berberine was first isolated in the early nineteenth century and takes its name from the genus Berberis (barberry), from which it was among the first alkaloids obtained; its vivid yellow color made it a dye long before its pharmacology was studied 11Reference 11ReviewBerberine: botanical occurrence, traditional uses, extraction methods, and relevance in cardiovascular, metabolic, hepatic, and renal disorders — reviewView study →. The first total chemical synthesis was reported by Kametani and co-workers in 1969 (as the iodide salt) 17Reference 17Molecule of the Week: BerberineView study →. Commercially, though, berberine is almost never synthesized: the plants that make it — chiefly Coptis chinensis rhizome (huánglián), Phellodendron bark and Berberis species — are so rich in it that solvent extraction is far cheaper than total or semi-synthesis, so essentially all supplement-grade berberine (usually berberine hydrochloride) is plant-extracted 11Reference 11ReviewBerberine: botanical occurrence, traditional uses, extraction methods, and relevance in cardiovascular, metabolic, hepatic, and renal disorders — reviewView study →.
Patents: not yet researched (future patent-loop pass).
Toxicity & Safety
Berberine is well tolerated at trial doses, and its drug interactions matter considerably more than its side effects — it inhibits three major drug-metabolizing enzymes, so the main risk is to what else you are taking.
- Well tolerated short-term. Trial adverse events are mostly gastrointestinal — constipation, diarrhea, cramping, nausea — more frequent than placebo but rarely serious.
- Inhibits CYP2D6, CYP2C9 and CYP3A4. Can raise blood levels of many medications; a real concern for narrow-margin drugs such as cyclosporine.
- Contraindicated in pregnancy, breastfeeding and neonates. Kernicterus risk — see the box below.
- No established maximum dose. Trials cap around 1.5 g/day; GI intolerance rises above that.
Full Safety & Interactions Detail
Berberine is generally well tolerated at the doses used in trials (~0.9–1.5 g/day), with adverse effects that are mostly gastrointestinal — constipation, diarrhea, cramping or nausea — more frequent than placebo but rarely serious 3,
The interactions matter more than the side effects: a controlled human study showed repeated oral berberine inhibits the drug-metabolizing enzymes CYP2D6, CYP2C9 and CYP3A4, so it can raise blood levels of many medications 14Reference 14Repeated administration of berberine inhibits cytochromes P450 in humansView study →, and it raised cyclosporine concentrations in kidney-transplant recipients, most likely through CYP3A4 inhibition — a clinically important effect for narrow-margin drugs 15Reference 15Effects of berberine on the blood concentration of cyclosporin A in renal transplanted recipients: clinical and pharmacokinetic studyView study →.
No formal maximum tolerated dose is established; trials generally cap around 1.5 g/day, above which GI intolerance rises 4,
Avoid. Berberine displaces bilirubin from serum albumin — in vitro far more potently than the reference drug phenylbutazone — and it crosses the placenta and enters breast milk; in a newborn, whose liver cannot yet clear bilirubin, this raises the risk of kernicterus (bilirubin brain injury) 16Reference 16In vitroDisplacement of bilirubin from albumin by berberine — in vitro and rat studyView study →. It is therefore contraindicated in pregnancy, breastfeeding and neonates 16,
Dosage
Clinical trials have most often used 900–1,500 mg per day of berberine (usually the hydrochloride), split into two or three doses with meals — divided dosing is standard because absorption is low and saturable 1,
| Application | Form | Dose (studied) | Source |
|---|---|---|---|
| Type 2 diabetes | Berberine HCl | 500 mg ×2–3/day | 1, |
| Dyslipidemia | Berberine HCl | 900–1,500 mg/day | 4Reference 4Meta-analysisOverall and sex-specific effect of berberine for the treatment of dyslipidemia in adults — systematic review and meta-analysis of randomised placebo-controlled trials (18 RCTs, n=1,788)View study → |
| NAFLD | Berberine HCl | 500 mg ×3/day | 5Reference 5RCTEfficacy of berberine in patients with non-alcoholic fatty liver disease — randomised controlled trial (n=184)View study → |
Bioavailability-enhanced forms (e.g. dihydroberberine, or berberine paired with absorption enhancers) reach higher plasma levels at lower doses but are less studied for hard outcomes 9Reference 9ReviewApproaching strategy to increase the oral bioavailability of berberine, a quaternary isoquinoline alkaloid — reviewView study →. These are doses studied in research and are not a personal recommendation — appropriateness depends on the individual, their medications (see interactions above) and professional guidance.
References
- Zhang Y, Li X, Zou D, Liu W, Yang J, Zhu N, et al. (2008). Treatment of type 2 diabetes and dyslipidemia with the natural plant alkaloid berberine — randomised controlled trial. Journal of Clinical Endocrinology & Metabolism, 93(7), 2559–2565. https://pubmed.ncbi.nlm.nih.gov/18397984/
- Yin J, Xing H, Ye J. (2008). Efficacy of berberine in patients with type 2 diabetes mellitus — randomised trial (head-to-head vs metformin). Metabolism, 57(5), 712–717. https://pubmed.ncbi.nlm.nih.gov/18442638/
- Lan J, Zhao Y, Dong F, Yan Z, Zheng W, Fan J, Sun G. (2015). Meta-analysis of the effect and safety of berberine in the treatment of type 2 diabetes mellitus, hyperlipemia and hypertension — meta-analysis (27 trials, n=2,569). Journal of Ethnopharmacology, 161, 69–81. https://pubmed.ncbi.nlm.nih.gov/25498346/
- Blais JE, Huang X, Zhao JV. (2023). Overall and sex-specific effect of berberine for the treatment of dyslipidemia in adults — systematic review and meta-analysis of randomised placebo-controlled trials (18 RCTs, n=1,788). Drugs, 83(5), 403–427. https://pubmed.ncbi.nlm.nih.gov/36941490/
- Yan HM, Xia MF, Wang Y, Chang XX, Yao XZ, Rao SX, et al. (2015). Efficacy of berberine in patients with non-alcoholic fatty liver disease — randomised controlled trial (n=184). PLoS ONE, 10(8), e0134172. https://pubmed.ncbi.nlm.nih.gov/26252777/
- Wei X, Wang C, Hao S, Song H, Yang L. (2016). The therapeutic effect of berberine in the treatment of nonalcoholic fatty liver disease — meta-analysis (6 RCTs, n=501). Evidence-Based Complementary and Alternative Medicine, 2016, 3593951. https://doi.org/10.1155/2016/3593951
- Xie L, Zhang D, Ma H, He H, Xia Q, Shen W, et al. (2019). The effect of berberine on reproduction and metabolism in women with polycystic ovary syndrome — systematic review and meta-analysis of randomised controlled trials (12 RCTs). Evidence-Based Complementary and Alternative Medicine, 2019, 7918631. https://pubmed.ncbi.nlm.nih.gov/31915452/
- Boberek JM, Stach J, Good L. (2010). Genetic evidence for inhibition of bacterial division protein FtsZ by berberine — in vitro. PLoS ONE, 5(10), e13745. https://pubmed.ncbi.nlm.nih.gov/21060782/
- Murakami T, Bodor E, Bodor N. (2023). Approaching strategy to increase the oral bioavailability of berberine, a quaternary isoquinoline alkaloid — review. Expert Opinion on Drug Metabolism & Toxicology, 19(3). https://pubmed.ncbi.nlm.nih.gov/37057922/
- Dehau T, Cherlet M, Croubels S, Van De Vliet M, Goossens E, Van Immerseel F. (2023). Berberine–microbiota interplay: modulation of the gut microbiota and metabolic transformation into bioactive metabolites — review. Frontiers in Pharmacology, 14, 1281090. https://doi.org/10.3389/fphar.2023.1281090
- Neag MA, Mocan A, Echeverría J, Pop RM, Bocsan CI, Crişan G, Buzoianu AD. (2018). Berberine: botanical occurrence, traditional uses, extraction methods, and relevance in cardiovascular, metabolic, hepatic, and renal disorders — review. Frontiers in Pharmacology, 9, 557. https://pubmed.ncbi.nlm.nih.gov/30186157/
- Bird DA, Facchini PJ. (2001). Berberine bridge enzyme, converting (S)-reticuline to (S)-scoulerine in benzylisoquinoline alkaloid biosynthesis — plant biochemistry. Planta, 213(6), 888–897. https://pubmed.ncbi.nlm.nih.gov/11722125/
- Xu Z, et al. (2024). Convergent evolution of berberine biosynthesis — plant genomics. Science Advances, 10, eads3596. https://pubmed.ncbi.nlm.nih.gov/39612339/
- Guo Y, Chen Y, Tan ZR, Klaassen CD, Zhou HH. (2012). Repeated administration of berberine inhibits cytochromes P450 in humans. European Journal of Clinical Pharmacology, 68(2), 213–217. https://pubmed.ncbi.nlm.nih.gov/21870106/
- Wu X, Li Q, Xin H, Yu A, Zhong M. (2005). Effects of berberine on the blood concentration of cyclosporin A in renal transplanted recipients: clinical and pharmacokinetic study. European Journal of Clinical Pharmacology, 61(8), 567–572. https://pubmed.ncbi.nlm.nih.gov/16133554/
- Chan E. (1993). Displacement of bilirubin from albumin by berberine — in vitro and rat study. Biology of the Neonate, 63(4), 201–208. https://pubmed.ncbi.nlm.nih.gov/8513024/
- American Chemical Society. Molecule of the Week: Berberine. https://www.acs.org/molecule-of-the-week/archive/b/berberine.html
- Kong, L. D., Cheng, C. H. K., & Tan, R. X. (2001). Monoamine oxidase inhibitors from rhizoma of Coptis chinensis. Planta Medica, 67(1), 74-76. https://pubmed.ncbi.nlm.nih.gov/11270727/