
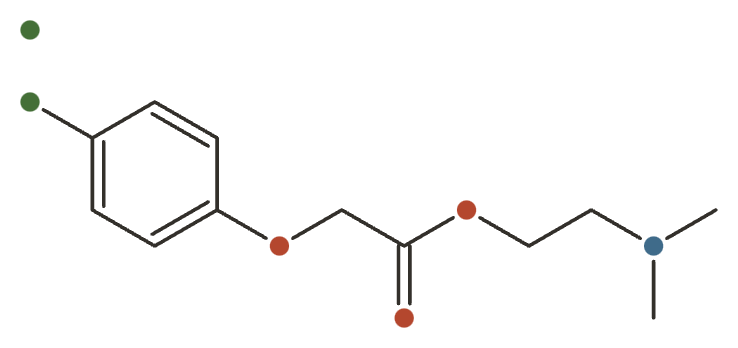
Centrophenoxine
A synthetic DMAE-ester nootropic marketed for "brain energy" and lipofuscin reduction — on evidence that is mostly old, animal, or low-quality clinical work.

Centrophenoxine at a Glance
Centrophenoxine (meclofenoxate) is a synthetic ester that pairs DMAE with 4-chlorophenoxyacetic acid — a lipid-soluble prodrug designed to carry DMAE across the blood–brain barrier. It has been sold since the 1960s under names like Lucidril and Helfergin, and it remains an approved medicine in some countries for cerebrovascular and cognitive disorders while being an unregulated nootropic supplement elsewhere.
It is wholly synthetic with no dietary source, and it is not a nutrient — there is no deficiency to correct.
It is best known for one distinctive claim: clearing lipofuscin, the fluorescent “age pigment” that accumulates in aged neurons. The framing that matters is that this is a mechanism-rich but clinically thin compound. The problem is not that it does nothing — the lipofuscin and antioxidant effects are real and reproducible in rodents and cell culture. The problem is that almost the entire human evidence base consists of small, methodologically weak trials from the 1970s and 80s, with no modern adequately powered study of any kind.
The honest bottom line: read it as a historical dossier. The animal story is genuinely interesting; nothing establishes that it translates into benefit for a living person, and the pigment-clearing effect has never been demonstrated in humans at all.
What It’s Used For
Ranked by how well the evidence holds up — which here means ranking things that are mostly preclinical:
- Cognition and memory — several small 1970s–80s controlled trials in elderly and mildly demented patients; mixed, weak, never replicated.
- Lipofuscin reduction — the signature claim, robust in aged rodents and cell culture, and never shown in a living human.
- Antioxidant neuroprotection — consistent in rodent toxicity models; no human data.
- Longevity — one unreplicated 1973 mouse study plus a theory.
Be sceptical of the whole “brain energy,” anti-aging and lipofuscin-clearing pitch aimed at healthy users. It rests on animal data and on 40- to 50-year-old clinical work that contemporary reviewers judged small, methodologically weak and inconclusive. And note the safety inheritance that marketing omits: centrophenoxine is a DMAE prodrug, so it carries DMAE’s developmental-safety caution. This is not a benign “basically a vitamin” molecule.
How It Works
Centrophenoxine is a delivery vehicle. On its own, DMAE does not cross into the brain especially well; esterifying it to 4-chlorophenoxyacetic acid makes the molecule lipid-soluble enough to get there, after which it is hydrolysed back into its two components. That design is the whole point of the compound — and it is confirmed by the pharmacokinetics, where the parent ester is not detectable in plasma at all 17Reference 17RCTBioequivalence and pharmacokinetic comparison of a single 200-mg dose of meclofenoxate hydrochloride capsule and tablet formulations in healthy Chinese adult male volunteers — randomised crossover studyView study →.
Once delivered, the DMAE moiety supplies the putative cholinergic rationale — the same disputed one that applies to DMAE itself.
The more distinctive mechanism is lipofuscin scavenging. Lipofuscin is cross-linked, oxidised cellular debris that accumulates with age and cannot be degraded normally. Centrophenoxine reduces it in aged rodent neurons and in cultured human retinal pigment epithelial cells 6,
Those last two threads feed the “membrane hypothesis of aging”: the idea that free-radical cross-linking damages compact cellular structures faster than dilute ones, and that a compound which both fluidises membranes and scavenges radicals should counter it 15Reference 15ReviewOn the role of intracellular physicochemistry in quantitative gene expression during aging and the effect of centrophenoxine — reviewView study →. It is an elegant theory. It has one old mouse life-span study behind it.
Pharmacology & Research
Centrophenoxine (meclofenoxate; brand names Lucidril, Helfergin) is a synthetic cholinergic nootropic — an ester that pairs DMAE (dimethylaminoethanol) with 4-chlorophenoxyacetic acid, acting as a lipid-soluble prodrug that delivers DMAE across the blood–brain barrier. It has been marketed since the 1960s for “brain energy,” memory, and — most distinctively — for clearing lipofuscin, the fluorescent “age pigment” that accumulates in aged neurons. The problem is not that the compound does nothing; it is that almost the entire evidence base is either decades-old, small, methodologically weak human trials or animal and in-vitro work, with essentially no modern, adequately powered human data. Read what follows as a historical, mechanism-rich but clinically thin dossier: the lipofuscin and antioxidant stories are real in rodents and cell culture, but their translation to benefit in healthy people is unproven.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
The human cognition data are old, small and mixed. A double-blind controlled trial in fit, able elderly subjects reported that meclofenoxate improved consolidation of new information into long-term memory and raised self-reported alertness, without affecting other memory domains 1Reference 1Clinical trialThe differential effects of meclofenoxate on memory loss in the elderly — controlled clinical trialView study →.
In medium-level dementia (DSM-III, average age 77), an 8-week double-blind trial at 2 g/day found memory improvement in 48% of the treated group vs 28% on placebo using the Nürnberger Alters-Inventar 2Reference 2RCTGerontopsychological studies using NAI on patients with organic psychosyndrome treated with centrophenoxine in a double-blind, randomized clinical trialView study → — a real but modest signal in a small, single-centre study. A companion trial in the same cohort measured body composition and biochemistry rather than cognition per se 3Reference 3RCTEffects of centrophenoxine on body composition and some biochemical parameters of demented elderly people as revealed in a double-blind clinical trialView study →.
A separate double-blind collaborative study examined centrophenoxine in neurasthenic syndromes 4Reference 4RCTDouble-blind collaborative study of centrophenoxine versus placebo in patients with neurasthenic syndromes — clinical trialView study →.
Contemporary critical reviews of centrophenoxine in senile dementia concluded the trials were small, methodologically weak and inconclusive 5Reference 5Clinical trialCritical review of clinical trials in senile dementia — reviewView study →, and no adequately powered modern trial exists.
Gap: the entire human cognition case rests on small, decades-old trials of variable quality with no modern replication; the benefit — where seen — is limited and in impaired, not healthy, populations.
This is centrophenoxine’s signature claim and its best-characterised mechanism — but the evidence is preclinical. Classic work showed that treating senile guinea pigs 6Reference 6Effect of centrophenoxine on the lipofuscin pigments in the neurones of senile guinea-pigsView study → and aged mice 7Reference 7AnimalLipofuscinogenesis in mice early treated with centrophenoxineView study → reduced neuronal lipofuscin in cerebral cortex and hippocampus over weeks of dosing. Early treatment slowed, though did not prevent, pigment accumulation 7Reference 7AnimalLipofuscinogenesis in mice early treated with centrophenoxineView study →.
In cultured human retinal pigment epithelial cells, centrophenoxine acted as a lipofuscin scavenger and, with a calcium-channel blocker, reduced pigment formation 8Reference 8In vitroCalcium overload is associated with lipofuscin formation in human retinal pigment epithelial cells fed with photoreceptor outer segments — in vitroView study →.
It also reversed “dark cell” (stressed neuron) formation in protein-malnourished rat cerebellum 9Reference 9James TJ, Sharma SP. (1992). ‘Dark’ cell formation under protein malnutrition: process of conversion and concept of ‘semi-dark’ type Purkinje cells — animal study. Indian Journal of Experimental Biology. https://pubmed.ncbi.nlm.nih.gov/1506025/View study →.
What is missing is any demonstration that this pigment reduction occurs in living humans or that it translates into cognitive or functional benefit.
Gap: lipofuscin clearance is reproducible in rodents and cell culture but has never been shown in people, and lipofuscin reduction is not itself an established route to better cognition or longer life.
In rodent toxicity models, centrophenoxine behaves as a neuroprotective antioxidant. In a rotenone model of Parkinson’s disease it attenuated motor dysfunction, restored glutathione, and reduced lipid peroxidation in dopaminergic regions 11Reference 11AnimalEffect of centrophenoxine against rotenone-induced oxidative stress in an animal model of Parkinson’s disease — animal studyView study →.
In aluminium-exposed rats it reversed redox disturbances across brain regions 13Reference 13AnimalReversal of an aluminium induced alteration in redox status in different regions of rat brain by administration of centrophenoxine — animal studyView study → and limited biochemical and histological damage 12Reference 12AnimalFurther evidence of centrophenoxine mediated protection in aluminium exposed rats by biochemical and light microscopy analysis — animal studyView study →.
Mechanistically, in a Fenton-reaction system it showed modest hydroxyl-radical scavenging — less potent than pyritinol, more than piracetam 10Reference 10In vitroProtection of cell proteins against free-radical attack by nootropic drugs — in vitro / ESR studyView study →.
These are consistent, mechanism-plausible findings, but every one is in animals or cell-free systems.
Gap: no human data; the antioxidant/neuroprotective effect is entirely preclinical and cannot be assumed to occur at tolerated human doses.
The anti-aging framing traces to a single 1973 study reporting extended life span in old male mice given the DMAE-p-chlorophenoxyacetate ester 16Reference 16AnimalEffect of dimethylaminoethyl p-chlorophenoxyacetate on the life span of male Swiss Webster Albino mice — animal studyView study →, read through the “membrane hypothesis of aging” — the idea that free-radical cross-linking damages compact cell structures (membranes) faster than dilute ones, and that centrophenoxine’s membrane-fluidising 14Reference 14In vitroFluidizing effects of centrophenoxine in vitro on brain and liver membranes from different age groups of mice — in vitroView study → and radical-scavenging actions counter this 15Reference 15ReviewOn the role of intracellular physicochemistry in quantitative gene expression during aging and the effect of centrophenoxine — reviewView study →. It is an elegant theory with one old, unreplicated rodent life-span result behind it.
Gap: a single decades-old mouse study plus mechanistic theory; no replication and no human longevity evidence of any kind.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| DMAE delivery (prodrug hydrolysis) | ↑ CNS DMAE; putative precursor pool for choline/acetylcholine | Cognitionmemory |
| Neuronal lipofuscin | ↓ accumulation / scavenging of age pigment | Lipofuscin reductionlongevity |
| Hydroxyl-radical scavenging | ↓ free-radical protein/lipid damage (modest) 10Reference 10In vitroProtection of cell proteins against free-radical attack by nootropic drugs — in vitro / ESR studyView study → | Antioxidant neuroprotectionlongevity |
| Glutathione / lipid peroxidation | ↑ GSH, ↓ LPO in toxicant-stressed brain 11, | Antioxidant neuroprotection |
| Membrane fluidity | ↑ fluidity of synaptic & liver membranes (in vitro) 14Reference 14In vitroFluidizing effects of centrophenoxine in vitro on brain and liver membranes from different age groups of mice — in vitroView study → | Longevity (membrane hypothesis) |
Pharmacokinetics
Centrophenoxine is a prodrug: after oral dosing it is hydrolysed to its two components, and the parent ester is not detected in plasma 17Reference 17RCTBioequivalence and pharmacokinetic comparison of a single 200-mg dose of meclofenoxate hydrochloride capsule and tablet formulations in healthy Chinese adult male volunteers — randomised crossover studyView study →. In a bioequivalence study, the active circulating metabolite measured was 4-chlorophenoxyacetic acid (DMAE being the other, cholinergic moiety) 17Reference 17RCTBioequivalence and pharmacokinetic comparison of a single 200-mg dose of meclofenoxate hydrochloride capsule and tablet formulations in healthy Chinese adult male volunteers — randomised crossover studyView study →. The chlorophenoxyacetate design is what makes the molecule lipid-soluble enough to carry DMAE into the CNS. Formal half-life and food-effect data in the modern sense are sparse; the compound is short-acting and was typically dosed 2–3 times daily in older trials. Doses used clinically span ~200 mg single doses in PK work up to ~1–2 g/day in the dementia trials.
Clinical trials
Registered modern trial activity is minimal. Centrophenoxine is an old, off-patent molecule with little commercial incentive for new trials; most human evidence predates the ClinicalTrials.gov era. It remains an approved drug in some countries (e.g. China, parts of Europe) for indications such as cerebrovascular and cognitive disorders, but is sold elsewhere as an unregulated nootropic supplement.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~10(mostly 1966–1994, small) | 0 | 0 | ~40+ |
Last checked: August 2026.
Dietary Sources
Centrophenoxine is a wholly synthetic molecule — it does not occur in food and has no dietary source. It is manufactured by esterifying DMAE with 4-chlorophenoxyacetic acid; the chlorophenoxyacetate group makes the molecule lipid-soluble enough to ferry DMAE across the blood–brain barrier, where it is hydrolysed back to its two components 17Reference 17RCTBioequivalence and pharmacokinetic comparison of a single 200-mg dose of meclofenoxate hydrochloride capsule and tablet formulations in healthy Chinese adult male volunteers — randomised crossover studyView study →.
The one dietary connection is indirect: DMAE itself occurs in trace amounts in some oily fish (sardines, anchovies) and is made endogenously in small quantities. If the goal is simply raising DMAE, oily fish supplies it in food — centrophenoxine is a pharmaceutical delivery form, not a nutrient.
Dosage
There is no RDA, AI, or Tolerable Upper Intake Level for centrophenoxine — it is a drug/nootropic, not an essential nutrient. Doses studied in research, not a personal recommendation:
| Context | Dose used | Source |
|---|---|---|
| Dementia / elderly cognition trials | ~1–2 g/day, split | 2, |
| Pharmacokinetic study (healthy men) | 200 mg single dose | 17Reference 17RCTBioequivalence and pharmacokinetic comparison of a single 200-mg dose of meclofenoxate hydrochloride capsule and tablet formulations in healthy Chinese adult male volunteers — randomised crossover studyView study → |
| Common nootropic self-use | ~250–500 mg, 1–3×/day | not from controlled trials |
Because it is a short-acting prodrug, older regimens split the dose across the day. It is typically taken earlier in the day, as the alerting effect can disrupt sleep. There is no established maximum-safe daily intake, and the gram-level doses in the trials were used under supervision in impaired elderly patients — they should not be read as a validated healthy-adult dose.
Safety
Human safety data are old and limited, and the most important point is inherited rather than measured.
- Avoid in pregnancy. Centrophenoxine delivers DMAE, which carries developmental-safety signals from animal embryo models. No human data offset this.
- Cholinergic side effects are the common ones — agitation, insomnia, irritability, headache and occasionally muscle tension or jaw tightness, generally dose-related.
- Human safety data are old and thin. The only modern study is a single-dose 200 mg pharmacokinetic trial 17Reference 17RCTBioequivalence and pharmacokinetic comparison of a single 200-mg dose of meclofenoxate hydrochloride capsule and tablet formulations in healthy Chinese adult male volunteers — randomised crossover studyView study →.
- May add to other cholinergic or stimulant compounds. Caution is reasonable with seizure disorders, bipolar disorder, or cholinergic medication — though formal interaction studies are lacking.
- No upper limit is set. Not a nutrient; the absence of a ceiling means it has not been characterised, not that it is high.
Full Safety & Interactions Detail
Human safety data are old and limited. In the one modern pharmacokinetic study, healthy men taking a single 200 mg dose were monitored for excitement, insomnia, lassitude and headache; the formulations were tolerated in that short single-dose setting 17Reference 17RCTBioequivalence and pharmacokinetic comparison of a single 200-mg dose of meclofenoxate hydrochloride capsule and tablet formulations in healthy Chinese adult male volunteers — randomised crossover studyView study →. Reported adverse effects from the cholinergic/DMAE activity include agitation, insomnia, irritability, headache and (rarely) muscle tension or jaw tightness, generally dose-related.
As a DMAE ester it inherits DMAE’s cautions — DMAE has a longstanding record of developmental-toxicity signals in animal work, which is the basis for avoiding it in pregnancy. Centrophenoxine may add to the effects of other cholinergic or stimulant compounds; caution is reasonable in people with seizure disorders, bipolar disorder, or on cholinergic medications, though formal interaction studies are lacking.
Scope disclosure. Interactions assessed? Partially — no formal drug-interaction studies were found; the cautions here are inferred from its cholinergic/DMAE pharmacology, not from interaction trials. Pregnancy/lactation assessed? No — no human data; avoidance is precautionary, based on the DMAE component. Upper limit established? No — absence of a UL does not mean high doses are safe, it means the ceiling has not been characterised. Where centrophenoxine has not been studied, that is stated rather than presented as reassurance.
Avoid. No adequate human pregnancy or lactation data exist, and the DMAE moiety centrophenoxine delivers carries developmental-safety concerns from animal embryo models. There is no safe-use evidence to offset that, so it should not be used during pregnancy or breastfeeding.
Related molecules: DMAE (deanol) — the cholinergic moiety centrophenoxine delivers, making this essentially a brain-penetrant DMAE prodrug — and the racetams, which are commonly stacked with centrophenoxine and a choline source in nootropic practice, though the combination is not evidence-based.
References
- Marcer D, Hopkins SM (1977). The differential effects of meclofenoxate on memory loss in the elderly — controlled clinical trial. Age and Ageing. https://pubmed.ncbi.nlm.nih.gov/329662/
- Pék G, Fülöp T, Zs-Nagy I. (1989). Gerontopsychological studies using NAI on patients with organic psychosyndrome treated with centrophenoxine in a double-blind, randomized clinical trial. Archives of Gerontology and Geriatrics. https://pubmed.ncbi.nlm.nih.gov/2506844/
- Fülöp T, Wórum I, Csongor J, Leövey A. (1990). Effects of centrophenoxine on body composition and some biochemical parameters of demented elderly people as revealed in a double-blind clinical trial. Archives of Gerontology and Geriatrics. https://pubmed.ncbi.nlm.nih.gov/15374499/
- Pieschl D, et al. (1983). Double-blind collaborative study of centrophenoxine versus placebo in patients with neurasthenic syndromes — clinical trial. Der Nervenarzt. https://pubmed.ncbi.nlm.nih.gov/6405290/
- Orgogozo JM. (1988). Critical review of clinical trials in senile dementia — review. Postgraduate Medical Journal. https://pubmed.ncbi.nlm.nih.gov/2891126/
- Nandy K, Bourne GH. (1967). Effect of centrophenoxine on the lipofuscin pigments in the neurones of senile guinea-pigs. Nature. https://pubmed.ncbi.nlm.nih.gov/4380940/
- Nandy K. (1978). Lipofuscinogenesis in mice early treated with centrophenoxine. Mechanisms of Ageing and Development. https://pubmed.ncbi.nlm.nih.gov/357853/
- Zhang L, et al. (2011). Calcium overload is associated with lipofuscin formation in human retinal pigment epithelial cells fed with photoreceptor outer segments — in vitro. Eye (London). https://pubmed.ncbi.nlm.nih.gov/21311572/
- James TJ, Sharma SP. (1992). ‘Dark’ cell formation under protein malnutrition: process of conversion and concept of ‘semi-dark’ type Purkinje cells — animal study. Indian Journal of Experimental Biology. https://pubmed.ncbi.nlm.nih.gov/1506025/
- Pavlík A, Pilar J. (1989). Protection of cell proteins against free-radical attack by nootropic drugs — in vitro / ESR study. Neuropharmacology. https://pubmed.ncbi.nlm.nih.gov/2547179/
- Verma R, Nehru B. (2009). Effect of centrophenoxine against rotenone-induced oxidative stress in an animal model of Parkinson’s disease — animal study. Neurochemistry International. https://pubmed.ncbi.nlm.nih.gov/19375462/
- Nehru B, et al. (2007). Further evidence of centrophenoxine mediated protection in aluminium exposed rats by biochemical and light microscopy analysis — animal study. Food and Chemical Toxicology. https://pubmed.ncbi.nlm.nih.gov/17688990/
- Nehru B, Bhalla P. (2007). Reversal of an aluminium induced alteration in redox status in different regions of rat brain by administration of centrophenoxine — animal study. Molecular and Cellular Biochemistry. https://pubmed.ncbi.nlm.nih.gov/16969688/
- Wood WG, et al. (1987). Fluidizing effects of centrophenoxine in vitro on brain and liver membranes from different age groups of mice — in vitro. Life Sciences. https://pubmed.ncbi.nlm.nih.gov/3023777/
- Zs-Nagy I. (1990). On the role of intracellular physicochemistry in quantitative gene expression during aging and the effect of centrophenoxine — review. Archives of Gerontology and Geriatrics. https://pubmed.ncbi.nlm.nih.gov/2517957/
- Hochschild R. (1973). Effect of dimethylaminoethyl p-chlorophenoxyacetate on the life span of male Swiss Webster Albino mice — animal study. Experimental Gerontology. https://pubmed.ncbi.nlm.nih.gov/4147092/
- Zou JJ, et al. (2009). Bioequivalence and pharmacokinetic comparison of a single 200-mg dose of meclofenoxate hydrochloride capsule and tablet formulations in healthy Chinese adult male volunteers — randomised crossover study. Clinical Therapeutics. https://pubmed.ncbi.nlm.nih.gov/18840370/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.



