
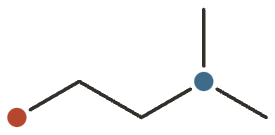
DMAE
A choline-related amino alcohol marketed for focus and skin firmness — the topical skin data are the clearest, and the oral cognition data are negative or absent.

Sources · 2
Where Does It Come From?
Concentration
Content by Source
Concentrations not reported. No percent-dry-weight or mg/g figures have been published for this compound in its source plants.
DMAE at a Glance
DMAE (2-dimethylaminoethanol, also called deanol) is a small amino alcohol — an analog of choline — sold in two completely different contexts: as an oral “focus” nootropic, and as a topical skin-firming cosmetic ingredient.
It is not an essential nutrient and has no reference intake. Small amounts occur in oily fish and in mammalian tissue, and it appears endogenously as an intermediate in choline and phospholipid metabolism, but almost all commercial DMAE is manufactured synthetically.
The framing that matters most: there is no deficiency to correct here. DMAE has no RDA, so there is no repletion benefit to fall back on. The only question is whether supplemental DMAE does something on top of a normal diet — and the oral rationale, that it feeds the acetylcholine pathway, depends on a step that has never been demonstrated in humans. Whether oral DMAE actually raises brain acetylcholine is genuinely disputed.
The honest bottom line, and the single most useful thing here: the evidence that works is topical, and it does not transfer to the capsule. A 3% gel modestly firms skin. Oral DMAE failed in Alzheimer’s disease, tardive dyskinesia and Huntington’s chorea, and has never been shown to improve memory or attention in healthy people.
What It’s Used For
- Skin firmness and fine wrinkles, topically — the one application with credible positive human evidence, and it is a cosmetic effect from a gel, not a capsule.
That is the entire list, which is unusual for a compound this widely sold. The oral uses are not scored below because the controlled human data are negative or absent, and presenting them as ranked benefits would misrepresent the literature.
Be sceptical of the whole oral category: “focus,” “mental clarity” and “brain fog” relief in healthy adults have no convincing controlled trial behind them. The lucid-dreaming claim traces to a single 1988 hypothesis paper. The anti-aging positioning is worse than unsupported — an aged-quail study found DMAE shortened lifespan.
Three honest misses are worth stating plainly. In double-blind trials DMAE failed in Alzheimer’s disease, where 6 of 13 patients were withdrawn for drowsiness, confusion and raised blood pressure; in tardive dyskinesia, where one trial saw psychiatric worsening and Cochrane finds the evidence too poor to support use; and in Huntington’s chorea.
There is also a purity problem specific to this corner of the market — see Safety.
How It Works
The oral rationale is a chain with a broken link. DMAE is structurally similar to choline, so the story goes that it serves as an indirect precursor and raises acetylcholine. The step that has never been established in humans is whether oral DMAE actually crosses into the brain and increases central acetylcholine at all. Formal human data on that point are weak, and that gap is precisely why the cognitive claims remain unproven rather than merely under-studied.
There is a further wrinkle that cuts against the premise: DMAE inhibits choline uptake and metabolism. Rather than simply feeding the cholinergic pathway, it competes with it — which is also the basis for the pregnancy caution below.
The topical mechanism is more interesting, and less flattering than the marketing suggests. Concentrated topical DMAE at around 3% causes rapid, reversible vacuolization of dermal fibroblasts — a mild cytopathic “puffing” that plausibly accounts for the quick apparent firming 12Reference 12In vitroThe antiwrinkle effect of topical concentrated 2-dimethylaminoethanol involves a vacuolar cytopathology — in vitro/in vivoView study →. At higher concentrations it reduces fibroblast viability outright 13Reference 13In vitroDimethylaminoethanol affects the viability of human cultured fibroblasts — in vitroView study →. So the effect may be a controlled mild irritation rather than genuine dermal remodelling.
In vitro it also scavenges hydroxyl, ascorbyl and lipid radicals directly 3Reference 3In vitroNew insights on dimethylaminoethanol (DMAE) features as a free radical scavenger — in vitroView study →, which is where the antioxidant framing comes from — an in-vitro property, not a demonstrated human benefit.
Pharmacology & Research
DMAE (2-dimethylaminoethanol, also called deanol or dimethylethanolamine) is a small amino alcohol — an analog of the B-vitamin choline and a putative indirect precursor of acetylcholine — sold both as an oral “focus” nootropic and as a topical skin-firming cosmetic ingredient. The oral rationale rests on the idea that DMAE feeds the acetylcholine pathway, but whether oral DMAE actually raises brain acetylcholine in humans is disputed, and the human trials that exist (dementia, tardive dyskinesia, Huntington’s chorea, hyperkinetic children) are old, small, and largely negative. The one application with a positive, replicated human signal is dermatologic: a 3% topical gel modestly increases skin firmness, though even that effect may owe more to a mild irritant/vacuolar reaction than to any cholinergic action. This is not a deficiency-correction story — DMAE is not an essential nutrient with an RDA — so there is no “repletion” benefit to fall back on; the question is purely whether supplemental DMAE does anything on top of a normal diet, and for cognition the honest answer is that it has not been shown to.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
DMAE has essentially one application with credible positive human evidence. Its heavily marketed oral cognitive uses are not scored here because the controlled human data are negative or absent — those are covered as honest misses in the takeaways above, not as scored benefits.
This is DMAE’s clearest human effect, and it is topical, not oral. A randomized, double-blind, split-face study compared a gel with 3% deanol (DMAE) against the same vehicle without it; the DMAE side showed a significant increase in skin firmness measured by shear-wave velocity 1Reference 1Split face study on the cutaneous tensile effect of 2-dimethylaminoethanol (deanol) gel — controlled studyView study →.
A review of a separate randomized clinical study reported that 3% DMAE facial gel applied daily for 16 weeks was safe and significantly reduced forehead lines and periorbital fine wrinkles and improved lip fullness, with effects persisting through a 2-week washout 2Reference 2ReviewThe role of dimethylaminoethanol in cosmetic dermatology — reviewView study →.
In vivo formulation work in mice and human skin found a DMAE-containing formulation increased dermal thickness and collagen-fiber thickness beyond the vehicle 11Reference 11Clinical trialIn vivo skin effects of a dimethylaminoethanol (DMAE) based formulation — animal/human studyView study →.
The effect size is cosmetic and modest, and the mechanism is contested: rather than a cholinergic muscle action, concentrated topical DMAE (≈3%) causes rapid, reversible vacuolization of dermal fibroblasts — a mild cytopathic “puffing” that could account for the quick apparent firming — and at higher concentrations reduces fibroblast viability in culture 12,
Free-base and bitartrate salt forms behave similarly in cosmetic preparations 14Reference 14Structural characterization and stability of dimethylaminoethanol and dimethylaminoethanol bitartrate for possible use in cosmetic firming — comparative studyView study →.
Gap: Small trials, cosmetic (not clinical) endpoints, and a mechanism that may be a controlled mild irritation rather than a genuine dermal-remodelling effect — none of which transfers to any oral benefit.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Choline / acetylcholine pathway | Proposed indirect precursor; human brain-acetylcholine elevation unproven and doubted | The (unsupported) oral cognitive rationale |
| Dermal fibroblasts | Rapid reversible vacuolization at ~3% topical; ↓ viability at higher doses 12, | Topical skin firming (likely mechanism) |
| Free radicals (hydroxyl, ascorbyl, lipid) | Direct scavenging in vitro 3Reference 3In vitroNew insights on dimethylaminoethanol (DMAE) features as a free radical scavenger — in vitroView study → | Preclinical antioxidant/“anti-aging” claims |
| Phospholipid / phosphatidylcholine metabolism | Methylation substrate; membrane-related effects | Cell-membrane “stabilizer” hypothesis |
Pharmacokinetics
DMAE is a small, water-soluble tertiary amine that is readily absorbed orally. In humans, ingested deanol is metabolized and excreted partly as deanol-N-oxide: after a 130 mg oral dose, deanol-N-oxide is measurable in urine, and the same metabolite appears after ingestion of meclofenoxate (centrophenoxine), which breaks down into deanol 15Reference 15Determination of urinary deanol-N-oxide excretion profiles after ingestion of nutritional supplements containing deanolView study →. Formal human data on the fraction that crosses the blood-brain barrier and raises central acetylcholine are weak, which is central to why the oral cognitive claims remain unproven. For skin, DMAE is used topically at ~3%, where it acts locally; free-base and bitartrate salts are both used cosmetically 14Reference 14Structural characterization and stability of dimethylaminoethanol and dimethylaminoethanol bitartrate for possible use in cosmetic firming — comparative studyView study →.
Clinical trials
Registered modern trial activity for oral DMAE as a nootropic is essentially absent — it is an old, off-patent compound with no industry program behind the cognition claims. The controlled human literature clusters in the 1970s–80s (dementia, tardive dyskinesia, Huntington’s, hyperkinetic children), and the only recent controlled human work is dermatologic. A related pro-cholinergic candidate (V0191) was tested in prodromal Alzheimer’s in a 242-patient RCT with no significant cognitive benefit 16Reference 16RCTEffect of six months of treatment with V0191 in patients with suspected prodromal Alzheimer’s disease — RCTView study →.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~8(mostly 1970s–80s, small) | 0known | 0 | ~15 |
Last checked: August 2026.
Dietary Sources
DMAE is not an essential nutrient and has no dietary reference intake, but small amounts occur naturally. It is found in oily fish — anchovies, sardines and salmon are the commonly cited sources — and in mammalian tissue, and trace quantities are produced endogenously as an intermediate in choline and phospholipid metabolism.
| Source | Notes |
|---|---|
| Oily fish (anchovy, sardine, salmon) | Most-cited natural food source; amounts small and variable |
| Mammalian tissue / brain | Trace endogenous presence |
| Endogenous synthesis | Intermediate in choline/phosphatidylcholine metabolism |
Because the body makes and interconverts choline-family compounds, dietary DMAE is not something to seek out — a normal diet supplying choline (eggs, liver, fish, soy) covers the pathway DMAE is claimed to feed. Most commercial DMAE is manufactured synthetically, typically as the bitartrate salt, rather than extracted from food.
Dosage
These are doses used or labelled in research and products, not a personal recommendation.
- No RDA/AI and no Tolerable Upper Intake Level exist for DMAE — it is not an essential nutrient, so there is no official intake target or ceiling.
- Oral supplements are usually sold as deanol bitartrate and labelled around 100–300 mg/day. This range reflects marketing convention, not a dose validated for any cognitive benefit — and the controlled cognitive trials that used deanol (often 300–1,800 mg/day of the acetamidobenzoate salt in dementia and movement-disorder studies) were negative.
- Salt vs free base: products differ (free-base DMAE, DMAE bitartrate, deanol acetamidobenzoate). The bitartrate and acetamidobenzoate salts weigh more per unit of DMAE, so the actual DMAE delivered per labelled milligram varies by salt — check which one a label refers to.
- Topical: the human skin studies used a 3% gel applied to the face. This is a cosmetic use, unrelated to oral dosing, and the oral product does not inherit its evidence.
Safety
At typical oral supplement doses DMAE has low acute toxicity, but the safety record is thin and comes mostly from trials in sick populations — and there is a market-integrity problem specific to this compound.
- Neuropsychiatric effects are the dose-limiting ones. In an Alzheimer’s trial, 6 of 13 patients on DMAE were withdrawn within five weeks for drowsiness, mental slowing, confusion and mildly raised blood pressure 7Reference 7RCTDouble-blind trial of 2-dimethylaminoethanol in Alzheimer’s disease — clinical trialView study →.
- Products are a known vector for an unapproved drug. Some “cognitive enhancement” supplements sold alongside DMAE contain unlabelled centrophenoxine (meclofenoxate) at 79–251 mg/serving — only 1 of 7 tested products labelled it accurately 17Reference 17The unapproved drug centrophenoxine (meclofenoxate) in cognitive enhancement dietary supplementsView study →.
- Anti-doping risk. Meclofenoxate is on the WADA prohibited list, and it metabolises to deanol — which matters for tested athletes 15,
17Reference 15Determination of urinary deanol-N-oxide excretion profiles after ingestion of nutritional supplements containing deanolView study →Reference 17The unapproved drug centrophenoxine (meclofenoxate) in cognitive enhancement dietary supplementsView study → . - Avoid in pregnancy. DMAE inhibits choline uptake and metabolism, and that inhibition caused developmental and neural-tube abnormalities in animal embryo models.
- May worsen psychiatric symptoms. A tardive-dyskinesia trial saw a tendency toward worsening of schizophrenic symptoms 9Reference 9RCTIneffectiveness of deanol in tardive dyskinesia: a placebo-controlled study — controlled clinical trialView study →.
- No upper limit is set, and DMAE is not a nutrient — absence of a limit implies nothing about safety.
Full Safety & Interactions Detail
The safety record is thin and mostly derived from clinical trials in sick populations. In a double-blind Alzheimer’s trial, 6 of 13 patients on DMAE were withdrawn within five weeks for side effects including drowsiness, mental slowing, increased confusion, and mildly elevated blood pressure 7Reference 7RCTDouble-blind trial of 2-dimethylaminoethanol in Alzheimer’s disease — clinical trialView study →.
In a tardive-dyskinesia trial, deanol was associated with a tendency toward worsening of psychiatric (schizophrenic) symptoms, consistent with an effect on central cholinergic function 9Reference 9RCTIneffectiveness of deanol in tardive dyskinesia: a placebo-controlled study — controlled clinical trialView study →.
Reported effects elsewhere include headache, muscle tension and insomnia. The dose-limiting problems are therefore neuropsychiatric — sedation and confusion — rather than organ toxicity.
Mechanistically, DMAE inhibits choline uptake and metabolism, and in neurulating mouse embryo and sea-urchin models such inhibition produced developmental and neural-tube abnormalities. That is the basis for the pregnancy caution, and it is a concrete signal rather than a theoretical one, since choline is critical for fetal neural development.
An aged-quail study found DMAE bitartrate shortened lifespan rather than extending it, which undercuts the “anti-aging” positioning entirely 6Reference 6Effects of dimethylaminoethanol upon life-span and behavior of aged Japanese quail — animal studyView study →. Topical 3% DMAE is well tolerated in short studies, though its firming effect may reflect a mild reversible irritant reaction (fibroblast vacuolization), and higher concentrations reduce fibroblast viability in culture 12,
Adulteration. Some cognitive-enhancement supplements marketed in the same category contain centrophenoxine (meclofenoxate) — an unapproved drug that metabolises to DMAE — at 79–251 mg per serving, with only 1 of 7 tested products labelling the amount accurately 17Reference 17The unapproved drug centrophenoxine (meclofenoxate) in cognitive enhancement dietary supplementsView study →. Meclofenoxate is WADA-prohibited, so this is a concrete anti-doping risk on top of the identity problem 15Reference 15Determination of urinary deanol-N-oxide excretion profiles after ingestion of nutritional supplements containing deanolView study →.
Scope disclosure. Interactions assessed? Partially — no systematic drug-interaction review exists. The clearest concern is additive or interfering effects on central cholinergic function, relevant to anticholinergic and pro-cholinergic drugs and to antipsychotics, where worsening was observed. Treat interactions as not fully assessed. Pregnancy/lactation assessed? At a mechanistic and animal level — the signal is negative; no human data. Upper limit established? No. Where DMAE has not been formally studied — most drug interactions, human pregnancy outcomes, long-term oral use — that is stated as “not assessed,” not as “safe.”
Avoid. DMAE is conventionally flagged as something to avoid during pregnancy, and this is more than hand-waving: its inhibition of the choline pathway caused developmental abnormalities in animal embryo models, and choline is critical for fetal neural development. No human safety data support use in pregnancy or lactation, so it should be treated as contraindicated pending evidence.
Related molecules: choline, the essential nutrient DMAE is an analog of and is claimed to feed into; and centrophenoxine, a DMAE-generating nootropic drug that is directly relevant to the adulteration and anti-doping issues above.
References
- Uhoda I, et al. (2002). Split face study on the cutaneous tensile effect of 2-dimethylaminoethanol (deanol) gel — controlled study. Skin Research and Technology. https://pubmed.ncbi.nlm.nih.gov/12236885/
- Grossman R. (2005). The role of dimethylaminoethanol in cosmetic dermatology — review. American Journal of Clinical Dermatology. https://pubmed.ncbi.nlm.nih.gov/15675889/
- Malanga G, et al. (2012). New insights on dimethylaminoethanol (DMAE) features as a free radical scavenger — in vitro. Drug Metabolism Letters. https://pubmed.ncbi.nlm.nih.gov/22300295/
- Blin O, et al. (2009). Effects of dimethylaminoethanol pyroglutamate (DMAE p-Glu) against memory deficits induced by scopolamine — preclinical and clinical (RCT). Psychopharmacology (Berl). https://pubmed.ncbi.nlm.nih.gov/19756528/
- Sergio W. (1988). Use of DMAE (2-dimethylaminoethanol) in the induction of lucid dreams — hypothesis. Medical Hypotheses. https://pubmed.ncbi.nlm.nih.gov/3173167/
- Cherkin A, et al. (1977). Effects of dimethylaminoethanol upon life-span and behavior of aged Japanese quail — animal study. Journal of Gerontology. https://pubmed.ncbi.nlm.nih.gov/830732/
- Fisman M, et al. (1981). Double-blind trial of 2-dimethylaminoethanol in Alzheimer’s disease — clinical trial. American Journal of Psychiatry. https://pubmed.ncbi.nlm.nih.gov/7020434/
- Tammenmaa-Aho I, et al. (2018). Cholinergic medication for antipsychotic-induced tardive dyskinesia — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/29553158/
- de Montigny C, et al. (1979). Ineffectiveness of deanol in tardive dyskinesia: a placebo-controlled study — controlled clinical trial. Psychopharmacology (Berl). https://pubmed.ncbi.nlm.nih.gov/117492/
- Caraceni TA, et al. (1978). 2-dimethylaminoethanol (deanol) in Huntington’s chorea — clinical trial. Journal of Neurology, Neurosurgery & Psychiatry. https://pubmed.ncbi.nlm.nih.gov/153384/
- Tadini KA, et al. (2009). In vivo skin effects of a dimethylaminoethanol (DMAE) based formulation — animal/human study. Pharmazie. https://pubmed.ncbi.nlm.nih.gov/20095140/
- Morissette G, et al. (2007). The antiwrinkle effect of topical concentrated 2-dimethylaminoethanol involves a vacuolar cytopathology — in vitro/in vivo. British Journal of Dermatology. https://pubmed.ncbi.nlm.nih.gov/17300230/
- Gragnani A, et al. (2007). Dimethylaminoethanol affects the viability of human cultured fibroblasts — in vitro. Aesthetic Plastic Surgery. https://pubmed.ncbi.nlm.nih.gov/17940822/
- Clares B, et al. (2010). Structural characterization and stability of dimethylaminoethanol and dimethylaminoethanol bitartrate for possible use in cosmetic firming — comparative study. Journal of Cosmetic Science. https://pubmed.ncbi.nlm.nih.gov/20716435/
- Krug O, et al. (2023). Determination of urinary deanol-N-oxide excretion profiles after ingestion of nutritional supplements containing deanol. Drug Testing and Analysis. https://pubmed.ncbi.nlm.nih.gov/37735938/
- Dubois B, et al. (2012). Effect of six months of treatment with V0191 in patients with suspected prodromal Alzheimer’s disease — RCT. Journal of Alzheimer’s Disease. https://pubmed.ncbi.nlm.nih.gov/22330824/
- Cohen PA, et al. (2022). The unapproved drug centrophenoxine (meclofenoxate) in cognitive enhancement dietary supplements. Clinical Toxicology (Phila). https://pubmed.ncbi.nlm.nih.gov/35959800/
For half-lives, timing and stacking across the nootropics on this site, see the Nootropic Dosage Guide.
Products · 1



