
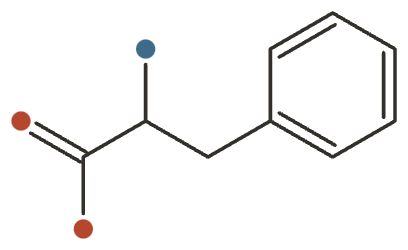
DL-Phenylalanine
A racemic L-/D-phenylalanine blend sold for mood and pain, on thin, dated, and partly negative evidence.

DL-Phenylalanine at a Glance
DL-phenylalanine is a 50:50 mixture of two mirror-image forms of the amino acid phenylalanine, and the mixture exists because each half does something different.
L-phenylalanine is the natural, essential form found in protein — the precursor to tyrosine and from there to dopamine and noradrenaline. D-phenylalanine is synthetic and not used to build proteins at all; it inhibits the enzymes that break down the body’s own opioid peptides. One form feeds catecholamines, the other prolongs endorphins.
What It’s Used For
- Chronic pain (D-phe) — prolongs the body’s own enkephalins for pain relief.
- Depression / low mood — supplies precursor for dopamine and noradrenaline.
- Vitiligo repigmentation (L-phe + phototherapy) — restores pigment when combined with phototherapy.
How It Works
The L-form is hydroxylated to tyrosine, then along the standard route to L-DOPA, dopamine and noradrenaline — the same pathway L-tyrosine feeds, one step further back. It also supplies the substrate for melanin, which is the basis of the vitiligo use alongside UV light.
The D-form works by inhibition rather than supply. Enkephalins — endogenous opioid peptides — are broken down by enzymes including carboxypeptidase A and enkephalinase; D-phenylalanine inhibits them, so the enkephalins already released persist longer. It raises the tone of a system already running rather than adding an opioid.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
DL-phenylalanine (DLPA) is a racemic 50/50 blend of two amino acids sold as one supplement: L-phenylalanine, the essential dietary amino acid that feeds tyrosine and the catecholamine (dopamine/noradrenaline) pathway, and D-phenylalanine, a non-dietary mirror-image isomer proposed to inhibit enkephalinase and so prolong the body’s own endorphins. That gives it two separate rationales — a mood one (L-form → catecholamines/phenylethylamine) and a pain one (D-form → endorphin sparing) — but the human evidence for both is thin, old, small, and in the one properly controlled pain trial, outright negative. Almost none of the supportive data comes from DLPA the racemate tested against placebo in replete people; it comes from single-isomer studies, uncontrolled case series, and mechanism papers. The strongest human signal actually belongs to L-phenylalanine combined with phototherapy for vitiligo, which is a different use than the mood/pain marketing.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up. Note two of these use a single isomer, not the DLPA racemate — read the form line in each toggle.
Form: L-phenylalanine (not the racemate). The most consistent human data for any phenylalanine use is dermatological, not psychiatric. An open trial in 70 patients with active vitiligo combined oral L-phenylalanine (100 mg/kg/day) and a topical 10% gel with UVA or sunlight plus low-potency clobetasol, reporting repigmentation in about 90% of participants over repeated visits 1Reference 1Clinical trialOral and topical L-phenylalanine, clobetasol propionate, and UVA/sunlight — a new study for the treatment of vitiligo — controlled clinical trial (open)View study →. Systematic reviews of natural-product and adjunctive vitiligo therapies list phenylalanine-plus-UVA among the better-studied options while stressing that trials are mostly open-label, combine it with phototherapy and/or steroids, and lack blinded placebo arms 2,
Gap: the amino acid is never tested alone against placebo — the UVA/sunlight is doing established work — so its independent contribution is unquantified, and this is the L-isomer, not DLPA.
Form: L-phenylalanine (the mood-relevant isomer). An early open (uncontrolled) study gave DL-phenylalanine 75–200 mg/day to 20 depressed patients for 20 days and reported that 12 could be discharged and 4 more improved, with “core” depressive symptoms responding preferentially 3Reference 3DL-phenylalanine in depressed patients: an open study — open (uncontrolled) studyView study → — but with no placebo control, this cannot establish efficacy. The stronger mechanistic thread is the phenylethylamine (PEA) hypothesis: depressed patients show low urinary/plasma phenylacetic acid (PEA’s metabolite), and L-phenylalanine — PEA’s precursor — improved mood in depressed patients only when given alongside a selective MAO-B inhibitor that stops PEA being destroyed 4,
Gap: no modern randomized placebo-controlled trial of DLPA for depression exists; the credible signal requires co-administration of an MAO-B inhibitor and uses the L-form, so DLPA-as-standalone-antidepressant is unproven.
Form: D-phenylalanine (the pain-rationale isomer). The enkephalinase-inhibition idea is real on paper — D-phenylalanine produces naloxone-reversible analgesia and potentiates acupuncture analgesia in animals, and has been proposed as an “endorphin-deficiency” agent 6Reference 6ReviewD-phenylalanine and other enkephalinase inhibitors as pharmacological agents: implications for some important therapeutic application — review/preclinicalView study →. But when tested properly in people it failed: a randomized, double-blind, placebo-controlled crossover trial of D-phenylalanine 250 mg four times daily in 30 chronic-pain patients found no significant analgesic effect over placebo 7Reference 7RCTAnalgesic effectiveness of D-phenylalanine in chronic pain patients — randomised controlled trial (negative)View study →. The widely repeated claim that DLPA “markedly potentiates opiate analgesia” traces to a single non-peer-reviewed report, not controlled human trials 5Reference 5DL-phenylalanine markedly potentiates opiate analgesia — hypothesis/commentary (not a controlled trial)View study →.
Gap: the best-designed human pain trial is negative; supportive evidence is animal, uncontrolled, or anecdotal, so analgesic marketing is not backed.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Phenylalanine hydroxylase → tyrosine → catecholamines | Substrate supply (L-form) | Moodalertness |
| Phenylethylamine (PEA) synthesis (L-form) | ↑ PEA, a trace-amine neuromodulator (rapidly cleared by MAO-B) | Mood |
| Enkephalinase / carboxypeptidase A (D-form) | Proposed ↓ enkephalin breakdown → ↑ endogenous opioids | Pain (unproven in humans) |
| Tyrosinase / melanin pathway + UVA (L-form) | Substrate for melanogenesis under phototherapy | Vitiligo repigmentation |
Pharmacokinetics
L-phenylalanine is absorbed efficiently from the gut via neutral-amino-acid transporters and crosses the blood–brain barrier in competition with other large neutral amino acids (tyrosine, tryptophan, the branched-chains), so a protein-rich meal blunts its CNS delivery — an amino-acid supplement is best taken away from protein. The D-isomer is handled differently: it is not a normal dietary amino acid, is only partially converted to the usable L-form (biological utilization roughly 28–81% in animal feeding studies, falling as dose rises), and the remainder is metabolized by D-amino-acid oxidase or excreted 10Reference 10AnimalThe nutritive value and safety of D-phenylalanine and D-tyrosine in mice — animal studyView study →. PEA generated from L-phenylalanine has a very short half-life because monoamine oxidase B degrades it within minutes, which is why the mood studies pair it with an MAO-B inhibitor. No reliable human half-life for supplemental DLPA itself has been established.
Clinical trials
Registered-trial activity for DLPA specifically is minimal — it is an off-patent, inexpensive amino acid with little commercial incentive for large trials, so most human data are decades old and small. The genuinely controlled work is essentially one negative pain RCT plus small open studies in mood and vitiligo.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~4(mostly small/open; 1 negative RCT) | 0known | 0known | ~15+ |
Last checked: July 2026.
Dietary Sources
Phenylalanine here means the L-isomer, which is abundant in ordinary protein — the D-isomer that half of DLPA is made of does not occur meaningfully in the diet and is a synthetic addition. Because L-phenylalanine is an essential amino acid found in virtually all protein foods, dietary deficiency is effectively unheard of in anyone eating enough protein, which undercuts the idea of “topping up” for mood in a well-fed person. The artificial sweetener aspartame is also a notable non-food source (it is ~50% phenylalanine by weight), which is why aspartame-containing products carry a PKU warning.
| Food (typical serving) | Approx. L-phenylalanine |
|---|---|
| Chicken/beef/fish (100 g) | ~800–1100 mg |
| Soybeans / tofu (100 g) | ~500–2000 mg |
| Eggs (2 large) | ~680 mg |
| Milk (1 cup) | ~390 mg |
| Nuts / seeds (28 g) | ~250–450 mg |
| Lentils / beans (100 g cooked) | ~400–500 mg |
A mixed adult diet easily supplies several grams of L-phenylalanine per day, comfortably above requirements (NIH ODS / IOM Dietary Reference Intakes for amino-acid requirements 11Reference 11Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Fatty Acids, Cholesterol, Protein, and Amino Acids — protein & amino acids chapterView study →).
Intake & Dosage
There is no RDI or Tolerable Upper Intake Level for DLPA or D-phenylalanine. The IOM sets a combined requirement for the aromatic amino acids L-phenylalanine + L-tyrosine of roughly 14 mg/kg/day in adults, which normal protein intake far exceeds 11Reference 11Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Fatty Acids, Cholesterol, Protein, and Amino Acids — protein & amino acids chapterView study →. Supplemental doses studied in research (not a personal recommendation) were small and inconsistent: the 1977 open depression study used only 75–200 mg/day of DLPA 3Reference 3DL-phenylalanine in depressed patients: an open study — open (uncontrolled) studyView study →; the negative pain trial used D-phenylalanine 250 mg four times daily (1000 mg/day) 7Reference 7RCTAnalgesic effectiveness of D-phenylalanine in chronic pain patients — randomised controlled trial (negative)View study →; the vitiligo work used oral L-phenylalanine at 100 mg/kg/day alongside phototherapy 1Reference 1Clinical trialOral and topical L-phenylalanine, clobetasol propionate, and UVA/sunlight — a new study for the treatment of vitiligo — controlled clinical trial (open)View study →. Because the D-isomer is only partially and dose-dependently converted to usable L-phenylalanine, higher doses do not scale cleanly. If taken for a CNS effect, amino-acid supplements are generally taken on an empty stomach, away from protein-containing meals, to reduce competition for brain uptake. These are doses used in studies, not a recommendation.
Safety
In people without PKU, phenylalanine looks low in toxicity at ordinary supplemental intakes — but it is absolutely contraindicated in phenylketonuria, and its safety envelope is otherwise poorly characterized because the trials are old and small.
- Contraindicated in phenylketonuria and related hyperphenylalaninemias. The body cannot metabolize phenylalanine, and accumulation is neurotoxic.
- Avoid in pregnancy and breastfeeding unless a clinician directs it. Elevated maternal phenylalanine is specifically harmful to the fetus — see the box below.
- Monoamine-oxidase inhibitors. A plausible interaction risk of excessive pressor response; avoid without medical supervision.
- Poorly controlled psychosis or schizophrenia. Theoretical caution given the dopaminergic rationale.
- High doses may cause mild gastrointestinal upset. Headache and jitteriness are reported anecdotally.
- Low apparent toxicity at ordinary intakes in people without PKU. The envelope is poorly characterized rather than known to be wide.
Full Safety & Interactions Detail
In people without PKU, phenylalanine appears low in toxicity at ordinary supplemental intakes, but its safety envelope is poorly characterized because the trials are old and small. The clearest hard rule is that DLPA is contraindicated in phenylketonuria (PKU) and related hyperphenylalaninemias, where the body cannot metabolize phenylalanine and accumulation is neurotoxic. Because L-phenylalanine feeds catecholamine and phenylethylamine synthesis, combining it with monoamine-oxidase inhibitors (MAOIs) is a plausible interaction concern (risk of excessive pressor/serotonergic-adrenergic response) and should be avoided without medical supervision; caution is also reasonable with other pro-monoaminergic drugs. Theoretical caution applies in poorly controlled psychosis/schizophrenia given the dopaminergic rationale. High doses may cause mild gastrointestinal upset or, anecdotally, headache/jitteriness. This is informational only, not medical advice.
Scope disclosure (honesty — not a claim):
- Interactions assessed? Partially — the pharmacologically obvious classes (MAOIs, and by extension other monoaminergic agents) were reviewed; a comprehensive drug-interaction screen was not performed.
- Pregnancy/lactation assessed? No — no human safety data identified; treated as avoid-by-default.
- Upper Limit (UL) established? No — no UL is set for phenylalanine outside the strict clinical limit imposed in PKU. Do not read the absence of a UL as license for unlimited intake.
Verdict: avoid unless directed by a clinician. Supplemental DLPA has not been studied for safety in pregnancy or lactation, and elevated maternal phenylalanine is specifically harmful to the fetus in maternal PKU. Absence of reports is not evidence of safety.
Related compounds / cross-links
- L-phenylalanine — the dietary, mood-relevant half.
- D-phenylalanine — the synthetic, pain-rationale half.
- L-tyrosine — the downstream product and the more direct catecholamine precursor.
- Phenylethylamine (PEA) — the trace amine central to the mood hypothesis.
References
- Camacho F, Mazuecos J. (2002). Oral and topical L-phenylalanine, clobetasol propionate, and UVA/sunlight — a new study for the treatment of vitiligo — controlled clinical trial (open). J Drugs Dermatol. https://pubmed.ncbi.nlm.nih.gov/12847735/
- Cohen BE, Elbuluk N, Mu EW, Orlow SJ. (2015). Alternative systemic treatments for vitiligo: a review — review. Am J Clin Dermatol. https://pubmed.ncbi.nlm.nih.gov/26329814/
- Beckmann H, Strauss MA, Ludolph E. (1977). DL-phenylalanine in depressed patients: an open study — open (uncontrolled) study. J Neural Transm. https://pubmed.ncbi.nlm.nih.gov/335027/
- Sabelli HC, et al. (1986). Clinical studies on the phenylethylamine hypothesis of affective disorder: urine and blood phenylacetic acid and phenylalanine dietary supplements. J Clin Psychiatry. https://pubmed.ncbi.nlm.nih.gov/3944066/
- Russell AL, McCarty MF. (2000). DL-phenylalanine markedly potentiates opiate analgesia — hypothesis/commentary (not a controlled trial). Med Hypotheses. https://pubmed.ncbi.nlm.nih.gov/10998643/
- Ehrenpreis S. (1982). D-phenylalanine and other enkephalinase inhibitors as pharmacological agents: implications for some important therapeutic application — review/preclinical. Acupunct Electrother Res. https://pubmed.ncbi.nlm.nih.gov/6128872/
- Walsh NE, Ramamurthy S, Schoenfeld L, Hoffman J. (1986). Analgesic effectiveness of D-phenylalanine in chronic pain patients — randomised controlled trial (negative). Arch Phys Med Rehabil. https://pubmed.ncbi.nlm.nih.gov/3524509/
- Shakhbazova A, Wu H, Chambers CJ, Sivamani RK. (2021). A systematic review of nutrition, supplement, and herbal-based adjunctive therapies for vitiligo — systematic review. J Altern Complement Med. https://pubmed.ncbi.nlm.nih.gov/33337930/
- Sabelli HC, Javaid JI. (1995). Phenylethylamine modulation of affect: therapeutic and diagnostic implications — review. J Neuropsychiatry Clin Neurosci. https://pubmed.ncbi.nlm.nih.gov/7711493/
- Friedman M, Gumbmann MR. (1984). The nutritive value and safety of D-phenylalanine and D-tyrosine in mice — animal study. J Nutr. https://pubmed.ncbi.nlm.nih.gov/6491762/
- Institute of Medicine. (2005). Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Fatty Acids, Cholesterol, Protein, and Amino Acids — protein & amino acids chapter. National Academies Press. https://nap.nationalacademies.org/catalog/10490/



