
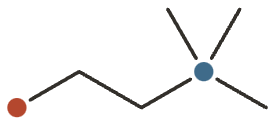

Choline at a Glance
Choline is an essential nutrient, grouped with the B-complex, that the body needs for three separate jobs: making the neurotransmitter acetylcholine, building the membrane phospholipid phosphatidylcholine, and supplying methyl groups (via betaine) for methylation reactions.
The body makes some choline endogenously — but not enough, and how much it makes depends on estrogen, which is why requirements differ by sex and menopausal status. The rest has to come from food: eggs, liver, meat, fish, soy and cruciferous vegetables.
The framing that matters here is unusual, because choline sits on both sides of the deficiency line. Its essentiality is settled — controlled human depletion reliably produces fatty liver and muscle damage, and repletion reverses it. The popular premise is not: that extra choline, on top of an adequate diet, sharpens cognition in a healthy person. Most people in the US and Europe do consume below the Adequate Intake, so there is often real room to improve intake — but that is a different claim from “choline is a nootropic.”
The honest bottom line: the form matters more than the dose. The cheap salts sold in nootropic stacks are poor at raising brain choline, and even the better-delivered forms have mixed, heavily industry-funded human data.
What It’s Used For
Ranked by how well the evidence actually holds up:
- Correcting deficiency and liver health — the best-supported use by a wide margin, and entirely a repletion effect.
- Maternal intake and infant neurodevelopment — one small but tightly controlled RCT, plus supportive cohort data.
- Cognition in impairment and dementia — modest, adjunctive, and specific to the citicoline and alpha-GPC forms rather than to choline salts.
- Cognition in healthy people — the mass-market claim, and the weakest.
- Athletic performance — single small alpha-GPC trials.
Be sceptical of the standard nootropic pitch. For choline bitartrate and citrate specifically — the forms most people actually buy — there is no citable trial establishing a cognitive benefit in healthy, replete adults, and these salts raise brain choline poorly. Two further correctives: citicoline failed to improve recovery in the large ICTUS stroke trial, and the choline in phosphatidylcholine feeds gut-bacterial production of TMAO, a metabolite associated with cardiovascular events. Neither fact supports “more is better.”
How It Works
Choline’s three jobs explain everything here, including the parts that disappoint.
As an acetylcholine precursor, choline is the substrate that choline acetyltransferase turns into the neurotransmitter underpinning memory and neuromuscular signalling. This is the mechanism every cognitive claim rests on — and the reason it so often fails to deliver is that substrate supply is not usually the limiting step in a well-fed brain.
Through the Kennedy pathway, choline becomes phosphatidylcholine, which the liver needs to package fat into VLDL and export it. When choline runs short, fat accumulates in the liver instead. This is the mechanism behind the strongest evidence on the page, and it is a genuine deficiency effect.
Via oxidation to betaine, choline donates methyl groups for homocysteine remethylation, tying it into one-carbon metabolism alongside folate and B12.
There is a fourth pathway that works against you. Gut bacteria convert unabsorbed choline to trimethylamine, which the liver oxidises to TMAO — the source of both the fishy odour at high doses and the cardiovascular concern.
The practical upshot is the form table below: weight percent and brain delivery are different things. Choline chloride is ~74% choline by weight and citicoline only ~18%, yet citicoline reaches cholinergic pathways far more effectively. Buying on elemental percentage gets this exactly backwards.
Pharmacology & Research
Choline is an essential nutrient, grouped with the B-complex, that supplies three metabolic needs: the neurotransmitter acetylcholine, the membrane phospholipid phosphatidylcholine, and methyl groups (via betaine) for methylation. The evidence posture is a study in contrasts. The nutrient’s essentiality is settled — controlled human depletion reliably produces fatty liver and muscle damage, and repletion reverses it — so correcting inadequacy is the best-supported use 1,
What is far weaker is the popular premise that extra choline, taken on top of an adequate diet, sharpens cognition in healthy people. That is where marketing outruns evidence, and where the form matters more than the dose: the cheap forms sold as “nootropics” (bitartrate, citrate) are poor at raising brain choline compared with alpha-GPC or CDP-choline (citicoline), and even for those better-absorbed forms the human cognitive data are mixed and heavily industry-funded 3,
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Choline’s essentiality is demonstrated by controlled feeding studies: when healthy adults were deprived of dietary choline (<50 mg/day), 77% of men and 80% of postmenopausal women developed fatty liver or muscle damage, versus only 44% of premenopausal women — a sex/estrogen difference, since estrogen upregulates endogenous phosphatidylcholine synthesis 2Reference 2Sex and menopausal status influence human dietary requirements for the nutrient choline — controlled feeding studyView study →.
The damage resolved when choline was added back 2Reference 2Sex and menopausal status influence human dietary requirements for the nutrient choline — controlled feeding studyView study →.
In long-term total parenteral nutrition, choline deficiency causes hepatic steatosis that is reversed by intravenous choline 10Reference 10Choline deficiency: a cause of hepatic steatosis during parenteral nutrition reversed with intravenous cholineView study →.
This is a genuine repletion effect, not a general “liver support” claim: the benefit is seen in the deficient, and observational links between habitual choline intake and liver disease in replete people are not causal 1Reference 1Choline — Health Professional Fact SheetView study →.
Gap: The effect is deficiency-dependent — it does not imply that supplementing an already-adequate person protects the liver.
In a randomized, double-blind controlled-feeding study, women in their third trimester consumed either 480 or 930 mg choline/day; infants of the 930 mg/day group had significantly faster mean reaction time (information-processing speed) across testing at 4–13 months 5Reference 5RCTMaternal choline supplementation during the third trimester improves infant information processing speed — randomized, double-blind controlled feeding studyView study →.
The trial was rigorous but very small (n=26 randomized, 24 infants tested). NIH recognizes adequate maternal choline as important for fetal brain development, and the AI rises in pregnancy (450 mg/day) and lactation (550 mg/day) 1Reference 1Choline — Health Professional Fact SheetView study →.
Cohort data linking maternal or dietary choline to child and adult cognition are supportive but observational 11Reference 11ObservationalThe relation of dietary choline to cognitive performance and white-matter hyperintensity in the Framingham Offspring Cohort — cohort studyView study →.
Gap: The causal human evidence is one small RCT; the dose that helped (~930 mg/day) is roughly twice the AI, and long-term outcomes are not established.
Here the evidence is about specific forms, not choline salts. Citicoline (CDP-choline) and alpha-GPC (choline alfoscerate) have been trialled in mild cognitive impairment, Alzheimer’s disease and post-stroke cognitive decline. A 2023 systematic review/meta-analysis of seven studies found citicoline a “promising” agent whose role in practice is not yet established 3Reference 3Meta-analysisIs citicoline effective in preventing and slowing down dementia? — systematic review and meta-analysisView study →.
Alpha-GPC has been studied mainly as an add-on to the acetylcholinesterase inhibitor donepezil (the ASCOMALVA trial, n=113 mild-to-moderate AD), with signals on behavioral symptoms and regional brain volume over 24–36 months 6Reference 6RCTAssociation between donepezil and choline alphoscerate on behavioral disturbances in Alzheimer’s disease — ASCOMALVA trial interim results (RCT)View study →.
Effects are modest and adjunctive.
Gap: Most trials are small, of variable quality, and several are linked to manufacturers; no form is an established treatment, and the older Cochrane review of CDP-choline noted heterogeneity.
The mass-market claim — take a choline supplement to think better — is the weakest. For choline bitartrate/citrate specifically, there is no citable trial establishing a cognitive benefit in healthy replete adults, and these forms raise brain choline poorly 4Reference 4RCTThe effect of citicoline supplementation on motor speed and attention in adolescent males — randomized trialView study →.
The better-absorbed forms have thin, industry-funded signals: citicoline 500 mg/day for 12 weeks improved some secondary memory measures in older adults with age-associated memory impairment (n=100, manufacturer-sponsored) 12Reference 12RCTCiticoline and memory function in healthy older adults — randomized, double-blind, placebo-controlled trialView study →, and citicoline 250–500 mg/day for 28 days improved attention and psychomotor speed in healthy adolescent males (n=75, manufacturer-sponsored) 4Reference 4RCTThe effect of citicoline supplementation on motor speed and attention in adolescent males — randomized trialView study →.
Gap: Benefits are secondary outcomes in small, sponsor-run trials of citicoline; the cheap salts most people buy have essentially no supporting cognitive data.
Alpha-GPC is marketed as a pre-workout ergogenic on the premise of raising acetylcholine and growth hormone. A crossover trial (n=48 college-aged males) reported greater lower-body force after 500 mg alpha-GPC versus placebo 7Reference 7RCTEvaluation of two doses of alpha-glycerylphosphorylcholine on physical and psychomotor performance — randomized crossover trialView study →, and a small study found alpha-GPC transiently increased growth-hormone secretion and fat oxidation in young adults 13Reference 13Glycerophosphocholine enhances growth hormone secretion and fat oxidation in young adultsView study →. Both are small and short.
Gap: Single small trials with performance endpoints that don’t consistently replicate; no durable performance benefit is established.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Acetylcholine synthesis (via choline acetyltransferase) | Substrate supply ↑ | Cognitionneuromuscularergogenic claims |
| Phosphatidylcholine (CDP-choline / Kennedy pathway) | Membrane phospholipid & VLDL export ↑ | Liver (steatosis)cell-membrane integrity |
| Betaine → homocysteine remethylation | Methyl-group donation ↑ | Methylationone-carbon metabolism |
| Gut microbial trimethylamine → hepatic TMAO | ↑ TMAO (undesirable) | Cardiovascular-risk caveat |
Pharmacokinetics
Choline is absorbed in the small intestine and circulates as free choline; a portion is converted by gut bacteria to trimethylamine, which the liver oxidizes to TMAO — the source of both the “fishy” odor at high doses and the cardiovascular-metabolite concern 1,
Clinical trials
Choline as a nutrient is off-patent, so most rigorous trial activity centers on the branded forms — citicoline (e.g. Cognizin) and alpha-GPC — often manufacturer-sponsored; the large independent trial (ICTUS, citicoline in acute stroke) was neutral 8Reference 8RCTCiticoline in the treatment of acute ischaemic stroke (ICTUS) — international, randomised, placebo-controlled trialView study →. Registered activity continues in maternal supplementation, MASLD/NAFLD, and cognitive aging.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~40+ | ~10 | few | Extensive |
Last checked: August 2026.
Forms of Choline
Choline’s forms differ enough that they behave like distinct supplements — this is a genuine forms split, not interchangeable vitamers. The salts (bitartrate, citrate, chloride) are cheap bulk choline used to correct intake or feed racetam stacks; alpha-GPC and citicoline are the forms carrying the limited, industry-linked cognitive data.
| Form | Elemental choline | Absorption / brain delivery | Gut / tolerance | Best for |
|---|---|---|---|---|
| Choline bitartrate | ~41% | Cheap; raises plasma choline but poor brain delivery | GI upset, fishy odour at high dose | Cheapest way to raise intake; racetam stacks |
| Choline citrate | ~50% | Similar to bitartrate | Similar | General intake |
| Choline chloride | ~74% | Highest by weight; same poor brain delivery as the salts | Hygroscopic, usually a liquid/feed form | Bulk intake, rarely sold retail |
| Alpha-GPC | ~40% | Efficient CNS delivery; acetylcholine precursor | Generally well tolerated | Cognitive/ergogenic use, dementia adjunct |
| Citicoline (CDP-choline) | ~18% | Efficient; supplies choline plus cytidine | Well tolerated | Cognitive support; most human trial data |
Honesty for forms: the “premium form = dramatically better” pitch is overstated. The real, defensible distinction is that bitartrate and citrate are poor at raising brain choline, so they are a weak basis for a cognitive claim — while alpha-GPC and citicoline are better delivered but still lack robust benefit in healthy people 3,
Dietary Sources
Choline is widely distributed in animal and some plant foods; the body synthesizes some endogenously (estrogen-dependent) but not enough, so diet is required. Most people in the US and Europe consume below the AI, though frank deficiency is uncommon in the otherwise well-fed 1Reference 1Choline — Health Professional Fact SheetView study →. Refining and low-egg/low-organ-meat diets lower intake.
| Food | Approx. choline | Notes |
|---|---|---|
| Egg (1 large, with yolk) | ~145 mg | Most concentrated common source; nearly all in the yolk |
| Beef liver (85 g) | ~350 mg | Richest common food |
| Beef / chicken / fish (85 g) | ~70–100 mg | Reliable everyday source |
| Soybeans, roasted (½ cup) | ~100 mg | Leading plant source |
| Cruciferous veg (broccoli, Brussels sprouts, ½ cup cooked) | ~30–60 mg | Modest but useful |
| Milk (1 cup) | ~40 mg | — |
Values are approximate; see the NIH ODS fact sheet for the full food table 1Reference 1Choline — Health Professional Fact SheetView study →. The absorbed fraction is high for food choline, and egg phosphatidylcholine is well utilized — though it also feeds the TMAO pathway in some people 1,
Dosage
Choline has an Adequate Intake (AI), not an RDA — the evidence was judged insufficient to set an Estimated Average Requirement 1Reference 1Choline — Health Professional Fact SheetView study →. Adult AI: 550 mg/day (men), 425 mg/day (women), rising to 450 mg/day in pregnancy and 550 mg/day in lactation 1Reference 1Choline — Health Professional Fact SheetView study →. The Tolerable Upper Intake Level is 3,500 mg/day for adults; the UL counts choline from supplements and food, and is set by hypotension and fishy odour rather than organ toxicity at that level 1Reference 1Choline — Health Professional Fact SheetView study →.
Elemental vs compound weight matters here more than almost anywhere else. Supplement labels often list the salt weight, not the choline delivered. Approximate choline content: choline chloride ~74%, choline citrate ~50%, choline bitartrate ~41%, alpha-GPC ~40%, CDP-choline/citicoline ~18%. A “500 mg choline bitartrate” capsule provides roughly 200 mg of choline. Studied supplemental ranges run from the AI up to ~930 mg/day (the maternal RCT) and 500 mg/day for the branded cognitive forms 5,
These are doses studied in research, not a personal recommendation.
Safety
At dietary and AI-level intakes choline is safe; the interesting question is what happens well above them.
- Safe at dietary and AI-level intakes. An essential nutrient with an established AI and a UL well above normal intake.
- Fishy body odour, sweating and hypotension near the UL. From bacterial trimethylamine production; also excessive salivation and GI upset 1Reference 1Choline — Health Professional Fact SheetView study →.
- The TMAO question argues against mega-dosing. The choline in phosphatidylcholine is converted by gut bacteria to TMAO, linked in cohort data to major adverse cardiovascular events 9Reference 9ObservationalIntestinal microbial metabolism of phosphatidylcholine and cardiovascular risk — cohort studyView study →.
- Caution in kidney disease. Reduced TMAO clearance is a plausible concern — worth clinician input.
- Drug interactions were not comprehensively assessed. Racetam co-use is a stacking pattern, not a known hazard.
- An upper limit does exist — 3,500 mg/day for adults, counting supplements and food.
Full Safety & Interactions Detail
The dose-limiting adverse effects appear near or above the 3,500 mg/day UL: a trimethylamine (“fishy”) body odour, sweating, excessive salivation, GI upset, and hypotension; very high intakes have been associated with liver effects 1Reference 1Choline — Health Professional Fact SheetView study →.
- Cardiovascular caveat: the choline moiety in phosphatidylcholine — and in supplements — is converted by gut bacteria to TMAO, a metabolite linked in cohort data to major adverse cardiovascular events 9Reference 9ObservationalIntestinal microbial metabolism of phosphatidylcholine and cardiovascular risk — cohort studyView study →. This is a reason to meet needs rather than mega-dose, especially for anyone with cardiovascular or renal disease.
- Renal impairment: reduced TMAO clearance is a plausible concern; caution and clinician input are warranted.
Scope disclosure. Interactions assessed? Partially — no major drug-interaction class was systematically reviewed; racetam co-use is a stacking pattern, not a hazard interaction, so treat drug interactions as not fully assessed. Pregnancy/lactation assessed? Yes — the AI and one RCT are reviewed above. Upper limit established? Yes — 3,500 mg/day for adults, counting supplements and food. Absence of interaction reports here is not evidence of safety; where it wasn’t studied, it is “not assessed.”
Meeting the raised AI is beneficial; mega-dosing is not established as safe. Adequate maternal choline supports fetal brain development, and the AI rises to 450 mg/day in pregnancy and 550 mg/day in lactation 1Reference 1Choline — Health Professional Fact SheetView study →. One controlled trial used ~930 mg/day in the third trimester with a favourable infant outcome and no reported harm, but a single small trial does not establish high-dose supplementation as routinely safe 5Reference 5RCTMaternal choline supplementation during the third trimester improves infant information processing speed — randomized, double-blind controlled feeding studyView study →. Meet the AI through diet or a prenatal, and discuss any higher-dose supplement with a clinician.
Related molecules: the two better-delivered forms, alpha-GPC and citicoline; the metabolite betaine (TMG); the dietary phospholipid phosphatidylcholine and its commercial source lecithin; and the one-carbon partners folate and vitamin B12.
References
- National Institutes of Health, Office of Dietary Supplements. Choline — Health Professional Fact Sheet. NIH ODS. https://ods.od.nih.gov/factsheets/Choline-HealthProfessional/
- Fischer LM, et al. (2007). Sex and menopausal status influence human dietary requirements for the nutrient choline — controlled feeding study. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/17490963/
- Bonvicini M, et al. (2023). Is citicoline effective in preventing and slowing down dementia? — systematic review and meta-analysis. Nutrients. https://pubmed.ncbi.nlm.nih.gov/36678257/
- McGlade E, et al. (2019). The effect of citicoline supplementation on motor speed and attention in adolescent males — randomized trial. Journal of Attention Disorders. https://pubmed.ncbi.nlm.nih.gov/26179181/
- Caudill MA, et al. (2018). Maternal choline supplementation during the third trimester improves infant information processing speed — randomized, double-blind controlled feeding study. FASEB Journal. https://pubmed.ncbi.nlm.nih.gov/29217669/
- Carotenuto A, et al. (2017). Association between donepezil and choline alphoscerate on behavioral disturbances in Alzheimer’s disease — ASCOMALVA trial interim results (RCT). Journal of Alzheimer’s Disease. https://pubmed.ncbi.nlm.nih.gov/28035924/
- Marcus L, et al. (2017). Evaluation of two doses of alpha-glycerylphosphorylcholine on physical and psychomotor performance — randomized crossover trial. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/29042830/
- Dávalos A, et al. (2012). Citicoline in the treatment of acute ischaemic stroke (ICTUS) — international, randomised, placebo-controlled trial. The Lancet. https://pubmed.ncbi.nlm.nih.gov/22691567/
- Tang WHW, et al. (2013). Intestinal microbial metabolism of phosphatidylcholine and cardiovascular risk — cohort study. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/23614584/
- Buchman AL, et al. (1995). Choline deficiency: a cause of hepatic steatosis during parenteral nutrition reversed with intravenous choline. Hepatology. https://pubmed.ncbi.nlm.nih.gov/7590654/
- Poly C, et al. (2011). The relation of dietary choline to cognitive performance and white-matter hyperintensity in the Framingham Offspring Cohort — cohort study. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/22071706/
- Nakazaki E, et al. (2021). Citicoline and memory function in healthy older adults — randomized, double-blind, placebo-controlled trial. The Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/33978188/
- Kawamura T, et al. (2012). Glycerophosphocholine enhances growth hormone secretion and fat oxidation in young adults. Nutrition. https://pubmed.ncbi.nlm.nih.gov/22673596/



