
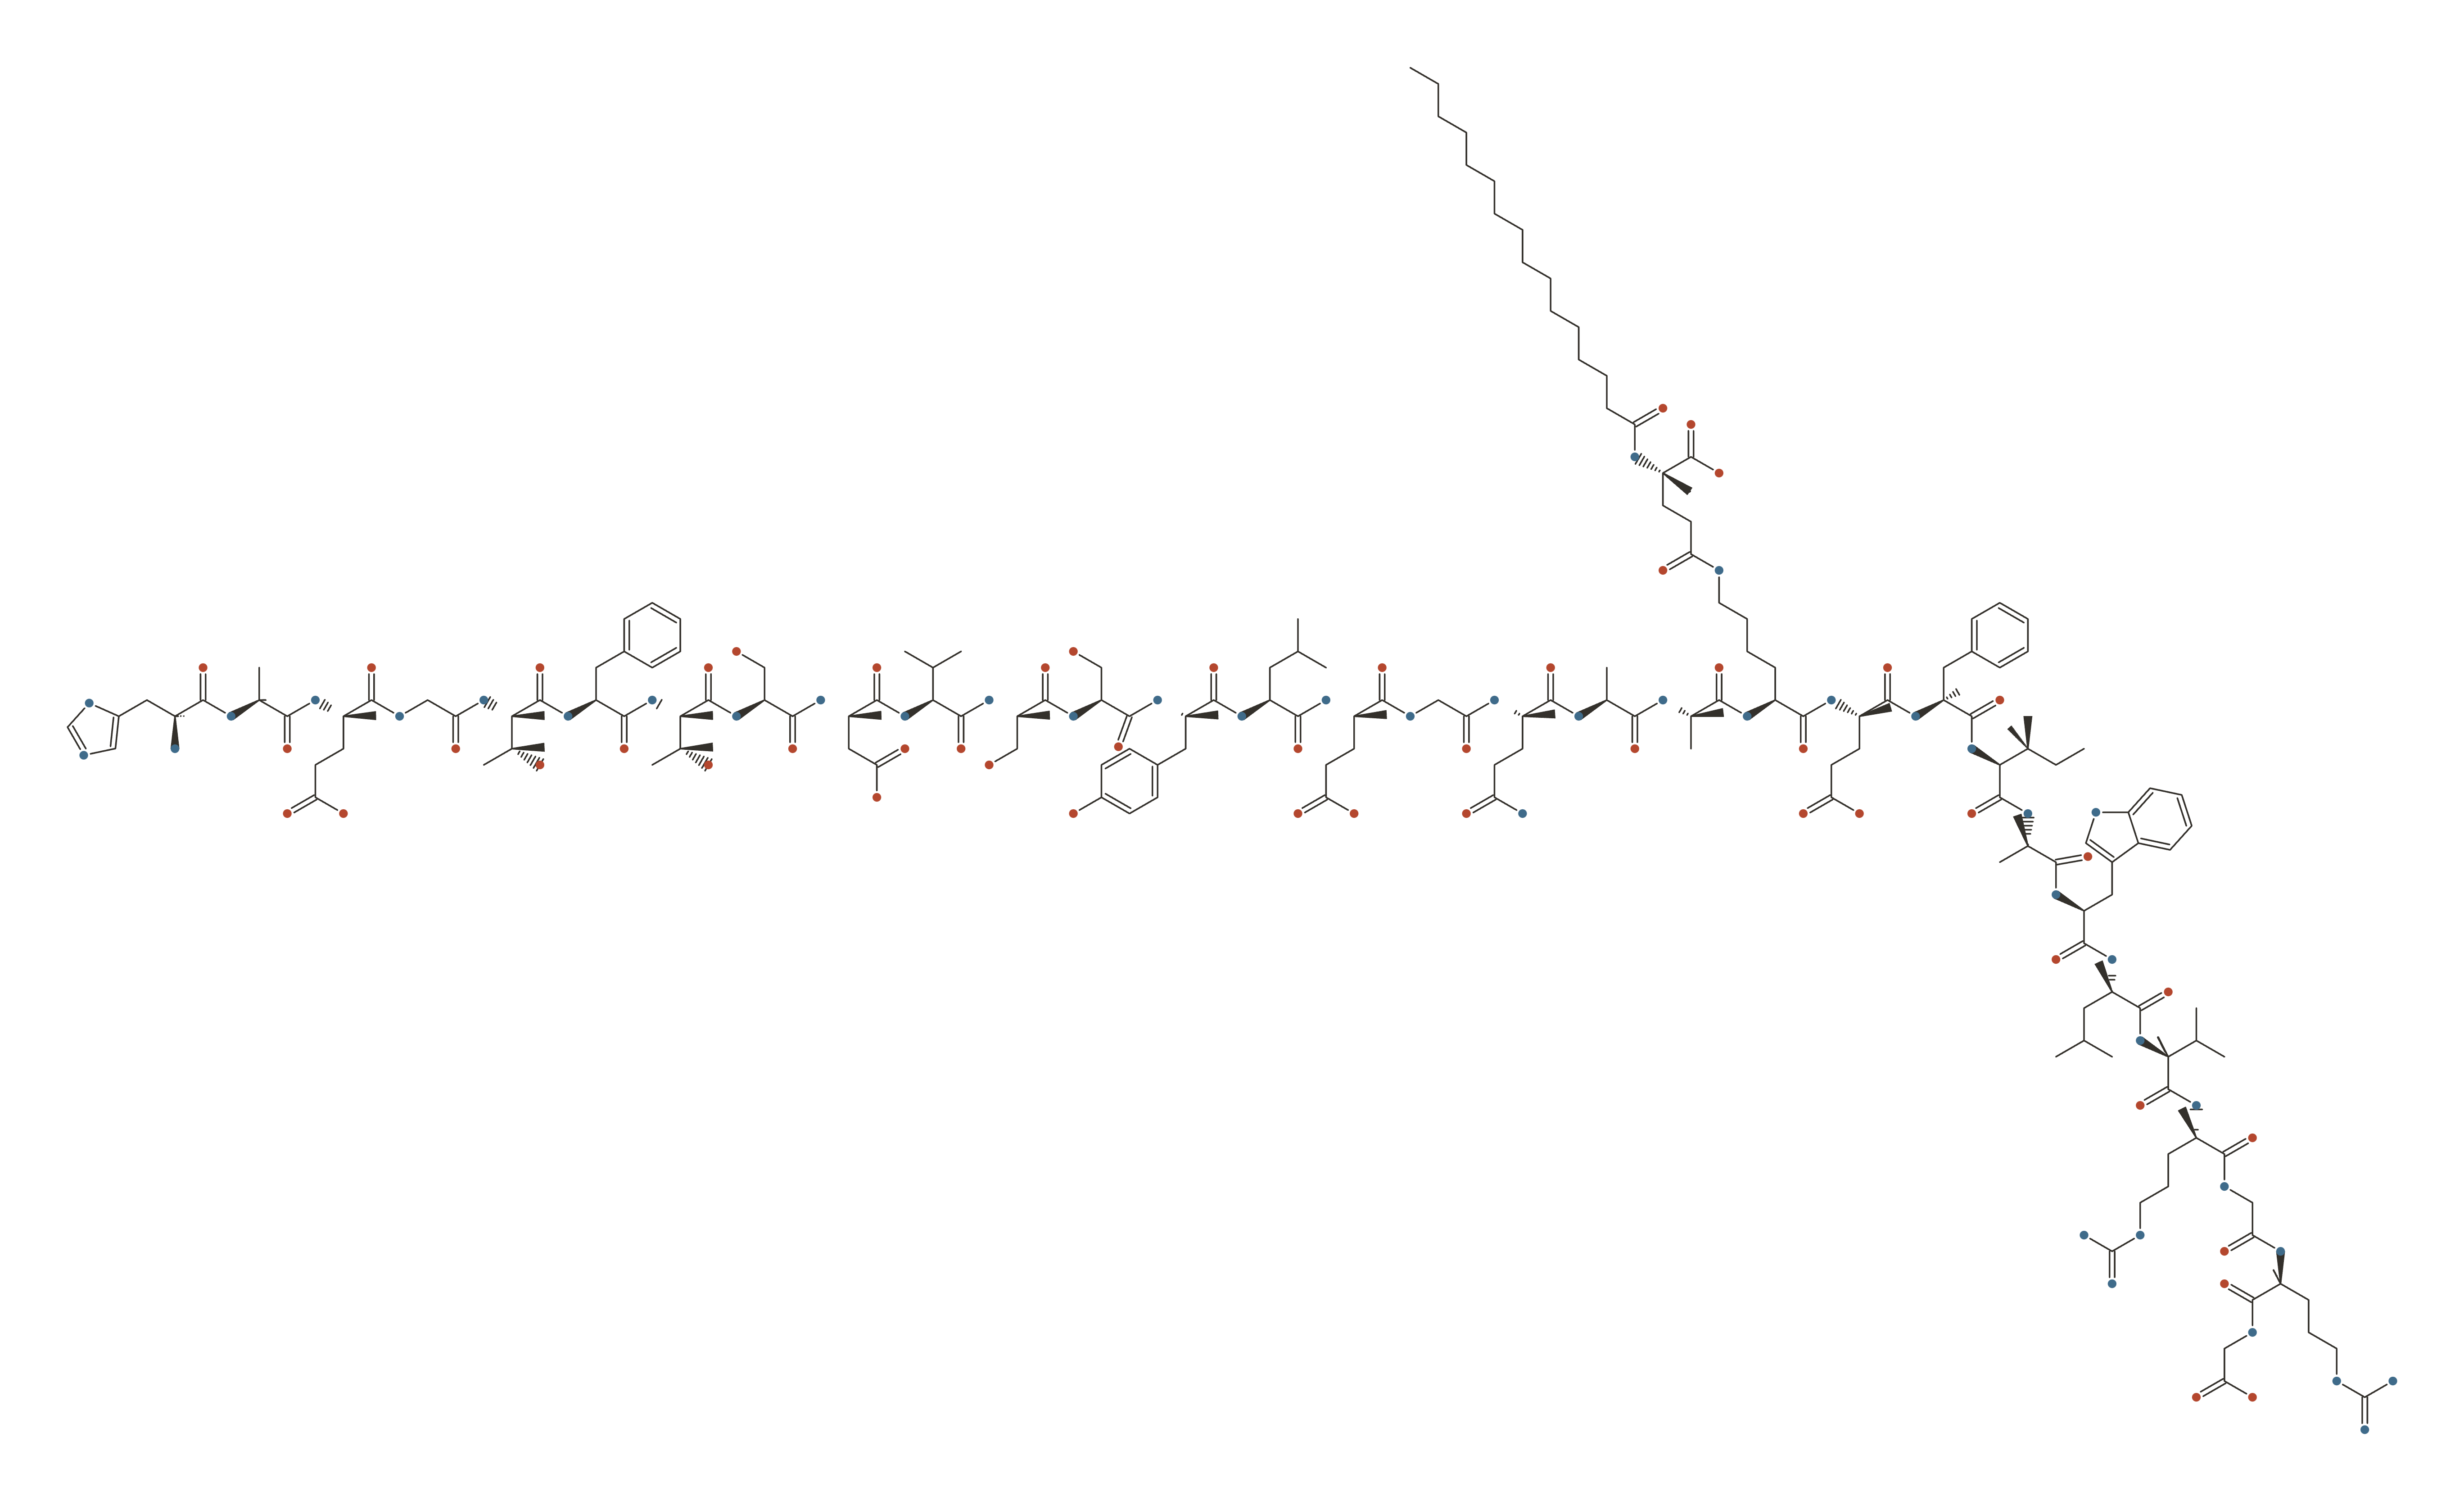

Liraglutide (Victoza / Saxenda) at a Glance
Liraglutide is the once-daily GLP-1 receptor agonist that preceded semaglutide, and the compound that established the class for weight management rather than diabetes alone. It works the same way — amplifying the post-meal signal that drives insulin release, slows gastric emptying and reduces appetite — with a shorter duration requiring daily injection. It is an approved prescription medicine for type 2 diabetes and chronic weight management, and its cardiovascular outcome data were among the first to show this class does more than lower blood sugar.
History & Development
Liraglutide was the compound that made GLP-1 into a usable medicine - the first of Novo Nordisk’s analogues to solve the problem that native GLP-1 disappears from the bloodstream within minutes.
| First described | Development programme described by its originators in 2019; originated as NN2211 25Reference 25The discovery and development of liraglutide and semaglutideView study → |
| Discovered / synthesised by | Novo Nordisk research programme; discovery account authored by Lotte Bjerre Knudsen and Jesper Lau 25Reference 25The discovery and development of liraglutide and semaglutideView study → |
| Institution | Novo Nordisk A/S, Maalov, Denmark 25Reference 25The discovery and development of liraglutide and semaglutideView study → |
| Origin | De-novo synthetic analogue of human GLP-1 |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Novo Nordisk A/S |
| Development status | Approved - EU 2009, FDA 2010 as Victoza (type 2 diabetes); later Saxenda (weight management) |
Discovery
The therapeutic target was type 2 diabetes, not obesity. GLP-1 had been identified as an incretin
- a hormone released by the gut after eating that prompts the pancreas to release insulin - and its appeal was that this effect is glucose-dependent, so it lowers blood sugar without the hypoglycaemia risk that comes with insulin itself.
The obstacle was entirely pharmacokinetic. Native GLP-1 is cleaved by DPP-4 within a couple of minutes, so the natural hormone cannot be given as a drug. Novo Nordisk’s solution was to attach a C16 palmitic acid via a linker, allowing the molecule to bind reversibly to circulating albumin 25Reference 25The discovery and development of liraglutide and semaglutideView study →. Bound peptide is protected from degradation and released gradually, which stretched the duration far enough for once-daily injection.
That albumin-binding strategy is the intellectual core of the entire class, and it is what semaglutide later extended - a C18 di-acid and a longer linker - to reach once-weekly dosing 25Reference 25The discovery and development of liraglutide and semaglutideView study →.
Development & ownership
Liraglutide originated at Novo Nordisk as NN2211 and stayed with the company throughout. It was approved in the European Union in 2009 and by the FDA in 2010 as Victoza for type 2 diabetes, subsequently gaining a cardiovascular risk-reduction indication on the strength of the LEADER outcome trial - one of the first results to show this class does more than lower blood sugar.
A higher-dose formulation was later approved as Saxenda for chronic weight management, making liraglutide the compound that established the transition of this drug class from diabetes into obesity medicine. The specific composition-of-matter patent was not established in the sources consulted for this section.
How it reached the market
Liraglutide reached patients through the standard regulatory route as a prescription medicine, and its market position has since been reshaped by its own successor: once-weekly semaglutide has displaced once-daily liraglutide for most new prescriptions, and liraglutide has begun to face generic competition as its protection lapses.
What It's Used For
Liraglutide is a 31-amino-acid analogue of human GLP-1(7-37) — 97% sequence-identical to the native incretin — carrying a C16 palmitic-acid side chain attached at Lys26 through a glutamic-acid spacer. That acylation does two things: it drives self-association at the injection depot and reversible binding to serum albumin, which together slow absorption and shield the peptide from dipeptidyl peptidase-4. The result is a half-life of about 13 hours and once-daily subcutaneous dosing. This is the drug that established the GLP-1 class in clinical practice — approved as Victoza for type 2 diabetes in 2010 and as Saxenda for chronic weight management in 2014 — and it is the one incretin on this hub whose story has moved past exclusivity: liraglutide is now available as a regulated generic in the US, EU and UK, which changes the sourcing calculus more than any pharmacological fact here.
Read alongside semaglutide and tirzepatide, liraglutide is the previous generation, and the honest framing is neither “lesser copy” nor “equal option”. On weight it is clearly beaten in head-to-head trials: weekly semaglutide 2.4 mg produced roughly twice the weight loss of daily liraglutide 3.0 mg in STEP 8 8Reference 8RCTEffect of Weekly Subcutaneous Semaglutide vs Daily Liraglutide on Body Weight (STEP 8) — human (RCT, head-to-head)View study →, and semaglutide 1.0 mg beat liraglutide 1.2 mg on both HbA1c and weight in SUSTAIN 10 9Reference 9RCTEfficacy and safety of once-weekly semaglutide 1.0 mg vs once-daily liraglutide 1.2 mg as add-on to 1–3 oral antidiabetic drugs in type 2 diabetes (SUSTAIN 10) — human (RCT, head-to-head)View study →.
There is no direct randomized comparison of liraglutide against tirzepatide — that chain is indirect, running through the semaglutide comparator. What liraglutide has instead is the longest continuous safety record in the class, a genuine positive cardiovascular outcomes trial (LEADER) 10Reference 10RCTLiraglutide and Cardiovascular Outcomes in Type 2 Diabetes (LEADER) — human (RCT, cardiovascular outcomes)View study →, the broadest pediatric licensing of any GLP-1 agonist, and an affordable, pharmacy-dispensed supply route that no other drug on this hub offers.
Route is load-bearing and absolute: a 31-residue peptide has negligible oral bioavailability, and unlike semaglutide there is no absorption-enhancer tablet. Liraglutide exists only as a subcutaneous injection.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
One row here is negative. The Alzheimer’s score is low because the trial was run and missed its primary endpoint — not because nobody has looked. A low number on this table can mean “untested” or “tested and failed”; here it means the latter, and the distinction matters.
This is human, approval-grade evidence and the founding indication. The phase 3 LEAD (Liraglutide Effect and Action in Diabetes) program tested liraglutide across the treatment ladder. In LEAD-3 Mono (n=746, 52 weeks, monotherapy), liraglutide 1.2 and 1.8 mg daily lowered HbA1c significantly more than glimepiride, with weight loss rather than weight gain and markedly less hypoglycemia 1Reference 1RCTLiraglutide versus glimepiride monotherapy for type 2 diabetes (LEAD-3 Mono) — human (RCT)View study →.
In LEAD-2 (added to metformin), liraglutide matched glimepiride on glycemic control while producing weight loss and fewer hypoglycemic episodes 2Reference 2RCTEfficacy and safety comparison of liraglutide, glimepiride, and placebo, all in combination with metformin, in type 2 diabetes (LEAD-2) — human (RCT)View study →.
In the open-label LEAD-6 head-to-head, once-daily liraglutide 1.8 mg lowered HbA1c more than twice-daily exenatide 10 µg 3Reference 3RCTLiraglutide once a day versus exenatide twice a day for type 2 diabetes (LEAD-6) — human (RCT, head-to-head)View study → — the comparison that effectively ended the first generation of GLP-1 agonists. The SCALE Diabetes RCT (JAMA, n=846 adults with type 2 diabetes and overweight or obesity) confirmed both weight and HbA1c effects at the 3.0 mg dose 5Reference 5RCTEfficacy of Liraglutide for Weight Loss Among Patients With Type 2 Diabetes (SCALE Diabetes) — human (RCT)View study →.
Gap: liraglutide is no longer the strongest option. SUSTAIN 10 (n=577) randomized adults with type 2 diabetes to once-weekly semaglutide 1.0 mg or once-daily liraglutide 1.2 mg and found semaglutide superior on both HbA1c and body weight 9Reference 9RCTEfficacy and safety of once-weekly semaglutide 1.0 mg vs once-daily liraglutide 1.2 mg as add-on to 1–3 oral antidiabetic drugs in type 2 diabetes (SUSTAIN 10) — human (RCT, head-to-head)View study →. Observational comparative-effectiveness work in a large veterans cohort (n=21,790) found broadly similar kidney and cardiovascular outcomes across liraglutide, semaglutide and dulaglutide, with the authors explicitly calling for head-to-head randomized trials 18Reference 18ObservationalLiraglutide vs Semaglutide vs Dulaglutide in Veterans With Type 2 Diabetes — human (target trial emulation, observational)View study → — so the efficacy gap is clearer on surrogate endpoints than on hard outcomes. Daily injection is also a real adherence cost against weekly agents.
This is human, approval-grade, hard-endpoint evidence — the highest evidence tier available anywhere on this hub. LEADER randomized 9,340 adults with type 2 diabetes at high cardiovascular risk to liraglutide (up to 1.8 mg daily) or placebo and followed them for a median 3.8 years. The primary composite of cardiovascular death, non-fatal myocardial infarction or non-fatal stroke occurred less often on liraglutide (13.0% vs 14.9%, HR 0.87), with significant reductions in cardiovascular death and all-cause mortality 10Reference 10RCTLiraglutide and Cardiovascular Outcomes in Type 2 Diabetes (LEADER) — human (RCT, cardiovascular outcomes)View study →.
This is placebo-controlled, which is worth stating plainly: it is a stronger design than tirzepatide’s active-comparator SURPASS-CVOT, which met noninferiority against dulaglutide but not superiority.
Gap: the population is type 2 diabetes with established or high cardiovascular risk. The result does not transfer to people using liraglutide for weight loss without diabetes — that population was never tested for cardiovascular outcomes with this molecule (semaglutide’s SELECT filled that gap for semaglutide, not for liraglutide). Liraglutide also raises resting heart rate by a few beats per minute, a consistent class effect confirmed in meta-analysis of non-diabetic overweight and obese participants 24Reference 24Meta-analysisEffect of glucagon-like peptide-1 receptor agonists on heart rate in non-diabetic individuals with overweight or obesity: a systematic review and pairwise and network meta-analysis of randomised controlled trials — human (meta-analysis)View study →; its long-term significance is unresolved.
This is human, approval-grade evidence. In the pivotal phase 3 SCALE Obesity and Prediabetes trial (n=3,731 adults with overweight or obesity, without diabetes), liraglutide 3.0 mg once daily plus lifestyle intervention produced a mean weight loss of about 8.4 kg (≈8.0%) versus 2.8 kg (≈2.6%) on placebo at 56 weeks, with far more participants reaching the ≥5% and ≥10% thresholds 4Reference 4RCTA Randomized, Controlled Trial of 3.0 mg of Liraglutide in Weight Management (SCALE Obesity and Prediabetes) — human (RCT)View study →.
SCALE Maintenance showed liraglutide could hold and extend low-calorie-diet-induced loss rather than merely produce it 6Reference 6RCTWeight maintenance and additional weight loss with liraglutide after low-calorie-diet-induced weight loss (SCALE Maintenance) — human (RCT)View study →, and the 3-year extension in participants with prediabetes reported sustained weight benefit and a substantially reduced rate of progression to type 2 diabetes 7Reference 7RCTle Roux CW, et al. (2017). 3 years of liraglutide versus placebo for type 2 diabetes risk reduction and weight management in individuals with prediabetes — human (RCT). Lancet. https://pubmed.ncbi.nlm.nih.gov/28237263/View study →.
Gap: the effect size is the weak point, and it has been measured directly. STEP 8 (n=338, 68 weeks) randomized adults with overweight or obesity without diabetes to weekly semaglutide 2.4 mg or daily liraglutide 3.0 mg: −15.8% versus −6.4% body weight 8Reference 8RCTEffect of Weekly Subcutaneous Semaglutide vs Daily Liraglutide on Body Weight (STEP 8) — human (RCT, head-to-head)View study →. Semaglutide roughly doubled the effect, with fewer participants discontinuing. Tirzepatide has never been compared with liraglutide directly, so its advantage is inferred through semaglutide rather than demonstrated. As with every drug in the class, weight returns after discontinuation — this is treatment, not cure.
This is human, approval-grade evidence in children and adolescents, and it is where liraglutide’s long tenure genuinely pays. Two dedicated phase 3 RCTs underpin two pediatric licenses.
For adolescent obesity, a randomized placebo-controlled trial (n=251, ages 12 to under 18) gave liraglutide 3.0 mg daily or placebo alongside lifestyle therapy for 56 weeks; liraglutide produced a significantly greater reduction in BMI standard-deviation score, and a greater proportion achieved ≥5% and ≥10% BMI reduction 11Reference 11RCTA Randomized, Controlled Trial of Liraglutide for Adolescents with Obesity — human (RCT, paediatric)View study →.
Saxenda was licensed for adolescents from age 12 on that basis. For youth-onset type 2 diabetes, the ELLIPSE trial (n=135, ages 10 to under 17, inadequately controlled on metformin with or without basal insulin) found HbA1c fell by 0.64 percentage points on liraglutide versus a 0.42-point rise on placebo at 26 weeks — a treatment difference of −1.06 points, sustained to 52 weeks 12Reference 12RCTLiraglutide in Children and Adolescents with Type 2 Diabetes (ELLIPSE) — human (RCT, paediatric)View study →.
Victoza was licensed from age 10 accordingly.
Gap: one pivotal trial per indication, each around 26–56 weeks, in populations that may be treated for decades. Long-term growth, pubertal and bone outcomes on chronic incretin therapy in children are unstudied. Weight regain after stopping was observed in adolescents as in adults 11Reference 11RCTA Randomized, Controlled Trial of Liraglutide for Adolescents with Obesity — human (RCT, paediatric)View study →, and gastrointestinal adverse events were more frequent than on placebo in both trials.
This is a small human phase 2 trial with a biopsy endpoint — real evidence, but two development stages behind semaglutide on the same disease. The LEAN trial (Lancet) was a multicenter, double-blind, placebo-controlled phase 2 study of liraglutide 1.8 mg daily in patients with biopsy-confirmed non-alcoholic steatohepatitis. Of 52 randomized patients, 9 of 23 (39%) on liraglutide achieved resolution of steatohepatitis without worsening of fibrosis, versus 2 of 22 (9%) on placebo 13Reference 13RCTLiraglutide safety and efficacy in patients with non-alcoholic steatohepatitis (LEAN) — human (RCT, phase 2)View study →.
Gap: n=52 is very small, this is phase 2, and no phase 3 trial of liraglutide in MASH has ever been run. The field moved to semaglutide (which now holds an accelerated approval for MASH with F2–F3 fibrosis) and to non-incretin agents. Liraglutide is not approved for liver disease anywhere, and given that development has effectively stopped, this row is unlikely to move.
This is a single human phase 3 RCT and not an approved indication. In SCALE Sleep Apnea (n=359 adults with obesity and moderate-to-severe obstructive sleep apnea unwilling or unable to use CPAP), liraglutide 3.0 mg daily reduced the apnea-hypopnea index by about 12.2 events per hour versus 6.1 on placebo at 32 weeks, alongside greater weight loss and improvements in HbA1c and systolic blood pressure 14Reference 14RCTEffect of liraglutide 3.0 mg in individuals with obesity and moderate or severe obstructive sleep apnea (SCALE Sleep Apnea) — human (RCT)View study →.
Gap: one trial, a modest absolute effect, and no license. The contrast with tirzepatide is instructive rather than incidental: tirzepatide ran two larger phase 3 trials, removed roughly 20–25 more events per hour than placebo, and became the first drug ever approved for OSA in December 2024. Liraglutide’s result is real, smaller, and was never taken to registration. The mechanism in both cases looks like weight loss unloading the upper airway rather than any airway-specific action, so benefit in non-obese OSA is untested.
This row exists to record evidence against. GLP-1 receptors are expressed in the brain, liraglutide crosses into the CNS, and preclinical models showed anti-inflammatory and neuroprotective effects — which is why the ELAD trial (NCT01843075) was run. ELAD was a randomized, double-blind, placebo-controlled phase 2b trial in 204 non-diabetic participants with mild-to-moderate Alzheimer’s disease, treated for 52 weeks. It missed its primary endpoint: there was no significant difference between liraglutide and placebo in the change in cerebral glucose metabolic rate on PET (difference −0.17; 95% CI −0.39 to 0.06; P=0.14) 15Reference 15RCTLiraglutide in mild to moderate Alzheimer’s disease: a phase 2b clinical trial (ELAD) — human (RCT, primary endpoint not met)View study →.
Volumetric MRI showed no significant group differences either. An unadjusted secondary analysis of executive function (ADAS-Exec) favored liraglutide (P=0.01), and exploratory voxel-based morphometry suggested less gray-matter decline — but these are secondary and exploratory endpoints in a trial whose primary endpoint failed, and they cannot carry a conclusion. Liraglutide was well tolerated.
Gap: none in the usual “nobody has looked” sense — the trial was done and it did not deliver. The context makes it worse rather than better: semaglutide’s much larger evoke and evoke+ phase 3 trials also read out negative in early Alzheimer’s disease. Two molecules, one failed phase 2b primary and two failed phase 3 programs. Liraglutide is not approved for any neurological indication and should not be used or sold for one. Whether GLP-1 agonism has a role in Parkinson’s disease or in pre-symptomatic neurodegeneration remains formally open, but the burden of proof has moved a long way.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| GLP-1 receptor (pancreatic β-cell) | ↑ glucose-dependent insulin secretion | Diabetespediatric T2D |
| GLP-1 receptor (pancreatic α-cell) | ↓ glucagon secretion | Diabetes |
| GLP-1 receptor (hypothalamic / hindbrain appetite centers) | ↓ appetite, ↑ satiety | Weight managementadolescent obesity |
| Gastric motility | Slowed gastric emptying | Post-prandial glycemia; GI adverse effects; gastroparesis and anesthesia aspiration risk |
| Cardiovascular (weight-, glycemia- and plausibly vascular-mediated) | ↓ MACE, ↓ cardiovascular and all-cause mortality | Cardiovascular risk in T2D (LEADER) |
| Hepatic fat & inflammation (largely weight-mediated) | ↓ steatosis, ↓ steatohepatitis | MASH (phase 2 only) |
| Sinoatrial / autonomic | ↑ resting heart rate by a few bpm (class effect) | Safety — long-term significance unresolved |
| CNS GLP-1 receptors | Anti-inflammatory / neuroprotective in preclinical models — did not translate in ELAD | Alzheimer’s disease (negative) |
| Albumin binding + depot self-association (C16 palmitoyl at Lys26) | Prolonged half-life (~13 h), DPP-4 resistance | Once-daily dosing (PK) |
Pharmacokinetics
Route is load-bearing, and here it is absolute. Liraglutide is given only by subcutaneous injection (abdomen, thigh or upper arm). A 31-residue peptide is digested rather than absorbed, and unlike semaglutide there is no SNAC-formulated oral tablet — no oral liraglutide exists in any approved form anywhere. Anything sold as “oral liraglutide”, sublingual drops or troches cannot deliver intact peptide.
Half-life is approximately 13 hours, which is why dosing is once daily rather than weekly. The duration comes from two engineered properties: the C16 palmitic-acid side chain attached at Lys26 via a glutamic-acid spacer drives reversible albumin binding and self-association into heptamers at the injection depot, slowing absorption and protecting the peptide from DPP-4 and neutral endopeptidase 16Reference 16In vitroOligomerization, albumin binding and catabolism of therapeutic peptides in the subcutaneous compartment: an investigation on lipidated GLP-1 analogs — in vitroView study →. Peak concentration is reached roughly 8–12 hours after injection. Rat work comparing lipidated and non-lipidated GLP-1 agonists found lymphatic uptake was similar for liraglutide and exenatide, indicating the acylation prolongs exposure through albumin binding and depot retention rather than through a lymphatic-routing effect 17Reference 17AnimalLymphatic uptake of the lipidated and non-lipidated GLP-1 agonists liraglutide and exenatide is similar in rats — animal (rat)View study → — animal data, cited for mechanism rather than for human dosing. Liraglutide is metabolized like a large protein, with no single organ dominating elimination, so no dose adjustment is specified for renal or hepatic impairment.
The shorter half-life has two practical consequences that cut in opposite directions. Against it: daily injection is a bigger adherence burden, and a missed dose produces a real gap in effect. For it: washout is days, not weeks — which matters when stopping ahead of a planned pregnancy, before surgery, or when an adverse effect needs to clear.
Licensed product is supplied as a sterile refrigerated solution in multi-dose prefilled pens, stored in the refrigerator before first use and at room temperature within a limited in-use window afterwards. Cold chain and in-use stability are part of the product specification.
Clinical & regulatory status
Liraglutide is an approved prescription medicine, not a dietary supplement and not a research chemical. Originated by Novo Nordisk as NN2211, it was approved by the FDA as Victoza (type 2 diabetes) in 2010 — later gaining a cardiovascular-risk-reduction indication in type 2 diabetes on the strength of LEADER, and a pediatric extension to age 10 on ELLIPSE — and as Saxenda (3.0 mg, chronic weight management) in 2014, extended to adolescents aged 12 and over in 2020. Corresponding approvals exist with the EMA, MHRA, TGA and elsewhere. It is prescription-only but not a scheduled/controlled substance.
The defining regulatory event is the loss of exclusivity. Liraglutide’s core patents have expired and it is now the first GLP-1 receptor agonist available as a generic — see Sourcing for the specific approvals and dates. Nothing else on this hub has crossed that line.
Registered trial activity remains substantial: about 513 interventional studies referencing liraglutide on ClinicalTrials.gov at the last check. Development of new indications has largely stopped, however — the sponsor’s program moved to semaglutide, and liraglutide’s remaining trial activity is mostly investigator-initiated. The headline readout of the last year was ELAD, which missed its primary endpoint 15Reference 15RCTLiraglutide in mild to moderate Alzheimer’s disease: a phase 2b clinical trial (ELAD) — human (RCT, primary endpoint not met)View study →; note that its registry record (NCT01843075) still shows an unknown status despite the 2026 publication, a reminder that registry status fields lag reality.
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| ~363(incl. LEAD 1–6, SCALE, LEADER, LEAN, ELLIPSE, ELAD) | ~37(recruiting + active; mostly investigator-initiated) | ~36(terminated or withdrawn) | extensive(foundational incretin and CNS biology) |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. Liraglutide is an approved prescription pharmaceutical — prescription-only, unscheduled, legal to possess and use with a valid prescription and dispensed through licensed pharmacies. That has been true since 2010. What is new, and what makes this section different from every other page on this hub, is who can now make it.
Generic liraglutide is real, approved, and on the market. This is the single most important practical fact about the compound:
- US, type 2 diabetes. The FDA approved the first generic of Victoza in December 2024 — the first generic of any once-daily GLP-1 injection — indicated to improve glycemic control in adults and pediatric patients aged 10 and over with type 2 diabetes. Hikma Pharmaceuticals launched it in the US that month.
- US, weight management. Teva announced FDA approval and US launch of generic Saxenda on 28 August 2025 — the first generic GLP-1 product carrying a weight-management indication, covering adults and pediatric patients aged 12 and over weighing more than 60 kg.
- Europe and the UK. Adalvo’s generic liraglutide prefilled pen received the first EU approval in June 2024; Biocon obtained the first UK approval in March 2024 and launched generic Victoza and Saxenda equivalents in the UK in February 2025, with Biocon/Zentiva securing EU decentralized-procedure approvals in December 2024. Further entrants have continued through 2026.
(These are regulatory and sponsor announcements, not journal articles, so they are attributed inline rather than numbered below.)
Why that reframes everything. Every other peptide on this hub presents the same dilemma: the only affordable supply is unregulated, so people buy lyophilized powder from vendors labeling it not for human consumption and perform the reconstitution, sterile handling, concentration arithmetic and dose measurement themselves. Liraglutide no longer sits in that dilemma. There is a licensed, pharmacy-dispensed, generically priced product carrying the same indications as the brand, made under manufacturing oversight, supplied in a prefilled pen, with a cold chain and a real adverse-event reporting pathway behind it. Anyone weighing gray-market GLP-1 powder against a prescription should know that for this molecule the regulated route is now the cheap route too. Given the effect-size gap to semaglutide, “cheaper and legal” is exactly the trade-off liraglutide now represents.
Gray-market liraglutide still exists, and it is now a worse deal than it used to be. Research-chemical vendors continue to sell liraglutide and generic “GLP-1” powders outside the prescription channel. The documented failure modes are unchanged and concrete: mislabeling (wrong peptide, wrong quantity, or a salt form never shown to be equivalent), sub- or super-potency, endotoxin and sterility failures, degradation from absent cold chain, and dosing errors during self-reconstitution — a licensed pen is engineered specifically to eliminate that last category. A third-party certificate of analysis is the minimum any buyer would want, and a COA from an unaccountable vendor is itself unverifiable. What has changed is the calculus: with a regulated generic available, the price argument that sustained the gray market for this molecule has largely evaporated, and buying unregulated liraglutide now means accepting identity and sterility risk to avoid a prescription rather than to avoid a cost.
How it’s supplied & administered. Licensed product — brand or generic — is a sterile refrigerated solution in a multi-dose prefilled pen, injected subcutaneously once daily and titrated upward by a clinician over weeks specifically to limit gastrointestinal effects.
This page does not recommend or link vendors. The efficacy and safety record above belongs to pharmaceutical-grade liraglutide used under medical supervision, and it does not transfer to material of unknown provenance.
Safety
Liraglutide is a prescription medicine with an approval-grade safety file, and the everyday experience of it is gastrointestinal — but the label-defining risks are the boxed thyroid C-cell warning and the pancreatic, biliary and gastric complications of a drug whose therapeutic action is to slow the gut.
- Boxed warning for thyroid C-cell tumors. Contraindicated with a personal or family history of medullary thyroid carcinoma or MEN 2.
- Pancreatitis, gallbladder disease and gastroparesis are label-carried risks. The signal concentrates at higher doses and in weight-loss rather than diabetes use.
- Not recommended in pregnancy. Discontinue when pregnancy is planned or recognized — see the box below.
- Tell the anesthetist or endoscopist before any sedation or surgery. Delayed gastric emptying is a documented aspiration concern.
- Gastrointestinal effects are dose-limiting. Nausea, vomiting, diarrhea and constipation, worst during titration and the leading reason for stopping.
- Additive hypoglycemia with insulin and sulfonylureas. The companion drug commonly needs its dose reduced.
Full Safety & Interactions Detail
Adverse effects (from trials). The dominant, dose-limiting effects are gastrointestinal — nausea, vomiting, diarrhea, constipation — dose-dependent, worst during titration, improving over time, and the leading reason for discontinuation across the LEAD and SCALE programs 1,
Gastroparesis and other serious GI events. A large population-based cohort study of GLP-1 receptor agonists prescribed for weight loss — including liraglutide specifically — found increased risks of pancreatitis, gastroparesis and bowel obstruction compared with bupropion-naltrexone 19Reference 19ObservationalRisk of Gastrointestinal Adverse Events Associated With Glucagon-Like Peptide-1 Receptor Agonists for Weight Loss — human (cohort)View study →. These are uncommon in absolute terms, but they are the mechanistically predictable consequence of a drug whose therapeutic action is to slow the gut, and they are more than a titration nuisance.
Delayed gastric emptying and anesthesia. Because liraglutide slows gastric emptying by design, retained stomach contents at induction of anesthesia or during upper endoscopy are a documented aspiration concern, and peri-procedural guidance in several jurisdictions now addresses GLP-1 receptor agonists as a class 22Reference 22ReviewClinical Consequences of Delayed Gastric Emptying With GLP-1 Receptor Agonists and Tirzepatide — reviewView study →. The ~13-hour half-life means the washout window is shorter than for the weekly agents, but the precaution is the same: anyone taking liraglutide should tell the anesthetist, endoscopist or proceduralist before any sedation or surgery.
Boxed warning. Liraglutide carries a boxed warning for thyroid C-cell tumors (medullary thyroid carcinoma) observed in rodents, and is contraindicated in anyone with a personal or family history of medullary thyroid carcinoma or Multiple Endocrine Neoplasia syndrome type 2 (MEN 2). The rodent finding has not been established in humans. The human picture is not entirely quiet, however: a French nationwide case-control study reported an association between 1–3 years of GLP-1 receptor agonist use and increased thyroid cancer risk, including medullary thyroid cancer 21Reference 21ObservationalGLP-1 Receptor Agonists and the Risk of Thyroid Cancer — human (nationwide case-control)View study →. That is observational, subject to detection bias, and contested — but it is why the contraindication is treated as absolute in practice rather than dismissed as a rodent artifact.
NAION — and this is where liraglutide differs from semaglutide. Non-arteritic anterior ischemic optic neuropathy is a sudden, usually irreversible loss of vision in one eye. The EMA’s pharmacovigilance committee concluded in June 2025 that NAION is a very rare side effect of semaglutide medicines, and semaglutide product information was updated accordingly. That labeling change is semaglutide-specific — it was not extended to liraglutide, and it is not imported here. The dedicated evidence supports that separation: a pooled analysis of placebo-controlled randomized trials of liraglutide and semaglutide (96,829 participants) found three confirmed NAION cases on GLP-1 receptor agonist versus five on placebo — roughly 3 versus 6 cases per 100,000 patient-years — and concluded the randomized data do not show an increased incidence versus placebo 23Reference 23RCTNon-arteritic anterior ischaemic optic neuropathy incidence in placebo-controlled clinical trials of liraglutide or semaglutide — human (pooled trial analysis)View study →. The observational signal that triggered the semaglutide review has not been reproduced in randomized data for liraglutide. Sudden vision loss on any treatment remains an urgent medical problem, but it is not a liraglutide-labeled risk.
Interactions. The clinically important, mechanism-based interactions are additive hypoglycemia with insulin and insulin secretagogues (sulfonylureas) — these commonly require dose reduction of the companion drug — and altered absorption and timing of orally co-administered medicines through delayed gastric emptying 22Reference 22ReviewClinical Consequences of Delayed Gastric Emptying With GLP-1 Receptor Agonists and Tirzepatide — reviewView study →. A complete interaction census belongs to the current label, not from here.
Who should avoid it. Anyone with a personal or family history of medullary thyroid carcinoma or MEN 2 (contraindicated); anyone with a history of pancreatitis; anyone with severe gastrointestinal disease or established gastroparesis; and — outside a supervised prescription — anyone who cannot guarantee product identity, sterility and correct dosing.
Scope disclosure (honesty, not a claim):
- Human data? Yes — extensive, approval-grade phase 3 RCTs across diabetes, weight, and cardiovascular outcomes, plus two pediatric pivotal trials and a phase 2b Alzheimer’s trial that missed its primary endpoint. This is the opposite of most peptides on this hub.
- Interactions assessed? Partially. The mechanism-based ones (insulin/sulfonylurea hypoglycemia, delayed gastric emptying affecting oral absorption, peri-procedural aspiration) are established; a complete census belongs to the current FDA/EMA label.
- Pregnancy/lactation assessed? At label level — not recommended in pregnancy; lactation data limited. No human outcome dataset.
- Long-term safety established? More so than anything else on this hub. Multi-year randomized data exist (LEADER over a median 3.8 years, the prediabetes extension over 3 years) and the molecule has been marketed since 2010 with a correspondingly long pharmacovigilance record. That still does not establish decade-scale safety, the safety of indefinite use for weight maintenance, the human relevance of the rodent thyroid C-cell signal, or long-term pediatric outcomes — and it says nothing at all about gray-market product.
Never imply safety from silence — and never transfer this trial record to unlicensed product. Everything above describes pharmaceutical-grade liraglutide used as prescribed.
Not recommended in pregnancy. The label advises against use, on the basis of animal reproductive-toxicity findings and the fact that intentional weight loss confers no benefit during pregnancy; liraglutide should be discontinued when pregnancy is planned or recognized. Human pregnancy safety is not established and lactation data are limited. The ~13-hour half-life means washout is a matter of days rather than the weeks required for semaglutide or tirzepatide — a genuine practical advantage in this specific situation. Two points still compound: delayed gastric emptying can affect oral contraceptive absorption, and weight loss itself can restore fertility in people who did not expect it. Contraception planning belongs at the start of treatment, not after.
Dosage
Liraglutide is a prescription medicine that is dosed and titrated by a clinician. Nothing here is a recommendation, and it must not be self-sourced or self-dosed. The figures below are reported as trial and label data for context.
For type 2 diabetes (Victoza and its generics), dosing starts at 0.6 mg once daily by subcutaneous injection — a starting dose intended for tolerability, not effect — and escalates after at least a week to 1.2 mg, and if needed to a maximum of 1.8 mg daily; this is the range used throughout the LEAD program and in LEADER 1,
The titration schedule is not a formality. Escalating faster than the label sequence is the main cause of severe gastrointestinal effects and of discontinuation. “Microdosing” — indefinite use of sub-therapeutic amounts, common in the gray market — has no trial evidence at all; it extrapolates from a dose-response curve that was never studied at those doses, usually using product whose actual concentration is unverified. This entry is informational only.
References
- Garber A, et al. (2009). Liraglutide versus glimepiride monotherapy for type 2 diabetes (LEAD-3 Mono) — human (RCT). Lancet. https://pubmed.ncbi.nlm.nih.gov/18819705/
- Nauck M, et al. (2009). Efficacy and safety comparison of liraglutide, glimepiride, and placebo, all in combination with metformin, in type 2 diabetes (LEAD-2) — human (RCT). Diabetes Care. https://pubmed.ncbi.nlm.nih.gov/18931095/
- Buse JB, et al. (2009). Liraglutide once a day versus exenatide twice a day for type 2 diabetes (LEAD-6) — human (RCT, head-to-head). Lancet. https://pubmed.ncbi.nlm.nih.gov/19515413/
- Pi-Sunyer X, et al. (2015). A Randomized, Controlled Trial of 3.0 mg of Liraglutide in Weight Management (SCALE Obesity and Prediabetes) — human (RCT). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/26132939/
- Davies MJ, et al. (2015). Efficacy of Liraglutide for Weight Loss Among Patients With Type 2 Diabetes (SCALE Diabetes) — human (RCT). JAMA. https://pubmed.ncbi.nlm.nih.gov/26284720/
- Wadden TA, et al. (2013). Weight maintenance and additional weight loss with liraglutide after low-calorie-diet-induced weight loss (SCALE Maintenance) — human (RCT). Int J Obes (Lond). https://pubmed.ncbi.nlm.nih.gov/23812094/
- le Roux CW, et al. (2017). 3 years of liraglutide versus placebo for type 2 diabetes risk reduction and weight management in individuals with prediabetes — human (RCT). Lancet. https://pubmed.ncbi.nlm.nih.gov/28237263/
- Rubino DM, et al. (2022). Effect of Weekly Subcutaneous Semaglutide vs Daily Liraglutide on Body Weight (STEP 8) — human (RCT, head-to-head). JAMA. https://pubmed.ncbi.nlm.nih.gov/35015037/
- Capehorn MS, et al. (2020). Efficacy and safety of once-weekly semaglutide 1.0 mg vs once-daily liraglutide 1.2 mg as add-on to 1–3 oral antidiabetic drugs in type 2 diabetes (SUSTAIN 10) — human (RCT, head-to-head). Diabetes Metab. https://pubmed.ncbi.nlm.nih.gov/31539622/
- Marso SP, et al. (2016). Liraglutide and Cardiovascular Outcomes in Type 2 Diabetes (LEADER) — human (RCT, cardiovascular outcomes). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/27295427/
- Kelly AS, et al. (2020). A Randomized, Controlled Trial of Liraglutide for Adolescents with Obesity — human (RCT, paediatric). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/32233338/
- Tamborlane WV, et al. (2019). Liraglutide in Children and Adolescents with Type 2 Diabetes (ELLIPSE) — human (RCT, paediatric). N Engl J Med. https://pubmed.ncbi.nlm.nih.gov/31034184/
- Armstrong MJ, et al. (2016). Liraglutide safety and efficacy in patients with non-alcoholic steatohepatitis (LEAN) — human (RCT, phase 2). Lancet. https://pubmed.ncbi.nlm.nih.gov/26608256/
- Blackman A, et al. (2016). Effect of liraglutide 3.0 mg in individuals with obesity and moderate or severe obstructive sleep apnea (SCALE Sleep Apnea) — human (RCT). Int J Obes (Lond). https://pubmed.ncbi.nlm.nih.gov/27005405/
- Edison P, et al. (2026). Liraglutide in mild to moderate Alzheimer’s disease: a phase 2b clinical trial (ELAD) — human (RCT, primary endpoint not met). Nat Med. https://pubmed.ncbi.nlm.nih.gov/41326666/
- Gallo M, et al. (2022). Oligomerization, albumin binding and catabolism of therapeutic peptides in the subcutaneous compartment: an investigation on lipidated GLP-1 analogs — in vitro. J Pharm Biomed Anal. https://pubmed.ncbi.nlm.nih.gov/35042144/
- Reddiar SB, et al. (2024). Lymphatic uptake of the lipidated and non-lipidated GLP-1 agonists liraglutide and exenatide is similar in rats — animal (rat). Eur J Pharm Biopharm. https://pubmed.ncbi.nlm.nih.gov/38789061/
- Derington CG, et al. (2025). Liraglutide vs Semaglutide vs Dulaglutide in Veterans With Type 2 Diabetes — human (target trial emulation, observational). JAMA Netw Open. https://pubmed.ncbi.nlm.nih.gov/41082229/
- Sodhi M, et al. (2023). Risk of Gastrointestinal Adverse Events Associated With Glucagon-Like Peptide-1 Receptor Agonists for Weight Loss — human (cohort). JAMA. https://pubmed.ncbi.nlm.nih.gov/37796527/
- He L, et al. (2022). Association of Glucagon-Like Peptide-1 Receptor Agonist Use With Risk of Gallbladder and Biliary Diseases: A Systematic Review and Meta-analysis of Randomized Clinical Trials — human (meta-analysis). JAMA Intern Med. https://pubmed.ncbi.nlm.nih.gov/35344001/
- Bezin J, et al. (2023). GLP-1 Receptor Agonists and the Risk of Thyroid Cancer — human (nationwide case-control). Diabetes Care. https://pubmed.ncbi.nlm.nih.gov/36356111/
- Jalleh RJ, et al. (2024). Clinical Consequences of Delayed Gastric Emptying With GLP-1 Receptor Agonists and Tirzepatide — review. J Clin Endocrinol Metab. https://pubmed.ncbi.nlm.nih.gov/39418085/
- Vilsbøll T, et al. (2026). Non-arteritic anterior ischaemic optic neuropathy incidence in placebo-controlled clinical trials of liraglutide or semaglutide — human (pooled trial analysis). Br J Ophthalmol. https://pubmed.ncbi.nlm.nih.gov/42049287/
- Zhang Y, et al. (2026). Effect of glucagon-like peptide-1 receptor agonists on heart rate in non-diabetic individuals with overweight or obesity: a systematic review and pairwise and network meta-analysis of randomised controlled trials — human (meta-analysis). Eur J Med Res. https://pubmed.ncbi.nlm.nih.gov/41582189/
- Knudsen, L. B., & Lau, J. (2019). The discovery and development of liraglutide and semaglutide. Frontiers in Endocrinology, 10, 155. https://pmc.ncbi.nlm.nih.gov/articles/PMC6474072/



