
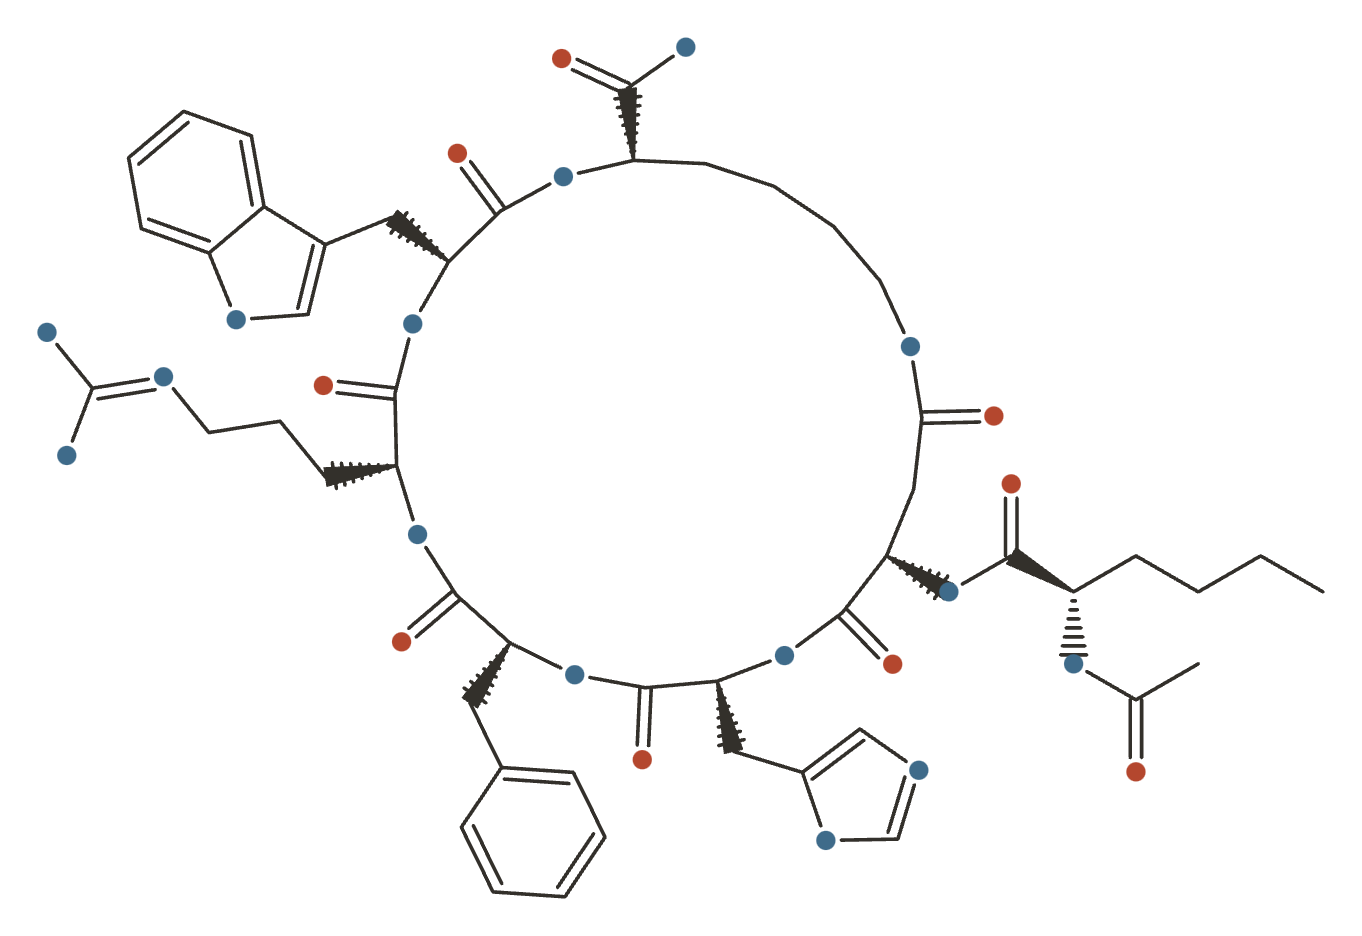
Melanotan II
An unapproved synthetic melanocortin-agonist peptide injected on the gray market as a tanning and libido aid, with a documented case-report harm record.

Melanotan II at a Glance
Melanotan-II is a synthetic, cyclic analogue of α-MSH that activates melanocortin receptors broadly, triggering melanin production and darkening skin without UV exposure. Because it hits several receptor subtypes at once it also produces the sexual arousal, nausea and flushing that led to PT-141 being developed from it. It was never approved anywhere and is injected on the grey market as a tanning and libido peptide.
History & Development
Melanotan-II came out of the same Arizona programme as its predecessor, and it is the compound whose side effect turned out to be more commercially interesting than its intended purpose.
| First described | Developed at the University of Arizona in the late 1980s-early 1990s, following the 1980 alpha-MSH analogue work 29Reference 29Sawyer, T. K., Sanfilippo, P. J., Hruby, V. J., Engel, M. H., Heward, C. B., Burnett, J. B., & Hadley, M. E. (1980). 4-Norleucine, 7-D-phenylalanine-alpha-melanocyte-stimulating hormone: a highly potent alpha-melanotropin with ultralong biological activity. Proceedings of the National Academy of Sciences, 77(10), 5754-5758. https://pubmed.ncbi.nlm.nih.gov/6777774/View study → |
| Discovered / synthesised by | The Hadley and Hruby melanocortin programme 29, |
| Institution | University of Arizona 29, |
| Origin | Cyclic synthetic analogue of the endogenous hormone alpha-MSH |
| Key patent | Not established in the sources consulted for this section |
| Assignee | n/a |
| Development status | Never approved in any jurisdiction; no completed development programme |
Discovery
The Arizona group’s founding work produced a superpotent, degradation-resistant alpha-MSH analogue in 1980 29Reference 29Sawyer, T. K., Sanfilippo, P. J., Hruby, V. J., Engel, M. H., Heward, C. B., Burnett, J. B., & Hadley, M. E. (1980). 4-Norleucine, 7-D-phenylalanine-alpha-melanocyte-stimulating hormone: a highly potent alpha-melanotropin with ultralong biological activity. Proceedings of the National Academy of Sciences, 77(10), 5754-5758. https://pubmed.ncbi.nlm.nih.gov/6777774/View study →. Melanotan-II followed as a cyclic analogue - a ring structure conferring further stability - developed as a candidate chemopreventive agent on the same reasoning: that inducing melanogenesis without ultraviolet exposure might reduce UV-driven DNA damage and skin cancer risk 30Reference 30UA-developed synthetic hormones speed a tanView study →.
The compound is less selective than melanotan-I, activating several melanocortin receptor subtypes rather than MC1 alone. That breadth is the origin of everything else about it. During early human testing the compound produced spontaneous erections and sexual arousal in male subjects - an unintended finding that redirected an entire line of research and led to PT-141 30Reference 30UA-developed synthetic hormones speed a tanView study →.
Development & ownership
Melanotan-II itself was never developed into a medicine. No company took it through a registered clinical programme, and it has never been approved anywhere. Its pharmacology instead produced two descendants that did reach approval by separating out one receptor effect each: afamelanotide for pigmentation, and bremelanotide for sexual desire.
The patent position and any assignee for melanotan-II specifically were not established in the sources consulted for this section.
How it reached the market
Melanotan-II reached consumers entirely outside pharmaceutical channels. It circulates as an unapproved injectable sold for tanning and libido, typically as lyophilised powder for self-reconstitution, and its non-selectivity means users encounter the nausea, flushing and spontaneous erections that were originally recorded as trial side effects. It is one of the clearest cases here of a research compound reaching the public without any development programme at all.
What It's Used For
Melanotan II (MT-II) is a synthetic, cyclic lactam-bridged analogue of α-melanocyte-stimulating hormone (α-MSH) that acts as a non-selective agonist across the melanocortin receptors — MC1R on melanocytes (skin darkening) and MC3R/MC4R in the hypothalamus (erection, appetite) 1,
Its evidence posture is unusual and worth stating plainly. MT-II does have a small, genuine human controlled-trial record from the 1990s — double-blind, placebo-controlled crossover studies of erectile response and a three-person phase I tanning pilot — but it was never taken through approval in any jurisdiction, and development pivoted instead to two relatives that were approved: melanotan I / afamelanotide (Scenesse, for erythropoietic protoporphyria) and PT-141 / bremelanotide (Vyleesi, an MT-II metabolite approved for hypoactive sexual desire disorder) 7,
MT-II is the unapproved, non-selective one in the middle. Everything beyond tanning and erection is rodent-only. Route is load-bearing: it is a peptide with negligible oral bioavailability, so it is injected subcutaneously (an illicit nasal spray also circulates). The decisive asymmetry here is that the most informative recent human literature about MT-II is not efficacy data at all — it is a run of adverse-event case reports: melanoma and eruptive atypical naevi, priapism, rhabdomyolysis, posterior reversible encephalopathy syndrome, and renal infarction 14,
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the strongest human data MT-II has — and it is small and old. In double-blind, placebo-controlled crossover studies in men, subcutaneous MT-II produced clinically apparent erections without sexual stimulation, quantified in real time by RigiScan. In men with psychogenic erectile dysfunction (n=10), MT-II produced erections in 8 of 10 with a mean duration of tip rigidity >80% of about 38 minutes versus roughly 3 minutes on placebo 3Reference 3RCTSynthetic melanotropic peptide initiates erections in men with psychogenic erectile dysfunction: double-blind, placebo controlled crossover study — human (RCT, crossover)View study →.
In men with organic erectile dysfunction (n=10), MT-II initiated erections after 12 of 19 injections versus 1 of 21 placebo doses, alongside self-reported increases in sexual desire 4Reference 4RCTEffect of an alpha-melanocyte stimulating hormone analog on penile erection and sexual desire in men with organic erectile dysfunction — human (RCT, crossover)View study →; the combined human series (n=20) is summarized separately 5Reference 5Clinical trialMelanocortin receptor agonists, penile erection, and sexual motivation: human studies with Melanotan II — human (controlled clinical trial)View study →.
The mechanism is central, not vascular — MC3R/MC4R signaling in the paraventricular nucleus — confirmed in anesthetized rats, where MT-II acts as both inducer and facilitator of erection 9Reference 9AnimalMelanotan-II: investigation of the inducer and facilitator effects on penile erection in anaesthetized rat — animal (rat)View study →.
Nausea and yawning/stretching were dose-limiting even at erectogenic doses 4,
MT-II’s own development then stopped; the melanocortin sexual-function program continued as bremelanotide (PT-141), which reached FDA approval for female hypoactive sexual desire disorder 7,
Gap: Every human trial is small (n≤20), decades old, single-center and short-term. MT-II was never advanced to phase III and never approved, and there is no controlled data on repeated real-world dosing.
Tanning is MT-II’s flagship real-world use, and the mechanism is not in doubt — agonism at melanocyte MC1R upregulates eumelanin synthesis 2Reference 2ReviewDiscovery and development of novel melanogenic drugsView study →.
The formal human record, however, is remarkably thin: the pivotal study is a 1996 phase I pilot in three male volunteers given daily subcutaneous MT-II, which produced visible tanning together with nausea, facial flushing and spontaneous erections 1Reference 1Clinical trialEvaluation of melanotan-II, a superpotent cyclic melanotropic peptide in a pilot phase-I clinical study — human (phase I, n=3)View study →.
Everything past that pilot is observational — a qualitative study of online-forum users and case material confirm that the pigmentation effect is real and reproducible in practice, but cannot establish dose-response, durability or safety 22,
Two cautions matter here. First, several widely-cited “melanotan” tanning trials actually studied the analogue afamelanotide (melanotan I), not MT-II — do not conflate them. Second, the pigment-cell stimulation that produces the tan is the same mechanism behind the melanoma and atypical-naevi reports in Safety below; tanning efficacy and the principal safety concern are not separable.
Gap: Human efficacy rests on a single three-person pilot. There is no controlled dose-response trial and no safety trial for MT-II tanning at all.
Rodent only. Centrally administered (intracerebroventricular) MT-II inhibits feeding and blunts the orexigenic and adipogenic effects of neuropeptide Y in male rats, consistent with MC4R-mediated satiety signaling 10Reference 10AnimalThe melanocortin agonist Melanotan-II reduces the orexigenic and adipogenic effects of neuropeptide Y in the male rat — animal (rat)View study →. The pathway is human-relevant in principle — the selective MC4R agonist setmelanotide is an FDA-approved drug for rare genetic (POMC/LEPR) obesity — but that is a different, selective molecule, and there is no human MT-II weight-loss trial of any kind. Appetite suppression is commonly reported by gray-market users 22Reference 22Melanotan II user experience: a qualitative study of online discussion forums — human (qualitative)View study →; that is a sociological observation about a self-selected, unblinded population, not evidence, and it is not scored.
Gap: No human MT-II data. Mechanistic plausibility plus a validated cousin drug transfers neither efficacy nor safety.
Rodent only, single model. In Otsuka Long-Evans Tokushima Fatty (OLETF) rats, subcutaneous MT-II delivered by osmotic mini-pump reduced food intake and body weight and improved insulin sensitivity and glucose tolerance on tolerance testing 11Reference 11AnimalThe melanocortin agonist melanotan II increases insulin sensitivity in OLETF rats — animal (rat)View study →. Whether this reflects a direct melanocortin metabolic effect or is simply secondary to reduced intake and weight loss is not resolved in the study, and there is no independent replication.
Gap: One rat strain, one lab, confounded by weight loss; no human data whatsoever.
Rodent only, single study. In rats, MT-II promoted peripheral-nerve regeneration and showed neuroprotective properties after sciatic-nerve injury 12Reference 12AnimalThe potent melanocortin receptor agonist melanotan-II promotes peripheral nerve regeneration and has neuroprotective properties in the rat — animal (rat)View study →. This is the kind of isolated preclinical finding that circulates in community writing as a general “healing” property of the peptide; it is one study from one group in one species, with no replication and no human work.
Gap: Single-lab rodent result, unreplicated, with no human data and no plausible route to it given the compound’s regulatory status.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| MC1R (melanocytes) | ↑ eumelanin synthesis → skin darkening | Tanning; also the melanoma/atypical-naevi concern |
| MC3R / MC4R (hypothalamus, PVN) | ↑ pro-erectile signaling | Erection (human + rat) |
| MC4R (central) | ↑ satiety; ↑ sympathetic tone / energy expenditure | Appetiteweight (rodent) |
| MC5R | Exocrine and other peripheral roles; poorly characterized for MT-II | — |
| Melanocortin system (peripheral, rodent) | Neurotrophic and insulin-sensitizing signals | Nerve regenerationglucose (rodent only) |
| Autonomic / vascular (central melanocortin) | Blood-pressure change, flushing, nausea, yawning/stretching | Dose-limiting effects; priapism risk |
MT-II is deliberately non-selective, and that breadth is the whole story: one molecule tans, erects and suppresses appetite because it hits four receptor subtypes at once — and the same non-selectivity is why the side-effect profile (nausea, blood-pressure change, priapism) tracks its central melanocortin activity rather than being separable from its cosmetic effect.
Pharmacokinetics
MT-II is a peptide with negligible oral bioavailability, so it is given subcutaneously; an illicit nasal-spray route also circulates 21Reference 21Case reportMelanotan II nasal spray: a possible risk factor for oral mucosal malignant melanoma? — human (case report)View study →. This is load-bearing rather than incidental — oral “melanotan” products cannot deliver intact peptide, and every rodent finding above was produced by injection or direct central administration. Human pharmacokinetics are essentially unpublished. The only formal PK study is preclinical: an LC-MS/MS characterization of MT-II disposition after intravenous dosing in rats 13Reference 13AnimalDetermination of melanotan-II in rat plasma by liquid chromatography/tandem mass spectrometry: pharmacokinetic parameters following intravenous administration — animal (rat, PK)View study →. By class, and by the hours-long duration of the erectile and flushing effects reported in the human trials 3,
Clinical & regulatory status
Melanotan II has never been approved as a medicine or a dietary supplement in any jurisdiction. Its entire human clinical record is a handful of small investigator-led studies from 1996–2000 that predate modern trial registration 1,
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 0registered* | 0 | Development discontinued (→ PT-141) | ~dozens(rodent) |
*Four small investigator-led human studies (1996–2000) exist but were never entered in trial registries 1,
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. MT-II is an unapproved research chemical with no marketing authorization anywhere in the world. Its sale for human consumption is illegal in the UK — where the MHRA has issued explicit warnings — and in many other countries, so it is typically marketed “for research use only / not for human consumption” to sidestep medicines law 21,
How it’s supplied & administered. Gray-market MT-II is sold as lyophilized powder in vials, reconstituted by the user — usually with bacteriostatic water — for subcutaneous injection; an illicit nasal spray also circulates and has its own reported harm (a 2025 case report describes oral mucosal melanoma after nasal-spray use) 21Reference 21Case reportMelanotan II nasal spray: a possible risk factor for oral mucosal malignant melanoma? — human (case report)View study →. Oral use is pharmacologically pointless. Reconstituted product should be refrigerated, but real-world storage, dosing accuracy and sterility are entirely in the hands of the user.
Sourcing reality (this is a safety issue, not a footnote). MT-II is produced and sold by unregulated vendors with no manufacturing oversight. Forensic analysis of black-market pigmentation and “sexual enhancer” products has characterized MT-II and bremelanotide sold without reference standards and alongside anabolic steroids and other performance-and-image-enhancing drugs — an unverified supply chain by construction 23Reference 23LC-HRMS characterization of the skin pigmentation and sexual enhancers melanotan II and bremelanotide sold on the black market — forensic product analysisView study →. What follows directly: mislabeling and unknown purity, endotoxin and microbial contamination, non-sterile reconstitution, injection-site infection, and dosing error from self-mixed concentrations. There is no meaningful certificate-of-analysis guarantee; where third-party testing exists at all it is vendor-commissioned. No vendors are recommended or linked here.
Safety
Melanotan II has no controlled long-term human safety data at all, and unusually for a research peptide the published human literature that does exist is predominantly a record of harm — melanoma and atypical moles, priapism, and acute systemic toxicity, all from an unregulated injectable.
- Case reports of new, changing and eruptive atypical moles — and of melanoma. Mechanism-driven via MC1R; anyone who has used it and notices a changing mole should get dermatological review.
- Priapism is the best-documented serious harm. A urological emergency that risks permanent erectile dysfunction if not treated promptly.
- Rhabdomyolysis, PRES and renal infarction have all been reported. Blood-pressure dysregulation and self-mixed dosing leave a thin margin.
- Contraindicated in pregnancy and breastfeeding. Not assessed — see the box below.
- An unapproved, unregulated gray-market injectable. Regulators including the UK MHRA have warned against it, and identity, purity and sterility are unverifiable.
- Nausea is dose-limiting even at erectogenic doses. Facial flushing, yawning and stretching, and blood-pressure changes are the other common effects.
Full Safety & Interactions Detail
Overall posture. This is the section that carries the page. MT-II has no controlled long-term human safety data of any kind, and unusually for a research peptide it has a real, published case-report harm literature — which is documented below with its citations, not softened.
Adverse effects seen in the human trials. Across the erectile and tanning studies the common effects were nausea, facial flushing, yawning and stretching, and blood-pressure changes, with nausea effectively dose-limiting even at erectogenic doses 1,
Priapism. The best-documented serious harm is priapism — a prolonged, painful, low-flow (ischemic) erection that is a urological emergency requiring cavernosal aspiration/irrigation and intracavernosal phenylephrine, and that risks permanent erectile dysfunction if not treated promptly. It has been reported after subcutaneous MT-II used for tanning 14Reference 14Case reportMelanotan tanning injection: a rare cause of priapism — human (case report)View study →, in a further indexed case 15Reference 15Case reportMelanotan-induced priapism: a hard-earned tan — human (case report)View study →, and specifically in the context of overdose 28Reference 28Case reportMelanotan II overdose associated with priapism — human (case report)View study →.
Rhabdomyolysis and systemic toxicity. A case of systemic sympathomimetic toxicity with rhabdomyolysis was reported after a 6 mg subcutaneous dose — roughly six times the user’s intended starting amount — illustrating how thin the margin is when dosing is self-mixed from a reconstituted powder 16Reference 16Case reportMelanotan II injection resulting in systemic toxicity and rhabdomyolysis — human (case report)View study →.
Posterior reversible encephalopathy syndrome (PRES). A case of posterior reversible encephalopathy syndrome — a neurological syndrome of headache, seizure, visual disturbance and characteristic imaging changes, typically driven by acute blood-pressure dysregulation — has been reported in association with melanotan use 26Reference 26Case reportMelanotan and the posterior reversible encephalopathy syndrome — human (case report)View study →. This is consistent with the compound’s central melanocortin effects on sympathetic outflow and blood pressure.
Renal injury. Renal infarction has been reported as a possible consequence of MT-II use, published with a review of the literature 27Reference 27Case reportMelanotan II: a possible cause of renal infarction — review of the literature and case report — human (case report + review)View study →.
Pigmented lesions and melanoma (mechanism-driven, and the key long-latency concern). Because MT-II directly stimulates melanocytes via MC1R, there are repeated case reports of new or rapidly changing atypical melanocytic naevi, eruptive melanocytic naevi, and cutaneous melanoma temporally associated with use 17,
Injection-specific and sourcing risks. Because the product is a self-injected, self-reconstituted, unregulated powder, add injection-site reactions, non-sterile technique, contamination and endotoxin exposure, and unknown purity and dose to everything above (see Sourcing) 23Reference 23LC-HRMS characterization of the skin pigmentation and sexual enhancers melanotan II and bremelanotide sold on the black market — forensic product analysisView study →.
Interactions. No formal interaction studies exist for MT-II. Mechanistically, co-use with PDE5 inhibitors (sildenafil and relatives) is a plausible additive erectile and hypotensive hazard — the related melanocortin PT-141 showed enhanced erectile response combined with low-dose sildenafil, and blood-pressure monitoring was a live concern in that program 6Reference 6ReviewMelanocortins in the treatment of male and female sexual dysfunction — reviewView study →. Treat any vasodilator or antihypertensive co-use as an unassessed hazard, not a cleared one.
Who should avoid it. Anyone with a personal or family history of melanoma, atypical-mole syndrome, or a high naevus count; anyone with cardiovascular disease or uncontrolled blood pressure; anyone predisposed to priapism (including sickle-cell disease); and — given the status — anyone who wants an approved, tested product, because this is not one.
Scope disclosure (honesty, not a claim):
- Human data? Yes, but limited and old — small double-blind placebo-controlled crossover erection trials (n≤20, 1996–2000) and a three-person tanning pilot. No approved-indication RCT and no long-term human data. All non-sexual, non-tanning applications are preclinical only.
- Interactions assessed? No. One mechanistically relevant class is flagged (PDE5 inhibitors, by read-across from the PT-141 program) and it is inferred, not tested.
- Pregnancy / lactation assessed? No — not assessed, not established.
- Long-term safety established? No. There is no controlled long-term safety data whatsoever. The melanoma and atypical-naevi signal is exactly the long-latency harm that the absence of trials cannot exclude.
Never imply safety from silence. Where MT-II has not been studied — interactions, pregnancy, long-term use, gray-market product purity — the correct statement is “not assessed,” not “safe.” And here the silence is not even neutral: the published human literature that does exist is predominantly a record of harm.
Not assessed / not established. There are no human pregnancy or lactation data and no accessible animal reproductive-toxicity data for MT-II. Treat as contraindicated in pregnancy and breastfeeding.
Dosage
There is no established human dose for Melanotan II, and none is recommended here. It has never been approved anywhere, no dose-finding study exists, and this is documentation of a widely used unapproved compound, not a protocol.
For context only: the 1990s human studies dosed MT-II subcutaneously at roughly 0.025 mg/kg, with nausea dose-limiting at or near the erectogenic dose 3,
References
- Dorr RT, et al. (1996). Evaluation of melanotan-II, a superpotent cyclic melanotropic peptide in a pilot phase-I clinical study — human (phase I, n=3). Life Sciences. https://pubmed.ncbi.nlm.nih.gov/8637402/
- Hadley ME, et al. (1998). Discovery and development of novel melanogenic drugs. Melanotan-I and -II — review. Pharmaceutical Biotechnology. https://pubmed.ncbi.nlm.nih.gov/9760697/
- Wessells H, et al. (1998). Synthetic melanotropic peptide initiates erections in men with psychogenic erectile dysfunction: double-blind, placebo controlled crossover study — human (RCT, crossover). Journal of Urology. https://pubmed.ncbi.nlm.nih.gov/9679884/
- Wessells H, et al. (2000). Effect of an alpha-melanocyte stimulating hormone analog on penile erection and sexual desire in men with organic erectile dysfunction — human (RCT, crossover). Urology. https://pubmed.ncbi.nlm.nih.gov/11018622/
- Wessells H, et al. (2000). Melanocortin receptor agonists, penile erection, and sexual motivation: human studies with Melanotan II — human (controlled clinical trial). International Journal of Impotence Research. https://pubmed.ncbi.nlm.nih.gov/11035391/
- Shadiack AM, et al. (2007). Melanocortins in the treatment of male and female sexual dysfunction — review. Current Topics in Medicinal Chemistry. https://pubmed.ncbi.nlm.nih.gov/17584134/
- Molinoff PB, et al. (2003). PT-141: a melanocortin agonist for the treatment of sexual dysfunction — human (clinical trial). Annals of the New York Academy of Sciences. https://pubmed.ncbi.nlm.nih.gov/12851303/
- Kingsberg SA, et al. (2019). Bremelanotide for the treatment of hypoactive sexual desire disorder: two randomized phase 3 trials — human (RCT, phase III). Obstetrics & Gynecology. https://pubmed.ncbi.nlm.nih.gov/31599840/
- Giuliano F, et al. (2006). Melanotan-II: investigation of the inducer and facilitator effects on penile erection in anaesthetized rat — animal (rat). Neuroscience. https://pubmed.ncbi.nlm.nih.gov/16360286/
- Raposinho PD, et al. (2003). The melanocortin agonist Melanotan-II reduces the orexigenic and adipogenic effects of neuropeptide Y in the male rat — animal (rat). Journal of Neuroendocrinology. https://pubmed.ncbi.nlm.nih.gov/12535159/
- Banno R, et al. (2004). The melanocortin agonist melanotan II increases insulin sensitivity in OLETF rats — animal (rat). Peptides. https://pubmed.ncbi.nlm.nih.gov/15350695/
- Ter Laak MP, et al. (2003). The potent melanocortin receptor agonist melanotan-II promotes peripheral nerve regeneration and has neuroprotective properties in the rat — animal (rat). European Journal of Pharmacology. https://pubmed.ncbi.nlm.nih.gov/12591111/
- Mock S, et al. (2002). Determination of melanotan-II in rat plasma by liquid chromatography/tandem mass spectrometry: pharmacokinetic parameters following intravenous administration — animal (rat, PK). Rapid Communications in Mass Spectrometry. https://pubmed.ncbi.nlm.nih.gov/12415547/
- Mallory CW, et al. (2021). Melanotan tanning injection: a rare cause of priapism — human (case report). Sexual Medicine. https://pubmed.ncbi.nlm.nih.gov/33460908/
- Dreyer BA, et al. (2019). Melanotan-induced priapism: a hard-earned tan — human (case report). BMJ Case Reports. https://pubmed.ncbi.nlm.nih.gov/30796078/
- Nelson ME, et al. (2012). Melanotan II injection resulting in systemic toxicity and rhabdomyolysis — human (case report). Clinical Toxicology. https://pubmed.ncbi.nlm.nih.gov/23121206/
- Hjuler KF, et al. (2014). Melanoma associated with the use of melanotan-II — human (case report). Dermatology. https://pubmed.ncbi.nlm.nih.gov/24355990/
- Paurobally D, et al. (2011). Melanotan-associated melanoma — human (case report). British Journal of Dermatology. https://pubmed.ncbi.nlm.nih.gov/21564053/
- Reid C, et al. (2013). Atypical melanocytic naevi following melanotan injection — human (case report). Irish Medical Journal. https://pubmed.ncbi.nlm.nih.gov/23914578/
- Burian EA, et al. (2019). Eruptive melanocytic nevi: a review — review. American Journal of Clinical Dermatology. https://pubmed.ncbi.nlm.nih.gov/31119650/
- Yassin Alsabbagh A, et al. (2025). Melanotan II nasal spray: a possible risk factor for oral mucosal malignant melanoma? — human (case report). International Journal of Oral and Maxillofacial Surgery. https://pubmed.ncbi.nlm.nih.gov/40210573/
- Gilhooley E, et al. (2021). Melanotan II user experience: a qualitative study of online discussion forums — human (qualitative). Dermatology. https://pubmed.ncbi.nlm.nih.gov/34464955/
- Mestria S, et al. (2021). LC-HRMS characterization of the skin pigmentation and sexual enhancers melanotan II and bremelanotide sold on the black market — forensic product analysis. Drug Testing and Analysis. https://pubmed.ncbi.nlm.nih.gov/33245851/
- Evans-Brown M, et al. (2009). Use of melanotan I and II in the general population — editorial. BMJ. https://pubmed.ncbi.nlm.nih.gov/19224885/
- Van Hout MC, et al. (2014). An in-depth case examination of an exotic dancer’s experience of melanotan — human (case study). International Journal of Drug Policy. https://pubmed.ncbi.nlm.nih.gov/24280586/
- Kaski D, et al. (2013). Melanotan and the posterior reversible encephalopathy syndrome — human (case report). Annals of Internal Medicine. https://pubmed.ncbi.nlm.nih.gov/23648958/
- Peters B, et al. (2020). Melanotan II: a possible cause of renal infarction — review of the literature and case report — human (case report + review). CEN Case Reports. https://pubmed.ncbi.nlm.nih.gov/31953620/
- Devlin J, et al. (2013). Melanotan II overdose associated with priapism — human (case report). Clinical Toxicology. https://pubmed.ncbi.nlm.nih.gov/23537392/
- Sawyer, T. K., Sanfilippo, P. J., Hruby, V. J., Engel, M. H., Heward, C. B., Burnett, J. B., & Hadley, M. E. (1980). 4-Norleucine, 7-D-phenylalanine-alpha-melanocyte-stimulating hormone: a highly potent alpha-melanotropin with ultralong biological activity. Proceedings of the National Academy of Sciences, 77(10), 5754-5758. https://pubmed.ncbi.nlm.nih.gov/6777774/
- Arizona Daily Star. UA-developed synthetic hormones speed a tan. https://tucson.com/news/local/education/college/ua-developed-synthetic-hormones-speed-a-tan/article_1aa2c79c-a216-5579-aead-7d012f7e02da.html



