
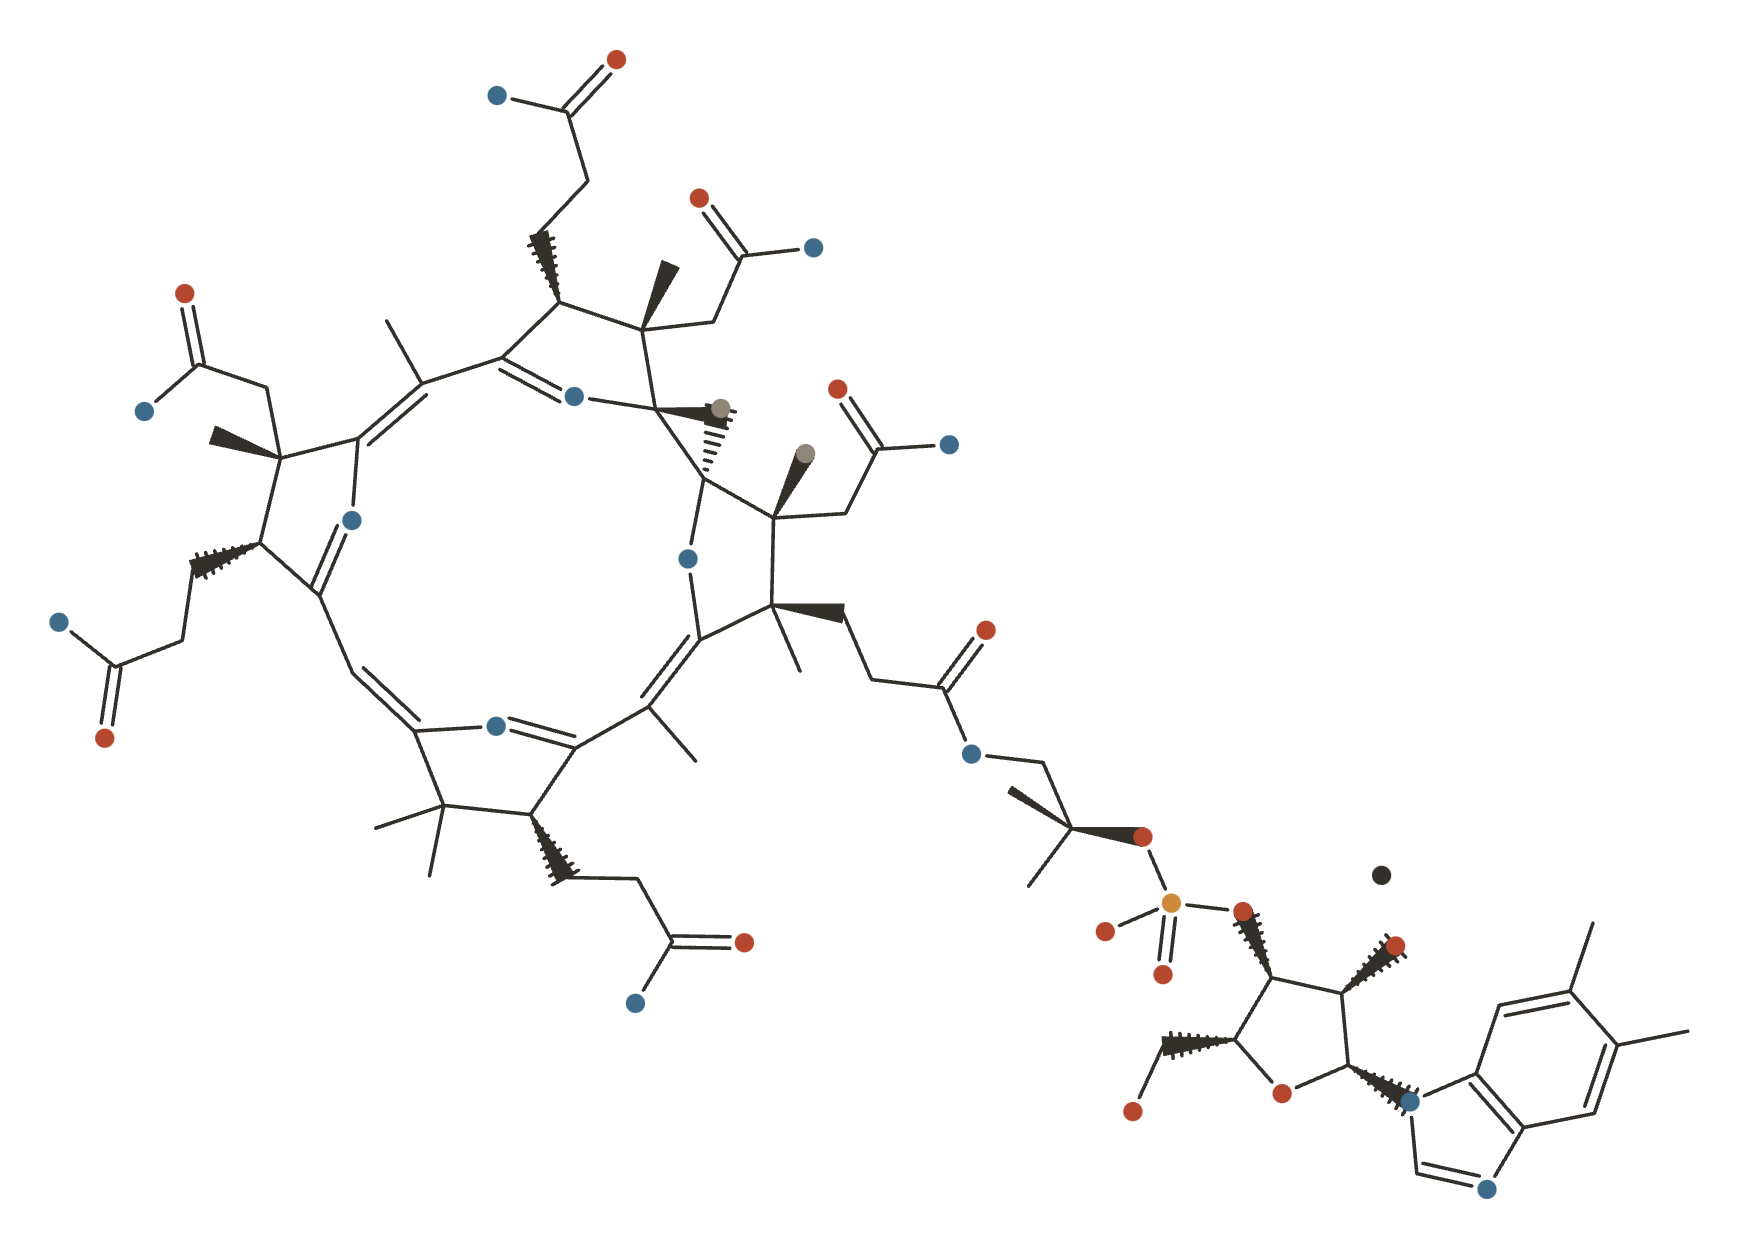
Vitamin B12
Cobalamin — the cobalt-containing B vitamin needed for red-blood-cell formation, DNA synthesis and the upkeep of the nervous system; found almost only in animal foods.

Vitamin B12 at a Glance
Vitamin B12 (cobalamin) is a cobalt-containing vitamin made by bacteria rather than by plants or animals, which is why it reaches us almost entirely through animal foods.
Its distinctive feature is the machinery required to absorb it: intrinsic factor, a protein made by the stomach, plus a dedicated receptor in the terminal ileum. That makes B12 status as much a question of absorption as of intake, and it is why deficiency shows up with age, after gastric surgery, and on long-term metformin or acid-suppressing drugs.
What It’s Used For
- Correcting deficiency & pernicious anemia — its core use, restoring red-cell production and energy.
- Deficiency-related neuropathy — repairs the nerve damage deficiency causes.
- Cognitive decline in high-homocysteine MCI — used where homocysteine is raised and cognition is declining.
- Depression (adjunct, long-term) — a long-term adjunct for mood.
How It Works
B12 is a cofactor for exactly two human enzymes. Methionine synthase converts homocysteine to methionine, feeding the methylation cycle that builds DNA and myelin — which is why deficiency produces both anemia and nerve damage. Methylmalonyl-CoA mutase handles branched-chain fats; when it stalls, methylmalonic acid accumulates, and that is the most specific marker of true deficiency.
Because normal absorption is receptor-limited, high-dose oral B12 works even in pernicious anemia — roughly 1% crosses by passive diffusion, which at 1,000 µg is enough.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Vitamin B12 (cobalamin) is a water-soluble, cobalt-containing B vitamin that acts as an obligatory cofactor for two enzymes — methionine synthase and methylmalonyl-CoA mutase — and its clinical story is overwhelmingly a story of deficiency correction, not of extra benefit layered on top of an adequate diet. Where a person is genuinely low (vegans, older adults with atrophic gastritis, people on metformin or with pernicious anemia), repletion is one of the more reliably effective interventions in nutrition, and — importantly — high-dose oral B12 works about as well as injections for most people 1,
Where a person is already replete, the evidence for the popular uses — energy, mood, general cognition — is thin to null 11Reference 11Meta-analysisEffects of vitamin B12 supplementation on cognitive function, depressive symptoms and fatigue: systematic review, meta-analysis and meta-regression — [meta-analysis]View study →.
Form matters less than marketing suggests: cyanocobalamin, methylcobalamin, hydroxocobalamin and adenosylcobalamin are largely interchangeable vitamers once absorbed, and fractional absorption is capped by intrinsic factor (~1.5–2 mcg per dose), which is precisely why corrective regimens use hundreds to thousands of micrograms.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is B12’s core, best-evidenced use. A Cochrane review of RCTs found that oral B12 (1,000–2,000 mcg/day) normalizes serum B12 as well as intramuscular injection, at lower cost — overturning the long-held belief that deficiency must be treated by injection 1Reference 1Systematic reviewOral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency — [Cochrane systematic review]View study →.
High-dose oral therapy works even in pernicious anemia (where intrinsic factor is absent) because ~1% of a large dose is absorbed by passive diffusion, independent of intrinsic factor — a fact clinicians were historically slow to adopt 2Reference 2ReviewOral cobalamin for pernicious anemia: back from the verge of extinction — [clinical review]View study →.
Even physiological oral doses (2 mcg/day) corrected anemia, lowered homocysteine and improved nerve conduction in deficient adolescents over 11 months 3Reference 3A physiological dose of oral vitamin B-12 improves haematological, biochemical and nerve-function indices — [intervention trial]View study →.
Form (cyano- vs methylcobalamin) does not change this outcome.
Gap: Trials are small and short (3–4 months); they confirm biochemical and hematological correction, but few report patient-centered symptom or quality-of-life outcomes head-to-head 1Reference 1Systematic reviewOral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency — [Cochrane systematic review]View study →.
The VITACOG trial (266 older adults with mild cognitive impairment) gave a B-vitamin combination (folic acid 0.8 mg, B12 0.5 mg, B6 20 mg) for 2 years. It lowered homocysteine ~30%, slowed whole-brain atrophy, and — in the pre-specified subgroup with baseline homocysteine above the median — stabilized executive function, global cognition and memory 7,
A follow-on imaging analysis reported up to a seven-fold reduction in atrophy of Alzheimer-vulnerable gray-matter regions, confined to the high-homocysteine participants 9Reference 9RCTPreventing Alzheimer’s disease-related gray matter atrophy by B-vitamin treatment — [RCT, imaging]View study →.
But this is one center’s combination-therapy result, and it does not generalize: a meta-analysis of 11 trials in 22,000 people found homocysteine lowering had no effect on cognitive aging (z-score difference 0.00), and a B12-specific meta-analysis found no cognitive benefit in people without deficiency 10,
A larger synthesis (95 studies) reported a small MMSE benefit from B vitamins overall but found that lower folate — not B12 or B6 — drove the association with dementia risk, reinforcing that any cognitive effect here is folate-led, not a B12 story 15Reference 15Meta-analysisB vitamins and prevention of cognitive decline and incident dementia: a systematic review and meta-analysis — [meta-analysis]View study →.
Gap: The effect is a combination (folate-led) effect seen only in elevated-homocysteine MCI, not a general B12 cognitive benefit; the positive trial’s senior authors hold patents on B-vitamin treatment of cognitive impairment, and independent replication at scale is still lacking 9,
A meta-analysis of RCTs of folate and/or B12 for depression found no reduction in depressive symptoms over days to weeks when added to antidepressants (standardized mean difference −0.12, 95% CI −0.45 to 0.22), but longer treatment (weeks to years) may reduce relapse (OR 0.33) and the onset of clinically significant symptoms in at-risk people (RR 0.65) 12Reference 12Meta-analysisSystematic review and meta-analysis of RCTs of folate and vitamin B12 for depression — [meta-analysis]View study →. A B12-specific meta-analysis likewise found no overall antidepressant effect in people without deficiency 11Reference 11Meta-analysisEffects of vitamin B12 supplementation on cognitive function, depressive symptoms and fatigue: systematic review, meta-analysis and meta-regression — [meta-analysis]View study →.
Gap: Trials are few, small and heterogeneous, almost always test B12 with folate rather than alone, and the only positive signals are for long-term relapse prevention in selected populations — not acute treatment 11,
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Methionine synthase (cytosol) | Cofactor; remethylates homocysteine → methionine (with 5-MTHF folate) | Homocysteine lowering; DNA methylation; folate “trap” when B12 low |
| Methylmalonyl-CoA mutase (mitochondria) | Cofactor; converts methylmalonyl-CoA → succinyl-CoA | Fatty-acid/amino-acid catabolism; MMA rises when B12 low (deficiency marker) |
| Myelin maintenance | Downstream of the two enzyme roles | Neuropathy; subacute combined degeneration |
| Erythropoiesis / DNA synthesis | Thymidylate supply via folate cycle | Megaloblastic anemia in deficiency |
Pharmacokinetics
Dietary B12 is released from food protein by gastric acid/pepsin, bound to intrinsic factor (secreted by gastric parietal cells) and absorbed in the terminal ileum. This receptor-mediated route is saturable at ~1.5–2 mcg per meal, so absorption efficiency falls sharply as dose rises — a single large dose is mostly wasted through that channel. However, roughly 1% of any oral dose is absorbed by passive diffusion independent of intrinsic factor, which is why 1,000–2,000 mcg/day oral tablets can treat pernicious anemia despite the absence of intrinsic factor 1,
Clinical trials
B12 is off-patent and cheap, so most modern trial activity is combination B-vitamin work (cardiovascular, cognitive) or deficiency-repletion and neuropathy studies out of Asia and Europe rather than industry-driven programs; registered activity continues, principally in diabetic neuropathy and cognitive aging.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~40+(repletion, neuropathy, homocysteine/cognition) | Several(DPN, cognitive aging) | Few | ~100s (mechanistic) |
Last checked: July 2026.
Dietary Sources
Vitamin B12 is synthesized only by microorganisms; it enters the human diet almost exclusively through animal foods, where it has accumulated up the food chain. Plant foods contain essentially none — so people avoiding animal products depend on fortified foods (some breakfast cereals, nutritional yeast) or supplements. Absorption from food is limited by intrinsic factor to roughly 1.5–2 mcg per meal regardless of how much the food contains, and up to 10–30% of older adults cannot liberate B12 from food protein efficiently (food-cobalamin malabsorption) even while absorbing the crystalline form in supplements and fortified foods normally.
| Food (typical serving) | Approx. B12 | Notes |
|---|---|---|
| Clams (3 oz) | ~84 mcg | Richest common source |
| Beef liver (3 oz) | ~70 mcg | Very high |
| Trout / salmon (3 oz) | ~3–5 mcg | Also omega-3s |
| Tuna, beef (3 oz) | ~2.5 mcg | — |
| Milk / yoghurt (1 cup) | ~1.2–1.4 mcg | Well absorbed |
| Egg (1 large) | ~0.5 mcg | Lower bioavailability |
| Fortified cereal / nutritional yeast | ~0.6–6 mcg | The reliable plant-based route (crystalline B12) |
Amounts per the NIH Office of Dietary Supplements Vitamin B12 fact sheet. The main dietary risk factor is simply avoiding animal foods without fortification.
Dosage & Intake
- RDA (adults): 2.4 mcg/day; pregnancy 2.6 mcg; lactation 2.8 mcg (IOM Dietary Reference Intakes).
- Upper limit: None established. B12 has very low toxicity and no UL — but “no UL” reflects lack of observed harm, not evidence that any dose is beneficial.
- Correcting deficiency: oral 1,000–2,000 mcg/day normalizes status as effectively as intramuscular injection for most people, including many with pernicious anemia, because ~1% is absorbed passively 1,
2Reference 1Systematic reviewOral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency — [Cochrane systematic review]View study →Reference 2ReviewOral cobalamin for pernicious anemia: back from the verge of extinction — [clinical review]View study → . Injections (hydroxocobalamin, 1,000 mcg) remain standard where malabsorption is severe or neurological signs are present. - Form: cyanocobalamin (most stable/cheapest), methylcobalamin, hydroxocobalamin and adenosylcobalamin are effectively interchangeable vitamers once absorbed — the body interconverts them. No convincing trial shows a clinically meaningful advantage of “active” methylcobalamin over cyanocobalamin for correcting deficiency, though cyanocobalamin is theoretically avoided in rare hereditary optic neuropathy and severe renal impairment.
- Because it is not a weight-based mineral, “elemental” adjustments do not apply — B12 is dosed directly in micrograms.
These are doses studied in research, not a personal recommendation.
Safety
Vitamin B12 is among the safest vitamins — the body excretes what it cannot store and no upper limit has been set. The real issues are interpretive and interactional, not toxic: several common drugs deplete it, and a high serum level in someone not supplementing is a signal to investigate, not to relax.
- Very low toxicity, no Tolerable Upper Intake Level. Corrective doses of hundreds to a thousand-plus micrograms are used freely.
- Recommended in pregnancy and lactation. Needs rise modestly and routine supplemental doses are considered safe — see the box below.
- Several drugs deplete B12. Metformin, proton-pump inhibitors and H2 blockers reduce absorption over the long term; nitrous oxide can precipitate acute deficiency.
- High-dose folic acid can mask B12 deficiency. The anemia resolves while neurological damage progresses — check B12 before treating with folate.
- An elevated serum B12 without supplementation warrants investigation. It can mark underlying liver or hematological disease.
- Avoid cyanocobalamin with hereditary Leber optic neuropathy. And do not switch from injections to oral without monitoring if neurological signs are present.
Full Safety & Interactions Detail
Vitamin B12 is among the safest vitamins: the body excretes what it cannot store, and no Tolerable Upper Intake Level has been established, so corrective doses of hundreds to a thousand-plus micrograms are used freely 1Reference 1Systematic reviewOral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency — [Cochrane systematic review]View study →.
Reported adverse effects are uncommon and mild — occasional acneiform or rosacea-like skin eruptions with high-dose supplementation. A more important clinical caveat is interpretive: an elevated serum B12 in someone not supplementing can be a marker of underlying liver or hematological disease and warrants investigation rather than reassurance.
Interactions (drug classes checked): Metformin lowers B12 absorption with long-term use (screen/supplement diabetics). Proton-pump inhibitors and H2 blockers reduce acid-dependent release of food B12 over years. Nitrous oxide irreversibly inactivates B12 and can precipitate acute deficiency in those with marginal stores. High-dose folic acid can mask the anemia of B12 deficiency while neurological damage progresses — a longstanding reason to check B12 before treating with folate.
Who should be cautious: people relying on injections due to malabsorption should not switch to oral without monitoring if neurological signs are present; those with hereditary Leber optic neuropathy should avoid cyanocobalamin.
Scope of this safety review (for honesty, not a claim):
- Interactions assessed? Yes — metformin, acid-suppressing drugs (PPIs/H2 blockers), nitrous oxide, and folic-acid masking were reviewed.
- Pregnancy/lactation assessed? Yes — increased need in pregnancy/lactation and infant risk from maternal deficiency.
- Upper Limit? No UL set by the IOM. This reflects low observed toxicity, not evidence that megadoses are beneficial — do not infer that unlimited intake is useful or risk-free.
Verdict: recommended at RDA levels; supplementation is important for those at risk. B12 needs rise modestly in pregnancy (2.6 mcg) and lactation (2.8 mcg), and maternal deficiency — particularly in vegan or vegetarian mothers — can cause serious neurological harm in exclusively breastfed infants. Routine supplemental doses are considered safe; there is no evidence of harm from typical prenatal amounts.
References
- Wang, H., Li, L., Qin, L. L., Song, Y., Vidal-Alaball, J., & Liu, T. H. (2018). Oral vitamin B12 versus intramuscular vitamin B12 for vitamin B12 deficiency — [Cochrane systematic review]. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/29543316/
- Lederle, F. A. (1998). Oral cobalamin for pernicious anemia: back from the verge of extinction — [clinical review]. Journal of the American Geriatrics Society. https://pubmed.ncbi.nlm.nih.gov/9736106/
- Yajnik, C. S., Behere, R. V., Bhat, D. S., et al. (2019). A physiological dose of oral vitamin B-12 improves haematological, biochemical and nerve-function indices — [intervention trial]. PLoS One. https://pubmed.ncbi.nlm.nih.gov/31600243/
- Didangelos, T., Karlafti, E., Kotzakioulafi, E., et al. (2021). Vitamin B12 supplementation in diabetic neuropathy: a 1-year, randomized, double-blind, placebo-controlled trial — [RCT]. Nutrients. https://pubmed.ncbi.nlm.nih.gov/33513879/
- Sawangjit, R., Thongphui, S., Chaichompu, W., & Phumart, P. (2020). Efficacy and safety of mecobalamin on peripheral neuropathy: systematic review and meta-analysis of RCTs — [meta-analysis]. Journal of Alternative and Complementary Medicine. https://pubmed.ncbi.nlm.nih.gov/32716261/
- Mansour, A., Amrollahi Bioky, A., Gerami, H., et al. (2026). Oral vitamin B-12 1000 μg vs 2000 μg on neuropathic outcomes in diabetic peripheral neuropathy — [RCT]. Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/41548600/
- Smith, A. D., Smith, S. M., de Jager, C. A., et al. (2010). Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment (VITACOG) — [RCT]. PLoS One. https://pubmed.ncbi.nlm.nih.gov/20838622/
- de Jager, C. A., Oulhaj, A., Jacoby, R., Refsum, H., & Smith, A. D. (2012). Cognitive and clinical outcomes of homocysteine-lowering B-vitamin treatment in mild cognitive impairment — [RCT]. International Journal of Geriatric Psychiatry. https://pubmed.ncbi.nlm.nih.gov/21780182/
- Douaud, G., Refsum, H., de Jager, C. A., et al. (2013). Preventing Alzheimer’s disease-related gray matter atrophy by B-vitamin treatment — [RCT, imaging]. Proceedings of the National Academy of Sciences. https://pubmed.ncbi.nlm.nih.gov/23690582/
- Clarke, R., Bennett, D., Parish, S., et al.; B-Vitamin Treatment Trialists’ Collaboration. (2014). Effects of homocysteine lowering with B vitamins on cognitive aging: meta-analysis of 11 trials, 22,000 individuals — [meta-analysis]. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/24965307/
- Markun, S., Gravestock, I., Jäger, L., et al. (2021). Effects of vitamin B12 supplementation on cognitive function, depressive symptoms and fatigue: systematic review, meta-analysis and meta-regression — [meta-analysis]. Nutrients. https://pubmed.ncbi.nlm.nih.gov/33809274/
- Almeida, O. P., Ford, A. H., & Flicker, L. (2015). Systematic review and meta-analysis of RCTs of folate and vitamin B12 for depression — [meta-analysis]. International Psychogeriatrics. https://pubmed.ncbi.nlm.nih.gov/25644193/
- Homocysteine Lowering Trialists’ Collaboration. (1998). Lowering blood homocysteine with folic acid based supplements: meta-analysis of randomised trials — [meta-analysis]. BMJ. https://pubmed.ncbi.nlm.nih.gov/9569395/
- Clarke, R., Halsey, J., Lewington, S., et al.; B-Vitamin Treatment Trialists’ Collaboration. (2010). Effects of lowering homocysteine levels with B vitamins on cardiovascular disease, cancer and cause-specific mortality: meta-analysis of 8 trials, 37,485 individuals — [meta-analysis]. Archives of Internal Medicine. https://pubmed.ncbi.nlm.nih.gov/20937919/
- Wang, Z., Zhu, W., Xing, Y., Jia, J., & Tang, Y. (2022). B vitamins and prevention of cognitive decline and incident dementia: a systematic review and meta-analysis — [meta-analysis]. Nutrition Reviews. https://pubmed.ncbi.nlm.nih.gov/34432056/
- Zhao, M., Wu, G., Li, Y., et al. (2017). Meta-analysis of folic acid efficacy trials in stroke prevention: insight into effect modifiers — [meta-analysis]. Neurology. https://pubmed.ncbi.nlm.nih.gov/28404799/



