

Sources · 5
Where Does It Come From?

Concentration
Content by Source
Reported concentrations across the plants that contain vitamin B6 — the bar marks the typical level, the line shows the reported range.
Literature figures for varying plant parts and preparations. Read them as a comparative guide, not exact assays.
Vitamin B6 at a Glance
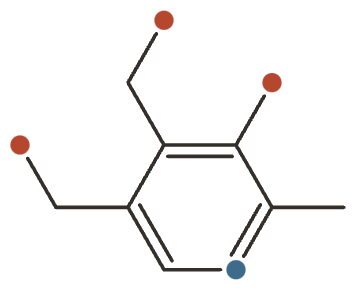
Vitamin B6 is a group of related compounds — pyridoxine, pyridoxal and pyridoxamine — that the body converts into the active coenzyme pyridoxal 5’-phosphate (P5P). It is found in fish, poultry, potatoes and chickpeas.
P5P is the workhorse coenzyme of amino-acid chemistry, involved in well over a hundred enzyme reactions. That includes the synthesis of serotonin, dopamine and GABA, which is why B6 turns up in formulas aimed at mood, sleep and premenstrual symptoms.
What It’s Used For
- Nausea & vomiting of pregnancy — a first-line treatment for morning sickness, often combined with doxylamine.
- Deficiency & drug-induced neuropathy — corrects deficiency, including the neuropathy caused by isoniazid and similar drugs.
- Premenstrual syndrome — eases premenstrual symptoms.
- Homocysteine lowering (biomarker) — lowers homocysteine alongside folate and B12.
- Kidney-stone prevention — reduces oxalate stone formation.
- Cognitive decline in MCI — studied with the other B vitamins in mild cognitive impairment.
How It Works
P5P works by forming a temporary bond with amino acids, which loosens their chemistry enough for enzymes to rearrange them. That single trick underlies transamination, decarboxylation and deamination — so P5P is required to build the neurotransmitters serotonin, dopamine, GABA and noradrenaline, to make haem, and to convert homocysteine down the transsulphuration pathway.
The kidney-stone effect comes from a different branch: B6 is a cofactor for the enzyme that diverts glyoxylate away from becoming oxalate. Because B6 is water-soluble, excess is normally excreted — though it is the one B vitamin with a meaningful upper limit, since very high long-term intakes cause a sensory neuropathy.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Vitamin B6 is a water-soluble vitamin — a family of six interconvertible vitamers (pyridoxine, pyridoxal, pyridoxamine and their 5’-phosphates) whose active coenzyme, pyridoxal 5’-phosphate (PLP), is a cofactor for well over a hundred enzymes, most of them in amino-acid metabolism. Because of that central metabolic role, B6 shows a sharp split between correcting a deficiency — where the effects are real and sometimes dramatic (sideroblastic anemia, isoniazid neuropathy prophylaxis, inborn errors like pyridoxine-responsive seizures and primary hyperoxaluria) — and taking extra on top of an already-adequate intake, where the evidence for most marketed benefits is thin or null. The best-replicated efficacy signal in replete people is symptomatic relief of nausea and vomiting of pregnancy. Form rarely matters much for correcting status: pyridoxine hydrochloride is cheap, well absorbed and converts efficiently to PLP, and the pre-phosphorylated “P5P” sold at a premium has no demonstrated advantage for the general user (it is dephosphorylated in the gut before absorption anyway). The decision-relevant caveat is on the safety side, not the efficacy side — chronic supra-gram or sustained triple-digit dosing causes a peripheral sensory neuropathy, which is the basis for the upper limit.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Pyridoxine is one of the best-evidenced uses of supplemental B6 and is a first-line option in obstetric guidelines. A double-blind, placebo-controlled RCT (n=342) found 25 mg pyridoxine every 8 h significantly reduced severe nausea versus placebo, though it had less effect on vomiting 1Reference 1RCTPyridoxine for nausea and vomiting of pregnancy: a randomized, double-blind, placebo-controlled trial — [RCT]View study →.
The Cochrane review of interventions for nausea and vomiting in early pregnancy concluded that pyridoxine (often paired with the antihistamine doxylamine) improves symptoms, while noting the overall evidence quality across agents is limited 2Reference 2Meta-analysisInterventions for nausea and vomiting in early pregnancy — [systematic review / meta-analysis]View study →.
Effect is symptomatic, seen in non-deficient women, and typically dosed 10–25 mg two-to-three times daily.
Gap: benefit is clearer for nausea than for vomiting, and the trial base, while positive, is modest in size and heterogeneity is high.
This is where B6 does its most decisive work — but only when status is low or a drug is depleting it. Pyridoxine-responsive sideroblastic anemia (often the X-linked ALAS2 form) can respond strikingly to pharmacologic pyridoxine, restoring hemoglobin synthesis 12,
Pyridoxine given alongside isoniazid prevents the peripheral neuropathy the drug otherwise causes by depleting B6 — established since the 1950s and now standard of care 14Reference 14Clinical trialProphylaxis of isoniazid neuropathy with pyridoxine — [clinical study]View study →.
High-dose pyridoxine is also the mainstay for the AGXT B6-responsive subtype of primary hyperoxaluria type 1, reducing oxalate overproduction. These are repletion or pharmacologic effects, not general-population benefits.
Gap: every one of these is deficiency- or disease-dependent; none implies benefit from extra B6 in a replete person.
B6, as PLP, is the cofactor for the transsulfuration arm that clears homocysteine, and B-vitamin regimens containing B6 reliably lower plasma homocysteine 3Reference 3ReviewHomocysteine, B-vitamins and CVD — [review]View study →. The problem is that this well-mapped biomarker effect does not translate to clinical benefit: large meta-analyses of homocysteine-lowering trials (tens of thousands of participants) show no reduction in cardiovascular events, myocardial infarction, or cardiovascular mortality 4,
Gap: this is a textbook biomarker-outcome disconnect — B6 moves the number, but lowering homocysteine with B vitamins has not prevented cardiovascular disease.
The VITACOG RCT gave high-dose B vitamins (including 20 mg B6) to older adults with mild cognitive impairment and reported slower brain atrophy on MRI, with the effect concentrated in participants with elevated baseline homocysteine 6Reference 6RCTHomocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment (VITACOG) — [RCT]View study →.
A follow-up analysis suggested the benefit was larger in those with good omega-3 status 7Reference 7RCTOmega-3 fatty acid status enhances the prevention of cognitive decline by B vitamins in mild cognitive impairment — [RCT, secondary analysis]View study →.
The signal is biologically coherent but rests on subgroup analyses from essentially one trial program and has not been convincingly replicated for hard cognitive endpoints.
Gap: subgroup-dependent (high-homocysteine only), single-program, and unreplicated for clinical dementia outcomes — promising, not established.
A BMJ systematic review of vitamin B6 for PMS pooled nine trials and found it “likely to be of benefit” for overall symptoms and depression, but explicitly cautioned that the included trials were of low methodological quality and the conclusion could not be robustly drawn 5Reference 5Systematic reviewEfficacy of vitamin B-6 in the treatment of premenstrual syndrome: systematic review — [systematic review]View study →. No high-quality modern RCT has settled the question.
Gap: the evidence is a synthesis of small, low-quality, older trials — a weak foundation for a widely marketed claim.
In the Nurses’ Health Study, higher vitamin B6 intake was associated with a modestly lower risk of incident kidney stones in women 16Reference 16ObservationalIntake of vitamins B6 and C and the risk of kidney stones in women — [prospective cohort]View study →; but the parallel analysis in men (Health Professionals Follow-up Study) found no such association 17Reference 17ObservationalDietary factors and the risk of incident kidney stones in men — [prospective cohort]View study →, and a later cohort analysis was likewise unconvincing. The rationale is that PLP is a cofactor in glyoxylate→glycine conversion, reducing oxalate production.
Gap: the association is sex-discordant (women only), observational, and not tested in a preventive RCT — mechanistically plausible but far from actionable.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Aromatic amino-acid decarboxylase (PLP cofactor) | Synthesis of serotonin, dopamine, GABA | MoodnauseaPMS claims |
| Transaminases (AST/ALT), amino-acid transamination | Enables amino-acid interconversion | Core metabolic role>140 PLP enzymes |
| Cystathionine β-synthase / γ-lyase (transsulfuration) | Clears homocysteine → cysteine | Homocysteine loweringCVD hypothesis |
| δ-aminolevulinate synthase (ALAS2, PLP-dependent) | Hem/hemoglobin synthesis | Sideroblastic anemia |
| Alanine-glyoxylate aminotransferase (AGXT) | Glyoxylate → glycine, less oxalate | Hyperoxaluriakidney stones |
| Glycogen phosphorylase (PLP structural) | Glycogen breakdown | Energy metabolism (large B6 reservoir in muscle) |
Pharmacokinetics
Dietary and supplemental B6 forms are dephosphorylated in the gut lumen, absorbed by passive diffusion in the jejunum, then re-phosphorylated and trapped in tissues — chiefly muscle, bound to glycogen phosphorylase, which holds the body’s largest B6 pool. Circulating PLP is the usual status marker. Because absorption is non-saturable and passive, oral bioavailability is high across forms, and the pre-phosphorylated “P5P” supplement confers no absorption advantage since it, too, must be dephosphorylated before uptake. B6 is water-soluble with limited storage beyond the muscle pool, so intake matters ongoing; excess is renally cleared as 4-pyridoxic acid. The neurotoxicity of chronic megadosing reflects accumulation of unphosphorylated pyridoxine reaching the dorsal root ganglia rather than a simple half-life effect.
Clinical trials
B6 is an off-patent, inexpensive nutrient, so there is little commercial trial activity; most rigorous data come from investigator- or government-funded studies (Cochrane, homocysteine trials, VITACOG). Registered-trial activity today centers on combination B-vitamin regimens and pregnancy nausea rather than B6 alone.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~40+(mostly combination/B-complex) | Few(B6-specific) | Few | ~hundreds(enzymology) |
Last checked: July 2026.
Dietary Sources
Vitamin B6 is widely distributed in the food supply, so frank dietary deficiency is uncommon in people eating a varied diet; it appears more often secondary to alcohol use, renal disease, or drugs that antagonize B6 (isoniazid, certain anticonvulsants). The richest, most bioavailable sources are animal foods and starchy vegetables. B6 in plant foods is partly present as pyridoxine glucoside, which is less bioavailable than the forms in animal foods, and the vitamin is degraded by heat, light and food processing — refining grains removes much of the B6, which is why some cereals and flours are fortified. Fractional absorption is high because uptake is passive and non-saturable.
| Food | Typical B6 per serving |
|---|---|
| Chickpeas, canned (1 cup) | ~1.1 mg |
| Beef liver (3 oz) | ~0.9 mg |
| Tuna / salmon (3 oz) | ~0.6–0.9 mg |
| Chicken breast (3 oz) | ~0.5 mg |
| Potato, baked (1 medium) | ~0.4 mg |
| Banana (1 medium) | ~0.4 mg |
| Fortified breakfast cereal (1 serving) | ~0.5–2.0 mg |
Amounts adapted from the NIH Office of Dietary Supplements Vitamin B6 fact sheet. A single cup of chickpeas or a serving of fish or poultry supplies most or all of an adult’s daily requirement.
Dosage & Intake
RDA (adults 19–50): 1.3 mg/day. Older adults: 1.5 mg/day (women 51+), 1.7 mg/day (men 51+). Pregnancy/lactation: 1.9–2.0 mg/day.
Tolerable Upper Intake Level (UL): the US Institute of Medicine sets 100 mg/day for adults, applying to supplemental B6 (food B6 is not implicated). Note that EFSA (2023) revised its adult UL down to 12 mg/day, a large divergence worth flagging — the difference reflects how conservatively each body read the sensory-neuropathy dose-response data.
Studied supplemental ranges (doses used in research, not a personal recommendation):
- Nausea/vomiting of pregnancy: 10–25 mg two-to-three times daily (30–75 mg/day).
- Homocysteine-lowering regimens: typically 10–25 mg/day B6 combined with folate and B12.
- VITACOG cognitive trial: 20 mg/day B6 (with 0.8 mg folate, 0.5 mg B12).
- Pharmacologic/inborn-error use (sideroblastic anemia, primary hyperoxaluria): much higher, physician-supervised doses — outside general-supplement territory and carrying real neuropathy risk.
Form note: pyridoxine hydrochloride is the standard, well-absorbed, inexpensive form. The pre-phosphorylated “P5P/pyridoxal 5’-phosphate” supplement is marketed as superior but is dephosphorylated in the gut before absorption like any other form, so it has no demonstrated bioavailability or efficacy advantage for the general user.
Safety
B6 from food carries no established risk — the concern is entirely supplemental. Chronic high-dose pyridoxine causes a peripheral sensory neuropathy, which is the sole basis for the upper limit and the reason “more is better” is actively wrong for this vitamin.
- Food B6 carries no established risk. RDA-level intake is safe, and the RDA rises only slightly in pregnancy and lactation.
- Chronic high doses cause sensory peripheral neuropathy. Numbness, tingling, ataxia and impaired proprioception — usually reversible, but recovery can be slow and incomplete.
- The two upper limits diverge sharply. The US sets 100 mg/day, EFSA 12 mg/day; both apply to supplemental B6, not food.
- Stacked B-complex products add up. Easy to exceed the limit when a separate B6 supplement sits on top of a multivitamin.
- Reduces the effect of unprotected levodopa. B6 accelerates its peripheral decarboxylation; modern carbidopa/levodopa formulations blunt this.
- Epidemiological lung-cancer signal in men. Long-term high-dose use in one cohort — associational, not proven causal.
Full Safety & Interactions Detail
Vitamin B6 from food carries no established risk. The concern is supplemental: chronic intake above the upper limit — the classic case reports and reviews describe sustained doses in the hundreds to thousands of mg/day, but the effect is now recognized at lower chronic intakes in susceptible people — can cause a dose- and duration-dependent peripheral sensory neuropathy (numbness, tingling, ataxia, impaired proprioception), first characterized by Schaumburg’s 1983 megavitamin-syndrome case series 10,
It is usually reversible on stopping, but recovery can be slow and incomplete. This neurotoxicity is the sole basis for the UL, and it is why “more is better” is actively wrong for B6.
Interactions (drug classes assessed):
- Levodopa (without carbidopa): B6 accelerates peripheral decarboxylation of levodopa, reducing CNS availability — clinically relevant for unprotected levodopa (modern carbidopa/levodopa formulations blunt this).
- Isoniazid, cycloserine, hydralazine, penicillamine: these antagonize or deplete B6; pyridoxine is co-prescribed with isoniazid to prevent neuropathy.
- Certain anticonvulsants (phenytoin, carbamazepine, valproate) and theophylline: can lower B6 status.
- Amiodarone: combining with high-dose B6 may increase photosensitivity.
Who should be cautious: anyone taking chronic high-dose B6 supplements or “B-complex” products stacked with separate B6, especially long-term; and people on unprotected levodopa. There is an epidemiological signal (VITAL cohort) linking long-term high-dose B6 (and B12) supplement use to increased lung-cancer risk in men 15Reference 15ObservationalLong-term, supplemental, one-carbon metabolism-related vitamin B use in relation to lung cancer risk (VITAL cohort) — [prospective cohort]View study → — associational, not proven causal, but another argument against routine megadosing.
Scope of this safety review (for honesty, not a claim):
- Interactions assessed? Yes — levodopa, isoniazid/antituberculars, anticonvulsants, penicillamine, amiodarone, theophylline reviewed above.
- Pregnancy/lactation assessed? Yes — low-dose pyridoxine is first-line for pregnancy nausea and the RDA increase is small.
- Upper Limit? Yes — 100 mg/day (US IOM); EFSA sets 12 mg/day. Both apply to supplemental B6, not food. Do not treat the absence of acute toxicity as license for unlimited chronic intake — the neuropathy is a chronic-exposure effect.
Verdict: safe and, for nausea, actively useful at low therapeutic doses. Pyridoxine 10–25 mg two-to-three times daily is a first-line, guideline-endorsed treatment for nausea and vomiting of pregnancy, and the RDA rises modestly (1.9 mg/day). Stay within therapeutic/UL limits — there is no reason to exceed them in pregnancy, and high-dose supplementation is not indicated.
References
- Vutyavanich, T., et al. (1995). Pyridoxine for nausea and vomiting of pregnancy: a randomized, double-blind, placebo-controlled trial — [RCT]. American Journal of Obstetrics and Gynecology. https://pubmed.ncbi.nlm.nih.gov/7573262/
- Matthews, A., et al. (2015). Interventions for nausea and vomiting in early pregnancy — [systematic review / meta-analysis]. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/26348534/
- McNulty, H., et al. (2008). Homocysteine, B-vitamins and CVD — [review]. Proceedings of the Nutrition Society. https://pubmed.ncbi.nlm.nih.gov/18412997/
- Martí-Carvajal, A. J., et al. (2017). Homocysteine-lowering interventions for preventing cardiovascular events — [Cochrane systematic review]. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/28816346/
- Wyatt, K. M., et al. (1999). Efficacy of vitamin B-6 in the treatment of premenstrual syndrome: systematic review — [systematic review]. BMJ. https://pubmed.ncbi.nlm.nih.gov/10334745/
- Smith, A. D., et al. (2010). Homocysteine-lowering by B vitamins slows the rate of accelerated brain atrophy in mild cognitive impairment (VITACOG) — [RCT]. PLoS One. https://pubmed.ncbi.nlm.nih.gov/20838622/
- Jernerén, F., et al. (2016). Omega-3 fatty acid status enhances the prevention of cognitive decline by B vitamins in mild cognitive impairment — [RCT, secondary analysis]. Journal of Alzheimer’s Disease. https://pubmed.ncbi.nlm.nih.gov/26757190/
- Clarke, R., et al. (2010). Effects of lowering homocysteine levels with B vitamins on cardiovascular disease, cancer, and cause-specific mortality — [meta-analysis]. Archives of Internal Medicine. https://pubmed.ncbi.nlm.nih.gov/20937919/
- Zhang, C., Chi, F. L., Xie, T. H., et al. (2013). Effect of B-vitamin supplementation on stroke: a meta-analysis of randomized controlled trials — [meta-analysis]. PLoS One. https://pubmed.ncbi.nlm.nih.gov/24282609/
- Schaumburg, H., et al. (1983). Sensory neuropathy from pyridoxine abuse: a new megavitamin syndrome — [case series]. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/6308447/
- Snodgrass, S. R. (1992). Vitamin neurotoxicity — [review]. Molecular Neurobiology. https://pubmed.ncbi.nlm.nih.gov/1463588/
- Harris, J. W., et al. (1994). X-linked, pyridoxine-responsive sideroblastic anemia — [editorial / review]. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/8107723/
- BOTTOMLEY, S. S. (1962). Pyridoxine-responsive anemia — [case report]. JAMA. https://pubmed.ncbi.nlm.nih.gov/13871708/
- Carlson, H. B., et al. (1956). Prophylaxis of isoniazid neuropathy with pyridoxine — [clinical study]. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/13334809/
- Brasky, T. M., et al. (2017). Long-term, supplemental, one-carbon metabolism-related vitamin B use in relation to lung cancer risk (VITAL cohort) — [prospective cohort]. Journal of Clinical Oncology. https://pubmed.ncbi.nlm.nih.gov/28829668/
- Curhan, G. C., et al. (1999). Intake of vitamins B6 and C and the risk of kidney stones in women — [prospective cohort]. Journal of the American Society of Nephrology. https://pubmed.ncbi.nlm.nih.gov/10203369/
- Taylor, E. N., et al. (2004). Dietary factors and the risk of incident kidney stones in men — [prospective cohort]. Journal of the American Society of Nephrology. https://pubmed.ncbi.nlm.nih.gov/15579526/



