
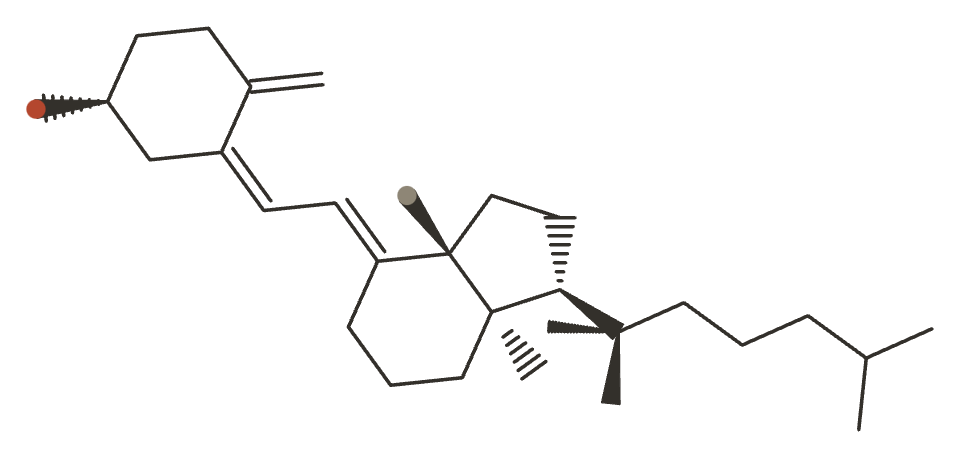

Vitamin D3 (Cholecalciferol) at a Glance
Vitamin D3 (cholecalciferol) is the form your skin makes from UVB sunlight, and the form found in oily fish and egg yolk.
Calling it a vitamin undersells it: once converted in the liver and kidney it acts as a hormone, with receptors in most tissues in the body. Its classical job is driving calcium absorption and building bone, and its reach beyond that — immunity, muscle, metabolism — is what makes it one of the most studied nutrients there is.
What It’s Used For
- Deficiency correction (rickets / osteomalacia / calcium absorption) — its core function: restoring calcium absorption and bone mineralisation.
- Fracture prevention (with calcium, in deficient older adults) — reduces fractures in deficient older adults, alongside calcium.
- Falls prevention — supports muscle function and balance in older adults.
- Respiratory infection prevention — reduces respiratory infections, most in those who were deficient.
- Autoimmune disease prevention — lowers autoimmune disease incidence in long-term trials.
- Type 2 diabetes prevention (in prediabetes) — studied in people with prediabetes.
- Mood / depression — used for low mood.
- Cancer / cardiovascular prevention — the focus of the largest prevention trials.
How It Works
D3 is a prohormone. The liver converts it to 25-hydroxyvitamin D — the form a blood test measures — and the kidney activates it to calcitriol, which binds the vitamin D receptor and directly regulates gene transcription. That receptor is present in immune cells, muscle and many other tissues, which is why its effects run well beyond bone.
It is fat-soluble, so it is absorbed better with a meal containing fat and is stored rather than cleared daily — which is why weekly dosing works as well as daily.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Vitamin D3 (cholecalciferol) is a fat-soluble secosteroid that acts as a pro-hormone: it is hydroxylated in the liver to 25-hydroxyvitamin D (25(OH)D, the status marker) and in the kidney to the active hormone calcitriol, which drives intestinal calcium and phosphate absorption through the vitamin D receptor. The evidence posture is unusually clean on the fundamentals and unusually disappointing on the extras: correcting genuine deficiency prevents rickets and osteomalacia and reliably improves calcium handling, but a decade of large randomized trials in replete populations has repeatedly failed to show benefit for fractures, cancer, cardiovascular disease, depression, or all-cause mortality. The single most important distinction here is therefore deficiency-correction (real, often dramatic) versus extra-on-top-of-adequacy (mostly null). The 2024 Endocrine Society guideline formalized this: it suggests empiric supplementation only for specific groups — children/adolescents, adults over 75, pregnancy, and high-risk prediabetes — and explicitly recommends against extra supplementation (and against routine 25(OH)D testing) in healthy adults under 75 20Reference 20Vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline — [clinical guideline]View study →.
Because supplements are dosed in IU of a stable, well-absorbed molecule, form and bioavailability are rarely the issue here — D3 is modestly more effective than D2 at raising 25(OH)D, and that is about the whole of the form story.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the core, non-negotiable role and the reason reference intakes exist. Vitamin D is required for active intestinal calcium and phosphate absorption; severe deficiency causes defective bone mineralization — rickets in children, osteomalacia in adults — which supplementation corrects. Reference bodies set an RDA of 15 mcg (600 IU)/day for adults to 70 and 20 mcg (800 IU)/day beyond 70 specifically to maintain bone health, and clinical guidelines define deficiency (commonly 25(OH)D < 30 nmol/L / 12 ng/mL) and its repletion 1,
The 2024 Endocrine Society guideline reaffirms empiric supplementation in children and adolescents (1–18 y) to prevent nutritional rickets 20Reference 20Vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline — [clinical guideline]View study →.
The benefit here is a repletion effect: it is large in the deficient and absent in the already-replete.
Gap: the effect is entirely deficiency-dependent — it says nothing about supplementing people who already have adequate status.
The best-evidenced “extra” benefit. A 2017 individual-participant-data meta-analysis of 25 RCTs (~11,000 participants) found vitamin D supplementation modestly reduced the risk of at least one acute respiratory infection, with the protective effect concentrated in those who were most deficient at baseline and who received daily or weekly (not large bolus) dosing 2Reference 2Meta-analysisVitamin D supplementation to prevent acute respiratory tract infections: systematic review and meta-analysis of individual participant data — [IPD meta-analysis]View study →.
A 2021 aggregate-data meta-analysis of 43 trials broadly reproduced a small protective effect while narrowing the effect size and again favoring regular, moderate dosing 10Reference 10Meta-analysisVitamin D supplementation to prevent acute respiratory infections: a systematic review and meta-analysis of aggregate data from RCTs — [meta-analysis]View study →.
For COVID-19 specifically the signal did not hold up: a randomized trial of a single 200,000 IU bolus in hospitalized moderate-to-severe patients showed no effect on length of stay or other outcomes 11Reference 11RCTEffect of a single high dose of vitamin D3 on hospital length of stay in patients with moderate-to-severe COVID-19 — [RCT, null]View study →.
The 2024 Endocrine Society guideline cites respiratory-infection reduction as part of its rationale for empiric supplementation in children/adolescents 20Reference 20Vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline — [clinical guideline]View study →.
Gap: absolute risk reductions are small, driven by deficient subgroups, and abolished by high intermittent bolus dosing — not a general “immune booster” for replete people.
Fracture data split cleanly by population and co-treatment. In generally healthy, replete midlife-and-older adults, the large VITAL trial (2,000 IU/day D3, ~25,000 people) found no reduction in total, non-vertebral, or hip fractures 3Reference 3RCTSupplemental vitamin D and incident fractures in midlife and older adults (VITAL) — [RCT]View study →.
Benefit appears only in the classic at-risk setting: pooled and meta-analytic data show vitamin D plus calcium reduces hip and total fractures in older, often institutionalized and vitamin-D-deficient adults, whereas vitamin D alone does not 5,
Consistent with a lack of skeletal benefit in the replete, a meta-analysis of bone mineral density found no clinically meaningful BMD improvement from vitamin D supplementation 4Reference 4Meta-analysisEffects of vitamin D supplements on bone mineral density: a systematic review and meta-analysis — [meta-analysis]View study →.
Gap: the benefit requires co-administered calcium and a deficient, high-risk population; vitamin D alone in replete adults does nothing for fractures or BMD.
A pre-specified ancillary of VITAL is the most encouraging “new” signal. Over ~5 years, 2,000 IU/day D3 (with or without omega-3) reduced incident confirmed autoimmune disease versus placebo, with the effect strengthening in later follow-up years 17Reference 17RCTVitamin D and marine omega-3 fatty acid supplementation and incident autoimmune disease (VITAL) — [RCT]View study →. The relative reduction (~22%) is meaningful but the absolute numbers are small, and this is a single trial in older adults.
Gap: one unreplicated RCT with a modest absolute effect; needs confirmation before it changes practice.
The clearest example of a trial and a meta-analysis reading differently. The purpose-built D2d trial randomized adults with prediabetes to 4,000 IU/day D3 or placebo and found no significant reduction in progression to type 2 diabetes on its primary endpoint 15Reference 15RCTVitamin D supplementation and prevention of type 2 diabetes (D2d) — [RCT, null]View study →.
However, a 2023 individual-participant-data meta-analysis pooling D2d with two other prediabetes trials found that vitamin D did reduce progression to diabetes in people with prediabetes (a modest but statistically significant relative reduction) 21Reference 21Meta-analysisVitamin D and risk for type 2 diabetes in people with prediabetes: a systematic review and meta-analysis of individual participant data — [IPD meta-analysis]View study →.
On that basis the 2024 Endocrine Society guideline suggests empiric supplementation specifically for adults with high-risk prediabetes 20Reference 20Vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline — [clinical guideline]View study →.
This is a genuine repletion-adjacent signal in a defined at-risk group — not a general metabolic benefit.
Gap: the effect is confined to high-risk prediabetes and is modest; the single dedicated RCT was null on its primary endpoint, and there is no benefit for metabolic health in the general replete population.
The most instructive reversal in the field. An influential 2009 meta-analysis found higher-dose daily vitamin D (700–1,000 IU) reduced falls in older adults 7Reference 7Meta-analysisFall prevention with supplemental and active forms of vitamin D: a meta-analysis of RCTs — [meta-analysis]View study →, and this fed guideline enthusiasm. Larger, better-designed modern data undercut it: VITAL found 2,000 IU/day did not reduce falls 9Reference 9RCTVITAL: effects of vitamin D supplements on risk of falls — [RCT]View study →, and — importantly — high intermittent dosing can cause harm, with a trial of monthly 60,000 IU increasing falls versus lower dosing 8Reference 8RCTMonthly high-dose vitamin D treatment for the prevention of functional decline — [RCT, harm signal]View study →.
The picture now is that daily physiological repletion in the deficient may modestly help, but bolus “megadosing” is counterproductive.
Gap: modern RCTs are null-to-harmful; any benefit is confined to daily repletion of deficient individuals, and high bolus doses increase falls.
Physiologically plausible, but the dedicated trial is null. VITAL-DEP randomized >18,000 adults to 2,000 IU/day D3 or placebo and found no effect on incident depression, recurrent depression, or mood scores over ~5 years 16Reference 16RCTEffect of long-term vitamin D3 supplementation vs placebo on risk of depression (VITAL-DEP) — [RCT, null]View study →. Trials in already-depressed or deficient populations are smaller and inconsistent.
Gap: the large prevention RCT in non-deficient adults is flatly null; there is no good evidence for supplementing replete people for mood.
Tested directly and negative for primary endpoints. VITAL found 2,000 IU/day D3 did not reduce the primary endpoints of invasive cancer incidence or major cardiovascular events over ~5 years 12Reference 12RCTVitamin D supplements and prevention of cancer and cardiovascular disease (VITAL) — [RCT]View study →.
A weak secondary signal for reduced cancer mortality (and in some analyses advanced/metastatic cancer) exists but is hypothesis-generating, not practice-changing. The D-Health trial likewise found no mortality benefit overall 13Reference 13RCTThe D-Health Trial: a randomised controlled trial of the effect of vitamin D on mortality — [RCT]View study → — though the 2024 Endocrine Society guideline, reading pooled data, suggests empiric supplementation in adults over 75 for its potential to lower mortality in that oldest group specifically 20Reference 20Vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline — [clinical guideline]View study →.
Gap: null for the primary cancer and CVD endpoints in a large RCT; the cancer-mortality and over-75 mortality hints are secondary/subgroup findings needing confirmation.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Vitamin D receptor (VDR), nuclear | Activated by calcitriol → transcription of calcium-transport genes | Calcium absorptionbone mineralization |
| Intestinal calcium/phosphate transport (TRPV6, calbindin) | Upregulated | Deficiency correctionbone |
| PTH–calcium axis | 25(OH)D repletion suppresses secondary hyperparathyroidism | Bone lossfracture risk |
| Immune cells (monocytes/macrophages, T cells) express VDR + 1α-hydroxylase | Modulates antimicrobial peptide (cathelicidin) and cytokine response | Respiratory infectionautoimmunity |
| Skeletal muscle VDR signaling | Supports muscle function (debated magnitude) | Fallsstrength |
Pharmacokinetics
Cholecalciferol is fat-soluble and absorbed in the small intestine with dietary fat, so taking it with a fat-containing meal improves absorption. It is stored in adipose tissue and has a long biological footprint: circulating 25(OH)D has a half-life of roughly 2–3 weeks, which is why daily and weekly dosing produce steadier status than large monthly/quarterly boluses. D3 raises and maintains serum 25(OH)D somewhat more effectively than D2 (ergocalciferol), the main practical difference between the two forms. Obesity lowers the 25(OH)D rise per dose (volumetric dilution into fat), so heavier individuals often need more — though the 2024 guideline found no evidence to support routine 25(OH)D testing even in people with obesity or dark skin 20Reference 20Vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline — [clinical guideline]View study →. Because it is stored rather than excreted, sustained intake well above the UL accumulates and underlies its toxicity potential — unlike water-soluble vitamins.
Clinical trials
Vitamin D is off-patent and cheap, yet — unusually — it has attracted very large publicly funded RCTs (VITAL, D-Health, D2d, VIDA, DO-HEALTH) precisely because observational hopes were so high; the resulting body of high-quality evidence is what has deflated most of the “extra-benefit” claims and grounds the cautious 2024 Endocrine Society guideline.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| 100+RCTs (several mega-trials >15,000 each) | Ongoing(dose-optimization, deficient subgroups) | Few | Extensive |
Last checked: July 2026.
Dietary Sources
Unusually among nutrients, most people’s vitamin D does not come from food — it is synthesized in skin on UVB exposure, and diet is a minor secondary source. Naturally rich foods are few: oily fish and, to a lesser extent, egg yolk, some mushrooms (D2), and liver. Because natural sources are so limited, many countries fortify staple foods (milk, plant milks, breakfast cereals, some spreads), which for many people is the main dietary contributor 1Reference 1ReviewVitamin D — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/VitaminD-HealthProfessional/View study →.
| Food (typical serving) | Approx. vitamin D |
|---|---|
| Cod liver oil (1 tbsp) | ~1,360 IU (34 mcg) |
| Trout / salmon (85 g, cooked) | ~570–645 IU (14–16 mcg) |
| Fortified milk / plant milk (1 cup) | ~100–120 IU (2.5–3 mcg) |
| Egg yolk (1 large) | ~44 IU (1.1 mcg) |
| UV-exposed mushrooms (½ cup) | ~46 IU (1.1 mcg; as D2) |
| Fortified breakfast cereal (1 serving) | ~40–80 IU (1–2 mcg) |
Values approximate, from NIH ODS 1Reference 1ReviewVitamin D — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/VitaminD-HealthProfessional/View study →. Sun exposure can supply far more than diet, but it varies with latitude, season, skin pigmentation, sunscreen, and age — which is why deficiency is common in winter and at high latitudes despite adequate diets. Supplemental D3 is manufactured by UV irradiation of 7-dehydrocholesterol from lanolin (sheep’s wool); vegan D3 is made from lichen.
Dosage & Intake
These are intakes and doses studied in research and set by reference bodies, not a personal recommendation. The RDA is 600 IU/day (15 mcg) for adults 19–70 and 800 IU/day (20 mcg) for adults over 70; the AI for infants is 400 IU/day (10 mcg) 1Reference 1ReviewVitamin D — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/VitaminD-HealthProfessional/View study →. NIH sets a Tolerable Upper Intake Level (UL) of 4,000 IU/day (100 mcg) for adults — this counts supplements and fortified food, not sun exposure, which is self-limiting 1Reference 1ReviewVitamin D — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/VitaminD-HealthProfessional/View study →.
The 2024 Endocrine Society guideline reframed who should take extra: it suggests empiric supplementation (above the DRI, without testing) only for children/adolescents (1–18 y), adults over 75, pregnancy, and high-risk prediabetes — and suggests against routine extra supplementation, and against routine 25(OH)D testing, in healthy adults under 75 20Reference 20Vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline — [clinical guideline]View study →. Deficiency repletion remains a separate clinical scenario: guidelines describe higher short-term loading (e.g. weekly dosing) to restore 25(OH)D, then a maintenance dose, ideally monitored by blood test 19Reference 19Evaluation, treatment, and prevention of vitamin D deficiency: an Endocrine Society clinical practice guideline — [clinical guideline]View study →.
- Form: D3 (cholecalciferol) raises and maintains serum 25(OH)D somewhat more effectively than D2 (ergocalciferol); for most purposes they are interchangeable but D3 is generally preferred.
- Timing: take with a fat-containing meal for best absorption. Daily or weekly dosing maintains steadier status than large monthly/quarterly boluses, and — importantly — bolus megadosing has caused harm (increased falls/fractures) in trials, so it is not a shortcut 8Reference 8RCTMonthly high-dose vitamin D treatment for the prevention of functional decline — [RCT, harm signal]View study →.
- Units: 1 mcg = 40 IU. Obesity increases requirements (the dose is diluted into fat), so heavier individuals may need more to reach the same 25(OH)D.
Safety
At recommended intakes vitamin D3 is very safe. Its distinctive risk comes from being fat-soluble and stored — sustained intake well above the upper limit accumulates and can cause hypercalcemia, which is what sets it apart from the water-soluble vitamins.
- Very safe at recommended intakes. One of the most widely used supplements in the world, with a 4,000 IU/day adult upper limit.
- Sustained megadosing causes hypercalcemia. Nausea, vomiting, weakness, frequent urination, kidney stones, and in severe cases kidney injury and calcification.
- High intermittent bolus dosing increased falls and fractures in randomized trials — more is not better.
- Exaggerated calcium responses in some conditions. Sarcoidosis and other granulomatous disease, primary hyperparathyroidism, lymphoma, and some kidney disease need medical supervision.
- Several drug interactions run through calcium. Thiazide diuretics add hypercalcemia risk, and raised calcium increases the risk of digoxin toxicity.
- Other drugs lower your status. Corticosteroids, orlistat and bile-acid sequestrants, anticonvulsants and some antiretrovirals.
Full Safety & Interactions Detail
At recommended intakes vitamin D3 is very safe, and this is one of the most widely used supplements in the world. Its distinctive risk comes from being fat-soluble and stored: unlike water-soluble vitamins, sustained intake well above the UL accumulates and can cause vitamin D toxicity (hypervitaminosis D) — hypercalcemia presenting as nausea, vomiting, weakness, frequent urination, kidney stones, and, in severe cases, kidney injury and calcification 1Reference 1ReviewVitamin D — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/VitaminD-HealthProfessional/View study →.
This is uncommon and generally requires prolonged intake of very high doses (often tens of thousands of IU/day), but it is a genuine risk that distinguishes D from most vitamins. A separate, counterintuitive harm is that high intermittent bolus dosing (e.g. 60,000 IU/month, or an annual megadose) has increased falls and fractures in randomized trials — more is not better 8Reference 8RCTMonthly high-dose vitamin D treatment for the prevention of functional decline — [RCT, harm signal]View study →.
Interactions (drug classes assessed here):
- Thiazide diuretics + vitamin D + calcium → additive hypercalcemia risk.
- Corticosteroids (e.g. prednisone) can impair vitamin D metabolism and calcium absorption.
- Weight-loss / cholesterol agents — orlistat and bile-acid sequestrants (cholestyramine) reduce absorption of fat-soluble vitamins including D; separate dosing.
- Anticonvulsants (phenobarbital, phenytoin) and some antiretrovirals increase catabolism of vitamin D, lowering status.
- Digoxin — because vitamin D can raise calcium, hypercalcemia increases the risk of digoxin toxicity/arrhythmia.
Who should be cautious: people with sarcoidosis or other granulomatous disease, primary hyperparathyroidism, lymphoma, or some forms of kidney disease can experience exaggerated calcium responses and should supplement only under medical supervision 1Reference 1ReviewVitamin D — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/VitaminD-HealthProfessional/View study →.
Verdict: routine maintenance intake at the RDA (600 IU/day) is recommended and safe; do not exceed the UL without medical advice. A Cochrane review found vitamin D supplementation in pregnancy may reduce the risk of pre-eclampsia, gestational diabetes, and low birth weight, though the evidence is of low-to-moderate certainty and optimal dosing is not settled; combining high-dose vitamin D with calcium showed a mixed safety signal (possible increase in preterm birth), so high-dose regimens should be clinician-directed 18Reference 18Systematic reviewVitamin D supplementation for women during pregnancy — [Cochrane systematic review]View study →. The 2024 Endocrine Society guideline now suggests empiric supplementation in pregnancy for its potential to lower the risk of pre-eclampsia, preterm birth, and neonatal/intra-uterine mortality 20Reference 20Vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline — [clinical guideline]View study →. This is general information, not antenatal advice — dosing in pregnancy should be decided with a healthcare professional who has the full clinical picture.
References
- National Institutes of Health, Office of Dietary Supplements. (2024). Vitamin D — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/VitaminD-HealthProfessional/
- Martineau, A. R., et al. (2017). Vitamin D supplementation to prevent acute respiratory tract infections: systematic review and meta-analysis of individual participant data — [IPD meta-analysis]. BMJ. https://pubmed.ncbi.nlm.nih.gov/28202713/
- LeBoff, M. S., et al. (2022). Supplemental vitamin D and incident fractures in midlife and older adults (VITAL) — [RCT]. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/35939577/
- Reid, I. R., et al. (2014). Effects of vitamin D supplements on bone mineral density: a systematic review and meta-analysis — [meta-analysis]. Lancet. https://pubmed.ncbi.nlm.nih.gov/24119980/
- Yao, P., et al. (2019). Vitamin D and calcium for the prevention of fracture: a systematic review and meta-analysis — [meta-analysis]. JAMA Network Open. https://pubmed.ncbi.nlm.nih.gov/31860103/
- Bischoff-Ferrari, H. A., et al. (2012). A pooled analysis of vitamin D dose requirements for fracture prevention — [pooled analysis of RCTs]. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/22762317/
- Bischoff-Ferrari, H. A., et al. (2009). Fall prevention with supplemental and active forms of vitamin D: a meta-analysis of RCTs — [meta-analysis]. BMJ. https://pubmed.ncbi.nlm.nih.gov/19797342/
- Bischoff-Ferrari, H. A., et al. (2016). Monthly high-dose vitamin D treatment for the prevention of functional decline — [RCT, harm signal]. JAMA Internal Medicine. https://pubmed.ncbi.nlm.nih.gov/26747333/
- LeBoff, M. S., et al. (2020). VITAL: effects of vitamin D supplements on risk of falls — [RCT]. Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/32492153/
- Jolliffe, D. A., et al. (2021). Vitamin D supplementation to prevent acute respiratory infections: a systematic review and meta-analysis of aggregate data from RCTs — [meta-analysis]. Lancet Diabetes & Endocrinology. https://pubmed.ncbi.nlm.nih.gov/33798465/
- Murai, I. H., et al. (2021). Effect of a single high dose of vitamin D3 on hospital length of stay in patients with moderate-to-severe COVID-19 — [RCT, null]. JAMA. https://pubmed.ncbi.nlm.nih.gov/33595634/
- Manson, J. E., et al. (2019). Vitamin D supplements and prevention of cancer and cardiovascular disease (VITAL) — [RCT]. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/30415629/
- Neale, R. E., et al. (2022). The D-Health Trial: a randomised controlled trial of the effect of vitamin D on mortality — [RCT]. Lancet Diabetes & Endocrinology. https://pubmed.ncbi.nlm.nih.gov/35026158/
- Zhang, Y., et al. (2019). Association between vitamin D supplementation and mortality: systematic review and meta-analysis — [meta-analysis]. BMJ. https://pubmed.ncbi.nlm.nih.gov/31405892/
- Pittas, A. G., et al. (2019). Vitamin D supplementation and prevention of type 2 diabetes (D2d) — [RCT, null]. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/31173679/
- Okereke, O. I., et al. (2020). Effect of long-term vitamin D3 supplementation vs placebo on risk of depression (VITAL-DEP) — [RCT, null]. JAMA. https://pubmed.ncbi.nlm.nih.gov/32749491/
- Hahn, J., et al. (2022). Vitamin D and marine omega-3 fatty acid supplementation and incident autoimmune disease (VITAL) — [RCT]. BMJ. https://pubmed.ncbi.nlm.nih.gov/35082139/
- Palacios, C., et al. (2019). Vitamin D supplementation for women during pregnancy — [Cochrane systematic review]. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/31348529/
- Holick, M. F., et al. (2011). Evaluation, treatment, and prevention of vitamin D deficiency: an Endocrine Society clinical practice guideline — [clinical guideline]. Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/21646368/
- Demay, M. B., et al. (2024). Vitamin D for the prevention of disease: an Endocrine Society clinical practice guideline — [clinical guideline]. Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/38828931/
- Pittas, A. G., et al. (2023). Vitamin D and risk for type 2 diabetes in people with prediabetes: a systematic review and meta-analysis of individual participant data — [IPD meta-analysis]. Annals of Internal Medicine. https://pubmed.ncbi.nlm.nih.gov/36745886/



