
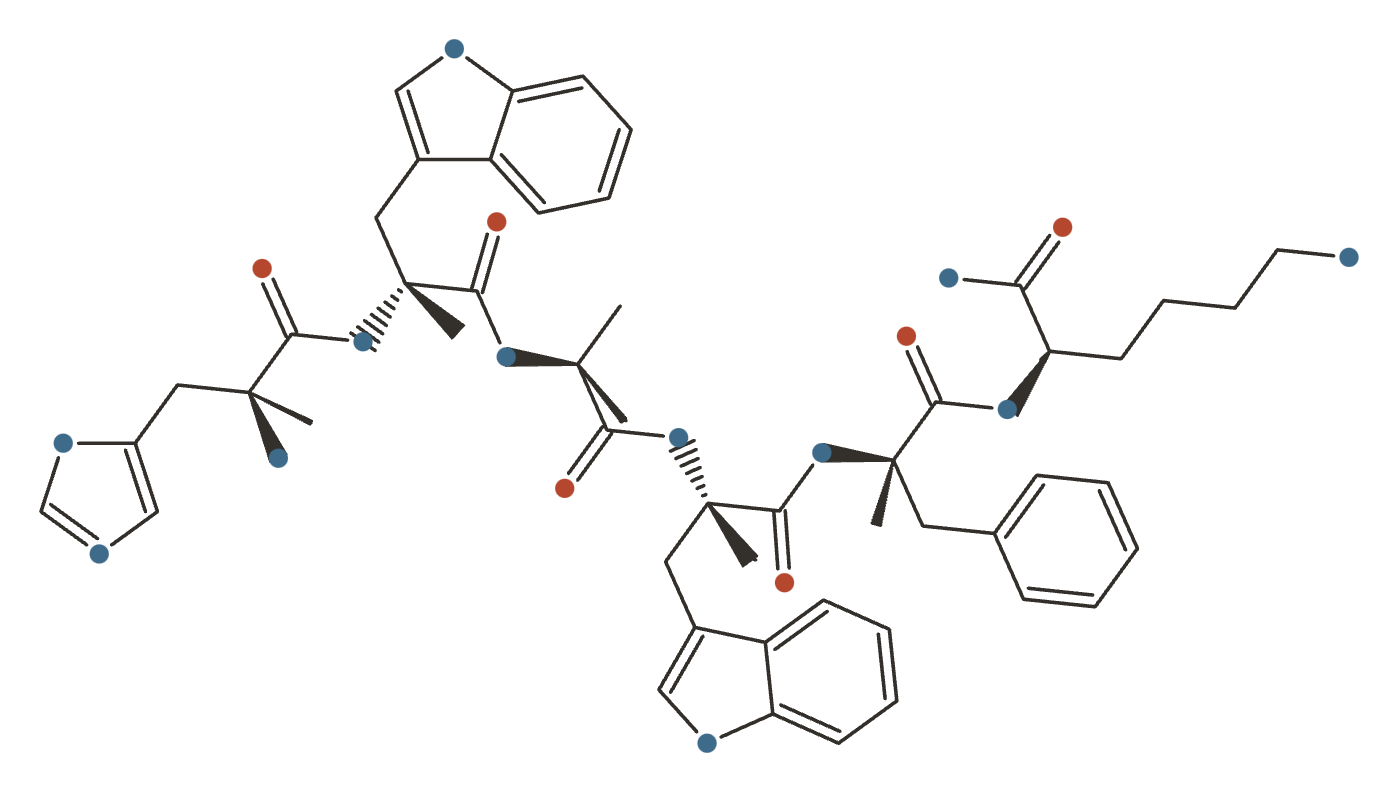
GHRP-6
The original growth-hormone-releasing peptide and a validated GH-stimulation-test reagent — the least selective GHRP, raising cortisol, prolactin and hunger too.

GHRP-6 at a Glance
GHRP-6 is the original growth-hormone-releasing peptide, the compound that revealed the ghrelin receptor existed before ghrelin itself was discovered. It remains a validated reagent for GH-stimulation testing, which makes it the least speculative peptide in this family — its ability to provoke growth hormone is not in question. It is also the most strongly appetite-stimulating of the group, a property that dominates real-world use as much as the GH effect does. It is unapproved as a therapeutic.
History & Development
GHRP-6 is the original growth-hormone-releasing peptide - the compound the whole class descends from, and the least selective member of it.
| First described | Not established in the sources consulted for this section |
| Discovered / synthesised by | Not established in the sources consulted for this section |
| Institution | Not established in the sources consulted for this section |
| Origin | Synthetic hexapeptide; ghrelin-receptor (GHS-R1a) agonist |
| Key patent | Not established in the sources consulted for this section |
| Assignee | Not established in the sources consulted for this section |
| Development status | Established as a GH-stimulation-test reagent; never approved as a therapy |
Discovery
GHRP-6 came first, and its existence is what revealed that the pituitary carries a receptor for something other than GHRH - the receptor later identified as the ghrelin receptor, years before ghrelin itself was found. The peptide effectively predicted its own endogenous ligand.
Its lack of selectivity is its defining property. Alongside growth hormone it raises cortisol, prolactin and hunger - the appetite effect being pronounced enough to define the user experience. Every later secretagogue in this family, ipamorelin especially, was designed to keep the GH release and drop the rest.
Development & ownership
GHRP-6’s established role is as a validated reagent for GH-stimulation testing - a diagnostic tool, not a therapy.
Its human evidence should be read for what it is: essentially every study measures GH concentration in blood, over a couple of hours, in a handful of volunteers. Those are pharmacodynamic demonstrations that the compound does what it says, not evidence of any clinical outcome. The effect is short-lived and attenuates with repetition.
The most active therapeutic research line is cardiac and entirely preclinical - including work in 26 dogs with pacing-induced dilated cardiomyopathy, where two weeks of subcutaneous GHRP-6 enhanced systolic function.
How it reached the market
GHRP-6 has never been approved as a therapy anywhere. It is sold as a research peptide for muscle gain and recovery, where its hallmark side effect - intense hunger - is often reframed as a benefit for bulking rather than as the off-target cost it represents.
What It's Used For
GHRP-6 is a synthetic hexapeptide — His-D-Trp-Ala-Trp-D-Phe-Lys-NH₂, about 873 Da — and it matters first as a piece of scientific history rather than as a therapy. Cyril Bowers’ group at Tulane built it in the 1980s from opioid-peptide fragments, and it became the pharmacological probe that revealed a growth-hormone-releasing pathway separate from GHRH 3Reference 3GH releasing peptides — structure and kinetics — human (GH response after IV, SC and oral dosing)View study →.
That receptor was named the growth-hormone-secretagogue receptor (GHS-R1a) after the drug that found it; the body’s own ligand for it, ghrelin, was not identified until 1999 — more than a decade later 25Reference 25ReviewPhysiology of ghrelin and related peptides — reviewView study →.
So GHRP-6 is the compound that led to the discovery of a hormone. That is a genuine and unusual pedigree, and it is worth being clear about what it is: a discovery story, not clinical evidence. GHRP-6 has never been approved as a medicine or a dietary supplement in any country, and no outcome trial has ever been completed for it.
What human data exist are almost entirely acute GH-pulse pharmacology in small volunteer groups from the 1990s and early 2000s, plus a body of diagnostic-test work in which GHRP-6 (usually combined with GHRH) served as a provocative stimulus for diagnosing adult growth-hormone deficiency 6,
That is a reagent’s paper trail, not a drug’s. The therapeutic lines that look most active today — cardioprotection, multi-organ cytoprotection — are animal and in-vitro only, and are concentrated in a single development program (Cuba’s CIGB, with Chinese collaborators, advancing GHRP-6 as CIGB-500) that remains preclinical 24Reference 24Subchronic safety assessment of CIGB-500 in beagle dog after repeated daily dose administration over 28 days — animal (dog, regulatory toxicology)View study →.
Route is worth noting because it cuts against the usual peptide rule: GHRP-6 releases GH in humans by intravenous, subcutaneous, intranasal and oral administration 3,
The property that actually distinguishes GHRP-6 from its successors is non-selectivity. It is the least selective of the GHRPs: in humans it raises ACTH and cortisol alongside GH 9,
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric.
Read the low scores carefully here, because they mean “never tested,” not “tested and failed.” GHRP-6 has essentially no negative human data — but it also has no positive human outcome data, for anything. Every human study here measures a hormone level or a diagnostic cut-off, and every therapeutic claim below the top two rows is preclinical. A high score on the diagnostic row is a score for a laboratory test, not for a treatment. Each application links down to its write-up.
GHRP-6’s most solid human application — and it is a laboratory test, not a therapy. Because GHRP-6 and GHRH release GH through different receptors, giving both together is a far more powerful provocative stimulus than either alone, which is exactly what a diagnostic test wants. In a human multicenter study of 125 adults with organic pituitary disease and 125 healthy controls, a single intravenous GHRH 1 µg/kg + GHRP-6 1 µg/kg produced mean GH peaks of 4.1 µg/L in patients versus 59.2 µg/L in controls — a far wider separation than the insulin-tolerance test achieved in the same subjects (0.5 vs 14.3 µg/L) — with no side-effects and no confounding by age, sex, adiposity or assay 6Reference 6GH-releasing hormone and GH-releasing peptide-6 for diagnostic testing in GH-deficient adults — human (multicentre diagnostic-accuracy study, n=250)View study →.
A second human study compared GHRP-6 alone and with GHRH against the ITT in adults 7Reference 7Diagnosis of growth hormone deficiency in adults by testing with GHRP-6 alone or in combination with GHRH: comparison with the insulin tolerance test — human (diagnostic comparison)View study →, and a three-way human comparison of the ITT, GHRH, GHRH+acipimox and GHRH+GHRP-6 positioned the GHRP-6 combination as a viable ITT alternative 8Reference 8Clinical trialComparison between insulin tolerance test, GHRH, GHRH plus acipimox and GHRH plus GHRP-6 for the diagnosis of adult GH deficiency in normal subjects, obese and hypopituitary patients — human (clinical trial)View study →.
A related human study used a GHRP-6 test to probe the hypothalamic-pituitary-adrenal axis for diagnosing adrenal insufficiency, again against the ITT reference 9Reference 9Clinical trialDiagnosis of adrenal insufficiency using the GHRP-6 test: comparison with the insulin tolerance test in patients with hypothalamic-pituitary-adrenal disease — human (clinical trial)View study →.
Gap: All human, all genuine — and entirely beside the point for anyone considering GHRP-6 as a drug. This is diagnostic-accuracy evidence for a reagent that was never approved as a product, and the role has since been taken by macimorelin, an approved oral GH secretagogue test. Nothing here speaks to therapeutic use, chronic dosing, or benefit of any kind.
This is what GHRP-6 is proven to do in humans, and the ceiling on that proof is important. Bowers’ original human work established that GHRP-6 releases GH after intravenous, subcutaneous and oral administration in healthy young men and women, more efficaciously than GHRH 1-44 3Reference 3GH releasing peptides — structure and kinetics — human (GH response after IV, SC and oral dosing)View study →; oral GHRP-6 also released GH in human children with varying degrees of GH deficiency, though at much larger doses (300 µg/kg) reflecting poor oral bioavailability 5Reference 5Clinical trialGrowth hormone-releasing effect of oral growth hormone-releasing peptide 6 (GHRP-6) administration in children with short stature — human (controlled clinical trial, paediatric)View study →.
Mechanistically the pathway is resolved in human pituitary tissue: GHRP-6 drove a dose-dependent 2.1–7.9-fold increase in phosphatidylinositol turnover in cultured somatotrophinoma cells from 8 of 8 tumors, with parallel GH release, confirming a PKC/Ca²⁺-dependent and cAMP-independent mechanism 1Reference 1In vitroGrowth hormone releasing peptide (GHRP-6) stimulates phosphatidylinositol (PI) turnover in human pituitary somatotroph cells — in vitro (human pituitary tumour cells)View study → — later shown to also cross-talk with cAMP production in the same human tumor cells 4Reference 4In vitroProtein kinase C-dependent growth hormone releasing peptides stimulate cyclic adenosine 3’,5’-monophosphate production by human pituitary somatotropinomas — in vitro (human pituitary tumour cells)View study →.
Class reviews confirm potent somatotrope stimulation through a receptor distinct from the GHRH receptor 2,
Note what this evidence is and is not. Every one of these studies measures GH concentration in blood, usually over a couple of hours, in a handful of volunteers. The effect is short-lived and attenuates on repeated dosing, and no trial — none — has followed a GHRP-6 GH pulse through to IGF-1 elevation sustained over weeks, let alone to a change in muscle, fat, strength, recovery or any clinical endpoint.
Gap: the biomarker moves; the outcome has never been measured. There is also no modern human study — the entire human GH-release literature predates 2005, uses small volunteer groups, and was never followed by a controlled efficacy trial.
The most active therapeutic research line, and it is entirely preclinical. In 26 dogs with pacing-induced dilated cardiomyopathy, two weeks of subcutaneous GHRP-6 (0.2 mg/kg/day) enhanced systolic wall thickening in non-ischemic myocardium (+53% vs +14% for GH and vehicle) and, strikingly, no GHRP-6-treated dog died during coronary occlusion while survival was 57% and 55% in the GH and vehicle arms. The authors attributed the effect to GH-secretagogue receptors rather than the GH/IGF-1 pathway — a GH-independent mechanism 15Reference 15A growth hormone secretagogue prevents ischemic-induced mortality independently of the growth hormone pathway in dogs with chronic dilated cardiomyopathy — animal (dog, n=26)View study →.
In rats, GHRP-6 blunted doxorubicin-induced myocardial and extra-myocardial damage by activating pro-survival signaling 16Reference 16AnimalGrowth hormone releasing peptide-6 (GHRP-6) prevents doxorubicin-induced myocardial and extra-myocardial damages by activating prosurvival mechanisms — animal (rat)View study →, and ameliorated post-infarct ventricular remodeling and systolic dysfunction after permanent coronary ligation 17Reference 17AnimalGrowth hormone-releasing peptide-6 (GHRP-6) ameliorates post-infarct ventricular remodeling and systolic dysfunction in a model of permanent coronary ligation — animal (rat)View study →.
The proposed molecular route is the CD36 scavenger receptor: GHRP-6 azapeptide analogues bind CD36 with anti-angiogenic and anti-atherosclerotic activity even when GHS-R1a affinity is deliberately engineered out in vitro 21,
Gap: No human trial, and none registered. All efficacy is dog and rat, and the program is dominated by a single developer — Cuba’s Center for Genetic Engineering and Biotechnology, with Chinese collaborators, advancing GHRP-6 as CIGB-500 for myocardial infarction, still at the preclinical-toxicology stage 24Reference 24Subchronic safety assessment of CIGB-500 in beagle dog after repeated daily dose administration over 28 days — animal (dog, regulatory toxicology)View study →. Independent replication outside that program is thin. A striking mortality result in eight dogs is a reason to run a trial, not a reason to use the compound.
This is GHRP-6’s most distinctive effect and the main reason it has a reputation at all — and the evidence for it is rodent, with the human side resting on class inference. Intracerebroventricular GHRP-6 in rats significantly stimulated food intake and activated the hypothalamic appetite centers (arcuate, paraventricular, dorsomedial and lateral hypothalamic nuclei, plus brainstem NTS and area postrema) on c-Fos mapping; the effect was blocked by an NPY Y1 antagonist, and cell activation occurred even when the animals were denied food afterward — so it is a direct central effect, not a consequence of eating 12Reference 12AnimalAcute central ghrelin and GH secretagogues induce feeding and activate brain appetite centers — animal (rat, intracerebroventricular)View study →.
In a second rat study, twice-daily subcutaneous GHRP-6 (250 µg/kg) increased food intake for up to seven hours per injection and, over two weeks, raised subcutaneous and visceral fat-pad weights by 15–20%; adrenalectomy abolished the food-intake effect unless corticosterone was replaced, so basal glucocorticoids are permissive for the hunger response 13Reference 13AnimalGlucocorticoid-dependent stimulation of adiposity and appetite by a ghrelin mimetic in the rat — animal (rat)View study →.
The human position must be stated precisely, because this is where the literature is routinely over-read. GHRP-6 is a ghrelin-receptor agonist, ghrelin is orexigenic in humans, and hunger is the effect gray-market users report most consistently — but no human study has ever measured food intake or appetite as an endpoint on GHRP-6. The human food-intake trials in this class were run on ghrelin itself and on GHRP-2, which are different molecules. Treating those results as GHRP-6 results is the single most common citation error in this literature.
Gap: replicated and mechanistically clean in rats; zero human food-intake, appetite-rating or cachexia outcome data for GHRP-6 specifically. No such trial is registered anywhere. The orexigenic effect is best described as a strong, mechanistically-expected class property with consistent user report — not a demonstrated human finding.
Beyond the heart, GHRP-6 protects several tissues in animal injury models, consistent with the same GH-independent CD36/pro-survival mechanism. In a rat hepatic ischemia/reperfusion model of multiple organ failure, GHRP-6 pre-treatment reduced hepatic and intestinal damage, neutrophil infiltration and lipid peroxidation by roughly 50–85%, with additive benefit alongside EGF, and drove gut epithelial cell migration in vitro 18Reference 18In vitroUse of growth-hormone-releasing peptide-6 (GHRP-6) for the prevention of multiple organ failure — animal (rat) and in vitroView study →.
In mice, GHRP-6 attenuated acute lung injury and its subsequent progression to interstitial fibrosis 19Reference 19AnimalGrowth hormone releasing peptide-6 (GHRP-6) ameliorates acute lung injury and its subsequent evolvement to interstitial fibrosis — animal (mouse)View study →.
A GHRP-6 hydrogel improved acute kidney injury via metabolic regulation in a rodent model 20Reference 20AnimalGrowth hormone-releasing peptide 6 (GHRP-6) hydrogel for acute kidney injury therapy via metabolic regulation — animal (rodent)View study →.
Gap: Animal and in-vitro only, again concentrated in the CIGB and collaborator program, and the newest of these papers are recent enough that independent replication has not had time to appear. There is no human cytoprotection data of any kind — no trial, no case series, no registered study.
Distinct from acute hunger: does chronic GHRP-6 actually change body composition? In rats, yes — but conditionally, and in the direction opposite to what physique users want. In streptozotocin-diabetic rats, GHRP-6 alone did not correct hyperglycemia or weight loss; only combined with insulin did the animals gain more weight, epididymal fat and serum leptin than any other group, so the adipogenic effect depends on insulin/glucose status 14Reference 14AnimalThe positive effects of growth hormone-releasing peptide-6 on weight gain and fat mass accrual depend on the insulin/glucose status — animal (rat)View study →.
In adrenalectomized versus adrenal-intact rats, GHRP-6-driven body-weight gain was glucocorticoid-independent but the fat accumulation was not — visceral and subcutaneous fat pads increased only in adrenal-intact animals 13Reference 13AnimalGlucocorticoid-dependent stimulation of adiposity and appetite by a ghrelin mimetic in the rat — animal (rat)View study →.
There is one human-relevant metabolic datum, and it is a caution rather than a benefit: in a double-blind, placebo-controlled study in ten healthy men, GHRP-6 1 µg/kg given under GH-receptor blockade with pegvisomant caused an acute, marked rise in serum insulin (10.3 → 81.3 mU/L) and glucose, indicating direct, non-pituitary-mediated effects on glucose handling 11Reference 11RCTBlockade of the growth hormone (GH) receptor unmasks rapid GH-releasing peptide-6-mediated tissue-specific insulin resistance — human (double-blind, placebo-controlled, n=10)View study →.
Gap: Rat-only for body composition, mechanistically contingent on two hormonal axes, and pointing toward more fat rather than less. No human body-composition data of any kind exists — no trial has ever weighed, scanned or DXA’d a person on GHRP-6.
A niche but genuinely human in-vitro finding, included because it is the only recent human GHRP-6 data of any kind. In an embryology study, 240 human germinal-vesicle oocytes cultured in media containing GHRP-6 matured faster than in standard or sham media, with an optimum around 75 ng/mL giving roughly 70–80% nuclear maturation and significantly earlier first-polar-body appearance. It did not significantly improve cytoplasmic maturation or the maturation-gene expression tested 26Reference 26In vitroAssessing the effectiveness of growth hormone releasing protein-6 in improving human oocyte maturation and meiotic progression in in vitro maturation culture media — in vitro (human oocytes)View study →.
Gap: this is laboratory culture-medium use, not human dosing — nobody was given GHRP-6. It is a single study from a single group, and the result is mixed (nuclear maturation yes, cytoplasmic no). It says nothing about GHRP-6 taken by a person, for fertility or anything else.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| GHS-R1a (ghrelin receptor), pituitary somatotrophs | Agonist → GH release via phosphatidylinositol turnover, PKC and Ca²⁺; cAMP-independent (human tissue) 1, | GH elevationdiagnostic testing |
| GHS-R1a, hypothalamus (arcuate, PVN, LH; NPY/AgRP and orexin neurons) | Agonist → increased food intake; blocked by an NPY Y1 antagonist (rat) 12Reference 12AnimalAcute central ghrelin and GH secretagogues induce feeding and activate brain appetite centers — animal (rat, intracerebroventricular)View study → | Appetite stimulation |
| Pituitary corticotrophs / lactotrophs — the non-selectivity | ACTH and cortisol rise alongside GH in humans 9, | Safety; the reason ipamorelin was developed |
| CD36 (class-B scavenger receptor) | Ligand → pro-survival, anti-angiogenic, anti-atherosclerotic signaling, independent of GH 15, | Cardioprotectioncytoprotection |
| Angiotensin-converting enzyme | Domain-selective inhibition (GHS class, in vitro) 23Reference 23In vitroNovel domain-selective ACE-inhibiting activity of synthetic growth hormone secretagogues — in vitroView study → | Cardiovascular mechanism (speculative) |
| Insulin / glucose handling (non-pituitary) | Acute rise in insulin and glucose under GH-receptor blockade (human) 11Reference 11RCTBlockade of the growth hormone (GH) receptor unmasks rapid GH-releasing peptide-6-mediated tissue-specific insulin resistance — human (double-blind, placebo-controlled, n=10)View study →; fat accrual requires insulin (rat) 14Reference 14AnimalThe positive effects of growth hormone-releasing peptide-6 on weight gain and fat mass accrual depend on the insulin/glucose status — animal (rat)View study → | Metabolic risk; conditional adiposity |
| Glucocorticoid axis (permissive) | Basal corticosterone required for the orexigenic and fat-accrual effect (rat) 13Reference 13AnimalGlucocorticoid-dependent stimulation of adiposity and appetite by a ghrelin mimetic in the rat — animal (rat)View study → | Appetitefat gain |
Pharmacokinetics
Route is unusually permissive for a peptide, and this is a real distinction. GHRP-6 releases GH in humans after intravenous, subcutaneous, intranasal and oral administration 3Reference 3GH releasing peptides — structure and kinetics — human (GH response after IV, SC and oral dosing)View study → — the last of these is genuinely notable, since almost every other peptide on this hub is destroyed by digestion. But oral bioavailability is poor enough that the doses diverge by orders of magnitude: diagnostic testing uses 1 µg/kg intravenously 6Reference 6GH-releasing hormone and GH-releasing peptide-6 for diagnostic testing in GH-deficient adults — human (multicentre diagnostic-accuracy study, n=250)View study →, while the pediatric oral study needed 300 µg/kg 5Reference 5Clinical trialGrowth hormone-releasing effect of oral growth hormone-releasing peptide 6 (GHRP-6) administration in children with short stature — human (controlled clinical trial, paediatric)View study →. So “orally active” is true and misleading at the same time — it does not make an oral product practical.
The GH-releasing effect is short: GH peaks within roughly 30–60 minutes and returns toward baseline within about two hours, and the response attenuates with frequent repeated dosing (tachyphylaxis) — a key reason GHRP-6 never became a chronic therapy and why its entire human record is acute-probe-shaped. A dedicated human plasma half-life has not been established in the primary literature located in this pass; it is best described as short, on the order of tens of minutes, and the specific figures circulating on vendor sites are not traceable to a primary source. None is invented here. GHRP-6 also has documented non-pituitary actions — the acute insulin and glucose rise seen under GH-receptor blockade was attributed to direct effects on the gastroentero-hepatic axis rather than to GH 11Reference 11RCTBlockade of the growth hormone (GH) receptor unmasks rapid GH-releasing peptide-6-mediated tissue-specific insulin resistance — human (double-blind, placebo-controlled, n=10)View study → — so its pharmacodynamics are not fully captured by the GH curve.
Gray-market supply is lyophilized powder requiring reconstitution by the user, typically with bacteriostatic water, and injected subcutaneously; reconstituted solution must be refrigerated and is short-lived. Reconstitution and stability parameters in that channel are vendor claims, not independently documented. The CIGB-500 development formulation is given intravenously 24Reference 24Subchronic safety assessment of CIGB-500 in beagle dog after repeated daily dose administration over 28 days — animal (dog, regulatory toxicology)View study →.
Clinical & regulatory status
GHRP-6 is an unapproved research chemical. It has never been approved as a drug or a dietary supplement by the FDA, EMA, TGA or any other regulator, in any country, for any indication — including the diagnostic use it was validated for. Its legitimate human history is entirely as an investigational diagnostic and pharmacological probe from the 1990s and 2000s, predating trial-registration mandates; that diagnostic role has since been filled by macimorelin, an approved oral GH-secretagogue test. As a growth-hormone secretagogue it is prohibited in sport at all times under the WADA Prohibited List (class S2). In the consumer market it is sold “for research use only / not for human consumption.”
A direct query of the ClinicalTrials.gov API in this pass returned zero registered studies for GHRP-6, for CIGB-500, and for “growth hormone releasing peptide-6” as an intervention or term. There is no completed trial, no ongoing trial and no terminated trial to report — the compound has never entered the modern registered-trial system at all. The only live therapeutic development is CIGB’s CIGB-500 program for myocardial infarction, which remains in preclinical toxicology 24Reference 24Subchronic safety assessment of CIGB-500 in beagle dog after repeated daily dose administration over 28 days — animal (dog, regulatory toxicology)View study →.
| Completed | Ongoing | Terminated | Preclinical |
|---|---|---|---|
| 0registered (the 1990s–2000s human diagnostic and GH-release studies predate registration) | 0registered | 0registered | Extensive — dog, rat and mouse efficacy models plus a 28-day beagle-dog CIGB-500 toxicology study |
Last checked: July 2026.
Sourcing, Route & Legal Status
Regulatory status. GHRP-6 is not approved anywhere, for anything — not as a medicine, not as a dietary supplement, and not (despite its validated performance as a test reagent) as a diagnostic product. It is not a scheduled or controlled substance in the US, but “not scheduled” is not “approved”: marketing it for human consumption is unlawful in most Western jurisdictions, which is why it is sold as a research chemical labeled not for human consumption — a labeling convention that shifts liability to the buyer and provides no quality assurance whatsoever. It is banned in sport at all times under WADA class S2 and is a routine target in doping-control assays. The one active therapeutic-development effort, Cuba’s CIGB with Chinese collaborators developing GHRP-6 as CIGB-500, is preclinical and not marketed 24Reference 24Subchronic safety assessment of CIGB-500 in beagle dog after repeated daily dose administration over 28 days — animal (dog, regulatory toxicology)View study →.
How it’s supplied and administered. Gray-market GHRP-6 arrives as a lyophilized (freeze-dried) powder in a multi-dose vial, commonly 5–10 mg, which the buyer reconstitutes with bacteriostatic or sterile water before subcutaneous injection. Lyophilized powder is stored refrigerated or frozen and protected from light; reconstituted solution is unstable and must be refrigerated and used quickly. The short duration of the GH pulse is why community protocols involve repeated daily injections — a pattern no study has ever evaluated. Although GHRP-6 is one of the few peptides here with genuine oral activity 3,
Sourcing reality (this is a safety issue, not a footnote). Every gray-market vial comes from an unregulated supplier with no manufacturing oversight. There is no assurance of identity, correct sequence, peptide content, freedom from synthesis impurities, or absence of bacterial endotoxin — the last of which matters acutely for an injected product, where contamination can cause fever, injection-site reactions or systemic illness. Mislabeling, under- and over-filling and outright substitution are documented problems across the research-peptide market. A specific hazard for this compound is substitution within its own class: GHRP-6, GHRP-2 and hexarelin are closely related hexapeptides with different selectivity profiles, and a buyer has no way to distinguish them without independent analysis. Third-party certificates of analysis — mass-spectrometry identity, HPLC purity and endotoxin testing — are the minimum needed to interpret the risk, and even those are only as trustworthy as whoever commissioned them. This page does not recommend or link vendors; gray-market peptide identity and purity cannot be assumed.
Safety
No human study of GHRP-6 has ever run beyond a single acute dose, so nothing here is a long-term safety record. Its defining liability is non-selectivity — it raises ACTH, cortisol and prolactin alongside growth hormone, which is precisely what the later secretagogues were engineered to avoid.
- The least selective of the GH secretagogues. It stimulates the stress axis every time it is dosed, and nobody has studied what chronic exposure does.
- Measured metabolic effect in humans. A roughly eight-fold acute rise in insulin and a rise in glucose under GH-receptor blockade.
- Several groups should not use it at all. Active or prior malignancy, diabetes, adrenal or pituitary disease, children and adolescents, and anyone pregnant or breastfeeding.
- Long-term safety is unstudied, not reassuring. The longest controlled data of any kind is a 28-day intravenous study in dogs.
- Strong hunger is the practical ceiling. In rodents that appetite effect translates into increased fat mass — the opposite of the intended use.
- Unregulated injected product. Injection-site reactions, non-sterile technique, endotoxin exposure and self-mixed dosing error.
Full Safety & Interactions Detail
Overall posture. No human study of GHRP-6 has ever run longer than a single acute dose. Within that narrow window it was well tolerated: the 250-subject diagnostic study reported no side-effects from a 1 µg/kg intravenous dose combined with GHRH 6Reference 6GH-releasing hormone and GH-releasing peptide-6 for diagnostic testing in GH-deficient adults — human (multicentre diagnostic-accuracy study, n=250)View study →, and the equivalent doses in the other diagnostic studies were similarly uneventful 7,
The defining liability is non-selectivity. GHRP-6 is the least selective of the growth-hormone secretagogues, and this is the single most decision-relevant safety fact on the page. In humans, GHRP-6 releases ACTH and cortisol alongside GH — reliably enough that it has been used as a deliberate provocative test of the hypothalamic-pituitary-adrenal axis 9,
Appetite as a dose-limiting effect. Strong hunger is the effect users report most consistently and the practical tolerability ceiling for most of them. It is well demonstrated in rats 12,
Metabolic effects. GHRP-6 acutely raised serum insulin roughly eight-fold and raised glucose in healthy men under GH-receptor blockade, an effect attributed to direct non-pituitary action 11Reference 11RCTBlockade of the growth hormone (GH) receptor unmasks rapid GH-releasing peptide-6-mediated tissue-specific insulin resistance — human (double-blind, placebo-controlled, n=10)View study →. Separately, the GH class carries recognized effects on insulin sensitivity and glucose handling and on fluid balance (edema, arthralgia and carpal-tunnel-type symptoms are characteristic of GH excess). The human GHRP-6 finding is measured; the class effects are mechanistic inference and are labeled as such.
Animal toxicology. A 28-day repeated-dose study in beagle dogs of the CIGB-500 formulation found only transient, non-adverse signs — hypersalivation, hypoactivity, reduced heart rate — with a NOAEL of 2000 µg/kg/day 24Reference 24Subchronic safety assessment of CIGB-500 in beagle dog after repeated daily dose administration over 28 days — animal (dog, regulatory toxicology)View study →. That is genuinely useful preclinical data. It is also 28 days, in dogs, intravenous, and does not establish human safety.
Interactions. No formal human drug-interaction study exists. Mechanistic cautions only: GHRH analogues (sermorelin, CJC-1295, tesamorelin) synergize strongly with GHRP-6 on GH release — that synergy is the entire basis of the diagnostic combination test 6Reference 6GH-releasing hormone and GH-releasing peptide-6 for diagnostic testing in GH-deficient adults — human (multicentre diagnostic-accuracy study, n=250)View study →, and it is also the most common community stacking pattern, meaning the combined endocrine effect is larger than either compound alone; glucose-lowering agents, given the demonstrated insulin/glucose effect 11Reference 11RCTBlockade of the growth hormone (GH) receptor unmasks rapid GH-releasing peptide-6-mediated tissue-specific insulin resistance — human (double-blind, placebo-controlled, n=10)View study →; and corticosteroids or dopaminergic agents, given the cortisol and prolactin effects. All inferred, none tested.
Who should avoid it. Anyone with active or prior malignancy, given GH/IGF-1’s proliferative signaling; anyone with diabetes or impaired glucose tolerance; anyone with adrenal or pituitary disease, or on corticosteroid therapy, given the ACTH/cortisol effect; anyone with a prolactin-sensitive condition; anyone pregnant, breastfeeding or trying to conceive; children and adolescents, in whom an unstudied compound acting on the growth axis during growth is indefensible; competitive athletes; and anyone unwilling to accept an unapproved product of unverified identity and purity.
Injection-specific risks. Reconstituted, self-injected product from unregulated sources brings injection-site reactions, infection from non-sterile technique, endotoxin exposure and dosing error from self-mixed concentrations. These are hazards of how the compound is obtained and used, independent of its pharmacology.
Scope disclosure (honesty, not a claim):
- Human data? Yes, but narrow and old — acute GH-release pharmacology and diagnostic-accuracy studies, essentially all from 1993–2010 in small volunteer or patient groups. There is no human outcome trial for any indication, and no human data at all for the muscle, fat-loss, recovery or anti-aging uses it is sold for.
- Interactions assessed? No. Only mechanism-based cautions (GHRH analogues, glucose-lowering agents, corticosteroids, dopaminergics).
- Pregnancy/lactation assessed? No — no human or animal reproductive data located.
- Long-term safety established? No. No human study has run beyond acute dosing. The longest controlled safety data of any kind is a 28-day intravenous study in dogs 24Reference 24Subchronic safety assessment of CIGB-500 in beagle dog after repeated daily dose administration over 28 days — animal (dog, regulatory toxicology)View study →.
- Appetite effect in humans measured? No. It is a consistent user report and a mechanistically-expected class property; no human trial has measured food intake or appetite on GHRP-6.
Never imply safety from silence. Where GHRP-6 has not been studied — chronic dosing, the subcutaneous community route, interactions, pregnancy, cortisol exposure over time, gray-market purity — the correct statement is “not assessed,” not “safe.”
Not assessed / not established. There are no human pregnancy or lactation data for GHRP-6 and no reproductive-toxicity data located, and there is no regulatory label to draw on. Treat as contraindicated by default in pregnancy and breastfeeding.
Dosage
There is no established human therapeutic dose for GHRP-6, and none is recommended here. It has never been approved for any indication in any country, so there is no label, no titration schedule and no maintenance regimen to report. Everything below is data reported for context, not a personal recommendation.
The only well-characterized human dose is diagnostic: 1 µg/kg intravenously, typically given simultaneously with GHRH 1 µg/kg as a single bolus, with GH sampled over the following 120 minutes 6,
References
- Lei T, Buchfelder M, Fahlbusch R, Adams EF. (1995). Growth hormone releasing peptide (GHRP-6) stimulates phosphatidylinositol (PI) turnover in human pituitary somatotroph cells — in vitro (human pituitary tumour cells). Journal of Molecular Endocrinology. https://pubmed.ncbi.nlm.nih.gov/7772238/
- Ghigo E, Arvat E, Muccioli G, Camanni F. (1997). Growth hormone-releasing peptides — review. European Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/9186261/
- Bowers CY. (1993). GH releasing peptides — structure and kinetics — human (GH response after IV, SC and oral dosing). Journal of Pediatric Endocrinology. https://pubmed.ncbi.nlm.nih.gov/8374685/
- Adams EF, Lei T, Buchfelder M, Bowers CY, Fahlbusch R (1996). Protein kinase C-dependent growth hormone releasing peptides stimulate cyclic adenosine 3’,5’-monophosphate production by human pituitary somatotropinomas — in vitro (human pituitary tumour cells). Molecular Endocrinology. https://pubmed.ncbi.nlm.nih.gov/8721987/
- Bellone J, Ghizzoni L, Aimaretti G, et al. (1995). Growth hormone-releasing effect of oral growth hormone-releasing peptide 6 (GHRP-6) administration in children with short stature — human (controlled clinical trial, paediatric). European Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/7581965/
- Popovic V, Leal A, Micic D, et al. (2000). GH-releasing hormone and GH-releasing peptide-6 for diagnostic testing in GH-deficient adults — human (multicentre diagnostic-accuracy study, n=250). The Lancet. https://pubmed.ncbi.nlm.nih.gov/11030292/
- Petersenn S, Jung R, Beil FU. (2002). Diagnosis of growth hormone deficiency in adults by testing with GHRP-6 alone or in combination with GHRH: comparison with the insulin tolerance test — human (diagnostic comparison). European Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/11980622/
- Cordido F, Alvarez-Castro P, Isidro ML, Casanueva FF, Dieguez C. (2003). Comparison between insulin tolerance test, GHRH, GHRH plus acipimox and GHRH plus GHRP-6 for the diagnosis of adult GH deficiency in normal subjects, obese and hypopituitary patients — human (clinical trial). European Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/12887288/
- Alaioubi B, Mann K, Petersenn S. (2010). Diagnosis of adrenal insufficiency using the GHRP-6 test: comparison with the insulin tolerance test in patients with hypothalamic-pituitary-adrenal disease — human (clinical trial). Hormone and Metabolic Research. https://pubmed.ncbi.nlm.nih.gov/19946832/
- de Sá LB, Nascif SO, Correa-Silva SR, et al. (2010). Effects of ghrelin, growth hormone-releasing peptide-6, and growth hormone-releasing hormone on growth hormone, adrenocorticotropic hormone, and cortisol release in type 1 diabetes mellitus — human (controlled study, n=18). Metabolism. https://pubmed.ncbi.nlm.nih.gov/20189610/
- Muller AF, Janssen JA, Hofland LJ, et al. (2001). Blockade of the growth hormone (GH) receptor unmasks rapid GH-releasing peptide-6-mediated tissue-specific insulin resistance — human (double-blind, placebo-controlled, n=10). Journal of Clinical Endocrinology & Metabolism. https://pubmed.ncbi.nlm.nih.gov/11158013/
- Lawrence CB, Snape AC, Baudoin FM, Luckman SM. (2002). Acute central ghrelin and GH secretagogues induce feeding and activate brain appetite centers — animal (rat, intracerebroventricular). Endocrinology. https://pubmed.ncbi.nlm.nih.gov/11751604/
- Tung YL, Hewson AK, Dickson SL. (2004). Glucocorticoid-dependent stimulation of adiposity and appetite by a ghrelin mimetic in the rat — animal (rat). European Journal of Endocrinology. https://pubmed.ncbi.nlm.nih.gov/15191362/
- Granado M, García-Cáceres C, Frago LM, Argente J, Chowen JA. (2010). The positive effects of growth hormone-releasing peptide-6 on weight gain and fat mass accrual depend on the insulin/glucose status — animal (rat). Endocrinology. https://pubmed.ncbi.nlm.nih.gov/20219977/
- Shen YT, Lynch JJ, Hargreaves RJ, Gould RJ. (2003). A growth hormone secretagogue prevents ischemic-induced mortality independently of the growth hormone pathway in dogs with chronic dilated cardiomyopathy — animal (dog, n=26). Journal of Pharmacology and Experimental Therapeutics. https://pubmed.ncbi.nlm.nih.gov/12750438/
- Berlanga-Acosta J, et al. (2024). Growth hormone releasing peptide-6 (GHRP-6) prevents doxorubicin-induced myocardial and extra-myocardial damages by activating prosurvival mechanisms — animal (rat). Frontiers in Pharmacology. https://pubmed.ncbi.nlm.nih.gov/38873418/
- Wang L, et al. (2026). Growth hormone-releasing peptide-6 (GHRP-6) ameliorates post-infarct ventricular remodeling and systolic dysfunction in a model of permanent coronary ligation — animal (rat). Pharmaceuticals (Basel). https://pubmed.ncbi.nlm.nih.gov/41901314/
- Cibrián D, Ajamieh H, Berlanga J, et al. (2006). Use of growth-hormone-releasing peptide-6 (GHRP-6) for the prevention of multiple organ failure — animal (rat) and in vitro. Clinical Science (London). https://pubmed.ncbi.nlm.nih.gov/16417467/
- Wang L, et al. (2026). Growth hormone releasing peptide-6 (GHRP-6) ameliorates acute lung injury and its subsequent evolvement to interstitial fibrosis — animal (mouse). International Immunopharmacology. https://pubmed.ncbi.nlm.nih.gov/41534456/
- Zhao X, et al. (2025). Growth hormone-releasing peptide 6 (GHRP-6) hydrogel for acute kidney injury therapy via metabolic regulation — animal (rodent). Journal of Nanobiotechnology. https://pubmed.ncbi.nlm.nih.gov/41327290/
- Sabatino D, Proulx C, Pohankova P, et al. (2011). Structure-activity relationships of GHRP-6 azapeptide ligands of the CD36 scavenger receptor by solid-phase submonomer azapeptide synthesis — in vitro. Journal of the American Chemical Society. https://pubmed.ncbi.nlm.nih.gov/21692501/
- Proulx C, Picard É, Boeglin D, et al. (2012). Azapeptide analogues of the growth hormone releasing peptide 6 as cluster of differentiation 36 receptor ligands with reduced affinity for the growth hormone secretagogue receptor 1a — in vitro. Journal of Medicinal Chemistry. https://pubmed.ncbi.nlm.nih.gov/22712585/
- Torsello A, Bresciani E, Ravelli M, et al. (2012). Novel domain-selective ACE-inhibiting activity of synthetic growth hormone secretagogues — in vitro. Pharmacological Research. https://pubmed.ncbi.nlm.nih.gov/22732396/
- Castro J, et al. (2025). Subchronic safety assessment of CIGB-500 in beagle dog after repeated daily dose administration over 28 days — animal (dog, regulatory toxicology). Regulatory Toxicology and Pharmacology. https://pubmed.ncbi.nlm.nih.gov/40024561/
- Anderson LL, Jeftinija S, Scanes CG, et al. (2005). Physiology of ghrelin and related peptides — review. Domestic Animal Endocrinology. https://pubmed.ncbi.nlm.nih.gov/15927771/
- Ostadian C, Hayati N, Zahiri Sorouri Z, Hosseini A. (2025). Assessing the effectiveness of growth hormone releasing protein-6 in improving human oocyte maturation and meiotic progression in in vitro maturation culture media — in vitro (human oocytes). International Journal of Fertility & Sterility. https://pubmed.ncbi.nlm.nih.gov/41090425/
- Dominikowski A, et al. (2026). The emerging landscape of performance-enhancing peptides modulating the GH-IGF1 axis: bridging the gap between clinical evidence and patient self-administration — review. Frontiers in Endocrinology. https://pubmed.ncbi.nlm.nih.gov/42395176/



