
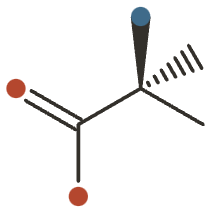
L-Alanine
A nonessential amino acid and the key nitrogen carrier of the glucose–alanine cycle; distinct from beta-alanine.

L-Alanine at a Glance
L-alanine is a non-essential amino acid — the second simplest after glycine — that the body makes readily from pyruvate. It is present in almost all protein foods.
Its defining role is as a glucose carrier. Muscle converts surplus nitrogen into alanine and ships it to the liver, which strips the nitrogen and rebuilds glucose. That shuttle runs constantly, and it is why alanine’s uses cluster around blood sugar rather than muscle building.
What It’s Used For
- Nocturnal hypoglycemia (type 1 diabetes) — raises overnight blood glucose to prevent night-time lows.
- Gluconeogenic support in glycogen storage disease — supplies glucose in disorders where glycogen cannot be released.
- Oral rehydration (alanine-fortified ORS) — improves sodium and water uptake in rehydration solutions.
- Benign prostatic hyperplasia (amino-acid blend) — used in an amino-acid blend for prostate symptoms.
How It Works
The glucose-alanine cycle is the mechanism behind most of this. Muscle transaminates pyruvate to alanine, exports it, and the liver reverses the reaction and feeds the pyruvate into gluconeogenesis — disposing of nitrogen and supplying glucose in one loop. Giving alanine directly feeds the liver end of that cycle, which is why it raises glucose slowly and steadily rather than spiking it.
In rehydration solutions the mechanism is different: alanine is co-transported with sodium across the intestinal wall, and water follows the sodium — the same principle that makes glucose-based oral rehydration work.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Alanine is a small, nonessential (dispensable) alpha-amino acid that the body synthesizes readily from pyruvate, and it is the pivotal nitrogen carrier of the glucose–alanine (Cahill) cycle — the loop by which working muscle exports amino nitrogen to the liver and the liver returns glucose. Because the body makes and recycles alanine so efficiently, almost all of the credible research concerns its physiological role or its use as a functional ingredient (a gluconeogenic substrate, a co-transported solute in rehydration fluids), not a benefit from taking it as a standalone pill in already-adequate people. The strongest human data sit in narrow clinical niches — fortified oral rehydration solutions and condition-specific hypoglycemia — and even there the results are mixed. A recurring caveat runs through the popular literature: most sports “alanine” products are actually beta-alanine, a structurally different, non-proteinogenic molecule, and evidence for one does not transfer to the other.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
L-Alanine is absorbed across the intestinal brush border by a sodium-coupled transporter, and in animal and Ussing-chamber work adding alanine to a glucose solution increases net sodium and water absorption — including in virally damaged jejunum 8,
This is the rationale for “super-ORS.” In a double-blind randomized trial in adults with severe cholera/ETEC dehydration (n=97), an alanine-plus-glucose ORS reduced stool output and ORS requirement versus standard WHO-ORS 11Reference 11RCTOral rehydration formula containing alanine and glucose for treatment of diarrhoea — randomised double-blind controlled trialView study →.
However, in acute non-cholera pediatric diarrhea the added benefit largely disappeared: a randomized infant trial found alanine ORS did not reduce purging versus standard ORS 7Reference 7RCTAlanine-based oral rehydration therapy for infants with acute diarrhea — randomised trialView study →, and a further randomized, double-blind pediatric trial of alanine ORS in acute non-cholera diarrhea likewise found no clear clinical advantage over standard ORS 12Reference 12RCTAlanine-based oral rehydration solution: assessment of efficacy in acute noncholera diarrhea among children — randomised double-blind trialView study →, while WHO’s own review of glycine-, alanine-, glutamine-, maltodextrin- and rice-based formulations concluded the amino-acid additions did not provide a reliable advantage in non-cholera diarrhea 14Reference 14Clinical trialClinical trials of improved oral rehydration salt formulations: a reviewView study →.
Interest in amino-acid ORS continues (e.g. multi-amino-acid formulations under formal trial) 15Reference 15RCTA double-blind clinical trial to compare a multiple amino acid-based ORS with standard WHO-ORS in non-cholera acute watery diarrhea — trial protocolView study →, but for the common cause of childhood diarrhea, alanine fortification has not displaced low-osmolarity glucose ORS.
Gap: benefit is real in high-purging cholera but inconsistent-to-null in the far more common non-cholera diarrhea; effect is a property of the fluid formulation, not of oral alanine taken by well people.
Because alanine is a glucagon secretagogue and gluconeogenic precursor, it has been tested as a sustained overnight glucose source. In a four-way crossover study of 15 patients with insulin-dependent diabetes, a bedtime dose of 40 g L-alanine (plus 10 g glucose, ~200 kcal) raised plasma glucose and reduced early-night hypoglycemia compared with no treatment, performing comparably to a standard snack and to terbutaline 5Reference 5RCTAlanine and terbutaline in the prevention of nocturnal hypoglycemia in IDDM — randomised crossover trialView study →.
The effect is plausible and consistent with alanine’s endocrine action 3,
Gap: one small crossover trial only; a condition-specific (disease-dependent) use at a high dose, never replicated at scale, and not a general benefit.
In disorders where hepatic glucose release is impaired (e.g. debrancher/GSD III), patients rely heavily on gluconeogenesis, and alanine is the principal gluconeogenic amino acid extracted by the liver 1,
A classic case report showed that high-protein nocturnal feeding — supplying gluconeogenic substrate — reversed myopathy, hypoglycemia and growth failure in a child with debrancher deficiency 6Reference 6Case reportReversal of debrancher deficiency myopathy by the use of high-protein nutrition — case reportView study →.
Here alanine is best understood as one component of a protein/substrate strategy rather than a proven standalone supplement.
Gap: mechanism-plus-case-report evidence in a rare disease; the intervention is high-protein nutrition, not isolated L-alanine, and none of it generalizes to healthy people.
A glycine–alanine–glutamic acid combination (“Paraprost”) was marketed decades ago for benign prostatic symptoms, with early uncontrolled reports of symptom relief 10Reference 10Palliative treatment of benign prostatic hypertrophy; value of glycine-alanine-glutamic acid combinationView study →. Later controlled work found it far weaker than an alpha-blocker: in a double-blind study prazosin improved flow rates while the amino-acid product left them essentially unchanged 13Reference 13RCTClinical evaluation of prazosin in benign prostatic obstruction; Paraprost-controlled double-blind studyView study →. This is a combination product, not standalone L-alanine, and modern urology does not use it.
Gap: old, largely uncontrolled data on a three-amino-acid blend; not isolated alanine, and outclassed by standard pharmacotherapy.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Alanine aminotransferase (ALT) / transamination | Transfers amino group between pyruvate and glutamate; interconverts alanine ⇄ pyruvate | Glucose–alanine cyclenitrogen transport |
| Hepatic gluconeogenesis | Alanine → pyruvate → glucose; principal gluconeogenic amino acid | Fasting/exercise glucose supplyGSDhypoglycemia |
| Pancreatic alpha-cell (glucagon secretion) | Alanine stimulates glucagon release | Counter-regulationhypoglycemia prevention |
| Intestinal Na⁺-coupled amino-acid transport | Co-transport of alanine with Na⁺ drives water absorption | Oral rehydration solutions |
Pharmacokinetics
Dietary and supplemental L-alanine is absorbed rapidly and near-completely in the small intestine via sodium-dependent neutral-amino-acid transporters (and, as dipeptides, via PepT1), and enters the portal circulation. It is a highly dynamic pool: plasma alanine rises with exercise as muscle exports nitrogen 2Reference 2Clinical trialChanges of free amino acids in plasma of healthy subjects induced by physical exercise — human studyView study → and falls during fasting as the liver consumes it for gluconeogenesis. Because the body synthesizes alanine from pyruvate and clears it briskly through transamination and gluconeogenesis, an oral dose does not produce a sustained, drug-like exposure — its metabolic fate is to be turned into glucose, urea nitrogen, or protein. There is no established “half-life” in the pharmacological sense; turnover is fast and tightly coupled to whole-body glucose and nitrogen flux 1,
Clinical trials
Registered/published trial activity is modest and clustered in oral rehydration and metabolic physiology; there is little industry-funded standalone-supplement trial activity, as alanine is an unpatentable dietary amino acid. Most “alanine” performance trials in registries are in fact beta-alanine studies and are not counted here.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~6–8(ORS, hypoglycemia) | 1–2(amino-acid ORS) | 0(known) | many(metabolism/transport) |
Last checked: July 2026.
Dietary Sources
L-Alanine is abundant in virtually all protein-containing foods and, unlike essential amino acids, is also synthesized by the body from pyruvate — so dietary intake is rarely a limiting factor. It is well represented in meat, poultry, fish, eggs, dairy, and in plant proteins such as legumes, soy, nuts, seeds and whole grains. Gelatin and other connective-tissue proteins are particularly rich in alanine. There is no meaningful risk of dietary deficiency in anyone eating adequate protein.
| Food group | Typical alanine content | Notes |
|---|---|---|
| Meat, poultry, fish | High | ~1–1.5 g per 100 g cooked protein-rich portion |
| Eggs, dairy | Moderate–high | Complete protein; steady contributor |
| Legumes, soy | Moderate–high | Main plant source |
| Nuts, seeds, whole grains | Moderate | Contributes across a mixed diet |
| Gelatin / collagen | Very high | One of the more alanine-dense proteins |
Amounts are approximate; alanine tracks total protein intake. Because the body synthesizes alanine, dietary supply is not considered rate-limiting in health. (No dedicated NIH ODS fact sheet exists for individual nonessential amino acids.)
Dosage
There is no RDA, Adequate Intake, or Tolerable Upper Intake Level for L-alanine — as a nonessential amino acid it is not assigned a dietary reference value, and adequacy is met through ordinary dietary protein. Standalone L-alanine supplementation is uncommon; the amino acid mainly appears within complete-protein powders, amino-acid blends, and clinical/parenteral nutrition. The largest doses in the research literature are experimental rather than recommended: e.g. a single bedtime dose of ~40 g was used to study nocturnal hypoglycemia in type 1 diabetes 5Reference 5RCTAlanine and terbutaline in the prevention of nocturnal hypoglycemia in IDDM — randomised crossover trialView study →, and alanine has been added to oral rehydration fluids at defined millimolar concentrations (e.g. 30–90 mmol/L) 7,
These are doses studied in research, not a personal recommendation. For general health there is no evidence that supplementing L-alanine on top of an adequate-protein diet confers benefit.
Safety
L-Alanine is a normal constituent of dietary protein with no meaningful toxicity at food levels. The most important practical caution is identity, not toxicity — it is routinely confused with beta-alanine, a different molecule with a different side-effect profile.
- Safe at dietary levels. A normal constituent of dietary protein, generally regarded as safe from food.
- No established drug interactions. It is not a substrate or inhibitor of the major drug-metabolizing pathways.
- Do not confuse it with beta-alanine. The tingling (paraesthesia) that beta-alanine causes does not apply to L-alanine.
- Care with hepatic or renal impairment. Limited capacity to handle a nitrogen load means large amino-acid doses warrant clinical guidance.
- High-dose, long-term safety uncharacterized. The ~40 g research doses were acute, and no upper limit has been set.
Full Safety & Interactions Detail
L-Alanine is a normal constituent of dietary protein and is generally regarded as safe at the levels obtained from food. Standalone supplementation is uncommon, so high-quality safety and dose-limiting data are sparse; the large experimental doses used in hypoglycemia research (~40 g) were given acutely without reported serious adverse effects, but long-term high-dose safety has not been characterized. The most important practical caution is one of identity, not toxicity: L-alanine is frequently confused with beta-alanine, a different molecule whose hallmark side effect (paraesthesia — skin tingling) does not apply to L-alanine. As with any amino acid, people with significant hepatic or renal impairment — who have limited capacity to handle nitrogen loads — should be cautious with large supplemental amino-acid doses and seek clinical guidance. Anyone considering supplementation for a medical condition (e.g. glycemic management) should consult a qualified healthcare professional, as this is not a self-treatment context.
Scope disclosure (REQUIRED honesty — not a claim, no citation):
- Interactions assessed? Partially — no clinically significant drug interactions are established for L-alanine; it is not a substrate/inhibitor of major drug-metabolizing pathways. Formal interaction studies are lacking.
- Pregnancy/lactation assessed? Not formally in a supplemental context — safe as a dietary component; no trials of isolated supplementation.
- Upper Limit (UL) established? No UL set. Absence of a UL does not imply that unlimited intake is safe; it reflects that the compound has not been formally evaluated for one.
Never imply safety from absence of reports. Where it wasn’t studied, it is marked “not assessed.”
Verdict: no specific safety concern at dietary levels; no data to support standalone high-dose supplementation. L-Alanine from food is part of normal maternal and fetal amino-acid metabolism and poses no known risk. There is no evidence base for taking isolated L-alanine supplements during pregnancy or breastfeeding, so supplementation beyond dietary intake is not advised without medical supervision.
References
- Felig, P. (1973). The glucose-alanine cycle — review. Metabolism. https://pubmed.ncbi.nlm.nih.gov/4567003/
- Brodan, V., et al. (1976). Changes of free amino acids in plasma of healthy subjects induced by physical exercise — human study. Eur J Appl Physiol Occup Physiol. https://pubmed.ncbi.nlm.nih.gov/1253785/
- Müller, W. A., et al. (1971). The effect of alanine on glucagon secretion — animal/human study. J Clin Invest. https://pubmed.ncbi.nlm.nih.gov/5116210/
- Martineau, A., et al. (1985). Simultaneous determination of glucose turnover, alanine turnover, and gluconeogenesis in humans — stable-isotope tracer study. Anal Biochem. https://pubmed.ncbi.nlm.nih.gov/3913335/
- Saleh, T. Y., & Cryer, P. E. (1997). Alanine and terbutaline in the prevention of nocturnal hypoglycemia in IDDM — randomised crossover trial. Diabetes Care. https://pubmed.ncbi.nlm.nih.gov/9250445/
- Slonim, A. E., et al. (1982). Reversal of debrancher deficiency myopathy by the use of high-protein nutrition — case report. Ann Neurol. https://pubmed.ncbi.nlm.nih.gov/7049057/
- Ribeiro Júnior, H. da C., & Lifshitz, F. (1991). Alanine-based oral rehydration therapy for infants with acute diarrhea — randomised trial. J Pediatr. https://pubmed.ncbi.nlm.nih.gov/2007961/
- Rhoads, J. M., et al. (1986). Alanine enhances jejunal sodium absorption in the presence of glucose — animal study. Pediatr Res. https://pubmed.ncbi.nlm.nih.gov/3018659/
- Sarker, S. A., et al. (1995). Alanine- and glucose-based hypo-osmolar oral rehydration solution in infants with persistent diarrhoea — randomised controlled trial. Acta Paediatr. https://pubmed.ncbi.nlm.nih.gov/7549296/
- Feinblatt, H. M., & Gant, J. C. (1958). Palliative treatment of benign prostatic hypertrophy; value of glycine-alanine-glutamic acid combination. J Maine Med Assoc. https://pubmed.ncbi.nlm.nih.gov/13514330/
- Patra, F. C., et al. (1989). Oral rehydration formula containing alanine and glucose for treatment of diarrhoea — randomised double-blind controlled trial. BMJ. https://pubmed.ncbi.nlm.nih.gov/2502251/
- Sazawal, S., et al. (1991). Alanine-based oral rehydration solution: assessment of efficacy in acute noncholera diarrhea among children — randomised double-blind trial. J Pediatr Gastroenterol Nutr. https://pubmed.ncbi.nlm.nih.gov/1865280/
- Yamaguchi, O., et al. (1990). Clinical evaluation of prazosin in benign prostatic obstruction; Paraprost-controlled double-blind study. Urol Int. https://pubmed.ncbi.nlm.nih.gov/1690481/
- Bhan, M. K., et al. (1994). Clinical trials of improved oral rehydration salt formulations: a review. Bull World Health Organ. https://pubmed.ncbi.nlm.nih.gov/7867142/
- Das, R., et al. (2022). A double-blind clinical trial to compare a multiple amino acid-based ORS with standard WHO-ORS in non-cholera acute watery diarrhea — trial protocol. Trials. https://pubmed.ncbi.nlm.nih.gov/36008819/



