
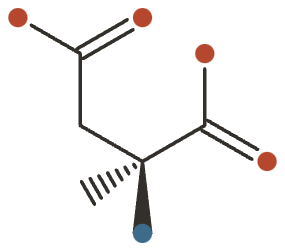
L-Aspartic Acid
L-Aspartic acid is a nonessential amino acid involved in the urea cycle, the TCA cycle, nucleotide synthesis and neurotransmission.

L-Aspartic Acid at a Glance
L-Aspartic acid (aspartate) is a nonessential, proteinogenic amino acid that sits at several metabolic crossroads — the urea cycle, the TCA cycle, nucleotide synthesis — and doubles as a weak excitatory neurotransmitter. The body makes it freely, and any protein-containing meal supplies it in grams. There is no deficiency to correct.
The most important thing here is a distinction. Almost all the supplement interest in “aspartic acid” belongs to two things that are not L-aspartic acid:
- D-aspartic acid, the mirror-image enantiomer, sold as a testosterone booster. Different molecule. The better-controlled trials in trained men are null, and one found testosterone went down.
- Aspartate salts — magnesium, potassium, zinc, arginine aspartate — where aspartate is the counter-ion carrying a mineral, and the mineral is the point.
Where aspartate genuinely earns its keep is that second role, quietly: it is a well-absorbed mineral carrier. Magnesium aspartate absorbs far better than magnesium oxide. That is the one durable, replicated finding here, and it is not about aspartate being active at all.
What It’s Used For
- Testosterone & muscle (D-aspartic acid) — the marketed use, the weakest evidence, and the wrong enantiomer.
- Anti-fatigue & endurance (aspartate salts) — a 1960s idea that better-controlled trials did not support.
Standalone L-aspartic acid is otherwise rarely supplemented, and there is no established rationale for doing so in a well-fed person.
How It Works
Aspartate’s negatively charged side chain makes it common in enzyme active sites, and its metabolic roles follow from being a cheap, interconvertible source of nitrogen and carbon:
It donates nitrogen to the urea cycle for ammonia disposal — which is the origin of the “anti-fatigue” idea, since exercise raises blood ammonia. It interconverts with oxaloacetate in the TCA cycle and drives the malate–aspartate shuttle that moves reducing equivalents into mitochondria. And it supplies backbone atoms for purine and pyrimidine synthesis.
In the nervous system L-aspartate is a weak excitatory transmitter at NMDA-type receptors — a physiological role, not a supplement effect.
The D-enantiomer is a separate story: D-aspartate accumulates in neuroendocrine tissue and Leydig cells, where it modulates hormone release 8Reference 8ReviewD-Aspartic acid: an endogenous amino acid with an important neuroendocrine role — reviewView study →. That mechanism is real; whether it translates into a useful testosterone effect in a training adult is what the trials below test, and mostly answer no.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Aspartic acid (aspartate) is a nonessential, proteinogenic amino acid that the body makes freely and obtains in gram quantities from any protein-containing meal, so unlike a vitamin or an essential amino acid it has no “deficiency” to correct and no established rationale for standalone supplementation in a well-fed person. Almost all of the supplement interest sits in two places that are easy to confuse with L-aspartic acid but are not the same thing: the mirror-image D-enantiomer (D-aspartic acid) sold as a testosterone booster, and aspartate salts (magnesium, potassium, arginine aspartate) used as mineral carriers or “anti-fatigue” ergogenics. The evidence in both is weak — the D-aspartic acid testosterone signal largely disappears in resistance-trained men, and the aspartate-salt ergogenic claims trace back to older, poorly-replicated work. Where aspartate does earn its place is quietly, as a well-absorbed counter-ion for minerals rather than as an active ingredient in its own right.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the D-enantiomer, D-aspartic acid (D-Asp) — a distinct molecule from the dietary L-aspartic acid described here, though the two are routinely conflated in marketing. A systematic review of 4 human and 23 animal studies found the effect strongly dependent on species, dose and training status, with animal and untrained-human data more favourable than trained-human data 1Reference 1Systematic reviewThe putative effects of D-aspartic acid on blood testosterone levels: a systematic review — systematic reviewView study →.
In resistance-trained men the controlled trials are unconvincing. 28 days of 3 g/day D-Asp with heavy training produced no change in testosterone, strength or body composition versus placebo 2Reference 2RCTD-aspartic acid supplementation combined with 28 days of heavy resistance training has no effect on body composition, muscle strength, and serum hormones — randomised controlled trialView study →.
A 3-month randomised, double-blind RCT (6 g/day, n=22) found no benefit and if anything a reduction in testosterone 3Reference 3RCTThe effects of d-aspartic acid supplementation in resistance-trained men over a three month training period — randomised controlled trialView study →.
A dose-ranging study (3 vs 6 g/day) in trained men likewise showed no meaningful hormonal gain 6Reference 6RCTThree and six grams supplementation of d-aspartic acid in resistance trained men — randomised trialView study →.
A 2025 RCT in idiopathic male infertility reported improvements when D-Asp was combined with zinc and coenzyme Q10, but the combination design means the effect can’t be pinned on D-Asp alone 7Reference 7RCTEvaluation of D-aspartic acid, zinc and coenzyme Q10 in idiopathic male infertility — randomised controlled trialView study →.
Gap: the marketed use — boosting testosterone in healthy, training men — is where the evidence is weakest and mostly null; and none of it involves the L-aspartic acid actually supplied by food and protein powders.
Potassium and magnesium aspartate were promoted from the 1960s as “anti-fatigue” agents, with early reports of improved endurance attributed to lowering exercise-induced blood ammonia. Better-controlled work did not hold up: a double-blind crossover in 8 men found 6 g of potassium-magnesium aspartate produced no difference in time to exhaustion, blood glucose, lactate or ammonia versus placebo 5Reference 5Clinical trialThe effects of oral administration of salts of aspartic acid on the metabolic response to prolonged exhausting exercise — controlled clinical trialView study →.
Arginine aspartate (where the ergogenic rationale really belongs to arginine, not aspartate) reduced exercise-induced hyperammonaemia in one small crossover but without a clear performance payoff 9Reference 9RCTEffect of arginine aspartate on the exercise-induced hyperammoniemia in humans: a two-period crossover trial — randomised controlled trialView study →, and chronic supplementation in marathon runners mainly lowered resting plasma amino acid levels rather than improving performance 10Reference 10RCTChronic arginine aspartate supplementation in runners reduces total plasma amino acid level at rest and during a marathon run — randomised controlled trialView study →.
The aspartate here is a salt counter-ion; the human ergogenic signal is small and inconsistent.
Gap: no replicated performance benefit in adequately-controlled trials, and the studied compounds are salts or combinations rather than L-aspartic acid on its own.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Urea cycle (argininosuccinate synthesis) | Donates nitrogen for ammonia disposal | Ammonia handling; basis of “anti-fatigue” claims |
| TCA cycle / malate–aspartate shuttle | Interconverts with oxaloacetate; shuttles reducing equivalents into mitochondria | Energy metabolism; ergogenic rationale |
| Purine & pyrimidine synthesis | Backbone nitrogen/carbon donor for nucleotides | Cell proliferation (endogenous role) |
| NMDA / excitatory receptors | L-aspartate acts as a weak excitatory neurotransmitter | CNS signalling (physiologicalnot a supplement effect) |
| GnRH / testosterone release (D-enantiomer) | D-Asp accumulates in neuroendocrine tissue and Leydig cells, modulating hormone release | D-aspartic acid testosterone claims |
Pharmacokinetics
Dietary and supplemental aspartate is absorbed in the small intestine and largely transaminated on first pass, so plasma aspartate is tightly regulated and rises little even after a substantial oral load — a 20 mg/kg aspartame dose (which delivers aspartate) produced no measurable increase in plasma aspartate concentration 11Reference 11RCTBioavailability of phenylalanine and aspartate from aspartame (20 mg/kg) in capsules and solution — randomised crossoverView study →. This tight homeostasis is a large part of why oral L-aspartic acid has little systemic pharmacology to exploit.
The decision-relevant PK fact is about aspartate as a mineral carrier: magnesium aspartate showed bioavailability comparable to magnesium chloride and lactate and far better than magnesium oxide, whose fractional absorption was around 4% 4Reference 4Bioavailability of US commercial magnesium preparations — comparative studyView study →, and renal-elimination studies place organic magnesium salts including aspartate above the inorganic oxide 12Reference 12RCTRenal elimination of magnesium as a parameter of bioavailability of oral magnesium therapy — randomised controlled trialView study →. As with all minerals, fractional absorption falls as dose rises, favouring split dosing. D-aspartic acid is cleared in part by D-aspartate oxidase, which may cap how much accumulates with chronic dosing.
Clinical trials
Registered-trial activity is modest and concentrated in sports nutrition (D-aspartic acid) and older aspartate-salt fatigue studies. L-aspartic acid is off-patent, cheap and dietary, so there is little industry incentive for large trials of the isolated molecule.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~8(small) | 1–2 | 0 | ~30(mostly animal D-Asp) |
Last checked: July 2026.
Dietary Sources
Aspartate is one of the most abundant amino acids in dietary protein, so intake is measured in grams per day from ordinary food and no supplement is required. It is especially concentrated in high-protein animal and plant foods, and asparagus — from which the related asparagine was first isolated — is a notable vegetable source. There is no RDA because the body synthesises it readily and dietary protein supplies far more than any physiological requirement.
| Food (typical serving) | Approx. aspartate/aspartic acid |
|---|---|
| Meat, poultry, fish (100 g) | ~1.5–2.5 g |
| Eggs (2 large) | ~1.2 g |
| Legumes / soy (100 g cooked) | ~1–2 g |
| Dairy (250 mL milk) | ~0.6 g |
| Asparagus, sprouts (100 g) | ~0.2–0.5 g |
Aspartate is also ingested as part of the sweetener aspartame (L-aspartyl-L-phenylalanine methyl ester), which is hydrolysed to release it. Even so, plasma aspartate does not rise appreciably after typical doses, because of that tight homeostatic regulation 11Reference 11RCTBioavailability of phenylalanine and aspartate from aspartame (20 mg/kg) in capsules and solution — randomised crossoverView study →. Nothing in normal cooking or food processing meaningfully depletes aspartate.
Intake & Dosage
These are doses studied in research, not a personal recommendation.
There is no RDA, Adequate Intake, or Tolerable Upper Intake Level for aspartic acid — it is nonessential and abundantly supplied by dietary protein.
Standalone L-aspartic acid is rarely supplemented on its own. The doses that appear in the literature are almost entirely for something else:
- The D-enantiomer, in sports-nutrition trials at 3–6 g/day — where the results are largely
null in trained men 2,
3, .6Reference 2RCTD-aspartic acid supplementation combined with 28 days of heavy resistance training has no effect on body composition, muscle strength, and serum hormones — randomised controlled trialView study →Reference 3RCTThe effects of d-aspartic acid supplementation in resistance-trained men over a three month training period — randomised controlled trialView study →Reference 6RCTThree and six grams supplementation of d-aspartic acid in resistance trained men — randomised trialView study → - Aspartate salts used as mineral carriers, where the relevant dose is that of the mineral (e.g. elemental magnesium), not the aspartate.
As with all minerals delivered as aspartate salts, fractional absorption falls as dose rises, so split dosing with food is sensible.
Safety
L-aspartic acid is well tolerated as a normal dietary component and is Generally Recognised As Safe in its common food-additive contexts. What is not characterised is the isolated, concentrated supplement.
- Safe as a dietary component. GRAS in its common food-additive contexts; unavoidable in any protein-containing diet.
- Isolated high doses are unstudied long-term. Concentrated supplemental L- or D-aspartic acid has no long-term safety record.
- GI upset at gram-level doses. The most common practical issue with amino-acid or mineral-salt loading.
- Aspartate salts carry their mineral’s interactions. Potassium aspartate with potassium-sparing diuretics or ACE inhibitors raises hyperkalaemia risk; magnesium salts interact with certain antibiotics.
- No upper limit is set. Absence of a UL is not evidence that unlimited intake is safe.
Full Safety & Interactions Detail
Concentrated supplemental doses of the isolated amino acid have not been studied for long-term safety. Because aspartate is an excitatory (NMDA-type) neurotransmitter there is a longstanding theoretical concern about excitotoxicity at very high intakes, though this has not been demonstrated at dietary or ordinary supplemental levels. The most common practical issue is gastrointestinal upset from gram-level amino-acid or mineral-salt doses.
- Interactions: no clinically significant drug interactions are documented for dietary L-aspartic acid. Aspartate salts carry the interaction profile of their mineral — potassium aspartate with potassium-sparing diuretics or ACE inhibitors (hyperkalaemia risk), magnesium salts with certain antibiotics. Interactions of isolated high-dose L- or D-aspartic acid have not been systematically studied.
- Phenylketonuria: aspartate is a component of aspartame, and people with PKU must avoid aspartame — but that restriction is driven by its phenylalanine content, not its aspartate.
Scope disclosure. Interactions were assessed partially, as described above. Pregnancy and lactation were not assessed for supplemental doses — no dedicated data exist, though dietary intake is safe. No Upper Limit has been set, and absence of one does not mean unlimited intake is safe; long-term high-dose safety is simply unstudied. Where something was not studied, it is marked “not assessed,” not “safe.”
Not established — concentrated supplements are not recommended in the absence of data. Aspartate from a normal diet is safe and unavoidable in pregnancy. Isolated high-dose L-aspartic acid or D-aspartic acid supplements have not been evaluated for safety in pregnancy or lactation, and should not be used without medical advice.
References
- Roshanzamir F, et al. (2017). The putative effects of D-aspartic acid on blood testosterone levels: a systematic review — systematic review. International Journal of Reproductive BioMedicine. https://pubmed.ncbi.nlm.nih.gov/28280794/
- Willoughby DS, Leutholtz B (2013). D-aspartic acid supplementation combined with 28 days of heavy resistance training has no effect on body composition, muscle strength, and serum hormones — randomised controlled trial. Nutrition Research. https://pubmed.ncbi.nlm.nih.gov/24074738/
- Melville GW, et al. (2017). The effects of d-aspartic acid supplementation in resistance-trained men over a three month training period — randomised controlled trial. PLoS One. https://pubmed.ncbi.nlm.nih.gov/28841667/
- Firoz M, Graber M (2001). Bioavailability of US commercial magnesium preparations — comparative study. Magnesium Research. https://pubmed.ncbi.nlm.nih.gov/11794633/
- Maughan RJ, Sadler DJ (1983). The effects of oral administration of salts of aspartic acid on the metabolic response to prolonged exhausting exercise — controlled clinical trial. International Journal of Sports Medicine. https://pubmed.ncbi.nlm.nih.gov/6874173/
- Melville GW, et al. (2015). Three and six grams supplementation of d-aspartic acid in resistance trained men — randomised trial. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/25844073/
- GamalEl Din SF, et al. (2025). Evaluation of D-aspartic acid, zinc and coenzyme Q10 in idiopathic male infertility — randomised controlled trial. Archivio Italiano di Urologia e Andrologia. https://pubmed.ncbi.nlm.nih.gov/40248985/
- D’Aniello A (2007). D-Aspartic acid: an endogenous amino acid with an important neuroendocrine role — review. Brain Research Reviews. https://pubmed.ncbi.nlm.nih.gov/17118457/
- Denis C, et al. (1991). Effect of arginine aspartate on the exercise-induced hyperammoniemia in humans: a two-period crossover trial — randomised controlled trial. Archives Internationales de Physiologie, de Biochimie et de Biophysique. https://pubmed.ncbi.nlm.nih.gov/1713484/
- Colombani PC, et al. (1999). Chronic arginine aspartate supplementation in runners reduces total plasma amino acid level at rest and during a marathon run — randomised controlled trial. European Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/10784382/
- Burns TS, Stargel WW, Hurwitz A, et al. (1990). Bioavailability of phenylalanine and aspartate from aspartame (20 mg/kg) in capsules and solution — randomised crossover. Metabolism. https://pubmed.ncbi.nlm.nih.gov/2233283/
- Kuhn I, et al. (1992). Renal elimination of magnesium as a parameter of bioavailability of oral magnesium therapy — randomised controlled trial. Methods and Findings in Experimental and Clinical Pharmacology. https://pubmed.ncbi.nlm.nih.gov/1507928/



