
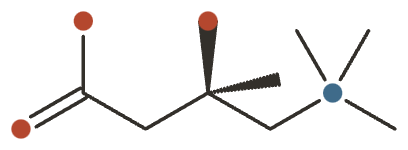
L-Carnitine
A conditionally-essential, amino-acid-derived compound that shuttles fatty acids into mitochondria for energy — genuinely useful for correcting a deficit, much weaker as a fat-burner.

L-Carnitine at a Glance
L-carnitine is a conditionally-essential compound, built from the amino acids lysine and methionine, whose defining job is to ferry long-chain fatty acids into mitochondria so they can be burned for energy. Its name comes from carnis — flesh — because it was first isolated from meat, which remains by far its richest dietary source.
The body makes its own supply and recycles it efficiently through the kidneys, so healthy adults eating an ordinary diet are normally replete without supplementing. That single fact sets the ceiling on what supplementation can be expected to do, and it is the sentence most carnitine marketing leaves out.
Pharmacologically, this is a deficiency-correction molecule first and a performance molecule a distant second. Where a genuine carnitine deficit exists — inborn transporter disease, dialysis, valproate therapy — replacement works and is established medicine. Where it doesn’t, you are adding more of something the body already has enough of, and the returns fall off sharply.
The honest bottom line: excellent for repletion, modest and form-specific for circulatory and nerve indications, and largely oversold as a fat-burner.
What It’s Used For
Ranked by how well the evidence actually holds up:
- Correcting carnitine deficiency — restores tissue carnitine in inborn errors, dialysis and drug-induced depletion. Established replacement therapy, not a discretionary supplement.
- Dialysis-related depletion — improves left-ventricular function and reduces intradialytic hypotension in a population that is genuinely depleted.
- Intermittent claudication — the propionyl form increases pain-free walking distance in peripheral arterial disease. Modest, form-specific, an adjunct rather than a replacement for exercise therapy.
- Male fertility — improves sperm motility and concentration; the endpoints couples care about, pregnancy and live birth, are not reliably improved.
- Diabetic neuropathy — the acetyl form (ALCAR) reduces neuropathic pain, on low-certainty evidence.
- Weight and fat loss — around 1.2–1.3 kg over months, concentrated in people who were overweight or depleted to begin with.
Be sceptical of the two claims that sell the most product: “fat burner” and “energy”. Carnitine is required for fat oxidation, but supplying extra to someone who already has enough does not meaningfully accelerate it — and in healthy people, muscle carnitine barely moves without weeks of dosing alongside carbohydrate. The cognitive claim is similar: the positive trials are old, used ALCAR, and studied people with mild cognitive impairment, not healthy users looking for an edge.
How It Works
Carnitine is a shuttle. Long-chain fatty acids cannot cross the inner mitochondrial membrane on their own; carnitine binds them and carries them through via the CPT-I / CACT / CPT-II transport system, delivering them to β-oxidation — the pathway that turns fat into usable energy. Tissues that run heavily on fat, especially heart and skeletal muscle, depend on this most.
A second, less advertised job matters for the exercise story: carnitine buffers acetyl-CoA. When metabolism generates acetyl groups faster than the Krebs cycle consumes them, carnitine exports the excess as acetylcarnitine, freeing up CoA for other reactions. This is why carnitine status affects metabolic flexibility rather than raw fuel supply.
The forms differ by which of these jobs they favour. The acetyl form carries an acetyl group and crosses into the brain more readily, which is the rationale for its use in nerve and cognitive indications. The propionyl form’s propionyl group feeds the Krebs cycle directly through anaplerosis, which is why it is the form studied in ischaemic muscle and claudication.
Absorption is the recurring limiter, and it cuts against the marketing: dietary carnitine is roughly 54–87% absorbed, supplemental carnitine only about 14–18%. The rest is fermented by gut bacteria — which is where the TMAO question in the Safety section comes from.
Pharmacology & Research
L-carnitine is a conditionally-essential, amino-acid-derived quaternary amine (biosynthesised from lysine and methionine) whose defining biochemical job is to shuttle long-chain fatty acids across the inner mitochondrial membrane for β-oxidation. The evidence splits cleanly along a single fault line: correcting a genuine carnitine deficit — inborn OCTN2/transporter disease, dialysis-related depletion, some drug- and diet-induced states — is well grounded, whereas the popular “fat-burner and energiser” framing in healthy, carnitine-replete people rests on much weaker data. Form matters more here than for most supplements: acetyl-L-carnitine (ALCAR) is the brain-penetrant form studied for cognition and neuropathy, propionyl-L-carnitine (PLC) is the form studied for circulatory disease, and L-carnitine L-tartrate (LCLT) is the exercise-recovery form. Bioavailability is the recurring limiter — oral supplements are only ~14–18% absorbed against a background where dietary carnitine is ~54–87% absorbed, so blood-level changes are modest and tissue loading is slow.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume, then tempered for consistency, form/bioavailability, and how far a benefit depends on pre-existing deficiency. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
The one indisputably established use. In primary carnitine deficiency (OCTN2/SLC22A5 transporter defects) and secondary deficiency (valproate and some other drugs, chronic kidney disease, certain organic acidemias, prolonged parenteral nutrition), oral or intravenous levocarnitine restores tissue carnitine and can reverse the associated cardiomyopathy, skeletal myopathy, and hypoketotic hypoglycaemia 1,
This is FDA-approved replacement therapy, not a discretionary supplement, and the benefit is a direct consequence of correcting a measurable deficit.
Gap: the benefit is entirely deficiency-dependent — it says nothing about supplementation in people with normal carnitine status, which describes most supplement buyers.
The best circulatory evidence is for propionyl-L-carnitine (PLC), whose propionyl group also feeds the Krebs cycle in ischaemic muscle. Multiple double-blind RCTs found PLC (typically 1–2 g/day, oral or IV) increased pain-free and maximum walking distance versus placebo in Fontaine stage II peripheral arterial disease 4,
A Cochrane review concluded PLC may improve walking distance but rated the certainty of evidence as limited by heterogeneity and older trial methodology 17Reference 17Systematic reviewPropionyl-L-carnitine for intermittent claudication — Cochrane systematic reviewView study →.
Gap: benefit is form-specific to PLC (not plain L-carnitine), effect sizes vary widely between trials, and it is a symptomatic adjunct — it does not replace exercise therapy or revascularisation.
A 2013 systematic review and meta-analysis of 13 controlled trials (N=3,629) reported that L-carnitine after acute myocardial infarction was associated with a 27% reduction in all-cause mortality (RR 0.78, 95% CI 0.60–1.00), a 65% reduction in ventricular arrhythmias, and a 40% reduction in angina versus control 10Reference 10Meta-analysisL-carnitine in the secondary prevention of cardiovascular disease — systematic review and meta-analysis (13 trials, N=3,629)View study →. Separate meta-analyses suggest symptomatic and ejection-fraction benefits in chronic heart failure 18Reference 18Meta-analysisEfficacy and safety of L-carnitine treatment for chronic heart failure — meta-analysisView study →.
Gap: the mortality signal rests on older, mostly small and pre-reperfusion-era trials; no large modern RCT has confirmed it, so it remains hypothesis-generating rather than practice-changing.
Meta-analyses of L-carnitine/acetyl-L-carnitine in idiopathic male subfertility report improvements in sperm concentration, total and progressive motility 6,
Gap: the hard endpoints patients care about — clinical pregnancy and live birth — are not reliably improved; trials are small, heterogeneous, and often combine carnitine with other antioxidants, so its independent contribution is uncertain.
Acetyl-L-carnitine (ALCAR) has been trialled for diabetic peripheral neuropathy on the rationale that it supports nerve-fibre regeneration. Pooled RCTs and a large multicentre trial reported reductions in neuropathic pain and improvements in nerve-fibre regeneration and vibratory perception, most evident at higher doses (~2–3 g/day) 8,
Gap: effects are modest and the evidence is low-certainty; benefit appears greatest in earlier, less-established neuropathy, and results have not been consistently replicated in recent high-quality trials.
This is the mass-market claim, and the data are unimpressive. A meta-analysis of 9 RCTs (n=911) found carnitine users lost on average 1.33 kg more than controls (95% CI −2.09 to −0.57) with a small BMI reduction 11Reference 11Meta-analysisThe effect of (L-)carnitine on weight loss in adults — systematic review and meta-analysisView study →; a larger 37-RCT dose–response meta-analysis found −1.21 kg 12Reference 12Meta-analysisEffects of L-carnitine on weight loss and body composition — systematic review, meta-analysis and dose-response (37 RCTs)View study →. Effects concentrate in people who are overweight/obese or older, where baseline carnitine may be lower.
Gap: ~1 kg over months is marginal, benefit is diluted or absent in lean, replete individuals, and the “burns fat / boosts metabolism” mechanism does not translate into meaningful body-composition change in healthy people.
Small RCTs of oral acetyl-L-carnitine in hepatic encephalopathy report reductions in blood ammonia and improvements in cognitive and neuropsychiatric scores 21Reference 21RCTAcetyl-L-carnitine improves cognitive functions in severe hepatic encephalopathy — RCTView study →. A Cochrane review acknowledged possible benefit on some outcomes but rated the evidence very low certainty and flagged that trials come largely from a single research group 22Reference 22Systematic reviewAcetyl-L-carnitine for patients with hepatic encephalopathy — Cochrane systematic reviewView study →.
Gap: the evidence base is small, concentrated, and low-certainty; ALCAR is not established standard care and should not displace lactulose/rifaximin.
A 2003 meta-analysis of double-blind RCTs found a significant benefit of ALCAR (1.5–3 g/day, 3–12 months) over placebo in mild cognitive impairment and early Alzheimer’s disease 23Reference 23Meta-analysisMeta-analysis of double-blind RCTs of acetyl-L-carnitine in mild cognitive impairment and early Alzheimer’s diseaseView study →. That signal is genuine but dated, and enthusiasm has cooled as newer, larger trials failed to confirm a robust effect; evidence in healthy people seeking a “nootropic” edge is essentially absent.
Gap: the positive data are old, in clinically impaired (not healthy) populations, and not replicated by modern trials — the everyday “brain-boost” use is unsupported.
L-carnitine L-tartrate (LCLT) at ~2 g/day improved biochemical markers of post-exercise recovery (reduced muscle damage and hypoxic stress markers) and modulated androgen-receptor responses in small crossover trials 24,
Gap: performance benefits are small and inconsistent in replete athletes, the recovery data come from small trials, and raising muscle carnitine at all requires prolonged co-ingestion with carbohydrate to drive insulin-mediated uptake.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Carnitine shuttle (CPT-I/CPT-II, CACT) | Transports long-chain fatty acids into mitochondria for β-oxidation | Deficiency correctionenergy metabolismall uses |
| Mitochondrial acetyl-CoA/CoA buffering | Exports excess acetyl groups as acetylcarnitine, freeing CoA | Exercise metabolismmetabolic flexibility |
| OCTN2 (SLC22A5) transporter | Active tissue uptake of carnitine; defective in primary deficiency | Primary/secondary deficiency syndromes |
| Propionyl → succinyl-CoA (anaplerosis) | Feeds Krebs cycle in ischaemic muscle (PLC form) | Intermittent claudicationcardiac ischaemia |
| Neurotrophic / cholinergic support (acetyl form) | Acetyl donor; NGF signalling, membrane repair | Diabetic neuropathycognition (ALCAR) |
| Gut microbiota (TMA lyase, CutC/gbu) | Converts unabsorbed carnitine to TMA → hepatic TMAO | TMAO/cardiovascular safety question |
Pharmacokinetics
Absorption is the decision-relevant fact. Dietary carnitine is ~54–87% bioavailable, but oral supplemental carnitine is only ~14–18% absorbed, the rest being metabolised by gut bacteria 26,
Clinical trials
L-carnitine has been studied for decades across cardiology, nephrology, andrology and neurology, but it is an off-patent, inexpensive molecule with little commercial incentive for large modern confirmatory trials — so much of the pivotal cardiovascular evidence dates to the 1990s–2000s. Registered-trial activity continues mostly in dialysis, fertility, metabolic and small nutraceutical studies rather than large outcome trials.
| Completed | Ongoing / planned | Terminated / withdrawn | Total registered |
|---|---|---|---|
| 233 | 61 | 42 | 416 |
Counts from ClinicalTrials.gov (query: “L-carnitine OR levocarnitine OR acetyl-L-carnitine”). Last checked: August 2026.
Forms of L-Carnitine
The forms differ enough in absorption, target tissue and studied use to be treated as distinct — but the differences are about which tissue and which use, not dramatic potency gaps. All deliver the same core carnitine molecule.
| Form | What’s different | Absorption | Best studied for |
|---|---|---|---|
| L-Carnitine (base) | The parent molecule | ~14–18% oral | General/metabolic use, deficiency |
| Acetyl-L-carnitine (ALCAR) | Acetylated; more brain-penetrant, provides an acetyl group | Somewhat better absorbed than base | Cognition, diabetic neuropathy, mood |
| Propionyl-L-carnitine (PLC) | Propionyl group feeds the Krebs cycle in ischaemic muscle | Well absorbed | Intermittent claudication, cardiac ischaemia |
| L-Carnitine L-tartrate (LCLT) | L-carnitine bound to tartaric acid; fast-dissolving | Rapidly absorbed | Exercise recovery, resistance training |
Honesty note: these are genuinely different use-cases, not marketing tiers — but no form is a dramatically superior “absorber,” and the base molecule is adequate for correcting deficiency. Match the form to the goal (ALCAR → brain/nerve; PLC → circulation; LCLT → exercise), not to absorption hype.
Dietary Sources
Carnitine is overwhelmingly an animal-food nutrient — its name comes from carnis (flesh). Red meat is by far the richest source, with poultry, fish and dairy contributing smaller amounts, and plant foods almost none. Healthy adults obtain roughly 60–180 mg/day from an omnivorous diet and synthesise the rest endogenously from lysine and methionine, so dietary intake and body stores are normally adequate without supplements.
| Food | Carnitine (approx.) |
|---|---|
| Beef steak (100 g, cooked) | ~55–100 mg |
| Ground beef (100 g) | ~85–95 mg |
| Pork (100 g) | ~20–30 mg |
| Fish, cod (100 g) | ~5–6 mg |
| Chicken breast (100 g) | ~3–5 mg |
| Milk (whole, 250 mL) | ~8 mg |
| Cheese (cheddar, 60 g) | ~1–2 mg |
| Bread, asparagus, avocado | <1–2 mg |
Values approximate; content varies with cut and cooking. Because absorption of dietary carnitine (~54–87%) is much higher than of supplemental carnitine (~14–18%), a meat-eating diet is an efficient source, while strict vegetarians and vegans have lower intakes and lower plasma carnitine — though they typically remain clinically sufficient through increased renal conservation and endogenous synthesis 26Reference 26ReviewKinetics, pharmacokinetics, and regulation of L-carnitine and acetyl-L-carnitine metabolism — reviewView study →.
Dosage
There is no RDA or Adequate Intake for carnitine and no Tolerable Upper Intake Level — it is conditionally essential, meaning healthy people make enough themselves. The figures below are doses studied in research, not a personal recommendation.
- General supplemental range: 500–2,000 mg/day of L-carnitine, usually split into 2 doses to offset the fall in fractional absorption at higher single doses.
- By indication (as studied): fertility and diabetic-neuropathy trials often use 2–3 g/day (frequently as ALCAR, or L-carnitine plus ALCAR); intermittent claudication uses 1–2 g/day of propionyl-L-carnitine; exercise-recovery trials use ~2 g/day of L-carnitine L-tartrate, ideally with carbohydrate to promote muscle uptake.
- Deficiency states (inborn errors, dialysis, valproate) are treated with prescription levocarnitine at physician-directed doses, often higher and sometimes intravenous.
- Form matters: plain L-carnitine and LCLT for metabolic/exercise use, ALCAR for cognitive/neurological use (more brain-penetrant), PLC for circulatory use. See the Forms table above.
Take with food; split doses improve absorption. Doses above ~3 g/day raise the likelihood of GI upset and body odour without clear added benefit in replete people.
Safety
L-carnitine is generally well tolerated at typical supplemental doses, and its notable safety question is an unresolved metabolic one rather than a toxicity problem.
- Well tolerated at typical doses. Decades of clinical use across cardiology, nephrology and andrology, including prescription levocarnitine.
- GI upset and fishy body odour above ~3 g/day. From bacterial production of trimethylamine; dose-related and reversible.
- The TMAO question is unresolved. Observational work links the metabolite to cardiovascular risk; supplement trials show neutral-to-favourable outcomes. Open question, not a demonstrated harm.
- Interacts with thyroid hormone and anticoagulants. May blunt levothyroxine peripherally; case reports of raised INR on warfarin.
- Advanced kidney disease needs oversight. Clearance is altered — supplement only under nephrology guidance.
- No upper limit is set. Absence of a UL is not evidence that unlimited intake is safe.
Full Safety & Interactions Detail
The most common adverse effects, mainly above ~3 g/day, are gastrointestinal upset (nausea, cramping, diarrhoea) and a fishy body odour from bacterial production of trimethylamine. Rarely, high doses cause a trimethylaminuria-like odour syndrome.
The most discussed concern is the TMAO/cardiovascular question: gut bacteria convert unabsorbed carnitine to trimethylamine, which the liver oxidises to trimethylamine-N-oxide (TMAO), a metabolite associated with atherosclerosis and adverse cardiac events in observational studies 14Reference 14Intestinal microbiota metabolism of L-carnitine, a nutrient in red meat, promotes atherosclerosisView study →.
This is a genuine open question, not a demonstrated harm — paradoxically, carnitine supplement trials in cardiac patients have shown neutral-to-favourable cardiovascular outcomes 10Reference 10Meta-analysisL-carnitine in the secondary prevention of cardiovascular disease — systematic review and meta-analysis (13 trials, N=3,629)View study →, and no trial has shown that supplemental carnitine causes cardiovascular events. It is treated here as unresolved.
- Thyroid hormone (levothyroxine): L-carnitine can antagonise thyroid hormone action peripherally and may blunt its effect — relevant in hypothyroid patients on replacement.
- Vitamin K antagonists (warfarin/acenocoumarol): case reports of enhanced anticoagulant effect (raised INR) — monitor.
- Valproate and pivalate-conjugated antibiotics: these cause secondary carnitine depletion; carnitine is used to counter it rather than being harmed by it.
- No clinically significant interaction is established with common analgesics or most cardiovascular drugs.
- Who should be cautious: people with advanced kidney disease or on dialysis (altered clearance — supplement only under nephrology guidance), those on thyroid hormone or anticoagulants, and anyone with a history of seizures (rare reports of increased seizure activity with high doses).
Not established — avoid supplemental doses unless prescribed. Safety of supplemental L-carnitine in pregnancy and lactation has not been adequately studied. Dietary carnitine and physiological levels are normal and necessary, but there is no evidence base supporting supplemental doses in pregnancy, so caution is warranted and any use should be physician-directed.
References
- Fu L, et al. (2013). Primary carnitine deficiency and cardiomyopathy — review. Korean Circulation Journal. https://pubmed.ncbi.nlm.nih.gov/24385988/
- Pons R, De Vivo DC (1995). Primary and secondary carnitine deficiency syndromes — review. Journal of Child Neurology. https://pubmed.ncbi.nlm.nih.gov/8576570/
- Duran M, Loof NE, Ketting D, et al. (1990). Secondary carnitine deficiency — review. J Clin Chem Clin Biochem. https://pubmed.ncbi.nlm.nih.gov/2199597/
- Brevetti G, et al. (1995). Propionyl-L-carnitine in intermittent claudication: double-blind, placebo-controlled multicentre RCT. Journal of the American College of Cardiology. https://pubmed.ncbi.nlm.nih.gov/7594063/
- Brevetti G, Diehm C, Lambert D (1999). European multicenter study on propionyl-L-carnitine in intermittent claudication — RCT. Journal of the American College of Cardiology. https://pubmed.ncbi.nlm.nih.gov/10551714/
- Salas-Huetos A, et al. (2018). Effect of nutrients and dietary supplements on sperm quality parameters — systematic review. Advances in Nutrition. https://pubmed.ncbi.nlm.nih.gov/30462179/
- Khaw SC, et al. (2020). L-carnitine and L-acetylcarnitine supplementation for idiopathic male infertility — systematic review/meta-analysis. Reproduction & Fertility. https://pubmed.ncbi.nlm.nih.gov/35128424/
- Sima AAF, et al. (2005). Acetyl-L-carnitine improves pain, nerve regeneration, and vibratory perception in diabetic neuropathy — multicentre RCT. Diabetes Care. https://pubmed.ncbi.nlm.nih.gov/15616239/
- De Grandis D, Minardi C (2002). Acetyl-L-carnitine (levacecarnine) in diabetic neuropathy — long-term RCT. Drugs in R&D. https://pubmed.ncbi.nlm.nih.gov/12455197/
- DiNicolantonio JJ, et al. (2013). L-carnitine in the secondary prevention of cardiovascular disease — systematic review and meta-analysis (13 trials, N=3,629). Mayo Clinic Proceedings. https://pubmed.ncbi.nlm.nih.gov/23597877/
- Pooyandjoo M, et al. (2016). The effect of (L-)carnitine on weight loss in adults — systematic review and meta-analysis. Obesity Reviews. https://pubmed.ncbi.nlm.nih.gov/27335245/
- Talenezhad N, et al. (2020). Effects of L-carnitine on weight loss and body composition — systematic review, meta-analysis and dose-response (37 RCTs). Clinical Nutrition ESPEN. https://pubmed.ncbi.nlm.nih.gov/32359762/
- Mielgo-Ayuso J, et al. (2021). Effect of acute and chronic oral L-carnitine supplementation on exercise performance — systematic review. Nutrients. https://pubmed.ncbi.nlm.nih.gov/34959912/
- Koeth RA, et al. (2013). Intestinal microbiota metabolism of L-carnitine, a nutrient in red meat, promotes atherosclerosis. Nature Medicine. https://pubmed.ncbi.nlm.nih.gov/23563705/
- Higuchi T, et al. (2016). Levocarnitine improves cardiac function in hemodialysis patients with left ventricular hypertrophy — RCT. American Journal of Kidney Diseases. https://pubmed.ncbi.nlm.nih.gov/26508680/
- Ibarra-Sifuentes HR, et al. (2017). Levocarnitine decreases intradialytic hypotension episodes — RCT. Therapeutic Apheresis and Dialysis. https://pubmed.ncbi.nlm.nih.gov/28805348/
- Kamoen V, et al. (2021). Propionyl-L-carnitine for intermittent claudication — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/34954832/
- Song X, et al. (2017). Efficacy and safety of L-carnitine treatment for chronic heart failure — meta-analysis. BioMed Research International. https://pubmed.ncbi.nlm.nih.gov/28497060/
- Ma X, et al. (2025). Efficacy and safety of L-carnitine and N-acetylcysteine in male infertility — meta-analysis. Revista Internacional de Andrología. https://pubmed.ncbi.nlm.nih.gov/40350672/
- Rolim LC, et al. (2019). Acetyl-L-carnitine for the treatment of diabetic peripheral neuropathy — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/31201734/
- Malaguarnera M, et al. (2011). Acetyl-L-carnitine improves cognitive functions in severe hepatic encephalopathy — RCT. Metabolic Brain Disease. https://pubmed.ncbi.nlm.nih.gov/21870121/
- Martí-Carvajal AJ, et al. (2019). Acetyl-L-carnitine for patients with hepatic encephalopathy — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/30610762/
- Montgomery SA, et al. (2003). Meta-analysis of double-blind RCTs of acetyl-L-carnitine in mild cognitive impairment and early Alzheimer’s disease. International Clinical Psychopharmacology. https://pubmed.ncbi.nlm.nih.gov/12598816/
- Volek JS, et al. (2002). L-carnitine L-tartrate supplementation favorably affects markers of recovery from exercise stress — RCT. American Journal of Physiology-Endocrinology and Metabolism. https://pubmed.ncbi.nlm.nih.gov/11788381/
- Kraemer WJ, et al. (2006). Androgenic responses to resistance exercise: effects of feeding and L-carnitine — RCT. Medicine & Science in Sports & Exercise. https://pubmed.ncbi.nlm.nih.gov/16826026/
- Rebouche CJ. (2004). Kinetics, pharmacokinetics, and regulation of L-carnitine and acetyl-L-carnitine metabolism — review. Annals of the New York Academy of Sciences. https://pubmed.ncbi.nlm.nih.gov/15591001/
- Rebouche CJ, Chenard CA. (1991). Metabolic fate of dietary carnitine in human adults. The Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/2007906/



