
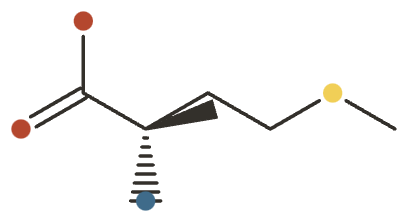
L-Methionine
L-Methionine is an essential sulfur-containing amino acid central to methylation (via SAMe) and a precursor for cysteine, taurine and glutathione.

L-Methionine at a Glance
L-Methionine is an essential, sulfur-containing amino acid — the residue that initiates every protein the body builds. But its interest as a supplement rests on what sits downstream: it is the metabolic entry point to SAMe, the body’s principal methyl donor, and to the transsulfuration pathway that yields cysteine, taurine and glutathione.
The evidence is lopsided in an unusual way. The two applications with genuine human backing are narrow clinical uses — an acetaminophen-poisoning antidote and urinary acidification for phosphate stones. The popular “methylation,” mood and antioxidant claims are almost entirely extrapolated from SAMe rather than demonstrated for methionine taken directly.
And the direction of the arrow is contested. In replete people a methionine load mainly raises homocysteine, a vascular risk marker, rather than delivering benefit — and the longevity literature actively studies methionine restriction. “More is better” is not a safe assumption here.
What It’s Used For
- Acetaminophen overdose antidote — real, effective, and a supervised emergency protocol rather than self-care.
- Urinary acidification (phosphate stones) — a long-standing clinical use in urology.
- Liver / glutathione support — mechanistically grounded, but the human data are on SAMe.
- Methylation / mood support — entirely borrowed from SAMe’s evidence, which is a different molecule.
How It Works
Methionine has two exits, and which one it takes decides everything.
The methylation exit. Methionine adenosyltransferase converts it to SAMe, the universal methyl donor for DNA, proteins, phospholipids and neurotransmitters. Having donated its methyl group, SAMe becomes homocysteine — which is then either remethylated back to methionine (needing folate, B12 or betaine) or pushed down the other exit.
The transsulfuration exit. Homocysteine converts to cysteine and onward to glutathione and taurine. This is the antidote mechanism: replenishing hepatic glutathione lets the liver detoxify NAPQI, the reactive metabolite that causes paracetamol injury.
Two consequences follow. First, the conversion to SAMe is rate-limited by an enzyme whose activity is reduced in liver disease, so a large oral dose does not translate linearly into SAMe or glutathione — which is exactly why SAMe, not methionine, is the studied liver intervention. Second, pushing intake above requirement predominantly raises homocysteine transiently (this is literally the clinical “methionine loading test”), and how cleanly that clears depends on folate, B12 and B6 status.
Separately, methionine is metabolised to sulfate, which lowers urine pH — the entire basis of the stone application.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Methionine is an essential, sulfur-containing amino acid and the initiating residue of protein synthesis, but its interest as a supplement rests on being the metabolic entry point to S-adenosylmethionine (SAMe) — the body’s principal methyl donor — and to the transsulfuration pathway that yields cysteine, taurine and glutathione. The evidence posture is lopsided: the two applications with genuine human backing (an acetaminophen-poisoning antidote and urinary acidification) are narrow clinical uses, while the popular “methylation,” mood and antioxidant claims are almost entirely extrapolated from SAMe rather than demonstrated for methionine taken directly. A central distinction runs through everything below — methionine reliably supports these pathways only when intake is inadequate; in people already replete from ordinary dietary protein, adding more mostly raises homocysteine transiently rather than delivering benefit. Because the amino acid is abundant in any protein-containing diet, most supplemental use is “extra on top of adequacy,” where the evidence is thinnest.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Oral L-methionine replenishes hepatic glutathione, the same mechanism as N-acetylcysteine (NAC), allowing detoxification of the reactive metabolite NAPQI. An early case series gave 30 at-risk patients 2–5 g oral methionine every four hours (up to 10 g total, first dose within ten hours), with no deaths and aminotransferases staying normal in 21 of 30 2Reference 2Case reportOral methionine in the treatment of severe paracetamol (acetaminophen) overdose — case seriesView study →.
Subsequent clinical use 3Reference 3Treatment of acetaminophen poisoning: the use of oral methionineView study → and the Cochrane review of paracetamol-poisoning interventions confirm methionine as an effective antidote, while noting NAC is now first-line and better studied 1Reference 1Systematic reviewInterventions for paracetamol (acetaminophen) overdose — Cochrane systematic reviewView study →.
This is a clinical, medically supervised use at gram-level doses — not a rationale for routine self-supplementation.
Gap: the supporting trials are decades old and small; methionine has been largely superseded by intravenous NAC, and timing (within roughly 8–10 hours) is critical to efficacy.
L-methionine is metabolised to sulfate and lowers urinary pH, which helps dissolve and prevent infection-related phosphate (struvite) and calcium-phosphate stones that form in alkaline urine. It has a long clinical track record in European urology for this purpose 14Reference 14Urinary acidification with L-methionine — prevention of phosphate calculiView study →, and modern reviews of urinary-pH modulators list methionine among the acidifying agents used in stone metaphylaxis 4Reference 4ReviewModulators of urinary pH in the context of urinary stone disease — literature reviewView study →.
Controlled acidification studies confirm the reproducible pH-lowering effect 5Reference 5RCTEffect of D,L-methionine and ammonium chloride on urine acidification — randomized controlled studyView study →.
The benefit is entirely dependent on the stone type and on achieving a target urine pH — it is not a general-health use.
Gap: the evidence is largely older European clinical practice and small studies, and chronic acidification carries its own risks (bone calcium loss, worsening calcium-oxalate stone risk), so this belongs under urological supervision.
Methionine sits directly upstream of cysteine and hepatic glutathione via transsulfuration, and impaired methionine metabolism is a well-described feature of chronic and alcohol-associated liver disease 7Reference 7ReviewMethionine metabolism in chronic liver diseases — reviewView study →. However, the therapeutic human data cluster around SAMe, the downstream activated form, which restored mitochondrial glutathione in alcoholic liver injury 6Reference 6S-adenosyl-L-methionine and mitochondrial reduced glutathione depletion in alcoholic liver diseaseView study → — not around swallowing methionine, which in a diseased liver with limited SAMe-synthetase activity may not be efficiently converted and can accumulate.
Gap: almost no controlled trials of oral L-methionine, as opposed to SAMe, for liver endpoints in people; the precursor logic does not guarantee clinical benefit.
Because methionine is the substrate for SAMe, it is marketed for the same “methylation” and mood indications, and SAMe itself has a genuine adjunctive-antidepressant signal in systematic reviews and meta-analyses 8,
But that evidence used SAMe — typically 800–1,600 mg/day — a distinct, activated molecule. There are essentially no RCTs showing that oral L-methionine improves mood or “methylation status” in replete people, and conversion of extra methionine to SAMe is tightly regulated.
Gap: the entire claim is borrowed from SAMe; direct methionine trials for mood are absent, and loading methionine can raise homocysteine rather than help.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Methionine adenosyltransferase → SAMe | ↑ methyl-donor supply for DNA, protein, phospholipid and neurotransmitter methylation | Methylationmoodliver |
| Transsulfuration (→ cysteine → glutathione, taurine) | ↑ antioxidant precursor supply | Liver / glutathioneacetaminophen antidote |
| Remethylation (homocysteine → methionine; folate/B12/betaine-dependent) | Excess load ↑ transient homocysteine when B-vitamins are limiting | Cardiovascular caution |
| Hepatic sulfate generation | ↓ urinary pH | Urinary acidification |
| Translation initiation (AUG start codon) | Initiates protein synthesis | Essential dietary requirement |
Pharmacokinetics
L-methionine is well absorbed from the small intestine via neutral amino-acid transporters and enters the portal circulation, where the liver is the main site of first-pass metabolism to SAMe. That conversion is rate-limited by methionine adenosyltransferase activity, which is reduced in liver disease — so a large oral dose does not translate linearly into SAMe or glutathione.
Free-amino-acid plasma peaks are reached within roughly 1–3 hours and the amino-acid pool turns over quickly; there is no meaningful long-term storage of free methionine, and excess is either remethylated, shunted to transsulfuration, or oxidised. The decision-relevant point for supplementation is that pushing intake above requirement predominantly raises homocysteine transiently — the basis of the clinical methionine-loading test — rather than expanding useful downstream pools, and that adequacy of folate, B12 and B6 governs how cleanly that load is cleared.
Clinical trials
Registered interventional trials on isolated oral L-methionine are limited and mostly historical — the acetaminophen antidote and urinary acidification. Contemporary trial activity concentrates on SAMe (mood, liver) and on dietary methionine restriction for metabolic and longevity endpoints, rather than on supplementation. As an off-patent nutrient supplied by food, it attracts little industry-funded trial investment.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~15(mostly older; antidote & acidification) | Few | Few | Many(restriction/longevity models) |
Last checked: August 2026.
Dietary Sources
Methionine is supplied by dietary protein and is abundant enough that deficiency is rare on any adequate diet. It is highest in animal proteins — eggs, fish, meat and dairy — and in some seeds and Brazil nuts. It is the limiting amino acid in legumes, which is why bean-heavy diets pair legumes with grains.
Requirements are set for the sulfur amino acids together (methionine + cysteine), because cysteine can be made from methionine but not the reverse.
| Food (approx. per 100 g) | Methionine |
|---|---|
| Parmesan / hard cheese | ~0.8–1.0 g |
| Chicken / beef / fish | ~0.5–0.9 g |
| Egg (whole) | ~0.4 g |
| Brazil nuts, sesame seeds | ~0.3–1.0 g |
| Legumes (beans, lentils) | ~0.1–0.3 g (the limiting amino acid) |
A typical mixed diet supplies roughly 1.5–2.5 g/day, comfortably above requirement, and absorption of dietary methionine is high — well over 90%. Cooking does not meaningfully destroy it, but refining and processing that strips protein lowers the content.
Intake & Dosage
These are doses studied in research, not a personal recommendation.
- Requirement: set jointly as sulfur amino acids (methionine + cysteine); the estimated average requirement is ~15 mg/kg/day and the RDA ~19 mg/kg/day combined — about 1.3–1.5 g/day for a 70 kg adult, met by ordinary protein intake. There is no separate methionine RDA and no established UL.
- General supplemental doses: modest, around 500 mg–1 g/day. Because free methionine loads raise homocysteine, splitting doses and ensuring adequate folate, B12 and B6 is prudent.
- Clinical acetaminophen antidote: 2–5 g orally every 4 hours up to 10 g total, started within roughly 8–10 hours of overdose — a supervised emergency protocol, not self-care.
- Urinary acidification: titrated to a urine-pH target, roughly 0.6–1.5 g/day, under urological supervision.
- Direction matters. Methionine restriction is an active research area for metabolic and
longevity endpoints 12,
13Reference 12ReviewThe impact of dietary protein intake on longevity and metabolic health — reviewView study →Reference 13AnimalMetabolic adaptations to methionine restriction that benefit health and lifespan in rodents — reviewView study → , so “more is better” is not established.
Safety
At dietary, food-level intakes L-methionine is safe and essential. The cautions all apply to isolated high supplemental doses.
- Safe and essential at food-level intakes. Deficiency is rare on any adequate-protein diet.
- High loads raise homocysteine. This is the basis of the clinical methionine-loading test; in a randomised crossover it raised the exercise blood-pressure response via endothelial dysfunction 10,
11Reference 10RCTElevation of plasma homocysteine by methionine loading increases the diastolic blood pressure response to exercise — randomized crossoverView study →Reference 11Homocysteine responses to methionine loading — research studyView study → . Worse when folate, B12 or B6 are low. - Caution in liver disease. SAMe-synthetase activity is reduced, so oral methionine may not convert efficiently and can accumulate — SAMe is the studied intervention there.
- Interacts with levodopa. Methionine and SAMe methylation may affect L-dopa handling — space the dosing and monitor.
- GI upset. Nausea and digestive complaints occur at higher doses.
- No upper limit is set. Absence of a UL does not imply unlimited supplemental methionine is safe.
Full Safety & Interactions Detail
Homocysteine is the dose-limiting concern. Large methionine loads transiently raise plasma
homocysteine — this is literally the basis of the clinical methionine-loading test — and in a
randomised crossover that rise increased the exercise blood-pressure response via endothelial
dysfunction 10,
- Liver disease: in impaired livers, SAMe-synthetase activity is reduced, so oral methionine may not convert efficiently and can accumulate. SAMe, not methionine, is the studied intervention there.
- Interactions: levodopa — methionine and SAMe methylation may affect L-dopa handling, so space the dosing and monitor. Any regimen where a raised homocysteine matters is also relevant, which brings concurrent B-vitamin status into scope. No large-scale interaction database exists for isolated methionine.
- GI upset: nausea and digestive complaints occur at higher doses.
Scope disclosure. Interactions were assessed partially — the homocysteine-relevant cofactors and levodopa were noted; a comprehensive drug-interaction review was not performed. Pregnancy and lactation were assessed at an overview level: dietary intake is fine, supplemental high-dose is not established. No UL has been set, and that absence does not imply unlimited supplemental methionine is safe. Where something was not studied, it is marked “not assessed,” not “safe.”
Dietary methionine is essential and appropriate; isolated high-dose supplements are not established. Both very low and very high maternal methionine have been flagged in animal models, so err toward diet-level intake. Isolated high-dose supplementation in pregnancy or lactation is best avoided without medical guidance.
References
- Chiew AL, Gluud C, Brok J, Buckley NA (2018). Interventions for paracetamol (acetaminophen) overdose — Cochrane systematic review. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/29473717/
- Crome P, Vale JA, Volans GN, Widdop B, Goulding R (1976). Oral methionine in the treatment of severe paracetamol (acetaminophen) overdose — case series. The Lancet. https://pubmed.ncbi.nlm.nih.gov/61500/
- Vale JA, et al. (1981). Treatment of acetaminophen poisoning: the use of oral methionine. Archives of Internal Medicine. https://pubmed.ncbi.nlm.nih.gov/7469632/
- Chan C, Sui W, Breeggemann MC, Stoller M (2025). Modulators of urinary pH in the context of urinary stone disease — literature review. Translational Andrology and Urology. https://pubmed.ncbi.nlm.nih.gov/40949433/
- Neal CE, Grissett GP, Fleming S, et al. (2024). Effect of D,L-methionine and ammonium chloride on urine acidification — randomized controlled study. American Journal of Veterinary Research. https://pubmed.ncbi.nlm.nih.gov/39255835/
- García-Ruiz C, et al. (2002). S-adenosyl-L-methionine and mitochondrial reduced glutathione depletion in alcoholic liver disease. Alcohol. https://pubmed.ncbi.nlm.nih.gov/12163147/
- Li Z, et al. (2020). Methionine metabolism in chronic liver diseases — review. Signal Transduction and Targeted Therapy. https://pubmed.ncbi.nlm.nih.gov/33273451/
- Peng TR, Cheng HY, Wu TW (2024). S-adenosylmethionine (SAMe) as adjuvant therapy for depression — updated systematic review and meta-analysis. General Hospital Psychiatry. https://pubmed.ncbi.nlm.nih.gov/38199136/
- Williams AL, et al. (2005). S-adenosylmethionine (SAMe) as treatment for depression — systematic review. Clinical and Investigative Medicine. https://pubmed.ncbi.nlm.nih.gov/16021987/
- Brett SE, Jiang BY, Turner C, Ritter JM, Chowienczyk PJ (2006). Elevation of plasma homocysteine by methionine loading increases the diastolic blood pressure response to exercise — randomized crossover. Journal of Hypertension. https://pubmed.ncbi.nlm.nih.gov/16957558/
- Chiarelli F, Pomilio M, Mohn A, et al. (2000). Homocysteine responses to methionine loading — research study. The Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/10969265/
- Kitada M, Ogura Y, Monno I, Koya D (2019). The impact of dietary protein intake on longevity and metabolic health — review. EBioMedicine. https://pubmed.ncbi.nlm.nih.gov/30975545/
- Perrone CE, Malloy VL, Orentreich DS, et al. (2013). Metabolic adaptations to methionine restriction that benefit health and lifespan in rodents — review. Experimental Gerontology. https://pubmed.ncbi.nlm.nih.gov/22819757/
- Bach D, Hesse A, Schaefer RM (1987). Urinary acidification with L-methionine — prevention of phosphate calculi. Fortschritte der Medizin. https://pubmed.ncbi.nlm.nih.gov/3609992/



