
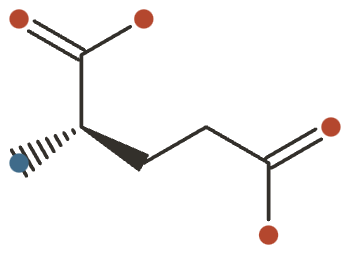
L-Glutamic Acid
L-Glutamic acid (glutamate) is a nonessential amino acid and the brain's principal excitatory neurotransmitter; also the source of GABA and glutamine.

L-Glutamic Acid at a Glance
L-Glutamic acid (glutamate) is the most abundant amino acid in dietary protein and, separately, the brain’s principal excitatory neurotransmitter. Those two facts are true at the same time and are almost entirely unrelated — which is the single most useful thing to understand about it.
Roughly 95% of ingested glutamate never reaches the bloodstream. The gut wall extracts and burns it as fuel on first pass. What does get through does not cross the blood–brain barrier in any meaningful amount: brain glutamate is synthesised locally and tightly regulated. So oral glutamate feeds the intestine, not the brain, and the “brain energy” and cognition claims made for glutamic-acid capsules have no mechanism to stand on.
What glutamate genuinely does, it does in food. Free glutamate is the umami stimulus — the savoury taste of parmesan, soy sauce, ripe tomatoes and kombu — and adding it can improve palatability and intake where appetite is failing. That is a food-formulation effect, not a supplement benefit.
What It’s Used For
- Appetite & palatability (umami) — the best-supported use, and it belongs to MSG in a meal rather than a capsule.
- Blood pressure — a large observational inverse association, with no trial behind it.
- Gut mucosal fuel & integrity — excellent mechanism, no human supplement trials.
- Gastric-acid support — glutamic-acid HCl does acidify the stomach; that is all that has been shown.
And one well-evidenced null. The “MSG symptom complex,” once called “Chinese restaurant syndrome,” does not survive blinding. Double-blind placebo-controlled challenge trials and systematic reviews have repeatedly failed to reproduce a reaction to dietary-level MSG in the general population.
How It Works
Glutamate is the central hub of amino-group metabolism. Through transamination it swaps its amino group with α-ketoglutarate, which makes it the exchange point through which most other amino acids are built and broken down. That is why the body never runs short: it can make glutamate from essentially any nitrogen source.
In the gut, glutamate is a primary oxidative fuel for the enterocyte — the cell burns it directly in the TCA cycle to meet its own substantial energy needs, alongside glutamine and aspartate. This is not a side effect of digestion; it is the main destination of dietary glutamate, and it is why so little arrives systemically.
On the tongue, free glutamate activates the T1R1/T1R3 umami receptor, producing the savoury taste and the cephalic-phase and vagal signalling that follow. Ageing, fermenting and slow-cooking raise free glutamate by breaking protein down, which is exactly why those foods taste more savoury.
In the brain, glutamate acts at NMDA, AMPA and kainate receptors — but that pool is synthesised
in the CNS behind the blood–brain barrier. Dietary intake does not feed it 1,
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Glutamic acid (glutamate) is a dispensable (“nonessential”) amino acid that is also the brain’s principal excitatory neurotransmitter and a central hub of amino-group metabolism. Almost none of the decision-relevant story is about supplementing it: the body makes glutamate in abundance, dietary protein supplies 10–20 g/day, and roughly 95% of ingested glutamate is consumed as fuel by the gut wall before it ever reaches the circulation — so oral glutamate does not raise brain glutamate and does not cross the blood–brain barrier to any meaningful degree 1,
The genuinely evidenced “applications” are therefore about glutamate in food — as the umami stimulus (monosodium glutamate, MSG) that can improve palatability and intake in under-eating populations — plus a scattering of thin, mechanism-level uses (gastric-acid support, gut-mucosal fuelling) and one notable observational blood-pressure signal. Standalone glutamic-acid capsules have essentially no efficacy literature behind them.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Added as MSG, free glutamate is the umami stimulus, and small human trials show it can raise the palatability and intake of savoury foods — the effect most useful where appetite is failing. In a randomised crossover in older adults, adding ~2 g MSG to a high-energy, high-protein liquid diet accelerated gastric emptying and improved nutrient handling 3Reference 3RCTMonosodium L-glutamate added to a high-energy, high-protein liquid diet promotes gastric emptying — randomised crossoverView study →.
Acute crossover studies adding MSG to whey-protein or high-protein meals show modest, sometimes inconsistent effects on satiety and subsequent intake — MSG can increase short-term fullness with protein yet increase selection and intake of savoury foods in other designs 4,
The signal is real but small, population-specific (elderly, patients, the undernourished), and about food formulation rather than a supplement.
Gap: trials are small and short; benefit is concentrated in under-eating populations and does not translate into a reason for healthy, well-fed people to take glutamate.
In the INTERMAP cross-sectional study of more than 4,000 adults across four countries, higher dietary glutamic acid (as a percent of total protein) was associated with lower systolic and diastolic blood pressure, independent of other nutrients 5Reference 5ObservationalGlutamic acid, the main dietary amino acid, and blood pressure: the INTERMAP Study — cross-sectional epidemiologyView study →.
Metabonomic follow-up analyses were consistent with a role for glutamic acid in the higher blood pressure of some populations 6Reference 6ObservationalDietary and urinary metabonomic factors possibly accounting for higher blood pressure — cohort/metabonomic analysisView study →, and the finding features in nutrient–BP reviews 14Reference 14ReviewAn update on nutrients and blood pressure — reviewView study →.
Because glutamic acid is the single most abundant amino acid in dietary protein, this may partly be a marker of overall protein and diet quality rather than a specific glutamate effect.
Gap: entirely observational — no randomised trial has tested glutamate or MSG intake as a blood-pressure intervention, so causation is unproven and no supplemental dose follows from it.
Isotope-tracer work established that glutamate is a primary oxidative fuel of the intestinal mucosa: the gut extracts and burns the majority of dietary glutamate in first pass, using it — with glutamine and aspartate — to meet enterocyte energy needs and to support mucosal protein and nucleotide synthesis 1,
Gap: compelling mechanism and animal data, but no human supplement trials showing a clinical GI benefit over an adequate protein diet.
Glutamic-acid hydrochloride has historically been sold as a “stomach-acid” supplement for suspected hypochlorhydria. A small controlled pharmacology study showed that oral glutamic-acid HCl transiently lowers gastric pH and can restore the absorption of pH-dependent drugs in people with low acid 7Reference 7Modification of gastric pH with oral glutamic acid hydrochloride — controlled pharmacology studyView study →. That confirms it acidifies the stomach; it does not demonstrate a clinical benefit for digestion, symptoms, or nutrient status.
Gap: a single small study of a surrogate endpoint (pH), no outcome trials, and validated approaches exist for genuine hypochlorhydria.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Umami taste receptor (T1R1/T1R3) | Activated by free glutamate → savoury taste, cephalic-phase and vagal signalling | Appetite & palatability |
| Enterocyte oxidative metabolism (TCA cycle) | Glutamate is a major first-pass fuel; ~95% of dietary glutamate is metabolised by the gut | Gut mucosal fuel; why oral glutamate barely enters circulation |
| Transamination (AST/ALT, α-ketoglutarate ⇄ glutamate) | Central amino-group donor and acceptor for amino-acid synthesis | Whole-body amino-acid metabolism |
| Glutamate decarboxylase (GAD) | Glutamate → GABA (inhibitory transmitter) | Neurotransmitter precursor — the CNS-synthesised poolnot the dietary one |
| NMDA / AMPA / kainate receptors | Excitatory neurotransmission | Brain glutamatesupplied by CNS synthesis rather than diet |
Pharmacokinetics
Dietary glutamate has very low systemic bioavailability: the intestinal mucosa extracts and oxidises
the great majority in first pass, so plasma glutamate rises only modestly after ordinary meals and is
cleared within minutes by rapid transamination 1,
Critically, glutamate does not freely cross the blood–brain barrier — brain glutamate is
synthesised locally and tightly regulated, which is why oral glutamate, including MSG, does not raise
brain glutamate in healthy people 1,
Clinical trials
Glutamic acid and MSG are off-patent food components, so there is little commercial trial activity. The human literature is dominated by small academic crossover studies of MSG in food and by safety/challenge trials, rather than by efficacy programmes for a supplement.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~15(mostly small MSG-in-food crossovers & safety challenges) | Few | — | Many(gut & neuro metabolism) |
Last checked: August 2026.
Dietary Sources
Glutamate is the single most abundant amino acid in dietary protein, supplied both as bound
glutamate — part of the proteins in meat, fish, eggs, dairy and legumes — and as free
glutamate, which is what the tongue tastes as umami. Typical intakes run roughly 10–20 g/day of
bound glutamate from protein plus about 1 g/day of free glutamate; added MSG contributes another
0.3–1.0 g/day in populations that use it 18,
Foods richest in free (umami-active) glutamate:
| Food | Free glutamate (approx., mg/100 g) |
|---|---|
| Kombu (dried kelp) | ~1,200–3,400 |
| Parmesan / aged cheeses | ~1,200–1,700 |
| Dried shiitake / mushrooms | ~70–1,000 |
| Soy sauce / fish sauce | ~400–1,400 |
| Cured ham (e.g. jamón) | ~300–700 |
| Ripe tomatoes (paste is higher) | ~150–250 |
| Green peas, corn | ~100–200 |
Cooking, fermenting, ageing and ripening all raise free-glutamate content, because breaking protein down releases bound glutamate. That is why aged, fermented and slow-cooked foods taste more savoury.
There is no practical way to be deficient in glutamate on any adequate-protein diet, and because the
gut metabolises the large majority of what is eaten, dietary intake mainly serves the intestine and
the whole-body amino-acid pool rather than raising circulating or brain glutamate 1,
Intake & Dosage
These are doses studied in research, not a personal recommendation.
- Requirement: none. Glutamic acid is a dispensable amino acid — the body synthesises it as needed — so there is no RDA or AI, and no evidence of dietary insufficiency in people eating adequate protein.
- Upper limit: none set. JECFA and EFSA have concluded MSG is safe at normal dietary use, and JECFA’s acceptable daily intake is “not specified.” EFSA in 2017 derived a group ADI of 30 mg/kg body weight/day for glutamic acid and glutamates as food additives — a conservative additive-safety figure, not a nutritional requirement.
- Doses used in research: MSG-in-food studies used ~0.5–3 g per meal; the historical glutamic-acid hydrochloride “digestive” products supplied a few hundred mg with meals. Standalone glutamic-acid supplementation has no established beneficial dose.
- Practical note: any effect of glutamate is best obtained in food, as umami seasoning to improve palatability and intake — not as a capsule. Taking a large amount as a bolus in liquid on an empty stomach is the scenario most likely to provoke transient symptoms, and it offers no benefit.
Safety
Glutamate has one of the most extensively studied safety records of any food component, and the headline finding is a null.
- The “MSG symptom complex” does not survive blinding. Multiple double-blind, placebo-controlled challenge studies and systematic reviews fail to reproduce a reaction to dietary-level MSG 8,
9, .10, 11Reference 8RCTReview of alleged reaction to monosodium glutamate and outcome of a multicenter double-blind, placebo-controlled study — RCT/reviewView study →Reference 9RCTThe monosodium glutamate symptom complex: assessment in a double-blind, placebo-controlled, randomized study — RCTView study →Reference 10Systematic reviewDoes monosodium glutamate really cause headache? A systematic review of human studies — systematic reviewView study →Reference 11ReviewA review of the alleged health hazards of monosodium glutamate — reviewView study → - Well tolerated at dietary and culinary intakes. Regulatory bodies (JECFA, EFSA) have concluded MSG is safe in normal food use.
- Large fasting boluses are a different matter. ≥3 g in water without food can cause transient, mild, self-limited symptoms — headache, flushing, tingling — in a minority of sensitive people 10,
11Reference 10Systematic reviewDoes monosodium glutamate really cause headache? A systematic review of human studies — systematic reviewView study →Reference 11ReviewA review of the alleged health hazards of monosodium glutamate — reviewView study → . - An unresolved obesity association. Early cohort analyses linked higher MSG intake to overweight 16,
17Reference 16ObservationalAssociation of monosodium glutamate intake with overweight in Chinese adults: the INTERMAP Study — cohortView study →Reference 17ObservationalConsumption of monosodium glutamate in relation to incidence of overweight in Chinese adults — prospective cohortView study → ; this has not been consistently replicated and is confounded by overall diet. - Glutamic-acid HCl acidifies the stomach, which could alter absorption of pH-dependent drugs 7Reference 7Modification of gastric pH with oral glutamic acid hydrochloride — controlled pharmacology studyView study →.
Full Safety & Interactions Detail
At normal dietary and culinary intakes glutamate is well tolerated. Multiple double-blind,
placebo-controlled challenge studies and systematic reviews have failed to reproduce the so-called
“MSG symptom complex” — reactions are not reliably triggered by dietary-level MSG under blinded
conditions 8,
- The obesity question. Early cohort analyses associated higher MSG intake with overweight
16,
17Reference 16ObservationalAssociation of monosodium glutamate intake with overweight in Chinese adults: the INTERMAP Study — cohortView study →Reference 17ObservationalConsumption of monosodium glutamate in relation to incidence of overweight in Chinese adults — prospective cohortView study → , but this has not been consistently replicated and is confounded by overall diet; comprehensive reviews do not support a causal link at normal intakes 11Reference 11ReviewA review of the alleged health hazards of monosodium glutamate — reviewView study →. It remains an unresolved observational signal rather than an established harm. - Interactions: none clinically significant is established at dietary levels. The theoretical exception is that glutamic-acid HCl acidifies the stomach and could alter the absorption of pH-dependent drugs, mirroring the mechanism demonstrated in 7Reference 7Modification of gastric pH with oral glutamic acid hydrochloride — controlled pharmacology studyView study →. Interaction data for high-dose standalone glutamic acid are limited.
- Who should be cautious: anyone who reports a consistent, reproducible reaction to added MSG can simply limit it.
Scope disclosure. Interactions were assessed partially, as above. Pregnancy and lactation were assessed for dietary MSG, which is regarded as safe; supra-dietary supplemental glutamic acid in pregnancy is not assessed. There is no IOM/DRI Upper Limit; JECFA’s ADI is “not specified” and EFSA’s group additive ADI is 30 mg/kg/day. Absence of a UL does not mean unlimited intake is advisable, particularly as large fasting boluses. Where something was not studied, it is marked “not assessed,” not “safe.”
Dietary glutamate, including MSG at culinary levels, is considered safe. Maternal dietary glutamate is largely metabolised by maternal gut and placental tissue and does not raise fetal brain glutamate, and regulatory bodies have not identified a pregnancy hazard from dietary MSG. As with any supplement, high-dose standalone glutamic-acid capsules have not been studied at supra-dietary doses in pregnancy or lactation and are not recommended.
References
- Reeds PJ, Burrin DG, Stoll B, Jahoor F (2000). Intestinal glutamate metabolism — review. Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/10736365/
- Burrin DG, Stoll B (2008). Emerging aspects of dietary glutamate metabolism in the developing gut — review. Asia Pacific Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/18296381/
- Zai H, Kusano M, Hosaka H, et al. (2009). Monosodium L-glutamate added to a high-energy, high-protein liquid diet promotes gastric emptying — randomised crossover. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/19056566/
- Anderson GH, Fabek H, Akilen R, et al. (2018). Acute effects of monosodium glutamate addition to whey protein on appetite, food intake and blood glucose — randomised trial. Appetite. https://pubmed.ncbi.nlm.nih.gov/28843973/
- Stamler J, Brown IJ, Daviglus ML, et al. (2009). Glutamic acid, the main dietary amino acid, and blood pressure: the INTERMAP Study — cross-sectional epidemiology. Circulation. https://pubmed.ncbi.nlm.nih.gov/19581495/
- Stamler J, Brown IJ, Yap IKS, et al. (2013). Dietary and urinary metabonomic factors possibly accounting for higher blood pressure — cohort/metabonomic analysis. Hypertension. https://pubmed.ncbi.nlm.nih.gov/24101663/
- Knapp MJ, Berardi RR, Dressman JB, et al. (1991). Modification of gastric pH with oral glutamic acid hydrochloride — controlled pharmacology study. Clinical Pharmacy. https://pubmed.ncbi.nlm.nih.gov/1686581/
- Geha RS, Beiser A, Ren C, et al. (2000). Review of alleged reaction to monosodium glutamate and outcome of a multicenter double-blind, placebo-controlled study — RCT/review. Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/10736382/
- Yang WH, Drouin MA, Herbert M, et al. (1997). The monosodium glutamate symptom complex: assessment in a double-blind, placebo-controlled, randomized study — RCT. Journal of Allergy and Clinical Immunology. https://pubmed.ncbi.nlm.nih.gov/9215242/
- Obayashi Y, Nagamura Y (2016). Does monosodium glutamate really cause headache? A systematic review of human studies — systematic review. Journal of Headache and Pain. https://pubmed.ncbi.nlm.nih.gov/27189588/
- Zanfirescu A, Ungurianu A, Tsatsakis AM, et al. (2019). A review of the alleged health hazards of monosodium glutamate — review. Comprehensive Reviews in Food Science and Food Safety. https://pubmed.ncbi.nlm.nih.gov/31920467/
- Luscombe-Marsh ND, Smeets AJ, Westerterp-Plantenga MS (2009). The addition of monosodium glutamate and inosine monophosphate-5 to high-protein meals: effects on satiety — randomised crossover. British Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/19267954/
- Bellisle F, Dalix AM, Chapppuis AS, et al. (1996). Monosodium glutamate affects mealtime food selection in diabetic patients — controlled study. Appetite. https://pubmed.ncbi.nlm.nih.gov/8800482/
- Chan Q, Stamler J, Elliott P (2016). An update on nutrients and blood pressure — review. Journal of Atherosclerosis and Thrombosis. https://pubmed.ncbi.nlm.nih.gov/26686565/
- Tomé D (2018). The roles of dietary glutamate in the intestine — review. Annals of Nutrition and Metabolism. https://pubmed.ncbi.nlm.nih.gov/30508814/
- He K, Zhao L, Daviglus ML, et al. (2008). Association of monosodium glutamate intake with overweight in Chinese adults: the INTERMAP Study — cohort. Obesity (Silver Spring). https://pubmed.ncbi.nlm.nih.gov/18497735/
- He K, Du S, Xun P, et al. (2011). Consumption of monosodium glutamate in relation to incidence of overweight in Chinese adults — prospective cohort. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/21471280/
- Jinap S, Hajeb P (2010). Glutamate: its applications in food and contribution to health — review. Appetite. https://pubmed.ncbi.nlm.nih.gov/20470841/
- Hawkins RA (2009). The blood-brain barrier and glutamate — review. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/19571220/
- Watford M (2018). Protein — review. Advances in Nutrition. https://pubmed.ncbi.nlm.nih.gov/30060014/



