
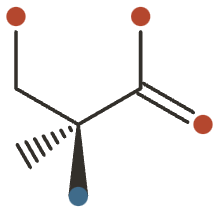
L-Serine
A non-essential amino acid central to one-carbon metabolism, phospholipids and neurotransmitter precursors, with disease-specific therapeutic use.

L-Serine at a Glance
L-serine is a non-essential amino acid the body makes from a glycolysis intermediate. It is available in most protein foods, and also produced in the brain by astrocytes.
Unusually for a “non-essential” amino acid, the brain depends on making its own — serine crosses the blood-brain barrier poorly, so central supply is largely local. That is why serine’s clinical uses are almost entirely neurological, and why the genetic disorders of serine synthesis present as severe brain disease.
What It’s Used For
- Serine-deficiency syndromes (3-PGDH) — treats the inherited disorders of serine synthesis; its clearest use.
- Hereditary neuropathy (HSAN1) — suppresses the toxic lipids that drive this inherited neuropathy.
- ALS — studied in amyotrophic lateral sclerosis.
- GRIN-related encephalopathy — used in NMDA-receptor-related encephalopathy.
- Diabetic peripheral neuropathy — explored for nerve pain in diabetes.
How It Works
Serine is a hub metabolite. It is the precursor to glycine and to D-serine, the co-agonist that must bind the NMDA receptor alongside glutamate for it to open — which is the basis of the GRIN-encephalopathy work. It also supplies the head group for phosphatidylserine and the backbone for sphingolipids, the fats that build myelin.
That last route explains HSAN1: when serine is short, the enzyme that normally uses it grabs alanine instead and produces neurotoxic deoxysphingolipids. Supplying serine outcompetes the error. Serine is also the main entry point into one-carbon metabolism, feeding the folate cycle.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-serine is a non-essential amino acid the body makes for itself from a glycolytic intermediate (3-phosphoglycerate) and from glycine, so a healthy, protein-fed person is essentially never short of it. Its therapeutic interest is therefore not “top up a common shortfall” but a handful of specific situations where serine supply or serine-derived lipids go wrong: inborn errors of serine synthesis, a rare inherited neuropathy (HSAN1), and — more speculatively — ALS, developmental NMDA-receptor disorders and diabetic nerve damage. The strongest data are in rare, genetically defined populations where supplementation corrects a real deficit; the popular “neuroprotective supplement” framing rests largely on preclinical work and one hypothesis (that dietary L-serine blocks misincorporation of the cyanobacterial toxin BMAA). Because L-serine competes with other neutral amino acids for transport into the brain, very high doses can paradoxically lower other amino acids — dose and context matter more than the fact of taking it.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Defects in the three enzymes that synthesize L-serine — most commonly 3-phosphoglycerate dehydrogenase (3-PGDH) — cause congenital microcephaly, severe psychomotor retardation and intractable seizures, and are unusual among neurometabolic diseases in being treatable 2Reference 2ReviewSerine-deficiency syndromes — reviewView study →.
Oral L-serine, often combined with glycine, can arrest otherwise drug-resistant seizures: in one 4½-year-old with 3-PGDH deficiency, seizures responded only to L-serine and glycine supplementation 3Reference 3Case reportCoşkun, T., Aydin, H. I., Kiliç, M., et al. (2009). 3-phosphoglycerate dehydrogenase deficiency: a case report of a treatable cause of seizures — case report. The Turkish Journal of Pediatrics. https://pubmed.ncbi.nlm.nih.gov/20196394/View study →.
This is a genuine repletion benefit — the supplement replaces a metabolite the patient cannot make — but it applies to a rare, genetically defined group, and dosing must be watched: in two siblings, very high-dose serine (1400 mg/kg/day) arrested head growth (reversible on dose reduction) and lowered CSF methionine, isoleucine and ornithine through competition for transport 4Reference 4Case reportPhenotypic heterogeneity and adverse effects of serine treatment in 3-phosphoglycerate dehydrogenase deficiency: report on two siblings — case reportView study →.
Gap: benefit is confined to people with a proven biosynthetic defect; no RCT (evidence is case reports/series), and the therapeutic window is dose-sensitive.
HSAN1, caused by SPTLC1/SPTLC2 mutations, produces neurotoxic 1-deoxysphingolipids because the mutant enzyme uses alanine instead of serine; loading the system with L-serine pushes the enzyme back toward its normal substrate. In a randomized, placebo-controlled trial (n=18, 400 mg/kg/day for 1 year with an open-label second year), the L-serine group improved on the Charcot-Marie-Tooth Neuropathy Score relative to placebo (−1.5 units, 95% CI −2.8 to −0.1), with reduced plasma deoxysphingolipids; the authors graded it Class I evidence that high-dose L-serine slows disease progression 1Reference 1RCTRandomized trial of l-serine in patients with hereditary sensory and autonomic neuropathy type 1 — randomised controlled trialView study →.
An iPSC model of the same disease shows L-serine-responsive neurite deficits, supporting the mechanism 12Reference 12In vitroAn iPSC model of hereditary sensory neuropathy-1 reveals L-serine-responsive deficits in neuronal ceramide — in vitro/iPSCView study →.
Gap: a single small trial (16 completers) in a rare disease; “slows progression” is not “reverses,” and the 400 mg/kg/day dose is far above ordinary supplemental use.
The ALS rationale is the BMAA hypothesis: the cyanobacterial non-protein amino acid β-N-methylamino-L-alanine can be misincorporated into proteins in place of L-serine, causing misfolding and aggregation, and excess L-serine inhibits that misincorporation in vitro 9Reference 9In vitroThe non-protein amino acid BMAA is misincorporated into human proteins in place of L-serine causing protein misfolding and aggregation — in vitroView study →.
A randomized, double-blind phase I trial (n=20; 0.5–15 g twice daily for 6 months) found L-serine generally safe and, against historical placebo controls, it “did not appear to accelerate” functional decline 5,
Independent review (ALSUntangled 38) judged the evidence preliminary 7Reference 7ReviewALSUntangled 38: L-serine (2017) — review. Amyotrophic Lateral Sclerosis & Frontotemporal Degeneration. https://pubmed.ncbi.nlm.nih.gov/27894192/View study →.
Gap: this is a safety/tolerability study, not an efficacy trial — comparison was to historical controls, three patients died during the trial, and the underlying BMAA-causation hypothesis remains unproven.
Low serine and accumulation of neurotoxic 1-deoxysphingolipids are implicated in diabetic peripheral neuropathy, and human genetic evidence (a 2026 preprint) links the serine-biosynthesis pathway to the disease 11Reference 11Human genetic evidence links serine biosynthesis to diabetic peripheral neuropathy — genetic association study (preprint). medRxiv. https://pubmed.ncbi.nlm.nih.gov/42326776/View study →. In db/db mice, 6 months of oral L-serine (5–20% of diet) suppressed toxic 1-deoxysphingolipids and improved functional/sensory measures, though structural axon degeneration still progressed 10Reference 10AnimalLong-term effects of l-serine supplementation upon a mouse model of diabetic neuropathy — animal studyView study →.
Gap: entirely preclinical plus genetic association — no completed human efficacy trial, and even in mice the structural protection was incomplete.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| One-carbon (folate) metabolism | Donates carbon units for nucleotide and methyl-group synthesis | General metabolism; rapidly dividing tissue |
| Phospholipid / sphingolipid synthesis | Precursor of phosphatidylserine and sphingoid bases | HSAN1diabetic neuropathy |
| Serine palmitoyltransferase substrate | Excess serine outcompetes alanine, lowering neurotoxic 1-deoxysphingolipids | HSAN1diabetic neuropathy |
| Glycine + cysteine synthesis | Metabolic precursor | Serine-deficiency syndromes |
| D-serine → NMDA receptor co-agonist | Supplies co-agonist for NMDA-receptor signaling | GRIN disorders; CNS signaling |
| Neutral amino-acid transport (LAT1) | Competes with Met/Ile/other neutral AAs at the blood–brain barrier | High-dose safety caveat |
Pharmacokinetics
Oral L-serine is absorbed through intestinal neutral-amino-acid transporters and enters the general amino-acid pool; the body also synthesizes it endogenously, so plasma levels are tightly regulated and the plasma half-life of a dose is short (on the order of hours, as for dietary amino acids generally). The decision-relevant PK fact is transport competition: L-serine shares carriers with other large neutral amino acids at the blood–brain barrier, so very high doses can lower CSF methionine, isoleucine and ornithine — this is why high-dose regimens are titrated and monitored rather than simply maximized 4Reference 4Case reportPhenotypic heterogeneity and adverse effects of serine treatment in 3-phosphoglycerate dehydrogenase deficiency: report on two siblings — case reportView study →. Studied oral doses span an enormous range, from grams/day up to 400 mg/kg/day (HSAN1) and 15 g twice daily (ALS).
Clinical trials
Registered human trials of L-serine are few and concentrated in rare disease: a completed HSAN1 RCT (NCT01733407), a completed ALS phase I trial, and a completed GRIN-encephalopathy phase 2A study (NCT04646447), with diabetic-neuropathy work still at the preclinical/genetic stage. As an unpatentable amino acid, L-serine attracts little industry-funded late-phase trial activity.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| 3 | 1–2 | 0 | ~20+ |
Last checked: July 2026.
Dietary Sources
L-serine is non-essential: healthy adults synthesize it from the glycolytic intermediate 3-phosphoglycerate and from glycine, and dietary protein supplies the rest, so deficiency from diet essentially does not occur in the general population. It is abundant in ordinary protein foods rather than concentrated in a few sources.
| Food group | Representative sources | Note |
|---|---|---|
| Animal protein | Eggs, meat, poultry, fish, dairy | High-quality, serine-rich protein |
| Legumes / soy | Soybeans, tofu, lentils, peanuts | Strong plant sources |
| Nuts & seeds | Almonds, walnuts, sesame, sunflower | Good density |
| Grains | Wheat, oats (whole) | Refining lowers overall protein/amino-acid content |
Because the body makes its own, “getting enough serine” is not a practical dietary concern; the therapeutic doses used in trials (grams per day to hundreds of mg/kg) far exceed anything obtainable from food and are pharmacological, not nutritional.
Intake & Dosage
There is no RDA/AI and no Tolerable Upper Intake Level for L-serine — it is a non-essential amino acid, not a nutrient with a Dietary Reference Intake. Supplemental doses studied in research vary enormously by indication:
- HSAN1: 400 mg/kg/day (≈28 g/day for a 70 kg adult), medically supervised.
- ALS (phase I): 0.5–15 g twice daily (up to 30 g/day).
- Serine-deficiency syndromes: weight-based dosing, often with glycine, titrated to effect and monitored (excessive doses have caused harm).
For healthy adults there is no established or recommended supplemental dose, because no benefit has been demonstrated in serine-replete people. As an amino acid competing for transport, L-serine is generally taken in divided doses. These are doses studied in research, not a personal recommendation.
Safety
L-serine is well tolerated as a dietary component and behaved safely at high doses in the trials that used it. The dose-limiting concern is transport competition — very high, weight-based doses crowd other neutral amino acids out of the brain, and that has caused real harm once.
- Generally safe in the trials that tested it. Both the ALS phase I trial and the HSAN1 RCT used high doses without a safety signal.
- Very high weight-based dosing has caused harm. An infant given ~1400 mg/kg/day had arrested head growth, which reversed on dose reduction.
- It competes with other neutral amino acids. High doses lower methionine, isoleucine and ornithine at the blood–brain barrier.
- GI upset is the common adverse effect. Two ALS participants withdrew for gastrointestinal problems.
- Renal impairment or amino-acid-restricted diets warrant care. High-dose use belongs under medical supervision, and no upper limit is set.
Full Safety & Interactions Detail
L-serine is well tolerated as a dietary component and was “generally safe” in the ALS phase I trial and the HSAN1 RCT at high doses 1,
The most common adverse effects at high doses are gastrointestinal (two ALS participants withdrew for GI problems) 5Reference 5RCTPhase I clinical trial of safety of L-serine for ALS patients — randomised controlled trial (phase I)View study →.
The dose-limiting concern is transport competition: high-dose serine competitively lowers other neutral amino acids (methionine, isoleucine, ornithine) at the blood–brain barrier, and in an infant given ~1400 mg/kg/day this coincided with arrested head growth that reversed on dose reduction 4Reference 4Case reportPhenotypic heterogeneity and adverse effects of serine treatment in 3-phosphoglycerate dehydrogenase deficiency: report on two siblings — case reportView study → — a caution specific to very high, weight-based dosing. People with renal impairment or on amino-acid-restricted diets should be cautious, and high-dose use belongs under medical supervision.
Scope disclosure (REQUIRED honesty):
- Interactions assessed? Partially. No specific drug-interaction studies exist; the main pharmacological interaction is competition with other neutral amino acids for transport (relevant to amino-acid-based therapies and CNS amino-acid balance). No CYP-based interactions are expected for an endogenous amino acid.
- Pregnancy/lactation assessed? No — not evaluated for supplemental use; treated as not established above.
- Upper Limit (UL) established? No UL set. Absence of a UL does not imply unlimited intake is safe — high weight-based doses have caused harm.
Verdict: not established. L-serine as a normal dietary amino acid is part of every pregnancy, but supplemental high-dose use has not been evaluated for safety in pregnancy or lactation. High-dose supplementation should be avoided in pregnancy/lactation without medical supervision.
References
- Fridman, V., Suriyanarayanan, S., Novak, P., et al. (2019). Randomized trial of l-serine in patients with hereditary sensory and autonomic neuropathy type 1 — randomised controlled trial. Neurology. https://pubmed.ncbi.nlm.nih.gov/30626650/
- de Koning, T. J., & Klomp, L. W. (2004). Serine-deficiency syndromes — review. Current Opinion in Neurology. https://pubmed.ncbi.nlm.nih.gov/15021249/
- Coşkun, T., Aydin, H. I., Kiliç, M., et al. (2009). 3-phosphoglycerate dehydrogenase deficiency: a case report of a treatable cause of seizures — case report. The Turkish Journal of Pediatrics. https://pubmed.ncbi.nlm.nih.gov/20196394/
- Häusler, M. G., Jaeken, J., Mönch, E., et al. (2001). Phenotypic heterogeneity and adverse effects of serine treatment in 3-phosphoglycerate dehydrogenase deficiency: report on two siblings — case report. Neuropediatrics. https://pubmed.ncbi.nlm.nih.gov/11571699/
- Levine, T. D., Miller, R. G., Bradley, W. G., et al. (2017). Phase I clinical trial of safety of L-serine for ALS patients — randomised controlled trial (phase I). Amyotrophic Lateral Sclerosis & Frontotemporal Degeneration. https://pubmed.ncbi.nlm.nih.gov/27589995/
- Bradley, W. G., Miller, R. X., Levine, T. D., et al. (2018). Studies of Environmental Risk Factors in Amyotrophic Lateral Sclerosis (ALS) and a Phase I Clinical Trial of L-Serine — clinical trial (phase I). Neurotoxicity Research. https://pubmed.ncbi.nlm.nih.gov/28527102/
- ALSUntangled 38: L-serine (2017) — review. Amyotrophic Lateral Sclerosis & Frontotemporal Degeneration. https://pubmed.ncbi.nlm.nih.gov/27894192/
- Juliá-Palacios, N., Olivella, M., Sigatullina Bondarenko, M., et al. (2024). L-serine treatment in patients with GRIN-related encephalopathy: a phase 2A, non-randomized study — clinical trial. Brain. https://pubmed.ncbi.nlm.nih.gov/38380699/
- Dunlop, R. A., Cox, P. A., Banack, S. A., et al. (2013). The non-protein amino acid BMAA is misincorporated into human proteins in place of L-serine causing protein misfolding and aggregation — in vitro. PLoS ONE. https://pubmed.ncbi.nlm.nih.gov/24086518/
- Xia, C., Suriyanarayanan, S., Gong, Y., et al. (2023). Long-term effects of l-serine supplementation upon a mouse model of diabetic neuropathy — animal study. Journal of Diabetes and Its Complications. https://pubmed.ncbi.nlm.nih.gov/36610321/
- Fridman, V., Kakar, A., Jensen, A., et al. (2026). Human genetic evidence links serine biosynthesis to diabetic peripheral neuropathy — genetic association study (preprint). medRxiv. https://pubmed.ncbi.nlm.nih.gov/42326776/
- Clark, A. J., Kugathasan, U., Baskozos, G., et al. (2021). An iPSC model of hereditary sensory neuropathy-1 reveals L-serine-responsive deficits in neuronal ceramide — in vitro/iPSC. Cell Reports Medicine. https://pubmed.ncbi.nlm.nih.gov/34337561/



