
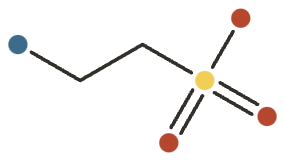
Taurine
Conditionally essential sulfur amino acid with modest, replicated cardiometabolic effects — strongest where there's a deficit to correct.

Taurine at a Glance
Taurine is a sulphur-containing amino acid, though not one used to build proteins. The body makes it from cysteine and it is abundant in shellfish, meat and fish — concentrated in the heart, retina, muscle and brain.
Its role is as a cell-volume regulator and membrane stabiliser, which is why it accumulates in exactly the tissues that work hardest and matters most when they are under load.
What It’s Used For
- Blood pressure — lowers blood pressure.
- Heart-failure adjunct — supports cardiac function alongside standard care, a long-standing use in Japan.
- Blood lipids (triglycerides) — lowers triglycerides.
- Glycemic control — improves glucose handling.
- Endurance & exercise — supports endurance performance.
- Anti-aging / longevity — the claim that returned taurine to attention, from animal work.
- Energy-drink “focus” / cognition — the context most people meet it in.
How It Works
Taurine is an osmolyte: it moves in and out of cells to regulate their volume, stabilising membranes under stress. In cardiac muscle it modulates calcium handling, which is the route to the blood-pressure and heart-failure effects; in the retina and brain it protects cells under metabolic load; and it conjugates bile acids, which is where the lipid effects come from.
It is dosed in grams, well tolerated, and builds up rather than acting acutely.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Taurine is a sulfur-containing, conditionally essential amino acid — one of the most abundant free amino acids in heart, skeletal muscle, brain, and blood cells, yet unusual in that it is never built into proteins. Its evidence base is strongest and most consistent in the cardiometabolic domain: multiple meta-analyses of randomized trials show small but replicated reductions in blood pressure, triglycerides, and fasting glucose, alongside modest gains in cardiac function in heart-failure patients 2Reference 2Meta-analysisEffects of oral taurine supplementation on cardiometabolic risk factors: a meta-analysis and systematic review of randomized clinical trials — [meta-analysis]View study →.
Effects are clearest where there is something to correct — hypertension, dysglycemia, disease-related depletion — and thinner in already-healthy people, which is the central caveat for anyone taking it “for general wellness.” Bioavailability is not the limiting factor here (oral taurine is well absorbed); the limiter is that many trials are small and the popular associations — “calm,” focus, energy-drink benefits, anti-aging — are far softer than the cardiometabolic data. A widely publicized 2023 claim that taurine decline drives aging was directly challenged by human data in 2025.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
The most reproducible human effect. A 2024 systematic review/meta-analysis (20 RCTs, 808 participants) found taurine lowered systolic BP by 4.0 mmHg (95% CI −7.3 to −0.7) and diastolic BP by 1.4 mmHg (−2.5 to −0.4), with no significant adverse effects 1Reference 1Meta-analysisInsights into the cardiovascular benefits of taurine: a systematic review and meta-analysis — [meta-analysis]View study →.
A separate 2024 meta-analysis targeting metabolic syndrome (25 RCTs, 1024 participants) reported essentially the same systolic effect (−4.0 mmHg) and a dose-dependent diastolic reduction 3Reference 3Meta-analysisTaurine reduces the risk for metabolic syndrome: a systematic review and meta-analysis of RCTs — [meta-analysis]View study →, and an earlier 2020 meta-analysis agreed on the direction, noting the blood-pressure benefit was clearest in people with metabolic or hepatic dysregulation 4Reference 4Meta-analysisThe effects of taurine supplementation on obesity, blood pressure and lipid profile: a meta-analysis of RCTs — [meta-analysis]View study →.
Doses ranged 0.5–6 g/day; the standard supplemental form (free taurine) is well absorbed, so form is not a limiting variable.
Gap: Absolute reductions are modest and drawn largely from short trials in hypertensive or metabolically abnormal groups — the effect in a normotensive person is likely smaller.
In people with type 2 diabetes, a 2022 meta-analysis (5 RCTs, 209 participants) found taurine reduced HbA1c (SMD −0.41), fasting blood glucose (SMD −1.28) and HOMA-IR (SMD −0.64) 5Reference 5Meta-analysisThe effects of taurine supplementation on diabetes mellitus in humans: a systematic review and meta-analysis — [meta-analysis]View study →.
A 2024 meta-analysis in adults with overweight/obesity found HbA1c and HOMA-IR improved only in the obese subgroup, with fasting insulin down across the board — i.e. the benefit tracked with how metabolically impaired participants were 6Reference 6Meta-analysisEffect of long-term taurine supplementation on the lipid and glycaemic profile in adults with overweight or obesity: a systematic review and meta-analysis — [meta-analysis]View study →.
A representative 8-week RCT using 3 g/day in T2D patients lowered fasting glucose, HOMA-IR, total and LDL cholesterol versus placebo 7Reference 7RCTThe effects of taurine supplementation on glycemic control and serum lipid profile in patients with type 2 diabetes: a randomized, double-blind, placebo-controlled trial — [RCT]View study →.
Gap: This is a repletion/disease effect — glycemic improvement concentrates in diabetic or insulin-resistant people and should not be read as a benefit for metabolically healthy adults.
Triglyceride-lowering is the most consistent lipid signal. The metabolic-syndrome meta-analysis found triglycerides down 18.3 mg/dL (95% CI −25.6 to −11.0, p<0.001) 3Reference 3Meta-analysisTaurine reduces the risk for metabolic syndrome: a systematic review and meta-analysis of RCTs — [meta-analysis]View study →.
A 2024 long-term meta-analysis (9 RCTs) reported reductions in triglycerides and total cholesterol with low heterogeneity for TG 6Reference 6Meta-analysisEffect of long-term taurine supplementation on the lipid and glycaemic profile in adults with overweight or obesity: a systematic review and meta-analysis — [meta-analysis]View study →.
The 2020 meta-analysis found total cholesterol and triglycerides fell in participants with liver/metabolic dysregulation, while LDL-C and HDL-C were unchanged 4Reference 4Meta-analysisThe effects of taurine supplementation on obesity, blood pressure and lipid profile: a meta-analysis of RCTs — [meta-analysis]View study →.
Mechanistically this fits taurine’s role in conjugating bile acids (taurocholate), which promotes cholesterol turnover.
Gap: LDL and HDL are generally unmoved, and effects are strongest in dyslipidemic populations — it is a triglyceride-and-total-cholesterol nudge, not a broad lipid overhaul.
Taurine concentrates in the myocardium and modulates calcium handling, which motivated the earliest trials. A 1985 double-blind crossover trial reported improved NYHA functional class in congestive heart failure 8Reference 8RCTTherapeutic effect of taurine in congestive heart failure: a double-blind crossover trial — [randomised crossover trial]View study →, and a 2011 randomized placebo-controlled trial found improved exercise capacity in heart-failure patients 9Reference 9RCTEffect of taurine supplementation on exercise capacity of patients with heart failure — [RCT]View study →.
The 2024 cardiovascular meta-analysis pooled these disease-population trials and found a left-ventricular ejection-fraction increase of ~5% and NYHA improvement 1Reference 1Meta-analysisInsights into the cardiovascular benefits of taurine: a systematic review and meta-analysis — [meta-analysis]View study →.
(Note: one frequently cited 2017 heart-failure RCT reporting functional-capacity gains has since been retracted and is excluded here.)
Gap: Trials are small, old, and confined to diagnosed heart-failure patients as an adjunct to standard therapy — this is not evidence for cardiac “support” in healthy people, and cardiac patients should not self-treat.
A 2018 meta-analysis found isolated oral taurine improved endurance performance (Hedges’ g = 0.40, 95% CI 0.12–0.67), with benefit at single doses of 1–6 g and no clear advantage of chronic over acute dosing 10Reference 10Meta-analysisThe effects of an oral taurine dose and supplementation period on endurance exercise performance in humans: a meta-analysis — [meta-analysis]View study →.
A larger 2025 meta-analysis of acute single doses (23 trials, k=69) found a smaller effect (g = 0.25) that was rated low-to-very-low certainty by GRADE owing to heterogeneity and risk of bias 11Reference 11Meta-analysisDoes one shot work? The acute impact of a single taurine dose on exercise performance: a meta-analytic review — [meta-analysis]View study →.
A 2025 network meta-analysis of caffeine and taurine concluded the two are hard to separate when co-formulated, as they usually are in energy drinks 12Reference 12Meta-analysisCaffeine and taurine: a systematic review and network meta-analysis of their individual and combined effects on physical capacity, cognitive function, and physiological markers — [network meta-analysis]View study →.
Gap: The effect is small and inconsistent, certainty is low, and much of the “taurine” performance reputation is really caffeine’s — isolated taurine’s independent ergogenic value is modest at best.
The everyday association of taurine with alertness comes from energy drinks, but the supporting trials nearly always co-administer caffeine and sugar. An early crossover trial of a taurine-and-caffeine drink reported improved cognitive performance and well-being 13Reference 13Clinical trialA taurine and caffeine-containing drink stimulates cognitive performance and well-being — [clinical trial]View study →, and an ingredient-teasing study found the cognitive effects tracked caffeine, with taurine and glucose contributing little independently 14Reference 14RCTDifferential cognitive effects of energy drink ingredients: caffeine, taurine, and glucose — [RCT]View study →.
No robust trial isolates a meaningful cognitive or “calming” effect of taurine alone at typical doses.
Gap: The independent cognitive/anxiolytic contribution of taurine is essentially unestablished in humans — the perceived “focus” is largely caffeine, and the “calm” claim rests on mechanism (weak GABA-A/glycine-receptor activity) rather than trial data.
A high-profile 2023 Science study reported that taurine declines with age and that supplementation extended healthspan and lifespan in worms, mice, and improved markers in monkeys 15Reference 15Taurine deficiency as a driver of aging — [animal/experimental]View study →.
This drove a wave of longevity marketing. However, the human case is weaker. A 2025 cross-sectional study of 137 physically inactive and active men aged 20–93 found no association between circulating taurine and age, muscle mass, strength, physical performance, or mitochondrial function, directly challenging taurine deficiency as a primary driver of human aging 16Reference 16Clinical trialExperimental evidence against taurine deficiency as a driver of aging in humans — [cross-sectional human study]View study →.
A 2025 NIA-led Science analysis questioned whether taurine is a reliable aging biomarker at all 17Reference 17Is taurine an aging biomarker? — [analysis/commentary]View study →.
Gap: The animal data are real but do not translate cleanly to humans; the current human evidence weighs against taurine deficiency as a driver of aging, so longevity claims are premature.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Cell-volume osmoregulation | Cytoprotective; stabilizes membranes | Cardiacmetabolicgeneral |
| Cardiomyocyte Ca²⁺ handling | Modulates calcium flux / contractility | Heart failureblood pressure |
| Bile-acid conjugation (taurocholate) | Promotes cholesterol → bile-acid turnover | Lipidstriglycerides |
| Antioxidant / taurine-chloramine | Dampens oxidative stress and inflammation | Metabolicvascularaging (preclinical) |
| Mitochondrial tRNA modification (5-taurinomethyluridine) | Supports mitochondrial translation / energy metabolism | Exercisemetabolic |
| GABA-A / glycine receptors (weak agonism) | Mild inhibitory neuromodulation | Proposed “calm” (thinly evidenced) |
Pharmacokinetics
Oral taurine is absorbed via the sodium-and-chloride-dependent taurine transporter (TauT/SLC6A6) in the gut and, as a small, water-soluble molecule, has good oral bioavailability — so unlike minerals, form is not the decision-relevant variable (supplements are simply free taurine). Plasma concentrations peak roughly 1–2.5 hours after a gram-scale dose and return toward baseline within hours (elimination half-life on the order of ~1 hour), with the kidney tightly regulating excretion to defend a large tissue pool held in muscle, heart, and brain. Endogenous synthesis from cysteine (via cysteine-sulfinic-acid decarboxylase) is comparatively low in humans, which is why dietary intake and — for people eating little animal protein — supplementation measurably influence status. Food has little effect on absorption, and because plasma clears quickly, disease trials commonly split the daily dose (e.g. 500 mg–1 g, two to three times daily).
Clinical trials
Taurine has been tested in dozens of small-to-moderate randomized trials, concentrated in cardiovascular, metabolic/diabetic, and exercise settings; because it is an inexpensive, off-patent molecule, there is little large-scale industry-sponsored trial activity, and most evidence comes from investigator-led studies pooled in meta-analyses. Longevity and metabolic-aging trials in humans are only now beginning.
| Completed | Planned / ongoing | Terminated | Preclinical |
|---|---|---|---|
| ~40+(mostly small RCTs) | ~10 | few | extensive(animal/in vitro) |
Last checked: July 2026.
Dietary Sources
Taurine is found almost exclusively in animal-source foods — it is essentially absent from plants, so intake tracks meat, fish, shellfish, and (to a lesser degree) dairy consumption. Shellfish and dark poultry meat are the richest common sources. Because humans synthesize only modest amounts endogenously (from cysteine), dietary intake meaningfully affects status, and strict vegans/vegetarians tend to have lower circulating and urinary taurine than omnivores. A typical omnivorous diet supplies on the order of tens to a few hundred milligrams per day — well below the gram-level doses used in supplement trials.
| Food (approx. per 100 g) | Taurine |
|---|---|
| Scallops / shellfish | very high (several hundred mg) |
| Dark chicken/turkey meat | high (~100–300 mg) |
| Fish (e.g. tuna, white fish) | moderate–high |
| Red meat (beef, pork) | moderate (~40–80 mg) |
| Dairy (milk) | low |
| Plant foods | negligible |
Values are approximate and vary by species and cooking; see the NIH ODS and food-composition databases for specifics. Cooking method (boiling leaches taurine into the liquid) and a plant-based diet both lower intake.
Dosage & Intake
Taurine is conditionally essential — the body makes some, but requirements can outstrip synthesis in infancy, illness, or on a low-animal-protein diet — so there is no RDA or Adequate Intake the way there is for vitamins and minerals, and no formal Tolerable Upper Intake Level. Doses studied in research (not personal recommendations):
- Cardiovascular / blood pressure: commonly ~1.5 g/day (e.g. 500 mg three times daily).
- Metabolic / glycemic: often 3 g/day, sometimes up to 6 g/day.
- Exercise: single doses of 1–6 g, typically ~1–2 g before exercise.
Because taurine is a small, water-soluble molecule that is well absorbed, form is not a meaningful variable (supplements are simply free taurine — there is no elemental-versus-compound weight issue as there is with minerals). Plasma clears within a few hours, so disease trials often split the dose across the day. These ranges are informational and reflect doses studied in research, not a personal recommendation.
Safety
Taurine is one of the better-tolerated things here — no serious adverse effects in the pooled cardiovascular and metabolic meta-analyses at 0.5–6 g/day. What matters is not the compound itself but what it adds to: it modestly lowers blood pressure and glucose, so the practical caution is with medications doing the same job.
- Well tolerated at 0.5–6 g/day. No serious adverse effects in the pooled trials; mild nausea or loose stool at higher doses.
- Additive with blood-pressure and glucose-lowering drugs. Monitor if combining with antihypertensives or antidiabetics.
- Renal impairment warrants care. Taurine is renally excreted and its transporter is kidney-regulated — involve a clinician.
- Cardiac patients should not self-treat. Heart failure and other cardiac conditions need clinician involvement.
- No formal upper limit. Up to 6 g/day has been used in trials, but absence of a limit is not evidence of long-term safety.
Full Safety & Interactions Detail
Taurine has a low toxicity profile and was generally well tolerated in the cited trials at 0.5–6 g/day, with no serious adverse effects reported in the pooled cardiovascular and metabolic meta-analyses. The most common complaints at higher doses are mild gastrointestinal (nausea, loose stool). Key considerations:
- Additive pharmacological effects: because taurine modestly lowers blood pressure and glucose, it could add to the effect of antihypertensive and glucose-lowering / antidiabetic medications — monitor if combining.
- Renal handling: taurine is renally excreted and its transporter is regulated by the kidney; people with significant renal impairment should be cautious and involve a clinician.
- Lithium (theoretical): as with other agents that affect renal handling and fluid balance, caution is reasonable, though direct interaction data are limited.
- Cardiac patients: those with heart failure or other cardiac conditions should not self-treat and should involve a clinician.
Scope of this safety review (for honesty, not a claim):
- Interactions assessed? Partially — screened for additive antihypertensive/antidiabetic effects, renal handling, and lithium; a comprehensive drug-interaction review (e.g. CYP-mediated) was not performed and is not expected to be a major route for this small water-soluble molecule.
- Pregnancy/lactation assessed? Yes (limited) — dietary/physiological taurine is well established; supplemental high-dose safety is not established.
- Upper Limit? No formal UL. Up to 6 g/day has been used in trials without serious adverse effects, but absence of a limit is not evidence that any dose is safe long-term.
Verdict: insufficient data — avoid high-dose supplementation. Taurine is a normal constituent of breast milk and is added to infant formula because infants have limited synthesis, so background dietary amounts are clearly compatible with pregnancy and lactation. However, supplemental gram-level doses have not been studied for safety in pregnant or breastfeeding people, so high-dose supplementation cannot be called safe and is best avoided pending data.
References
- Tzang, C. C., Lin, W. C., Lin, L. H., et al. (2024). Insights into the cardiovascular benefits of taurine: a systematic review and meta-analysis — [meta-analysis]. Nutrition Journal. https://pubmed.ncbi.nlm.nih.gov/39148075/
- Nie, Z., Liu, Y., Zhang, M., et al. (2025). Effects of oral taurine supplementation on cardiometabolic risk factors: a meta-analysis and systematic review of randomized clinical trials — [meta-analysis]. Nutrition Reviews. https://pubmed.ncbi.nlm.nih.gov/41275513/
- Tzang, C. C., Chi, L. Y., Lin, L. H., et al. (2024). Taurine reduces the risk for metabolic syndrome: a systematic review and meta-analysis of RCTs — [meta-analysis]. Nutrition & Diabetes. https://pubmed.ncbi.nlm.nih.gov/38755142/
- Guan, L., & Miao, P. (2020). The effects of taurine supplementation on obesity, blood pressure and lipid profile: a meta-analysis of RCTs — [meta-analysis]. European Journal of Pharmacology. https://pubmed.ncbi.nlm.nih.gov/32871172/
- Tao, X., Zhang, Z., Yang, Z., & Rao, B. (2022). The effects of taurine supplementation on diabetes mellitus in humans: a systematic review and meta-analysis — [meta-analysis]. Food Chemistry (Oxford). https://pubmed.ncbi.nlm.nih.gov/35769396/
- Sun, Q., Wang, J., Wang, H., et al. (2024). Effect of long-term taurine supplementation on the lipid and glycaemic profile in adults with overweight or obesity: a systematic review and meta-analysis — [meta-analysis]. Nutrients. https://pubmed.ncbi.nlm.nih.gov/39796489/
- Maleki, V., Alizadeh, M., Esmaeili, F., & Mahdavi, R. (2020). The effects of taurine supplementation on glycemic control and serum lipid profile in patients with type 2 diabetes: a randomized, double-blind, placebo-controlled trial — [RCT]. Amino Acids. https://pubmed.ncbi.nlm.nih.gov/32472292/
- Azuma, J., Sawamura, A., Awata, N., et al. (1985). Therapeutic effect of taurine in congestive heart failure: a double-blind crossover trial — [randomised crossover trial]. Clinical Cardiology. https://pubmed.ncbi.nlm.nih.gov/3888464/
- Beyranvand, M. R., Kadkhodai Khalafi, M., Roshan, V. D., et al. (2011). Effect of taurine supplementation on exercise capacity of patients with heart failure — [RCT]. Journal of Cardiology. https://pubmed.ncbi.nlm.nih.gov/21334852/
- Waldron, M., Patterson, S. D., Tallent, J., & Jeffries, O. (2018). The effects of an oral taurine dose and supplementation period on endurance exercise performance in humans: a meta-analysis — [meta-analysis]. Sports Medicine. https://pubmed.ncbi.nlm.nih.gov/29546641/
- Deng, H., Song, T., Yin, M., et al. (2025). Does one shot work? The acute impact of a single taurine dose on exercise performance: a meta-analytic review — [meta-analysis]. Scandinavian Journal of Medicine & Science in Sports. https://pubmed.ncbi.nlm.nih.gov/40852891/
- Deng, H., Wang, L., Liu, P., et al. (2025). Caffeine and taurine: a systematic review and network meta-analysis of their individual and combined effects on physical capacity, cognitive function, and physiological markers — [network meta-analysis]. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/41032459/
- Seidl, R., Peyrl, A., Nicham, R., & Hauser, E. (2000). A taurine and caffeine-containing drink stimulates cognitive performance and well-being — [clinical trial]. Amino Acids. https://pubmed.ncbi.nlm.nih.gov/11140366/
- Giles, G. E., Mahoney, C. R., Brunyé, T. T., et al. (2012). Differential cognitive effects of energy drink ingredients: caffeine, taurine, and glucose — [RCT]. Pharmacology, Biochemistry, and Behavior. https://pubmed.ncbi.nlm.nih.gov/22819803/
- Singh, P., Gollapalli, K., Mangiola, S., et al. (2023). Taurine deficiency as a driver of aging — [animal/experimental]. Science. https://pubmed.ncbi.nlm.nih.gov/37289866/
- Marcangeli, V., Cefis, M., Hammad, R., et al. (2025). Experimental evidence against taurine deficiency as a driver of aging in humans — [cross-sectional human study]. Aging Cell. https://pubmed.ncbi.nlm.nih.gov/41061678/
- Fernandez, M. E., Bernier, M., Price, N. L., et al. (2025). Is taurine an aging biomarker? — [analysis/commentary]. Science. https://pubmed.ncbi.nlm.nih.gov/40472098/



