

Sources · 4
Where Does It Come From?

Concentration
Content by Source
Reported concentrations across the plants that contain vitamin B9 — the bar marks the typical level, the line shows the reported range.
Literature figures for varying plant parts and preparations. Read them as a comparative guide, not exact assays.
Vitamin B9 at a Glance
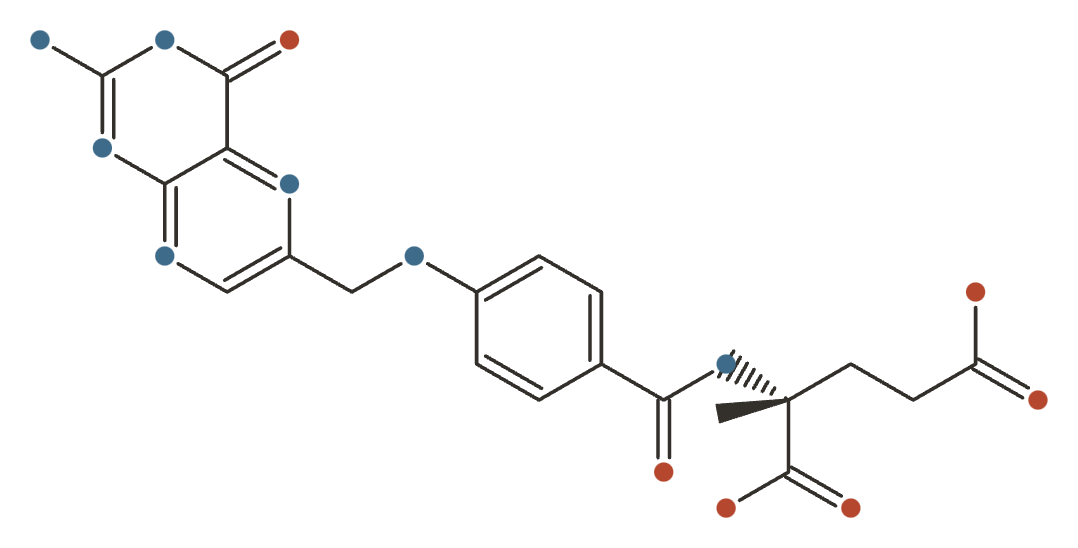
Vitamin B9 is folate — the form in leafy greens, legumes and liver — and folic acid, the more stable synthetic form used in supplements and in fortified flour.
Its job is carrying and donating one-carbon units, the single-atom building blocks needed to make DNA. That makes it indispensable wherever cells divide quickly, which is why it matters most in pregnancy and in blood formation, and why folate fortification is one of the most successful public health measures ever implemented.
What It’s Used For
- Neural-tube-defect prevention — prevents spina bifida and anencephaly when taken before conception and in early pregnancy.
- Folate-deficiency anemia — corrects the large-cell anemia deficiency causes.
- Homocysteine lowering — lowers homocysteine more than any other B vitamin.
- Stroke prevention — reduces stroke risk, most clearly in unfortified populations.
- Depression (adjunctive L-methylfolate) — used as an antidepressant adjunct in its methylated form.
- Cognition in older adults — studied for cognitive function with the other B vitamins.
How It Works
Folate cycles through several forms, each carrying a one-carbon unit at a different oxidation state. Those units build the purines and thymidine that DNA is made from — so when folate runs short, cells that divide fastest fail first, producing the oversized red cells of megaloblastic anemia and, in an embryo, a neural tube that does not close.
The same cycle intersects with B12 at methionine synthase, which is why the two vitamins are always discussed together and why folate can mask a B12 deficiency. Folic acid needs enzymatic reduction before use, and people carrying common MTHFR variants convert it less efficiently — which is the rationale for the pre-converted L-methylfolate form.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Vitamin B9 (folate) is a water-soluble B vitamin and the coenzyme backbone of one-carbon metabolism — the pathway that builds DNA and RNA bases, matures red blood cells, and (with vitamin B12) remethylates homocysteine to methionine. Its evidence base is unusually clean at one end and unusually oversold at the other: periconceptional supplementation to prevent neural-tube defects is among the best-proven interventions in preventive medicine, while the “lower your homocysteine, protect your heart” story that drove a decade of supplementation has largely collapsed in large trials. A recurring theme is that folate corrects a deficiency dramatically but adds little on top of adequacy — and that in fortified countries most people are already replete. Form matters at the margins: synthetic folic acid is more bioavailable than food folate but must be reduced by the body, whereas L-methylfolate (5-MTHF) is the already-active circulating form, relevant mainly to people who carry MTHFR variants or take folate-depleting drugs.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
The MRC Vitamin Study (1991), a double-blind RCT in 1,817 women with a prior affected pregnancy, found 4 mg/day folic acid before and in early pregnancy cut recurrent neural-tube defects by ~72% 1Reference 1RCTPrevention of neural tube defects: results of the Medical Research Council Vitamin Study — [randomised controlled trial]View study →.
The Hungarian trial of Czeizel & Dudás (1992) extended this to first occurrence: a periconceptional multivitamin containing 0.8 mg folic acid essentially eliminated NTDs in ~4,750 women versus trace-element controls 2Reference 2RCTPrevention of the first occurrence of neural-tube defects by periconceptional vitamin supplementation — [randomised controlled trial]View study →.
These results drove mandatory folic-acid fortification of grain in the US, Canada and dozens of countries, which measurably lowered spina bifida and anencephaly rates. The effect is causal, large, and largely dose-secured at ordinary supplemental amounts; higher (4–5 mg) doses are reserved for prior-NTD pregnancies and some anti-epileptic drug users.
Gap: it must be taken before the neural tube closes (~28 days post-conception), so it only helps women supplementing before they may know they are pregnant — an intake-timing problem, not an efficacy one.
Folate is required for red-cell maturation; a shortfall produces megaloblastic (macrocytic) anemia indistinguishable on blood film from B12 deficiency. Oral folate reliably corrects the hematology of true folate deficiency, which arises from poor intake, malabsorption (celiac, alcohol), pregnancy demand, or folate-depleting drugs (methotrexate, some anticonvulsants). This is textbook repletion therapy rather than a “benefit” in replete people.
Gap: correcting the anemia with folate alone can mask coexisting B12 deficiency while its neurological damage progresses — B12 status must be checked first. This is entirely deficiency-dependent.
Folic acid is the single most effective nutrient for lowering plasma total homocysteine, typically reducing it ~20–25% at 0.5–5 mg/day, with most of the effect achieved by ~0.8 mg; adding B12 and B6 gives a further small drop 5,
The biochemistry — 5-MTHF donating a methyl group so B12 can remethylate homocysteine to methionine — is robust and reproducible. The problem is that lower homocysteine has not translated into the vascular protection the “homocysteine hypothesis” predicted (see stroke and the cardiovascular caveat).
Gap: homocysteine is a validated biomarker response, not a validated clinical endpoint here — lowering it does not, in fortified populations, reduce heart attacks.
The China Stroke Primary Prevention Trial (CSPPT, 2015) randomized 20,702 hypertensive adults without folic-acid fortification to enalapril plus 0.8 mg folic acid versus enalapril alone; first stroke fell from 3.4% to 2.7% over ~4.5 years (HR ~0.79) 4Reference 4RCTEfficacy of folic acid therapy in primary prevention of stroke among adults with hypertension in China (CSPPT) — [randomised controlled trial]View study →.
An earlier meta-analysis of folic-acid RCTs found a modest overall stroke reduction concentrated in trials with low baseline folate and no fortification 5Reference 5Meta-analysisEfficacy of folic acid supplementation in stroke prevention: a meta-analysis — [meta-analysis]View study →.
The signal is real but population-specific.
Gap: the benefit appears only where baseline folate is low and grain is unfortified; trials in fortified countries (US/Canada) show no stroke benefit, so this does not generalize to replete populations.
Low folate status is associated with poorer antidepressant response, motivating L-methylfolate as an add-on. In a randomized trial, 15 mg/day L-methylfolate added to an SSRI improved response among inadequate responders versus placebo augmentation, with the 15 mg (not 7.5 mg) arm carrying the signal 6Reference 6RCTEffect of adjunctive L-methylfolate 15 mg among inadequate responders to SSRIs in depressed patients — [randomised controlled trial]View study →. Results across trials are small and inconsistent, and much of the L-methylfolate literature is linked to the product’s manufacturer.
Gap: benefit is modest, concentrated in subgroups (low folate, obesity, inflammation) rather than depression generally, and the strongest data come from industry-associated trials.
In the Dutch FACIT trial (2007), 800 mcg/day folic acid for 3 years in 818 older adults with elevated homocysteine and low-normal folate (an unfortified setting) improved memory and information-processing speed relative to placebo 7Reference 7RCTEffect of 3-year folic acid supplementation on cognitive function in older adults in the FACIT trial — [randomised controlled trial]View study →. This is one well-conducted RCT in a specific population; trials in folate-replete elders have generally not shown cognitive benefit, and folic acid has not been shown to prevent dementia.
Gap: a single positive RCT restricted to older adults with raised homocysteine and no fortification — it does not support routine folate for cognition in replete people.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Tetrahydrofolate (THF) one-carbon pool | Donates single-carbon units for purine and thymidylate synthesis | DNA/RNA synthesiscell divisionNTD preventionanemia |
| 5-methyl-THF → methionine synthase (B12-dependent) | Remethylates homocysteine to methionine; regenerates SAM methyl donor | Homocysteine loweringmethylation reactions |
| Thymidylate synthase / dUMP→dTMP | Supplies methyl for thymidine; deficiency causes uracil misincorporation | Megaloblastic anemiarapidly dividing tissue |
| MTHFR enzyme (C677T variant) | Converts 5,10-methylene-THF to 5-methyl-THF; variant lowers activity | Rationale for L-methylfolate in variant carriers |
Pharmacokinetics
Synthetic folic acid taken on an empty stomach is ~85–100% bioavailable; natural food folate is roughly 50% as available, which is why intakes are expressed in dietary folate equivalents (DFE): 1 mcg DFE = 1 mcg food folate = 0.6 mcg folic acid from fortified food/supplements with meals = 0.5 mcg folic acid on an empty stomach 11Reference 11Conversion of calcium-L-methylfolate and (6S)-5-methyltetrahydrofolic acid glucosamine salt into dietary folate equivalents — [regulatory opinion]View study →. Absorbed folic acid is reduced in the intestine and liver to THF and 5-methyl-THF, the main circulating form; the liver stores roughly 10–30 mg, about half the body’s total, giving a buffer of months before deficiency appears. Excess is renally excreted. At high supplemental doses (typically above ~200–400 mcg per dose) the intestinal reduction capacity is exceeded and unmetabolized folic acid appears in blood — the basis for the B12-masking concern and for interest in L-methylfolate, which bypasses reduction. Plasma half-life of a folate dose is short (hours), but tissue turnover is slow.
Clinical trials
Folate is off-patent and cheaply fortified, so most large trials are publicly funded (fortification epidemiology, CSPPT, homocysteine/cardiovascular RCTs); the main commercially sponsored activity is around branded L-methylfolate (5-MTHF) products.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~40+major RCTs | Several(fortification, pregnancy) | Few | Extensive(>1000s) |
Last checked: July 2026.
Dietary Sources
Folate is concentrated in dark leafy greens, legumes, liver and certain vegetables and fruit; the name derives from the Latin folium (“leaf”). Since mandatory fortification, enriched grain products (bread, pasta, cereal, rice) are also a major source in many countries and supply the more-bioavailable synthetic folic acid. Natural food folate is roughly half as bioavailable as folic acid, and is easily destroyed by prolonged cooking, boiling (it leaches into water) and food processing — which is why refined, unfortified grains are poor sources.
| Food | Serving | Folate (approx.) |
|---|---|---|
| Beef liver | 85 g | ~215 mcg DFE |
| Lentils / chickpeas (cooked) | ½ cup | ~180 mcg DFE |
| Spinach (cooked) | ½ cup | ~130 mcg DFE |
| Asparagus | ½ cup | ~130 mcg DFE |
| Fortified breakfast cereal | 1 serving | ~100–400 mcg DFE |
| Avocado | ½ fruit | ~60 mcg DFE |
| Broccoli (cooked) | ½ cup | ~50 mcg DFE |
| Orange | 1 medium | ~30 mcg DFE |
Values approximate; from the NIH ODS Folate fact sheet 10Reference 10ReviewFolate — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/Folate-HealthProfessional/View study →. Intakes are expressed in dietary folate equivalents (DFE) because folic acid is ~1.7× more bioavailable than food folate.
Dosage & Intake
Reference intakes (adults): the RDA is 400 mcg DFE/day, rising to 600 mcg DFE/day in pregnancy and 500 mcg DFE in lactation 10Reference 10ReviewFolate — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/Folate-HealthProfessional/View study →. Because of the neural-tube-defect window, women who could become pregnant are advised to get 400 mcg/day of folic acid from fortified food or a supplement in addition to food folate — the supplemental amount, not just total intake, is what the trial evidence supports 1,
Supplemental ranges studied: 400–800 mcg/day (general/prenatal), 0.8 mg (stroke and homocysteine trials 4,
DFE conversion (important): 1 mcg DFE = 1 mcg food folate = 0.6 mcg folic acid taken with food = 0.5 mcg folic acid on an empty stomach. A “400 mcg folic acid” supplement label therefore equals ~667 mcg DFE. Form: folic acid and L-methylfolate (5-MTHF) are both effective at raising folate status; 5-MTHF is the already-active form and is marketed to MTHFR-variant carriers, but for most people the practical difference is small and the choice is mainly about avoiding unmetabolized folic acid at high doses.
These are doses studied in research, not a personal recommendation.
Safety
Folate has an unusually wide safety margin, and the dose-limiting concern is not toxicity but masking — high-dose folic acid can correct the anemia of B12 deficiency while its neurological damage continues undetected.
- Wide safety margin. Food folate has no upper limit and no reported toxicity.
- Actively protective in pregnancy. Periconceptional folic acid sharply reduces neural-tube defects.
- Can mask vitamin B12 deficiency. Assess B12 status before high-dose folate, especially in older adults and vegans.
- The 1,000 mcg/day limit is a masking limit, not a toxicity one. It applies only to synthetic folic acid from supplements and fortified food.
- Unmetabolized folic acid at large doses is still under study. A growth-promotion signal appears in the colorectal-adenoma data, but overall cancer incidence was not raised.
- Folate antagonists and depleters. Methotrexate, anticonvulsants, sulfasalazine, trimethoprim and chronic alcohol use.
Full Safety & Interactions Detail
Folate has a wide safety margin; food folate has no upper limit and no reported toxicity. The UL of 1,000 mcg/day applies only to synthetic folic acid from supplements and fortified food. The dose-limiting concern is not folate toxicity but masking: high folic-acid intake can correct the megaloblastic anemia of vitamin B12 deficiency while the neurological damage of that deficiency continues undetected — so B12 status should be assessed before high-dose folate, especially in older adults and vegans. High circulating unmetabolized folic acid at large doses is a topic of ongoing research (possible immune and, from the colorectal-adenoma data, growth-promotion signals 9Reference 9RCTFolic acid for the prevention of colorectal adenomas: a randomized clinical trial — [RCT]View study →) but is not established as harmful at ordinary intakes; overall cancer incidence was not raised in a large meta-analysis 3Reference 3Meta-analysisEffects of folic acid supplementation on overall and site-specific cancer incidence during randomised trials — [meta-analysis]View study →.
Interactions: folate antagonists and depleters include methotrexate (folinic-acid, not folic-acid, rescue is used deliberately in oncology; folate supplementation is standard in low-dose methotrexate for rheumatoid arthritis), anticonvulsants (phenytoin, carbamazepine, valproate — mutual depletion; folate may modestly lower phenytoin levels), sulfasalazine and trimethoprim (dihydrofolate reductase inhibition), and chronic alcohol use. Space folate and these drugs and monitor as clinically indicated.
Scope of this safety review (for honesty, not a claim):
- Interactions assessed? Yes — methotrexate, anticonvulsants (phenytoin/carbamazepine/valproate), sulfasalazine, trimethoprim, and alcohol are the principal folate-depleting or antagonizing agents.
- Pregnancy/lactation assessed? Yes — folate is actively recommended periconceptionally and in pregnancy; protective, not merely tolerated.
- Upper Limit? Yes — 1,000 mcg/day for synthetic folic acid (supplements/fortified food); no UL for food folate. This is a masking limit, not a toxicity limit.
Verdict: recommended and protective. Adequate folate before conception and in the first trimester is one of the best-evidenced prenatal interventions, sharply reducing neural-tube defects 1,
References
- MRC Vitamin Study Research Group. (1991). Prevention of neural tube defects: results of the Medical Research Council Vitamin Study — [randomised controlled trial]. Lancet. https://pubmed.ncbi.nlm.nih.gov/1677062/
- Czeizel, A. E., & Dudás, I. (1992). Prevention of the first occurrence of neural-tube defects by periconceptional vitamin supplementation — [randomised controlled trial]. New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/1307234/
- Vollset, S. E., et al. (2013). Effects of folic acid supplementation on overall and site-specific cancer incidence during randomised trials — [meta-analysis]. Lancet. https://pubmed.ncbi.nlm.nih.gov/23352552/
- Huo, Y., et al. (2015). Efficacy of folic acid therapy in primary prevention of stroke among adults with hypertension in China (CSPPT) — [randomised controlled trial]. JAMA. https://pubmed.ncbi.nlm.nih.gov/25771069/
- Wang, X., et al. (2007). Efficacy of folic acid supplementation in stroke prevention: a meta-analysis — [meta-analysis]. Lancet. https://pubmed.ncbi.nlm.nih.gov/17544768/
- Papakostas, G. I., et al. (2014). Effect of adjunctive L-methylfolate 15 mg among inadequate responders to SSRIs in depressed patients — [randomised controlled trial]. Journal of Clinical Psychiatry. https://pubmed.ncbi.nlm.nih.gov/24813065/
- Durga, J., et al. (2007). Effect of 3-year folic acid supplementation on cognitive function in older adults in the FACIT trial — [randomised controlled trial]. Lancet. https://pubmed.ncbi.nlm.nih.gov/17240287/
- Martí-Carvajal, A. J., et al. (2017). Homocysteine-lowering interventions for preventing cardiovascular events — [Cochrane systematic review]. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/28816346/
- Cole, B. F., et al. (2007). Folic acid for the prevention of colorectal adenomas: a randomized clinical trial — [RCT]. JAMA. https://pubmed.ncbi.nlm.nih.gov/17551129/
- National Institutes of Health, Office of Dietary Supplements. (2024). Folate — Fact Sheet for Health Professionals — [authoritative review]. https://ods.od.nih.gov/factsheets/Folate-HealthProfessional/
- EFSA NDA Panel. (2022). Conversion of calcium-L-methylfolate and (6S)-5-methyltetrahydrofolic acid glucosamine salt into dietary folate equivalents — [regulatory opinion]. EFSA Journal. https://pubmed.ncbi.nlm.nih.gov/36034319/



