
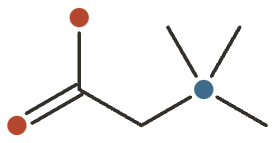
Betaine (TMG)
Betaine (trimethylglycine) is a methyl donor that lowers homocysteine and an osmolyte studied for strength and power output.

Betaine (TMG) at a Glance
Betaine is glycine carrying three methyl groups — hence the alternative name trimethylglycine, usually shortened to TMG. It was first isolated from sugar beet, which is where the name comes from (Beta vulgaris), and it remains a by-product of sugar refining today.
It does two quite different jobs, and most of the confusion around this supplement comes from people meeting one and assuming it explains the other.
The first is methyl donation. Betaine hands a methyl group to homocysteine, converting it back into methionine. That reaction is one of only two routes the body has for clearing homocysteine — the other runs on folate and B12 — and it reliably lowers blood homocysteine, which is the basis for betaine’s genuine clinical use in homocystinuria, a rare inherited disorder where homocysteine accumulates to dangerous levels.
The second is osmolyte function. Betaine is one of a small class of molecules cells accumulate to hold their water balance under stress without disrupting protein structure. Kidney medulla cells depend on it. So, more speculatively, might muscle cells under the osmotic stress of hard training — which is the rationale behind betaine’s presence in pre-workout formulas.
The honest summary: the homocysteine effect is solid and mechanistically clean; the performance claim is plausible, has a real trial literature, and is not settled.
What It’s Used For
- Lowering homocysteine — the best-established effect, and the one with a regulatory footprint. A reliable biochemical result; whether it improves cardiovascular outcomes is a separate and much less favourable question.
- Homocystinuria treatment — a genuine prescription indication (as Cystadane), and a serious inherited condition rather than a wellness use.
- Strength & power output — the reason it appears in pre-workout products. Real, small, and inconsistent across outcome measures.
- Liver / fatty liver disease — a coherent mechanism, encouraging pilots, and one properly powered RCT that was negative.
Worth separating carefully: betaine HCl is a different product. It is sold as a stomach-acid supplement and has nothing to do with the methyl-donor or performance uses described here. The two are routinely confused on retail sites.
And one thing betaine does not do: improve body composition. Fat mass, lean mass and BMI were all null in meta-analysis.
How It Works
As a methyl donor. Homocysteine sits at a metabolic junction: it can be converted onward to cysteine, or recycled back to methionine. The recycling step needs a methyl group, and betaine-homocysteine methyltransferase supplies it directly from betaine — a route that runs largely in liver and kidney and works independently of folate and B12. This is why betaine lowers homocysteine even when the folate pathway is impaired, and why it is used in homocystinuria. Downstream, more methionine means more S-adenosylmethionine, the universal methyl donor for DNA, protein and phospholipid methylation.
As an osmolyte. Betaine is a zwitterion that cells can accumulate to high concentrations without interfering with enzyme function — which is exactly what an osmolyte needs to be. Kidney medulla cells use it constantly to survive the extreme salt gradients they work in. The training hypothesis extends this: muscle cells under osmotic and thermal stress may hold hydration better with betaine present, and better-hydrated cells resist fatigue and may signal more strongly for growth. Plausible, and the honest word for its status in muscle is proposed.
In the liver, betaine’s methyl donation feeds phosphatidylcholine synthesis, and phosphatidylcholine is required to package fat into VLDL for export. Insufficient methyl supply means fat accumulates in hepatocytes instead of leaving — the mechanistic link to fatty liver disease.
One curiosity that matters practically: gut bacteria convert some betaine to trimethylamine, the compound responsible for the fishy odour associated with high doses of choline and carnitine. It is the same chemistry, and the reason a small number of people notice a smell at higher intakes.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
Betaine (trimethylglycine, TMG) is an amino-acid-derived methyl donor and organic osmolyte, and its evidence base splits cleanly along those two jobs. As a methyl donor it lowers plasma homocysteine reliably and dose-dependently — a clean biochemical effect with a regulatory footprint and a genuine clinical use in the inherited disorder homocystinuria. As an osmolyte it has become a pre-workout ingredient, where a real but inconsistent trial literature suggests a small effect on lower-body strength and little else. Two caveats run through everything below: the homocysteine effect is well-established but its cardiovascular value is not, and at 6 g/day betaine measurably raises LDL and total cholesterol — a trade-off that matters precisely for the people taking it on cardiovascular grounds. The form studied is betaine anhydrous; betaine HCl (a stomach-acid product) is unrelated.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the reliable effect. A meta-analysis of 5 placebo-controlled RCTs (≥4 g/day, 6–24 weeks) found betaine lowered plasma homocysteine by a pooled 1.23 µmol/L (95% CI −1.61 to −0.85) 3Reference 3Meta-analysisBetaine supplementation decreases plasma homocysteine in healthy adult participants: a meta-analysisView study →.
A double-blind crossover dose-response study showed the effect is acute and dose-linear: single 3 g and 6 g doses lowered homocysteine within 2 hours, while 1 g did not 1Reference 1RCTOrally administered betaine has an acute and dose-dependent effect on serum betaine and plasma homocysteine concentrations in healthy humans — randomized controlled trialView study →.
Across the literature, 6 g/day lowers fasting homocysteine by up to about 20%, and betaine also blunts the post-methionine-load spike by up to 50% where folate does not 2Reference 2ReviewEffects of betaine intake on plasma homocysteine concentrations and consequences for health — reviewView study →.
Critically, this works independently of the folate/B12 pathway and is seen in people with normal homocysteine, so it is a general effect rather than a deficiency-only one. EFSA’s panel accepted a cause-and-effect relationship for betaine and normal homocysteine metabolism at 1.5 g/day 4Reference 4Scientific opinion on the substantiation of health claims related to betaine and contribution to normal homocysteine metabolismView study →.
Gap: lowering homocysteine is a biochemical result, not a proven clinical benefit — homocysteine-lowering trials, mostly with B vitamins, have generally failed to reduce cardiovascular events, and betaine’s own lipid effect may work against it 11,
Betaine is a genuine prescription therapy for homocystinuria — the inherited cystathionine β-synthase deficiency where homocysteine accumulates to dangerous levels — marketed as Cystadane. The foundational report treated 10 pyridoxine-unresponsive patients with 6 g/day added to conventional therapy: all had substantial, statistically significant falls in plasma homocysteine and rises in cysteine, with clinical improvement in six and no adverse effects 13Reference 13Homocystinuria — the effects of betaine in the treatment of patients not responsive to pyridoxineView study →.
Betaine is embedded in the international management guidelines for CBS deficiency and the cobalamin-related remethylation disorders 14,
Gap: this is a rare-disease indication managed by metabolic clinicians, not a wellness use; the supporting data are largely uncontrolled case series rather than RCTs — appropriate to an orphan condition, but a lower evidence tier.
The reason betaine is in pre-workouts, and the least settled of its real uses. A 2024 systematic review and meta-analysis (17 studies, 317 participants) found a significant effect on maximal strength (SMD 0.47, 95% CI 0.04–0.89), driven by the lower body (SMD 0.49), plus improved vertical jump after excluding a low-quality trial — but no effect on upper-body strength, cycling sprint power, or muscular endurance 5Reference 5Meta-analysisEffects of chronic betaine supplementation on exercise performance: systematic review and meta-analysisView study →.
An earlier systematic review was more sceptical: of 7 excellent-quality RCTs, only 2 reported any strength or power gain 6Reference 6Systematic reviewEffects of betaine supplementation on muscle strength and power: a systematic reviewView study →.
Individual trials are mixed — a crossover in resistance-trained men (2.5 g/day, 14 days) found a roughly 6.5% rise in bench-press repetitions and volume but no change in power or isometric force 16Reference 16RCTThe effects of chronic betaine supplementation on exercise performance, skeletal muscle oxygen saturation and associated biochemical parameters in resistance trained men — randomized controlled trialView study →.
A 6-week trial in trained men improved body composition and bench-press work capacity but not 1RM strength 17Reference 17RCTEffects of betaine on body composition, performance, and homocysteine thiolactone — randomized controlled trialView study →.
The typical dose is 2.5 g/day, usually split.
Gap: the signal is small, inconsistent across outcome measures, and concentrated in lower-body maximal strength; several well-designed trials are outright null, and some positive trials had supplement-industry involvement.
Mechanistically coherent — betaine’s methyl donation feeds phosphatidylcholine synthesis, which is needed to package and export liver fat — and the early data were encouraging. A pilot study of betaine anhydrous over 12 months improved aminotransferases and histology in most of 7 completers 7Reference 7Betaine, a promising new agent for patients with nonalcoholic steatohepatitis: results of a pilot studyView study →.
But the properly designed test — a randomised placebo-controlled trial of 55 NASH patients on 20 g/day for 12 months — found betaine did not improve hepatic steatosis (though it may have protected against worsening) and did not shift the underlying disease mechanisms 8Reference 8RCTBetaine for nonalcoholic fatty liver disease: results of a randomized placebo-controlled trialView study →.
Recent low-dose pilot trials (2–8 g/day, 12–24 weeks) in MASLD reported significant falls in ALT and AST and in serologic fibrosis markers at 2 g and above, but these were small paired-comparison pilots with industry co-authors 9Reference 9RCTPilot trials of oral betaine in participants with metabolic dysfunction-associated steatotic liver disease and elevated alanine aminotransferase — randomized controlled trialView study →.
Gap: the one adequately powered, biopsy-controlled RCT was negative for the primary steatosis outcome; the positive data are pilots without a robust placebo comparison.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Betaine-homocysteine methyltransferase (BHMT) | Donates a methyl group, remethylating homocysteine → methionine (liver and kidney, folate-independent) | Homocysteine lowering; homocystinuria |
| S-adenosylmethionine (SAM) pool | ↑ methionine → ↑ SAM, the universal methyl donor for DNA, protein and phospholipid methylation | Homocysteine; liver |
| Organic osmolyte (zwitterion) | Accumulates intracellularly to stabilise cell volume and protein structure under osmotic and thermal stress | Kidney medulla function; proposed muscle cell hydration |
| Phosphatidylcholine synthesis | Methyl supply supports PC → VLDL assembly and hepatic fat export | Fatty liver disease |
| Gut microbial conversion | A fraction is converted to trimethylamine (→ TMAO) | Fishy body odour; the TMAO/cardiovascular debate |
Pharmacokinetics
Betaine is absorbed rapidly, and its effect on serum betaine and plasma homocysteine is acute and dose-dependent — a single 3 g or 6 g dose lowers homocysteine within about 2 hours, while a 1 g dose does not measurably move it 1Reference 1RCTOrally administered betaine has an acute and dose-dependent effect on serum betaine and plasma homocysteine concentrations in healthy humans — randomized controlled trialView study →. Only a very small fraction of an ingested dose is excreted in urine 1Reference 1RCTOrally administered betaine has an acute and dose-dependent effect on serum betaine and plasma homocysteine concentrations in healthy humans — randomized controlled trialView study →.
Dietary intake supplies roughly 0.5–2 g/day and the body also synthesises betaine endogenously from choline, so supplemental doses sit on top of a meaningful baseline 2Reference 2ReviewEffects of betaine intake on plasma homocysteine concentrations and consequences for health — reviewView study →. Performance studies typically split the 2.5 g/day dose in two; homocysteine studies use up to 6 g/day.
Clinical trials
Betaine is an off-patent dietary compound with a genuine orphan-drug indication (Cystadane) but limited large-scale industry trial activity for its wellness uses. Most performance and liver trials are small (n ≈ 20–55), and several carry supplement-industry co-authorship. Registered activity continues in metabolic liver disease.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~30+(homocysteine, performance, liver) | Few(mostly MASLD) | Rare | Many(animal NAFLD, osmolyte biology) |
Last checked: August 2026.
Dietary Sources
Betaine is a normal dietary component, and unlike most compounds here, food intake is a meaningful fraction of the supplemental range. Typical dietary intake runs about 0.5–2 g/day 2Reference 2ReviewEffects of betaine intake on plasma homocysteine concentrations and consequences for health — reviewView study →, against the 2.5–6 g used in studies — so supplements sit on top of a real baseline rather than filling an empty tank.
The body also synthesises betaine from choline, which is why choline and betaine status are linked and usually discussed together 2Reference 2ReviewEffects of betaine intake on plasma homocysteine concentrations and consequences for health — reviewView study →. Refining grains strips most of the betaine out, so whole grains supply far more than refined ones.
| Source | Notes |
|---|---|
| Wheat bran and wheat germ | The richest common source by a wide margin |
| Beets / beetroot | The original source (Beta vulgaris), and where the name comes from |
| Spinach and quinoa | High |
| Shellfish, particularly shrimp | Good animal source |
| Whole grains generally | Moderate; refining removes most of it |
Dosage
These are doses studied in research, not a personal recommendation.
- No RDA/AI and no Upper Limit — betaine is not an essential nutrient (it is made endogenously from choline), so there is no reference intake to hit and no official upper limit to stay under.
- Performance studies cluster at 2.5 g/day, usually split into two doses 16,
17Reference 16RCTThe effects of chronic betaine supplementation on exercise performance, skeletal muscle oxygen saturation and associated biochemical parameters in resistance trained men — randomized controlled trialView study →Reference 17RCTEffects of betaine on body composition, performance, and homocysteine thiolactone — randomized controlled trialView study → . Betaine anhydrous is the form used in research. - Homocysteine studies have used up to 6 g/day. The homocysteine-lowering effect is
dose-dependent — and 6 g/day is also the level at which LDL and total cholesterol rise
1,
3, .11Reference 1RCTOrally administered betaine has an acute and dose-dependent effect on serum betaine and plasma homocysteine concentrations in healthy humans — randomized controlled trialView study →Reference 3Meta-analysisBetaine supplementation decreases plasma homocysteine in healthy adult participants: a meta-analysisView study →Reference 11RCTEffect of homocysteine-lowering nutrients on blood lipids: results from four randomised, placebo-controlled studies in healthy humansView study → - Homocystinuria is treated with prescription betaine at doses set by a metabolic clinician — not a self-directed use 13Reference 13Homocystinuria — the effects of betaine in the treatment of patients not responsive to pyridoxineView study →.
- Betaine HCl is a different product, sold for stomach acid, and should not be substituted for betaine anhydrous.
Safety
Betaine has a benign profile at the doses used in performance research, with three things worth knowing before starting.
- Well tolerated at typical doses. A normal dietary component with a long record of food exposure.
- Raises LDL and total cholesterol at ≥4–6 g/day. Pooled RCT data show 6 g/day raised LDL by 0.36 mmol/L and the total:HDL ratio by 0.23 11Reference 11RCTEffect of homocysteine-lowering nutrients on blood lipids: results from four randomised, placebo-controlled studies in healthy humansView study →, and a meta-analysis of ≥4 g/day trials found total cholesterol up 0.34 mmol/L 12Reference 12Meta-analysisBetaine supplementation moderately increases total cholesterol levels: a systematic review and meta-analysisView study →. Below 4 g/day the homocysteine benefit appears without the lipid penalty 18Reference 18Meta-analysisEffects of betaine supplementation on cardiovascular markers: a systematic review and meta-analysisView study →.
- GI upset at higher intakes. Nausea, cramping and diarrhoea are the usual dose-related complaints; roughly a third of participants in recent liver-disease pilots reported mild transient GI symptoms 9Reference 9RCTPilot trials of oral betaine in participants with metabolic dysfunction-associated steatotic liver disease and elevated alanine aminotransferase — randomized controlled trialView study →.
- Fishy body odour. Gut conversion to trimethylamine can produce a noticeable smell at higher doses — harmless, but the usual reason people stop.
- Kidney impairment. Betaine is an osmolyte handled by the kidney.
- Not evaluated in pregnancy or lactation at supplemental doses — see the box below.
Full Safety & Interactions Detail
- GI upset at higher intakes. Nausea, cramping and diarrhoea are the usual dose-related complaints at gram-level doses; roughly a third of participants in recent liver-disease pilots reported mild transient GI symptoms 9Reference 9RCTPilot trials of oral betaine in participants with metabolic dysfunction-associated steatotic liver disease and elevated alanine aminotransferase — randomized controlled trialView study →.
- Fishy body odour. Gut bacteria convert a fraction of betaine to trimethylamine, which can produce a noticeable smell in some people at higher doses. Harmless but socially unwelcome, and the usual reason people stop. The same pathway produces TMAO, whose cardiovascular significance is debated and unresolved.
- The lipid signal is the genuine flag. Pooled RCT data show betaine at 6 g/day raised LDL by 0.36 mmol/L and the total:HDL ratio by 0.23 in healthy adults 11Reference 11RCTEffect of homocysteine-lowering nutrients on blood lipids: results from four randomised, placebo-controlled studies in healthy humansView study →, and a meta-analysis of trials at ≥4 g/day found a moderate increase in total cholesterol (+0.34 mmol/L) 12Reference 12Meta-analysisBetaine supplementation moderately increases total cholesterol levels: a systematic review and meta-analysisView study →. A separate cardiovascular-marker meta-analysis suggests the effect concentrates at doses ≥4 g/day, with below 4 g/day lowering homocysteine without the lipid penalty 18Reference 18Meta-analysisEffects of betaine supplementation on cardiovascular markers: a systematic review and meta-analysisView study →. Anyone taking betaine specifically for cardiovascular reasons could be trading one marker for another.
- Who should be cautious: anyone with a lipid disorder, given the cholesterol finding, and anyone with kidney impairment, since betaine is an osmolyte handled by the kidney.
Scope disclosure. Interactions were assessed only partially — no formal drug-interaction screen was run. The pharmacologically relevant interactions are metabolic: betaine shares the methylation cycle with folate, B12 and choline, so status in those affects and is affected by betaine intake. No significant cytochrome-P450 drug interactions are described. Pregnancy and lactation were not evaluated at supplemental doses; treat as not established. No Upper Limit has been set, and absence of one does not mean unlimited intake is safe — the 6 g/day lipid signal is the practical ceiling flag. Where betaine has not been studied, that is stated as “not assessed,” not as “safe.”
Not evaluated at supplemental doses. Betaine is a normal dietary component and dietary intake raises no specific concern, but supplemental gram-level doses have not been studied in pregnancy or lactation. Methylation metabolism is central to fetal development and is already carefully managed in pregnancy through folate — adding an unstudied methyl donor on top is not a self-directed decision. Discuss with a qualified practitioner before use.
References
- Schwab U, Törrönen A, Meririnne E, et al. (2006). Orally administered betaine has an acute and dose-dependent effect on serum betaine and plasma homocysteine concentrations in healthy humans — randomized controlled trial. The Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/16365055/
- Olthof MR, Verhoef P (2005). Effects of betaine intake on plasma homocysteine concentrations and consequences for health — review. Current Drug Metabolism. https://pubmed.ncbi.nlm.nih.gov/15720203/
- McRae MP (2013). Betaine supplementation decreases plasma homocysteine in healthy adult participants: a meta-analysis. Journal of Chiropractic Medicine. https://pubmed.ncbi.nlm.nih.gov/23997720/
- EFSA Panel on Dietetic Products, Nutrition and Allergies (2011). Scientific opinion on the substantiation of health claims related to betaine and contribution to normal homocysteine metabolism. EFSA Journal. https://pubmed.ncbi.nlm.nih.gov/42078764/
- Zawieja E, Machek S, Zanchi NE, et al. (2024). Effects of chronic betaine supplementation on exercise performance: systematic review and meta-analysis. Journal of Sports Sciences. https://pubmed.ncbi.nlm.nih.gov/39514262/
- Ismaeel A (2017). Effects of betaine supplementation on muscle strength and power: a systematic review. Journal of Strength and Conditioning Research. https://pubmed.ncbi.nlm.nih.gov/28426517/
- Abdelmalek MF, Angulo P, Jorgensen RA, et al. (2001). Betaine, a promising new agent for patients with nonalcoholic steatohepatitis: results of a pilot study. The American Journal of Gastroenterology. https://pubmed.ncbi.nlm.nih.gov/11569700/
- Abdelmalek MF, Sanderson SO, Angulo P, et al. (2009). Betaine for nonalcoholic fatty liver disease: results of a randomized placebo-controlled trial. Hepatology. https://pubmed.ncbi.nlm.nih.gov/19824078/
- Lim AS, Cruz SN, Uddin AA, et al. (2026). Pilot trials of oral betaine in participants with metabolic dysfunction-associated steatotic liver disease and elevated alanine aminotransferase — randomized controlled trial. Hepatology. https://pubmed.ncbi.nlm.nih.gov/40758380/
- Ashtary-Larky D, Bagheri R, Tinsley GM, et al. (2022). Betaine supplementation fails to improve body composition: a systematic review and meta-analysis. British Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/34743773/
- Olthof MR, van Vliet T, Verhoef P, et al. (2005). Effect of homocysteine-lowering nutrients on blood lipids: results from four randomised, placebo-controlled studies in healthy humans. PLoS Medicine. https://pubmed.ncbi.nlm.nih.gov/15916468/
- Zawieja EE, Zawieja B, Chmurzynska A (2021). Betaine supplementation moderately increases total cholesterol levels: a systematic review and meta-analysis. Journal of Dietary Supplements. https://pubmed.ncbi.nlm.nih.gov/31809615/
- Wilcken DE, Wilcken B, Dudman NP, Tyrrell PA (1983). Homocystinuria — the effects of betaine in the treatment of patients not responsive to pyridoxine. The New England Journal of Medicine. https://pubmed.ncbi.nlm.nih.gov/6877313/
- Morris AA, Kožich V, Santra S, et al. (2017). Guidelines for the diagnosis and management of cystathionine beta-synthase deficiency — systematic review. Journal of Inherited Metabolic Disease. https://pubmed.ncbi.nlm.nih.gov/27778219/
- Huemer M, Diodato D, Schwahn B, et al. (2017). Guidelines for diagnosis and management of the cobalamin-related remethylation disorders — review. Journal of Inherited Metabolic Disease. https://pubmed.ncbi.nlm.nih.gov/27905001/
- Trepanowski JF, Farney TM, McCarthy CG, et al. (2011). The effects of chronic betaine supplementation on exercise performance, skeletal muscle oxygen saturation and associated biochemical parameters in resistance trained men — randomized controlled trial. Journal of Strength and Conditioning Research. https://pubmed.ncbi.nlm.nih.gov/22080324/
- Cholewa JM, Wyszczelska-Rokiel M, Glowacki R, et al. (2013). Effects of betaine on body composition, performance, and homocysteine thiolactone — randomized controlled trial. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/23967897/
- Ashtary-Larky D, Bagheri R, Ghanavati M, et al. (2022). Effects of betaine supplementation on cardiovascular markers: a systematic review and meta-analysis. Critical Reviews in Food Science and Nutrition. https://pubmed.ncbi.nlm.nih.gov/33764214/



