
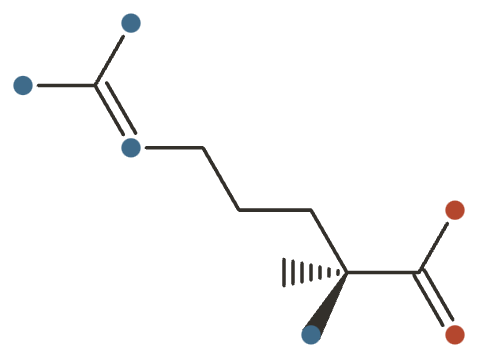
L-Arginine
L-Arginine is a conditionally essential amino acid and a nitric-oxide precursor, taken for blood flow, blood pressure, and exercise "pump".

L-Arginine at a Glance
L-Arginine is a conditionally essential amino acid whose entire reputation rests on one reaction: it is the direct substrate for nitric-oxide synthase, the enzyme that makes nitric oxide — the body’s principal endogenous vasodilator. Feed the enzyme, the argument goes, and you get more blood flow.
The evidence is genuinely bimodal, and not in the direction the marketing suggests. The cardiovascular end — blood pressure, endothelial function — is the better-supported half. The sports-performance and “pump” claims that sell most of the powder are the weakest.
One fact explains much of that gap. Oral arginine is largely destroyed before it arrives: arginase in the gut and liver degrades a large fraction on first pass, so bioavailability is modest and varies a lot between people. L-citrulline sidesteps that loss entirely and raises plasma arginine more effectively than arginine does — which is why, for anything driven by nitric oxide, citrulline is often the better molecule to take.
What It’s Used For
- Blood pressure — the strongest signal, modest in size, plateauing around 9 g/day.
- Endothelial function — improves flow-mediated dilation, but mainly in people whose vascular function is already impaired.
- Preeclampsia in high-risk pregnancy — a supervised clinical use, not a self-directed one.
- Erectile dysfunction — mechanistically on target, but the positive data come mostly from combination formulas.
- Sickle cell disease pain — the one setting where arginine is genuinely depleted and repletion is physiologically justified.
- Exercise performance — the most-marketed use and the least supported.
- Perioperative immunonutrition — a real clinical benefit, but delivered inside a multi-ingredient surgical formula rather than as arginine alone.
- Glucose & insulin sensitivity — small trials in metabolically impaired groups; not a glucose-control supplement.
- Growth hormone — a genuine intravenous testing phenomenon that gets stretched into an oral muscle-building claim it cannot support.
Worth knowing what it is not for: in serious cardiovascular disease it has failed twice. Given after a heart attack it produced more deaths than placebo 14Reference 14RCTL-arginine therapy in acute myocardial infarction: the Vascular Interaction With Age in Myocardial Infarction (VINTAGE MI) randomized clinical trial — randomized controlled trialView study →, and in peripheral arterial disease it showed no benefit and possible harm 15Reference 15RCTL-arginine supplementation in peripheral arterial disease: no benefit and possible harm — randomized controlled trialView study →. Those are the two hardest facts here — and they are worth stating precisely, because the early literature pointed the other way. A small 3-week study in 1998 reported large gains in pain-free walking distance in claudication 23Reference 23Clinical trialRestoring vascular nitric oxide formation by L-arginine improves the symptoms of intermittent claudication in patients with peripheral arterial occlusive disease — controlled trialView study →, and that result is still quoted. It did not survive: the larger, longer, oral 6-month trial found the opposite 15Reference 15RCTL-arginine supplementation in peripheral arterial disease: no benefit and possible harm — randomized controlled trialView study →. When a short, small, infusion-era positive is overturned by a longer oral RCT, the later trial is the one to believe.
How It Works
Nitric-oxide synthase converts arginine to citrulline and NO. NO diffuses into vascular smooth muscle, relaxes it, and the vessel widens — which is the whole mechanism behind the blood-pressure, endothelial and erectile applications.
Two complications sit on top of that simple story. The first is the “arginine paradox”: plasma arginine is normally far above the concentration eNOS needs, so extra substrate should do nothing — yet it sometimes does. The leading explanation is competition with ADMA, an endogenous eNOS inhibitor, which is also why the benefit concentrates in people whose endothelium is already impaired rather than in healthy adults.
The second is first-pass loss. Gut and hepatic arginase, plus bacterial degradation, destroy much of an oral dose before it reaches circulation, and fractional absorption falls as the single dose rises — so a big bolus buys diarrhoea rather than plasma arginine.
Arginine also acutely stimulates growth-hormone release, which is the basis of the clinical arginine GH stimulation test. This is frequently repurposed as a marketing claim; in practice arginine blunts rather than aids the GH response to exercise 19Reference 19ReviewGrowth hormone, arginine and exercise — reviewView study →.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Arginine is a conditionally essential amino acid whose main claim to fame is being the direct substrate for nitric-oxide synthase (NOS) — the enzyme that makes nitric oxide (NO), the body’s principal endogenous vasodilator. Its evidence base is genuinely bimodal: the cardiovascular/vascular literature (blood pressure, endothelial function) is the better-supported end, while the sports-performance and “pump” claims that sell most of the powder are the weakest. A recurring limiter runs through the whole record — oral arginine has modest and variable bioavailability because a large fraction is destroyed by arginase in the gut and liver before it reaches the circulation, which is why L-citrulline (which bypasses that first-pass loss and raises plasma arginine more effectively) is increasingly preferred for the same NO endpoints. Several of the clearer signals are also repletion effects, concentrated in people who start with impaired NO signalling (low baseline flow-mediated dilation, arginine-depleting disease, at-risk pregnancy) rather than a general boost in already-healthy adults.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume, then tempered for consistency, form/bioavailability, and how much of the effect depends on treating a deficiency rather than adding on top of adequacy. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
This is the strongest signal. A 2022 systematic review and dose–response meta-analysis of randomised trials found L-arginine supplementation significantly lowered both systolic and diastolic blood pressure, with the effect concentrated at moderate doses and no additional benefit above roughly 9 g/day 1Reference 1Meta-analysisEffect of l-Arginine supplementation on blood pressure in adults: a systematic review and dose-response meta-analysis of randomized clinical trials — meta-analysisView study →.
It replicates an earlier meta-analysis of double-blind, placebo-controlled RCTs that reported average reductions of about 5 mmHg systolic and 2–3 mmHg diastolic 2Reference 2Meta-analysisEffect of oral L-arginine supplementation on blood pressure: a meta-analysis of randomized, double-blind, placebo-controlled trials — meta-analysisView study →.
Doses used were typically oral L-arginine (free amino acid form) in the 4–24 g/day range, consistent with the NO-precursor mechanism. The effect is modest — comparable to a single lifestyle change, not a substitute for antihypertensive therapy.
Gap: effect sizes are small, heterogeneity across trials is high, and much of the benefit appears in people with elevated baseline pressure rather than normotensive adults.
Meta-analyses of RCTs show oral L-arginine can improve flow-mediated dilation (FMD), a functional marker of endothelial NO availability — but the benefit is conditional. A 2009 meta-analysis found the FMD improvement was effective specifically when baseline FMD was low, i.e. in people whose endothelium was already impaired 3Reference 3Meta-analysisIncrease in fasting vascular endothelial function after short-term oral L-arginine is effective when baseline flow-mediated dilation is low — meta-analysisView study →.
A 2018 meta-analysis in patients with cardiovascular or metabolic disorders similarly reported favourable movement in endothelial markers 4Reference 4Meta-analysisAssociation of l-Arginine supplementation with markers of endothelial function in patients with cardiovascular or metabolic disorders — meta-analysisView study →.
This is a repletion/rescue pattern, not a general vascular upgrade for healthy adults.
Gap: trials are short-term, use the poorly-bioavailable free amino acid, and the effect largely vanishes in people with normal baseline endothelial function.
Preeclampsia involves impaired placental NO signalling, giving a mechanistic rationale for arginine supplementation. Systematic reviews and meta-analyses in high-risk pregnancies report reduced preeclampsia incidence and improved maternal/neonatal outcomes with L-arginine (often alongside antioxidants or L-citrulline) 7,
Gap: trials are heterogeneous in dose, timing and co-interventions, several are small or industry-adjacent, and supplementation in pregnancy must be clinician-supervised — this is not a self-directed use.
The rationale is direct: erection depends on NO-mediated smooth-muscle relaxation, and arginine feeds that pathway. A 2019 meta-analysis found arginine supplements improved erectile function versus placebo 5Reference 5Meta-analysisThe potential role of arginine supplements on erectile dysfunction: a systematic review and meta-analysis — meta-analysisView study →, and a 2024 network meta-analysis of nutraceuticals for ED ranked arginine-containing interventions favourably 6Reference 6Meta-analysisNutraceutical interventions for erectile dysfunction: a systematic review and network meta-analysis — network meta-analysisView study →.
The important caveat is that much of the positive data comes from combination products (arginine with pycnogenol, ginseng, tribulus, or other actives), so the effect attributable to arginine alone is uncertain.
Gap: monotherapy evidence is thin and confounded by combination formulas; effect sizes are smaller and less reliable than established PDE5-inhibitor therapy.
Sickle cell disease depletes plasma arginine (through haemolysis-driven arginase release), making this a genuine deficiency state — the one setting where arginine repletion is most physiologically justified. A 2025 multicentre Phase-2 randomised, placebo-controlled trial evaluated IV arginine for vaso-occlusive pain crises 12Reference 12RCTArginine therapy for pain in sickle cell disease: a Phase-2 randomized, placebo-controlled trial — randomized controlled trialView study →, and a 2023 systematic review/meta-analysis of clinical trials summarised reductions in pain scores and opioid use 13Reference 13Meta-analysisEffects of l-arginine supplementation in patients with sickle cell disease: a systematic review and meta-analysis of clinical trials — systematic review/meta-analysisView study →. A Phase-3 trial is underway.
Gap: this is a disease-specific repletion effect (largely IV, in hospital) and does not generalise to oral supplementation in healthy people; the definitive Phase-3 result is still pending.
Arginine is a core ingredient — alongside omega-3 fatty acids and nucleotides — in the “immunonutrition” formulas given around major surgery. Meta-analyses in upper-gastrointestinal and other cancer surgery show these formulas reduce postoperative infectious complications by roughly 30% (RR 0.72, 95% CI 0.57–0.92) versus standard nutrition 20Reference 20Meta-analysisImpact of perioperative immunonutrition on postoperative outcomes in patients with upper gastrointestinal cancer — systematic review and meta-analysisView study →, and a systematic review of amino acids in wound healing links arginine to improved healing markers such as hydroxyproline deposition 21Reference 21Meta-analysisThe effect of amino acids on wound healing — systematic review and meta-analysis on arginine and glutamineView study →.
This is the one setting where a clinical body of evidence supports giving arginine deliberately.
Gap: arginine is delivered inside a multi-ingredient blend, so its individual contribution cannot be isolated. The benefit is a supervised perioperative one and does not transfer to everyday wound healing in healthy people.
Despite being one of the most-marketed uses (“nitric oxide” pre-workouts), the ergogenic evidence for arginine specifically is weak. A 2020 meta-analysis reported some performance benefit 9Reference 9Meta-analysisEffects of arginine supplementation on athletic performance based on energy metabolism: a systematic review and meta-analysis — meta-analysisView study →, but it was subsequently the subject of a published methodological critique arguing the pooled estimates were distorted by analytical errors 10Reference 10Meta-analysisCommon errors in sports nutrition meta-analyses lead to distortion of pooled effect estimatesView study →.
A separate meta-analysis of endurance performance found arginine, unlike dietary nitrate, did not produce a clear benefit 11Reference 11Meta-analysisEffect of food sources of nitrate, polyphenols, L-arginine and L-citrulline on endurance exercise performance — meta-analysisView study →.
Oral arginine’s poor bioavailability is the likely mechanistic reason it underperforms citrulline and nitrate here.
Gap: the flagship positive meta-analysis is contested, endurance pooling is null, and the free-amino-acid form barely raises plasma arginine — this application should be treated as unproven.
Mechanistic reviews and small trials suggest arginine can improve insulin sensitivity and endothelial function in obesity and type 2 diabetes via the nitric-oxide pathway 22Reference 22ReviewL-arginine modulates glucose and lipid metabolism in obesity and diabetes — reviewView study →, and a 2025 trial in overweight and obese patients with polycystic ovary syndrome reported improved insulin sensitivity and reproductive markers with supplementation 24Reference 24Clinical trialImproved insulin sensitivity and reproductive profile in overweight and obese PCOS patients under L-arginine supplementation — clinical trial. https://pubmed.ncbi.nlm.nih.gov/39874141/View study →.
Gap: the human evidence is small, largely confined to metabolically impaired or disease populations, and nowhere near sufficient to recommend arginine as a glucose-control supplement in healthy people.
Intravenous arginine is a reliable, decades-old pharmacological stimulus for growth-hormone secretion, and it is still used clinically in growth-hormone stimulation testing 25Reference 25ReviewGrowth hormone responses during arginine and clonidine stimulation testing — reviewView study →.
That clinical fact is routinely stretched into a claim that oral arginine supplements meaningfully raise growth hormone for muscle-building. They do not: ordinary oral doses produce only weak, transient rises, which are further blunted by exercise, with no established anabolic benefit 19Reference 19ReviewGrowth hormone, arginine and exercise — reviewView study →.
Gap: the robust growth-hormone effect is an intravenous, testing-context phenomenon. Oral supplementation for body composition is not supported, and this is one of the clearest cases on the site of a real pharmacological finding being mis-sold.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Nitric-oxide synthase (eNOS) | ↑ NO synthesis → vasodilation | Blood pressureendothelial functionpreeclampsiaED |
| Arginase (gut/liver) | Degrades arginine (first-pass loss) | Poor oral bioavailability; rationale for citrulline |
| Arginine–ADMA balance | Competes with the endogenous eNOS inhibitor ADMA | Endothelial function (“arginine paradox”) |
| Anterior-pituitary GH axis | Acute ↑ growth-hormone secretion (basis of the arginine GH stimulation test); blunts, not aids, exercise-induced GH 19Reference 19ReviewGrowth hormone, arginine and exercise — reviewView study → | Diagnostic use; a frequently overstated marketing claim |
| Urea cycle / ammonia clearance | Intermediate in urea synthesis | Rare inborn urea-cycle disorders (clinicalnot supplemental) |
Pharmacokinetics
Oral L-arginine is absorbed via intestinal cationic amino-acid transporters but suffers substantial
first-pass metabolism: gut and hepatic arginase and bacterial degradation destroy a large
fraction before it reaches systemic circulation, giving oral bioavailability commonly cited around
~20–50% and highly variable between people. Plasma half-life of the free amino acid is short (on the
order of ~1–2 hours). A head-to-head pharmacokinetic study found oral L-citrulline raised plasma
arginine more than L-arginine itself and increased NO metabolites, because citrulline escapes
first-pass arginase and is converted to arginine in the kidney 16,
Clinical trials
L-arginine has an extensive registered-trial footprint spanning cardiovascular, obstetric, metabolic, haematologic and critical-care indications, though much recent activity uses arginine within combination products rather than as a sole agent, and there is limited fresh industry-funded monotherapy work (it is an off-patent commodity amino acid).
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~450 | ~110 | ~85 | Extensive |
Last checked: August 2026.
Dietary Sources
Arginine is a non-essential/conditionally essential amino acid, so the body synthesises some (mainly via the intestinal–renal citrulline–arginine axis) and healthy adults obtain the rest from ordinary dietary protein. It is abundant in protein-dense foods, with the richest sources being nuts, seeds, legumes, poultry, seafood and dairy. Because it is a normal protein building block, outright dietary deficiency is rare in well-nourished people; the “conditionally essential” label reflects that requirements can outstrip synthesis during illness, trauma, rapid growth or specific diseases (such as sickle cell disease).
| Food (per ~100 g) | Approx. arginine |
|---|---|
| Pumpkin/squash seeds | ~5.4 g |
| Peanuts | ~3.5 g |
| Soybeans (dry) | ~2.6 g |
| Almonds | ~2.5 g |
| Turkey / chicken breast | ~1.8–2.0 g |
| Chickpeas / lentils (dry) | ~1.8–2.0 g |
| Shrimp / tuna | ~1.5–1.8 g |
Amounts are indicative; refining and heavy processing of protein foods reduces content.
A typical mixed diet supplies roughly 4–6 g arginine/day — which overlaps the low end of the doses studied in blood-pressure trials. That overlap is part of why “extra on top of an adequate diet” so often shows only modest effects in replete adults.
Intake & Dosage
These are doses studied in research, not a personal recommendation.
There is no RDA/AI and no Tolerable Upper Intake Level for arginine — it is not treated as a dietary-essential nutrient. “No UL” means one has not been set, not that unlimited intake is safe.
- Blood pressure / vascular: most trials used 4–9 g/day oral L-arginine; the dose–response meta-analysis found benefit plateauing around 9 g/day, with no added effect — and more GI side effects — at higher intakes 1Reference 1Meta-analysisEffect of l-Arginine supplementation on blood pressure in adults: a systematic review and dose-response meta-analysis of randomized clinical trials — meta-analysisView study →.
- Erectile dysfunction: the trials that report benefit generally used 1.5–5 g/day, usually
inside a combination formula rather than as arginine alone 5,
6Reference 5Meta-analysisThe potential role of arginine supplements on erectile dysfunction: a systematic review and meta-analysis — meta-analysisView study →Reference 6Meta-analysisNutraceutical interventions for erectile dysfunction: a systematic review and network meta-analysis — network meta-analysisView study → . - Split the dose: oral bioavailability is modest and variable, and fractional absorption drops as the single dose rises, so the daily total is usually split into 2–3 doses. Single boluses of 9 g or more frequently cause diarrhoea and nausea.
- Consider citrulline instead: because L-citrulline bypasses first-pass
arginase and raises plasma arginine more effectively, ~3–6 g/day of citrulline is often used to
reach the same NO endpoint at lower GI cost 16,
17Reference 16RCTPharmacokinetic and pharmacodynamic properties of oral L-citrulline and L-arginine: impact on nitric oxide metabolism — randomized controlled trialView study →Reference 17ReviewEndogenous flux of nitric oxide: citrulline is preferred to arginine — reviewView study → . - Watch the salt form: arginine is a free amino acid, so labelled grams are grams of L-arginine — but in arginine-HCl or arginine-AKG products a fraction of the weight is the counter-ion.
Safety
At studied oral doses L-arginine is generally well tolerated. The cautions that matter are not about toxicity — they are cardiovascular and pharmacological.
- Well tolerated at studied doses. GI upset is the dose-limiting effect, appearing mainly at single doses of 9 g or more.
- Avoid after a recent heart attack. The VINTAGE MI randomised trial found no benefit from adding L-arginine after acute MI and reported a higher death rate in the arginine group 14Reference 14RCTL-arginine therapy in acute myocardial infarction: the Vascular Interaction With Age in Myocardial Infarction (VINTAGE MI) randomized clinical trial — randomized controlled trialView study →.
- No benefit, possible harm in peripheral arterial disease. A randomised trial found worse functional outcomes than placebo 15Reference 15RCTL-arginine supplementation in peripheral arterial disease: no benefit and possible harm — randomized controlled trialView study →.
- Additive hypotension. Arginine lowers blood pressure — combining it with antihypertensives, nitrates or PDE5 inhibitors (sildenafil, tadalafil) can stack.
- Renal or hepatic impairment. Arginine metabolism loads the urea cycle and kidneys.
- Clinician-directed use only in pregnancy. It has been studied for preeclampsia, but under supervision — see the box below.
Full Safety & Interactions Detail
Gastrointestinal upset — diarrhoea, nausea, bloating — is the dose-limiting adverse effect, and it appears mainly at single doses of 9 g or more. Splitting the daily total across 2–3 doses is the standard mitigation.
- The two cardiovascular failures are the important part of this section. In VINTAGE MI, L-arginine added to standard therapy after acute myocardial infarction produced no vascular benefit and a higher mortality rate than placebo 14Reference 14RCTL-arginine therapy in acute myocardial infarction: the Vascular Interaction With Age in Myocardial Infarction (VINTAGE MI) randomized clinical trial — randomized controlled trialView study →. In peripheral arterial disease, a randomised trial found no benefit and possible harm on functional outcomes 15Reference 15RCTL-arginine supplementation in peripheral arterial disease: no benefit and possible harm — randomized controlled trialView study →. Both are the opposite of what the NO mechanism predicts, and both are reasons to keep arginine away from serious cardiovascular disease rather than toward it.
- Interactions: the main risk is additive hypotension with antihypertensive drugs, nitrates and PDE5 inhibitors. A comprehensive drug-interaction review has not been performed.
- Herpes (theoretical): arginine is a substrate for herpes-virus replication. The relevance to supplementation is unproven, but it is sometimes flagged for people with frequent cold sores — and it is the mirror image of the L-lysine claim.
- Renal or hepatic impairment: arginine metabolism loads the urea cycle and the kidneys, so caution applies where either is compromised.
Scope disclosure. Interactions were assessed partially — antihypertensives, nitrates, PDE5 inhibitors and the post-MI/PAD cardiovascular context were screened; a comprehensive review was not performed. Pregnancy and lactation were assessed only for the high-risk-pregnancy preeclampsia indication; general self-supplementation safety is not established. No Upper Limit exists, and absence of one does not mean unlimited intake is safe — GI tolerance and the ~9 g/day efficacy plateau are the practical ceilings in trials. Where something was not studied, it is marked “not assessed,” not “safe.”
Clinician-supervised use only — do not self-supplement. Arginine, often alongside citrulline or
antioxidants, has been studied for preeclampsia prevention in high-risk pregnancies under medical
supervision 7,
References
- Shiraseb F, Asbaghi O, Bagheri R, et al. (2022). Effect of l-Arginine supplementation on blood pressure in adults: a systematic review and dose-response meta-analysis of randomized clinical trials — meta-analysis. Advances in Nutrition. https://pubmed.ncbi.nlm.nih.gov/34967840/
- Dong JY, et al. (2011). Effect of oral L-arginine supplementation on blood pressure: a meta-analysis of randomized, double-blind, placebo-controlled trials — meta-analysis. American Heart Journal. https://pubmed.ncbi.nlm.nih.gov/22137067/
- Bai Y, et al. (2009). Increase in fasting vascular endothelial function after short-term oral L-arginine is effective when baseline flow-mediated dilation is low — meta-analysis. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/19056561/
- Rodrigues-Krause J, et al. (2018). Association of l-Arginine supplementation with markers of endothelial function in patients with cardiovascular or metabolic disorders — meta-analysis. Nutrients. https://pubmed.ncbi.nlm.nih.gov/30577559/
- Rhim HC, et al. (2019). The potential role of arginine supplements on erectile dysfunction: a systematic review and meta-analysis — meta-analysis. The Journal of Sexual Medicine. https://pubmed.ncbi.nlm.nih.gov/30770070/
- Barbonetti A, Tienforti D, Antolini F, et al. (2024). Nutraceutical interventions for erectile dysfunction: a systematic review and network meta-analysis — network meta-analysis. The Journal of Sexual Medicine. https://pubmed.ncbi.nlm.nih.gov/39279185/
- Naderipour F, Keshavarzi F, Mirfakhraee H, et al. (2024). Efficacy of L-Arginine for preventing preeclampsia and improving maternal and neonatal outcomes in high-risk pregnancies — systematic review/meta-analysis. International Journal of Fertility & Sterility. https://pubmed.ncbi.nlm.nih.gov/39564822/
- Makama M, McDougall ARA, Cao J, et al. (2025). L-Arginine and L-Citrulline for prevention and treatment of pre-eclampsia: a systematic review and meta-analysis — meta-analysis. BJOG. https://pubmed.ncbi.nlm.nih.gov/39800868/
- Viribay A, et al. (2020). Effects of arginine supplementation on athletic performance based on energy metabolism: a systematic review and meta-analysis — meta-analysis. Nutrients. https://pubmed.ncbi.nlm.nih.gov/32370176/
- Trexler ET (2025). Common errors in sports nutrition meta-analyses lead to distortion of pooled effect estimates. Comment on Viribay et al. — commentary. Nutrients. https://pubmed.ncbi.nlm.nih.gov/40733000/
- d’Unienville NMA, Blake HT, Coates AM, et al. (2021). Effect of food sources of nitrate, polyphenols, L-arginine and L-citrulline on endurance exercise performance — meta-analysis. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/34965876/
- Morris CR, Hatabah D, Korman R, et al. (2025). Arginine therapy for pain in sickle cell disease: a Phase-2 randomized, placebo-controlled trial — randomized controlled trial. American Journal of Hematology. https://pubmed.ncbi.nlm.nih.gov/40270092/
- Sadeghi A, Taherifard E, Dehdari Ebrahimi N, et al. (2023). Effects of l-arginine supplementation in patients with sickle cell disease: a systematic review and meta-analysis of clinical trials — systematic review/meta-analysis. Health Science Reports. https://pubmed.ncbi.nlm.nih.gov/37064309/
- Schulman SP, et al. (2006). L-arginine therapy in acute myocardial infarction: the Vascular Interaction With Age in Myocardial Infarction (VINTAGE MI) randomized clinical trial — randomized controlled trial. JAMA. https://pubmed.ncbi.nlm.nih.gov/16391217/
- Wilson AM, et al. (2007). L-arginine supplementation in peripheral arterial disease: no benefit and possible harm — randomized controlled trial. Circulation. https://pubmed.ncbi.nlm.nih.gov/17592080/
- Schwedhelm E, et al. (2008). Pharmacokinetic and pharmacodynamic properties of oral L-citrulline and L-arginine: impact on nitric oxide metabolism — randomized controlled trial. British Journal of Clinical Pharmacology. https://pubmed.ncbi.nlm.nih.gov/17662090/
- Bahadoran Z, Mirmiran P, Kashfi K, et al. (2021). Endogenous flux of nitric oxide: citrulline is preferred to arginine — review. Acta Physiologica. https://pubmed.ncbi.nlm.nih.gov/33089645/
- Tang WHW, et al. (2009). Diminished global arginine bioavailability and increased arginine catabolism as metabolic profile of increased cardiovascular risk — cohort/observational. Journal of the American College of Cardiology. https://pubmed.ncbi.nlm.nih.gov/19477356/
- Kanaley JA (2008). Growth hormone, arginine and exercise — review. Current Opinion in Clinical Nutrition and Metabolic Care. https://pubmed.ncbi.nlm.nih.gov/18090659/
- Matsui R, et al. (2024). Impact of perioperative immunonutrition on postoperative outcomes in patients with upper gastrointestinal cancer — systematic review and meta-analysis. Nutrients. https://pubmed.ncbi.nlm.nih.gov/38474706/
- Arribas-López E, et al. (2021). The effect of amino acids on wound healing — systematic review and meta-analysis on arginine and glutamine. Nutrients. https://pubmed.ncbi.nlm.nih.gov/34444657/
- Hu S, et al. (2017). L-arginine modulates glucose and lipid metabolism in obesity and diabetes — review. Current Protein & Peptide Science. https://pubmed.ncbi.nlm.nih.gov/27356939/
- Böger RH, Bode-Böger SM, Thiele W, et al. (1998). Restoring vascular nitric oxide formation by L-arginine improves the symptoms of intermittent claudication in patients with peripheral arterial occlusive disease — controlled trial. Journal of the American College of Cardiology. https://pubmed.ncbi.nlm.nih.gov/9809945/
- Genazzani AD, Battipaglia C, Foschi M, et al. (2025). Improved insulin sensitivity and reproductive profile in overweight and obese PCOS patients under L-arginine supplementation — clinical trial. https://pubmed.ncbi.nlm.nih.gov/39874141/
- Sodero G, Mariani F, Caprarelli M, et al. (2023). Growth hormone responses during arginine and clonidine stimulation testing — review. Growth Horm IGF Res. https://pubmed.ncbi.nlm.nih.gov/36502626/



