
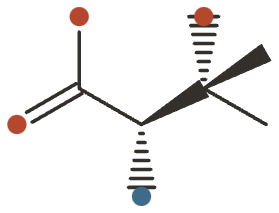
L-Threonine
Essential amino acid central to gut mucin and the mucus barrier; supplementation benefits are largely deficiency-dependent.

L-Threonine at a Glance
L-threonine is an essential amino acid found in meat, dairy, eggs and lentils. It was the last of the essential amino acids to be identified, in 1936.
What distinguishes it is where the body sends it: threonine is heavily concentrated in mucin, the glycoprotein that forms the protective mucus layer lining the gut. A large share of dietary threonine is consumed by the intestine itself before it ever reaches the bloodstream.
What It’s Used For
- Correcting deficiency: gut mucin & barrier — restores mucin production and intestinal barrier integrity.
- Immune / mucosal immunity support — supports mucosal immune function.
- Spasticity (MS & spinal) — reduces spasticity in multiple sclerosis and spinal injury.
How It Works
Mucin is exceptionally rich in threonine — the amino acid provides the attachment points for the sugar chains that give mucus its gel structure. Because the gut extracts threonine for that purpose first, intestinal demand competes directly with the rest of the body, which is why threonine status shows up as a barrier-function problem before anything else.
Its neurological use runs through a different route: threonine is metabolised to glycine, an inhibitory neurotransmitter in the spinal cord, which is the rationale for raising spinal glycine to damp spasticity.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Threonine is an essential (indispensable) amino acid — the body cannot make it, so all of it comes from dietary protein. Its decision-relevant biology is nutritional rather than pharmacological: it is a major building block of mucin, the threonine-rich glycoprotein that forms the protective mucus layer of the gut, and it feeds into glycine and serine metabolism. The evidence divides cleanly into two stories that are easy to conflate. The repletion/deficiency story — threonine limitation impairs gut mucin synthesis and barrier function — is well demonstrated, but almost entirely in animals and in the context of restriction, not supplementation on top of an adequate diet. The pharmacological story — high-dose L-threonine (4.5–7.5 g/day) as a glycine precursor to treat spasticity — produced statistically real but clinically trivial effects in small human trials from the early 1990s and has not advanced since. For a healthy person eating enough protein, standalone threonine supplementation has no established benefit.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
Threonine is used disproportionately by the gut. Mucins — the gel-forming glycoproteins secreted by goblet cells — are exceptionally rich in threonine, so intestinal mucin synthesis is one of the first processes to suffer when dietary threonine is scarce. In rats, restricting dietary threonine to 30% of requirement specifically and significantly reduced mucin fractional synthesis rate in the duodenum, ileum, and colon, while leaving general mucosal protein synthesis intact — a targeted hit to the mucus barrier 7Reference 7AnimalDietary threonine restriction specifically reduces intestinal mucin synthesis in rats — controlled animal studyView study →.
A large fraction of dietary threonine is extracted by the gut on first pass and committed to mucin rather than oxidized, and this demand rises during intestinal inflammation 8,
In intrauterine-growth-retarded weanling piglets, 2 g/kg-diet L-threonine raised ileal Muc2, secretory IgA, and goblet-cell density and dampened inflammation 10Reference 10L-threonine improves intestinal mucin synthesis and immune function of intrauterine growth-retarded weanling piglets — animal studyView study →.
The consistent theme: threonine is limiting for mucin production, so adding it back when intake is low restores barrier function. What is missing is any evidence that extra threonine helps a person already eating adequate protein — a systematic review of nutritional support for mucosal healing in inflammatory bowel disease found the supporting data for threonine (and other amino acids) came almost entirely from animal and cell studies, not human trials 16Reference 16ReviewMucosal healing in inflammatory bowel diseases: is there a place for nutritional supplementation? — reviewView study →.
Gap: The benefit is deficiency-dependent and demonstrated in animals; there is no human supplementation trial showing gut benefit in replete people.
This is the one genuinely pharmacological human use. The rationale: L-threonine is a precursor for glycine, an inhibitory neurotransmitter in the spinal cord, so raising threonine might enhance glycinergic inhibition of overactive motor reflexes. Three small double-blind trials tested it. In familial spastic paraparesis, 4.5–6.0 g/day produced a statistically significant (p < 0.02) decrease in spasticity ratings — but the authors concluded “the benefits were not clinically valuable,” and CSF glycine did not actually rise 1Reference 1RCTL-threonine in the treatment of spasticity — randomised double-blind crossover trialView study →.
In multiple sclerosis, 7.5 g/day reduced signs of spasticity on examination with no side effects and no sedation (a real contrast with baclofen and tizanidine), but again produced no symptomatic improvement the patient or physician could feel 3Reference 3RCTAn antispasticity effect of threonine in multiple sclerosis — randomised crossover trialView study →.
A third crossover trial at 6 g/day in spinal spasticity reported a “modest but definite” antispastic effect 2Reference 2RCTA double-blind study of L-threonine in patients with spinal spasticity — randomised crossover trialView study →.
Later systematic reviews were unimpressed: a Cochrane review of anti-spasticity agents found the threonine data, like most in this field, methodologically weak 4Reference 4Systematic reviewAnti-spasticity agents for multiple sclerosis — systematic reviewView study →, and a dedicated MS systematic review concluded the single RCT “does not support its effectiveness” 5Reference 5Systematic reviewClinical effectiveness of oral treatments for spasticity in MS — systematic reviewView study →.
Gap: Effect is statistically real but clinically negligible, glycine did not rise as hypothesized, and no trial has been run in over two decades.
Because mucins and secretory antibodies are part of the gut’s frontline immune barrier, threonine deficiency and repletion track with mucosal immune measures. In IUGR piglets, L-threonine supplementation increased ileal secretory IgA alongside Muc2 and reduced pro-inflammatory cytokines 10Reference 10L-threonine improves intestinal mucin synthesis and immune function of intrauterine growth-retarded weanling piglets — animal studyView study →.
Threonine’s role in maintaining goblet-cell number and mucus output — the physical component of innate gut defense — is well described in the animal-nutrition literature, where it is a recognized limiting amino acid for barrier function under immune challenge 9,
However, one of those challenge studies found supplemental threonine did not further increase mucin output in Salmonella-challenged pigs, suggesting mucin secretion is metabolically prioritized and extra threonine only helps when it is genuinely limiting 12Reference 12Effect of dietary fiber and threonine on intestinal barrier function in challenged pigs — animal studyView study →.
Gap: All immune data are from young or challenged animals under deficiency conditions; there is no evidence that threonine supplementation strengthens immunity in healthy, well-fed humans.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Mucin (MUC2) synthesis in goblet cells | Substrate — threonine-rich glycoprotein; limiting for synthesis | Gut barriermucosal immunity |
| Spinal glycine (inhibitory neurotransmission) | Proposed precursor; ↑ glycinergic inhibition (glycine did not measurably rise in trials) | Spasticity |
| Glycine / serine one-carbon metabolism | Catabolic substrate via threonine dehydrogenase / threonine dehydratase | Systemic amino-acid metabolism |
| Protein synthesis (collagen, elastin, antibodies) | Incorporated as an indispensable residue; frequent O-glycosylation / phosphorylation site | Connective tissueimmune proteins |
Pharmacokinetics
L-Threonine is absorbed in the small intestine via sodium-dependent neutral amino acid transporters. A defining feature is heavy first-pass gut extraction: roughly a quarter or more of an oral dose is taken up by the portal-drained viscera and liver before reaching the systemic circulation, and a large share of the gut’s uptake is committed to mucin synthesis rather than oxidation 8,
Clinical trials
Registered-trial activity for standalone L-threonine is minimal. It is off-patent, cheap, and of no commercial interest as a drug, so the human evidence is essentially frozen at the small neurology trials of the early 1990s plus the ALS amino-acid trials; the active research is in animal nutrition (swine/poultry feed), where threonine is a routine feed additive.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~4(spasticity/ALS, small) | ~0 | 0 | many(animal-nutrition) |
Last checked: July 2026.
Dietary Sources
L-Threonine is supplied by virtually all dietary protein; deficiency is essentially unknown in people eating adequate protein. It is relatively abundant in animal proteins and concentrated in some plant sources, while being a limiting amino acid in cereal grains — one reason grain-heavy diets historically paired grains with legumes.
| Food (per typical serving) | Approx. threonine |
|---|---|
| Lean beef / poultry (100 g) | ~1.2–1.4 g |
| Fish (100 g) | ~0.9–1.1 g |
| Eggs (2 large) | ~0.6 g |
| Cottage cheese / dairy (100 g) | ~0.5–0.7 g |
| Lentils / beans, cooked (1 cup) | ~0.6–0.7 g |
| Soy / tofu (100 g) | ~0.5–0.7 g |
| Wheat / rice (limiting AA) | low relative to needs |
A mixed diet providing adequate total protein delivers roughly 2–2.5 g of threonine per day, comfortably above the ~1 g/day physiological requirement. Refining grains lowers protein and threonine content; the amino acid is otherwise stable in ordinary cooking. See the NIH ODS and dietary-reference literature for authoritative food composition.
Intake & Dosage
Physiological requirement. Threonine is an indispensable amino acid. Modern stable-isotope (indicator amino acid oxidation) studies in adults converge on a mean requirement of about 15 mg/kg/day — roughly 1.0–1.1 g/day for a 70 kg adult — which is about double the older 1985 FAO/WHO nitrogen-balance figure of 7 mg/kg/day that those studies specifically overturned 13,
Supplemental / research doses. There is no established reason to supplement threonine on top of an adequate diet. The doses studied in humans were pharmacological, for spasticity: 4.5–7.5 g/day 1,
These are doses studied in research, not a personal recommendation. A varied diet with adequate protein already supplies more threonine than the body requires.
Safety
L-Threonine is a dietary essential with an unusually quiet safety profile — even the multi-gram doses used in the spasticity trials produced little more than mild gut upset. The honest caveat is how little has been formally studied rather than any documented harm.
- Well tolerated at studied doses. Up to 7.5 g/day for weeks caused only minimal side effects, with no sedation or motor weakness.
- No documented drug interactions. Threonine is not a CYP450 substrate — though this reflects an absence of reports, not proven absence.
- Mild gastrointestinal effects at high doses. Nausea and loose stools.
- No Upper Intake Level is set. The absence of a limit is not evidence that very high chronic intakes are safe.
- Supplemental doses unstudied in pregnancy and breastfeeding. Diet is safe; gram-level supplements are not established — see the box below.
Full Safety & Interactions Detail
L-Threonine is well tolerated. As a normal dietary constituent it carries no concern at food-level intakes, and the multi-gram doses used in the spasticity trials (up to 7.5 g/day for weeks) produced only minimal side effects, with no sedation or motor weakness — a contrast the MS investigators specifically highlighted against conventional antispastic drugs 1,
Reported effects at high doses are mild and gastrointestinal (nausea, loose stools). Very high sustained intakes can raise plasma threonine (hyperthreoninemia); this has been studied mainly in developing animals and is not an established human concern at dietary or trial doses. No clinically significant drug interactions are documented, and threonine is not a substrate for the CYP450 drug-metabolizing enzymes; formal interaction studies are lacking, so this reflects an absence of reports rather than proven absence. No Tolerable Upper Intake Level is set for individual amino acids, threonine included — the absence of a limit is not evidence that very high chronic intakes are safe.
Verdict: not formally established — treat dietary intake as safe, supplemental high doses as unstudied. Threonine from food is essential and safe throughout pregnancy and lactation, and requirements rise modestly. There are no controlled trials of high-dose L-threonine supplementation in pregnant or breastfeeding women, so gram-level supplementation should not be assumed safe. Anyone pregnant or breastfeeding should get threonine from a balanced diet rather than isolated supplements unless directed by a clinician. This is general information, not medical advice; individual decisions should be made with a qualified healthcare professional.
References
- Growdon JH, Nader TM, Schoenfeld J, Wurtman RJ. (1991). L-threonine in the treatment of spasticity — randomised double-blind crossover trial. Clin Neuropharmacol. https://pubmed.ncbi.nlm.nih.gov/1742749/
- Lee A, Patterson V. (1993). A double-blind study of L-threonine in patients with spinal spasticity — randomised crossover trial. Acta Neurol Scand. https://pubmed.ncbi.nlm.nih.gov/8296531/
- Hauser SL, Doolittle TH, Lopez-Bresnahan M, et al. (1992). An antispasticity effect of threonine in multiple sclerosis — randomised crossover trial. Arch Neurol. https://pubmed.ncbi.nlm.nih.gov/1520082/
- Shakespeare DT, Young CA, Boggild M. (2000). Anti-spasticity agents for multiple sclerosis — systematic review. Cochrane Database Syst Rev. https://pubmed.ncbi.nlm.nih.gov/11034714/
- Paisley S, Beard S, Hunn A, Wight J. (2002). Clinical effectiveness of oral treatments for spasticity in MS — systematic review. Mult Scler. https://pubmed.ncbi.nlm.nih.gov/12166503/
- Parton M, Mitsumoto H, Leigh PN. (2003). Amino acids for amyotrophic lateral sclerosis / motor neuron disease — systematic review. Cochrane Database Syst Rev. https://pubmed.ncbi.nlm.nih.gov/14583978/
- Faure M, Moënnoz D, Montigon F, et al. (2005). Dietary threonine restriction specifically reduces intestinal mucin synthesis in rats — controlled animal study. J Nutr. https://pubmed.ncbi.nlm.nih.gov/15735082/
- Rémond D, Buffière C, Godin JP, et al. (2009). Intestinal inflammation increases gastrointestinal threonine uptake and mucin synthesis in enterally fed minipigs — animal study. J Nutr. https://pubmed.ncbi.nlm.nih.gov/19193812/
- Mao X, Zeng X, Qiao S, Wu G, Li D. (2011). Specific roles of threonine in intestinal mucosal integrity and barrier function — review. Front Biosci (Elite Ed). https://pubmed.ncbi.nlm.nih.gov/21622125/
- Zhang H, Chen Y, Li Y, et al. (2019). L-threonine improves intestinal mucin synthesis and immune function of intrauterine growth-retarded weanling piglets — animal study. Nutrition. https://pubmed.ncbi.nlm.nih.gov/30504005/
- Puiman PJ, Jensen M, Stoll B, et al. (2011). Intestinal threonine utilization for protein and mucin synthesis is decreased in formula-fed preterm pigs — animal study. J Nutr. https://pubmed.ncbi.nlm.nih.gov/21593357/
- Wellington MO, Hamonic K, Krone JEC, et al. (2020). Effect of dietary fiber and threonine on intestinal barrier function in challenged pigs — animal study. J Anim Sci Biotechnol. https://pubmed.ncbi.nlm.nih.gov/32318266/
- Wilson DC, Rafii M, Ball RO, Pencharz PB. (2000). Threonine requirement of young men determined by indicator amino acid oxidation — human metabolic study. Am J Clin Nutr. https://pubmed.ncbi.nlm.nih.gov/10702170/
- Borgonha S, Regan MM, Oh SH, Condon M, Young VR. (2002). Threonine requirement of healthy adults, derived with a 24-h indicator amino acid balance technique — human metabolic study. Am J Clin Nutr. https://pubmed.ncbi.nlm.nih.gov/11916756/
- Kurpad AV, Raj T, Regan MM, et al. (2002). Threonine requirements of healthy Indian men, measured by a 24-h indicator amino acid oxidation and balance technique — human metabolic study. Am J Clin Nutr. https://pubmed.ncbi.nlm.nih.gov/12324292/
- Lan A, Blachier F, Benamouzig R, et al. (2015). Mucosal healing in inflammatory bowel diseases: is there a place for nutritional supplementation? — review. Inflamm Bowel Dis. https://pubmed.ncbi.nlm.nih.gov/25208104/



