
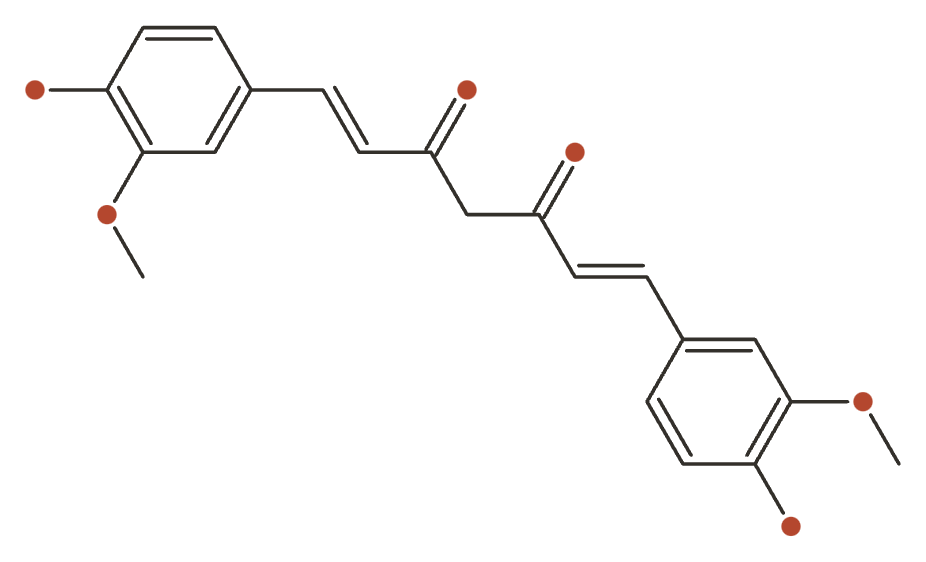
Curcumin (turmeric extract)
Curcumin is the bright-orange principal curcuminoid of turmeric — a genuine but notoriously poorly-absorbed anti-inflammatory with real randomized-trial signals in osteoarthritis and ulcerative colitis, and an equally real reputation as a chemically unstable pan-assay-interference compound whose in-vitro hits often do not translate.

Sources · 4
Where Does It Come From?

Concentration
Content by Source
Reported concentrations across the plants that contain curcumin (turmeric extract) — the bar marks the typical level, the line shows the reported range.
Literature figures for varying plant parts and preparations. Read them as a comparative guide, not exact assays.
Curcumin (turmeric extract) at a Glance
Curcumin (diferuloylmethane) is the bright-orange diarylheptanoid pigment and principal curcuminoid of turmeric (Curcuma longa), sitting alongside its close siblings demethoxycurcumin and bisdemethoxycurcumin. It is one of the most heavily studied natural products in existence — tens of thousands of papers describe anti-inflammatory, antioxidant, anti-cancer, glycaemic and neuroprotective activity — and it is also one of the most cautionary. Two facts dominate any honest account of curcumin, and everything here is built around them.
First, curcumin is barely absorbed. It is a textbook BCS class-IV molecule: very poor water solubility, chemical instability at physiological pH, and rapid first-pass glucuronidation and sulfation. Oral curcumin produces vanishingly low plasma concentrations, which is why almost every commercial product bundles it with a bioavailability enhancer — piperine from black pepper, or a phospholipid/nanoparticle carrier (Meriva, Theracurmin, BCM-95) 4,
The credible signal that survives both problems comes from human randomized trials of standardised, bioavailability-optimised extracts — most convincingly in osteoarthritis and in maintaining remission in ulcerative colitis, with weaker signals in lipids/metabolic syndrome and depression 11,
The Bioavailability Problem
This is the single most important thing to understand about curcumin, and the reason “turmeric cures X” claims collapse in practice. The molecule that works in a dish barely reaches your bloodstream when you swallow it.
Unformulated oral curcumin is absorbed poorly, what little is absorbed is rapidly conjugated in the gut wall and liver to curcumin glucuronide and sulfate, and it is cleared quickly — human and rodent pharmacokinetic work repeatedly finds only trace, often unmeasurable, free curcumin in plasma even after gram doses 4,
- Piperine co-administration. The alkaloid piperine from black pepper inhibits the UGT glucuronidation that destroys curcumin first-pass. In the landmark human study, 20 mg of piperine raised curcumin bioavailability by about 2,000% 4Reference 4Clinical trialInfluence of piperine on the pharmacokinetics of curcumin in animals and human volunteersView study →. This is the cheapest and most common enhancer, and the reason “turmeric + black pepper” folklore has a real mechanism behind it.
- Phospholipid complexes (Meriva). Binding curcumin to soy phosphatidylcholine raised absorption of total curcuminoids roughly 29-fold versus an unformulated standard in a human crossover study 8Reference 8Comparative absorption of a standardized curcuminoid mixture and its lecithin formulationView study →.
- Nanoparticle / colloidal dispersions (Theracurmin). Reducing particle size to the nanometre range raised the area-under-curve about 27-fold over conventional curcumin in healthy volunteers 9,
10Reference 9Innovative preparation of curcumin for improved oral bioavailabilityView study →Reference 10Clinical trialDose-escalation and pharmacokinetic study of nanoparticle curcumin, a potential anticancer agent with improved bioavailability, in healthy human volunteersView study → . - Turmeric-oil / self-emulsifying blends (BCM-95). Co-formulating curcuminoids with turmeric essential oil (including ar-turmerone) improved relative bioavailability several-fold in a pilot crossover 21Reference 21A Pilot Cross-Over Study to Evaluate Human Oral Bioavailability of BCM-95CG (Biocurcumax), A Novel Bioenhanced Preparation of CurcuminView study →.
There is a deeper twist. Because free curcumin is so scarce systemically, some researchers argue the active species in vivo may not be curcumin at all but its reduced metabolite tetrahydrocurcumin (a colourless, more stable, strongly antioxidant conjugate) or the conjugates and degradation products 5,
Is Curcumin a Drug or an Assay Artefact?
Curcumin is the textbook example that medicinal chemists cite when they warn against promiscuous natural products, and any responsible monograph has to say so plainly. In 2017 Nelson and colleagues published “The Essential Medicinal Chemistry of Curcumin”, arguing that curcumin has almost none of the properties a real drug lead needs 1Reference 1The Essential Medicinal Chemistry of CurcuminView study →. The specific charges:
- It is a PAINS (pan-assay interference compound). Curcumin registers as a “hit” against an implausibly broad range of unrelated targets — a signature not of miraculous versatility but of non-specific assay interference 1,
2Reference 1The Essential Medicinal Chemistry of CurcuminView study →Reference 2Deceptive curcumin offers cautionary tale for chemistsView study → . - It is an IMPS (invalid metabolic panacea). The same over-broad activity profile recurs across metabolic assays 1Reference 1The Essential Medicinal Chemistry of CurcuminView study →.
- It interferes with the readouts themselves. Curcumin is fluorescent, chelates metals (iron, copper), participates in redox cycling and covalently reacts with thiols — so it can produce apparent activity in fluorescence-, absorbance- and redox-based assays without any true target engagement 1,
2Reference 1The Essential Medicinal Chemistry of CurcuminView study →Reference 2Deceptive curcumin offers cautionary tale for chemistsView study → . - It is chemically unstable. Under physiological (neutral-to-alkaline) conditions curcumin degrades within minutes to hours, yielding ferulic acid, vanillin and other fragments — so “curcumin” in a cell assay is often a shifting mixture, not the parent compound 6Reference 6Stability of curcumin in buffer solutions and characterization of its degradation productsView study →.
The wider scientific press picked this up as a cautionary tale for the whole field of natural-product screening 2Reference 2Deceptive curcumin offers cautionary tale for chemistsView study →. This does not mean curcumin does nothing — it means the enormous in-vitro literature is a weak foundation, and the only claims worth much are those that survive to human randomized trials of a defined, bioavailable formulation. That filter is exactly how the rest of the evidence is weighted.
What It's Used For
Curcumin’s mechanistic literature is vast; its trustworthy clinical literature is small. The two honesty sections above are the lens: treat in-vitro “activity” as hypothesis-generating at best, and lean on the randomized human trials of standardised extracts.
Support is an experimental score — weighted by study type (human > animal > in vitro) and volume. A beta, not a validated metric. Human trials here are of standardised bioavailable extracts, not turmeric powder or pure curcumin, so read every score through that formulation lens.
Curcumin’s strongest human evidence. A systematic review and meta-analysis of randomized trials concluded that turmeric/curcumin extracts (typically ~1,000 mg/day of curcuminoids) reduced arthritis pain and improved function, with an effect size in the range of common anti-inflammatory drugs 11Reference 11Meta-analysisEfficacy of Turmeric Extracts and Curcumin for Alleviating the Symptoms of Joint Arthritis: A Systematic Review and Meta-Analysis of Randomized Clinical TrialsView study →.
A multicentre randomized trial found a standardised Curcuma domestica extract as effective as ibuprofen for knee-osteoarthritis pain over four weeks, with fewer gastrointestinal complaints 12Reference 12Clinical trialEfficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthritis: a multicenter studyView study →.
Every positive trial used a standardised, bioavailability-optimised extract — not culinary turmeric.
Gap: trials are mostly short (4–12 weeks), heterogeneous in formulation and dose, and several are industry-funded; long-term and head-to-head formulation data are thin 11,
A genuinely interesting inflammatory-bowel-disease signal, and mechanistically plausible given curcumin’s NF-κB inhibition acting locally in the gut, where poor systemic absorption is an advantage rather than a liability. A randomized, double-blind, placebo-controlled trial found curcumin maintenance therapy (2 g/day) significantly reduced relapse in quiescent ulcerative colitis over six months 13Reference 13RCTCurcumin maintenance therapy for ulcerative colitis: randomized, multicenter, double-blind, placebo-controlled trialView study →.
A later randomized trial showed curcumin added to mesalamine induced clinical and endoscopic remission in mild-to-moderate active disease far more often than mesalamine plus placebo 14Reference 14RCTCurcumin in Combination With Mesalamine Induces Remission in Patients With Mild-to-Moderate Ulcerative Colitis in a Randomized Controlled TrialView study →.
Gap: trials are small and single-region; the durable place of curcumin in IBD management versus established biologics/aminosalicylates is unproven, and formulations/doses differ 13,
A real but modest signal, almost always studied as a curcuminoid–piperine combination. In randomized trials in metabolic syndrome, adjunctive curcuminoids improved the lipid profile (lowering triglycerides and non-HDL cholesterol, raising HDL) and reduced circulating inflammatory cytokines versus placebo 15,
Gap: short trials, surrogate endpoints (lipids/cytokines, not cardiovascular events), and heavy reliance on piperine co-administration confound attribution to curcumin itself 15,
Small human trials suggest an antidepressant effect. A randomized controlled trial reported curcumin was comparable to fluoxetine and added to it in major depressive disorder 17Reference 17RCTEfficacy and safety of curcumin in major depressive disorder: a randomized controlled trialView study →, and a meta-analysis of the available trials concluded curcumin reduced depressive symptoms versus placebo, particularly in middle-aged patients and with longer dosing 18Reference 18Meta-analysisClinical Use of Curcumin in Depression: A Meta-AnalysisView study →.
Proposed mechanisms include monoamine-oxidase modulation, raised BDNF and anti-neuroinflammatory action — though the MAO-inhibitor potency figures widely quoted for curcumin are unreliable.
Gap: trials are small, short, mostly single-centre and heterogeneous in formulation; the meta-analytic evidence is rated low-quality, and publication bias is likely 17,
The mechanistic core of curcumin’s reputation, and the best-characterised biology — but overwhelmingly preclinical. Curcumin inhibits the master inflammatory transcription factor NF-κB, is a dual inhibitor of arachidonic-acid metabolism (down-regulating COX-2 and 5-LOX), and activates the Nrf2/ARE antioxidant programme, inducing heme oxygenase-1 and endogenous antioxidant enzymes 19,
These actions are genuine in cells and animals and give the clinical anti-inflammatory signals a coherent story.
Gap: most of this is in-vitro or rodent work at concentrations unattainable in human plasma given curcumin’s pharmacokinetics — and precisely the kind of broad-target activity the PAINS critique warns can be assay artefact 1,
The largest and most disappointing body of curcumin research. Thousands of preclinical papers report curcumin modulating transcription factors, kinases, growth factors and apoptosis across essentially every cancer type 20,
Yet no convincing human oncology efficacy has emerged, and reviews of completed clinical trials attribute this directly to poor bioavailability and to the PAINS/instability problems that inflate the preclinical signal 1,
Gap: the preclinical-to-clinical translation has repeatedly failed; claims of curcumin as a cancer therapy are not supported by human outcome data, and the in-vitro basis is the weakest kind of evidence for this molecule 1,
How Curcumin Works
Curcumin is a polypharmacological electrophile: an α,β-unsaturated diketone (a Michael acceptor) that reacts with protein thiols, chelates metals and cycles redox states. That same reactivity is why it hits so many targets — and why much of the in-vitro data is suspect 1Reference 1The Essential Medicinal Chemistry of CurcuminView study →. The mechanisms with the best support:
NF-κB & Inflammatory Signalling
Curcumin inhibits activation of NF-κB, blunting TNF-driven transcription of pro-inflammatory cytokines, adhesion molecules and COX-2 — the central node behind its anti-inflammatory and much of its anticancer preclinical activity 19,
Eicosanoid Pathways
It acts as a dual inhibitor of arachidonic-acid metabolism, down-regulating cyclooxygenase-2 and 5-lipoxygenase and thereby prostaglandin and leukotriene synthesis 19Reference 19Antioxidant and anti-inflammatory properties of curcuminView study →.
Nrf2 / Antioxidant Response
Curcumin activates the Nrf2–ARE pathway, inducing heme oxygenase-1 and phase-II antioxidant enzymes — an indirect antioxidant effect that is more physiologically plausible than its direct free-radical scavenging, which requires high concentrations 20Reference 20Curcumin activates the haem oxygenase-1 gene via regulation of Nrf2 and the antioxidant-responsive elementView study →.
Direct Reactivity & Metal Chelation
Curcumin scavenges reactive oxygen species, chelates iron and copper, and covalently modifies thiols. These are real chemical properties — but they are also exactly the mechanisms that generate false positives in biochemical assays, which is why the same reactivity underlies both its bioactivity claims and the PAINS critique 1,
Pharmacokinetics
Curcumin’s ADME is the whole story, and it is unflattering. Oral bioavailability is very low — commonly cited as under a few percent for unformulated curcumin, with free plasma curcumin often below detection even after gram doses 4,
- Absorption — poor, limited by very low aqueous solubility (BCS class IV) and by chemical degradation in the neutral small-intestinal environment 4,
6Reference 4Clinical trialInfluence of piperine on the pharmacokinetics of curcumin in animals and human volunteersView study →Reference 6Stability of curcumin in buffer solutions and characterization of its degradation productsView study → . - Metabolism — extensive and rapid first-pass glucuronidation and sulfation in the gut wall and liver, producing curcumin glucuronide/sulfate as the dominant circulating species; reductive metabolism yields di-, tetra-, hexa- and octahydrocurcumin, of which tetrahydrocurcumin is the most studied and may carry much of the antioxidant activity 5,
17Reference 5AnimalCharacterization of metabolites of the chemopreventive agent curcumin in human and rat hepatocytes and in the rat in vivo, and evaluation of their ability to inhibit phorbol ester-induced prostaglandin E2 productionView study →Reference 17RCTEfficacy and safety of curcumin in major depressive disorder: a randomized controlled trialView study → . - Degradation — under physiological pH curcumin breaks down within minutes to hours to ferulic acid, vanillin, feruloylmethane and other fragments, so systemic exposure is to a mixture, not the parent 6Reference 6Stability of curcumin in buffer solutions and characterization of its degradation productsView study →.
- Half-life / clearance — rapid; unabsorbed curcumin is largely excreted in the faeces, and absorbed curcumin is cleared quickly as conjugates in bile and urine 5Reference 5AnimalCharacterization of metabolites of the chemopreventive agent curcumin in human and rat hepatocytes and in the rat in vivo, and evaluation of their ability to inhibit phorbol ester-induced prostaglandin E2 productionView study →.
Formulation changes everything. Piperine (UGT/CYP inhibition, ~20-fold), phospholipid complexes (~29-fold), nanoparticle dispersions (~27-fold) and turmeric-oil blends each raise systemic curcuminoid exposure substantially 4,
Clinical Trials
Curcumin has been studied in an enormous number of human trials across inflammation, gastroenterology, metabolism, oncology, dermatology and psychiatry — but the quality and formulations vary wildly, and reviews of the completed-trial record stress that positive results cluster in the bioavailability-enhanced-extract trials in osteoarthritis and ulcerative colitis, while the oncology promise has largely failed to translate 7Reference 7Clinical trialTherapeutic roles of curcumin: lessons learned from clinical trialsView study →.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| Many(OA, UC, metabolic syndrome, depression, phase-I oncology) | Ongoing(formulation & oncology-adjunct) | Some(oncology efficacy signals absent) | Vast(largely PAINS-caveated) |
Last checked: July 2026.
Isolate vs. Plant Studies
The isolate-vs-plant distinction is unusually consequential for curcumin, because a third category — the standardised extract — dominates the good evidence, and it is neither the pure molecule nor the whole herb.
Evidence for the Standardised Extract
Nearly all credible human trials use a standardised ~95%-curcuminoid extract (curcumin plus demethoxycurcumin and bisdemethoxycurcumin), usually with a bioavailability enhancer 11,
Evidence for the Isolate
Pure curcumin dominates the mechanistic in-vitro and rodent literature — and this is exactly the body of work the PAINS/instability critique targets, since isolated curcumin in a buffer is a degrading, promiscuous mixture 1,
Evidence for the Whole Herb
Culinary turmeric delivers only ~1–5% curcumin at very low absorption, so dietary intake is a poor guide to the trial results; the essential-oil constituents (ar-turmerone, turmerones) contribute separately and are not curcumin. Whole-herb effects should not be inferred from curcumin-extract trials, or vice versa.
Prevalence in Nature
Curcumin is effectively confined to the genus Curcuma (Zingiberaceae). Its overwhelming natural source is the rhizome of turmeric (Curcuma longa), where the total curcuminoid fraction is about 2–9% of dry weight, of which curcumin is roughly 70–75%, demethoxycurcumin ~15–20% and bisdemethoxycurcumin ~3–8% 3,
Discovery & Synthesis
Curcumin was first isolated in 1815 by Vogel and Pelletier, who obtained the “yellow colouring matter” from turmeric rhizome; a purer preparation followed in 1842. Its structure was assigned in 1910 by Miłobędzka, Kostanecki and Lampe as diferuloylmethane, and Lampe reported the first total synthesis in 1913 1Reference 1The Essential Medicinal Chemistry of CurcuminView study →. The name derives directly from the plant’s Latin genus, Curcuma (itself from the Arabic kurkum, saffron/turmeric). As a dye it carries the colour-index designation C.I. Natural Yellow 3.
Synthetically, curcumin is made by aldol-type condensation of acetylacetone (via a boron-complex-protected intermediate) with two equivalents of vanillin — a tidy irony, since vanillin is also a principal degradation product of curcumin 1,
Patents: not yet researched.
Commercial Production
Commercial curcumin is produced almost entirely by solvent extraction of turmeric oleoresin, then crystallisation and purification to a standardised ~95% total curcuminoid powder — the material used in supplements and in most clinical trials. Total synthesis is chemically straightforward but not cost-competitive with extraction from a cheap, abundant crop, so natural-source curcumin dominates the market.
The commercially important innovation is not making curcumin but delivering it: an entire formulation industry exists to defeat its pharmacokinetics — piperine-standardised blends, phospholipid complexes (Meriva), nanoparticle/colloidal dispersions (Theracurmin), turmeric-oil self-emulsifying systems (BCM-95), cyclodextrin complexes, micelles and liposomes 4,
Toxicity & Safety
Curcumin’s acute toxicity is low — it has GRAS-adjacent food-colour status and is well tolerated at high oral doses — but “low toxicity” is not “no risk”, and the drug-interaction and hepatic-signal picture deserves care.
General Tolerability
Phase-I studies have escalated oral curcuminoids to 8 g/day with only mild, mostly gastrointestinal effects (nausea, diarrhoea, bloating) 23Reference 23Dose escalation of a curcuminoid formulationView study →. Poor systemic absorption is, ironically, part of why unformulated curcumin is so well tolerated.
Hepatotoxicity Signal
Turmeric/curcumin has been linked to a small but growing number of drug-induced liver-injury cases. The U.S. Drug-Induced Liver Injury Network reported a series of hepatocellular injury cases (several with autoimmune features, one fatal) associated with turmeric products — disproportionately the high-absorption, piperine-enhanced formulations, plausibly because those are the ones that actually deliver meaningful systemic exposure 26Reference 26Liver Injury Associated with Turmeric — A Growing Problem: Ten Cases from the Drug-Induced Liver Injury Network [DILIN]View study →. The very engineering that makes curcumin “work” may also be what makes rare hepatotoxicity possible.
Bleeding & Antiplatelet Interaction
Curcumin inhibits platelet aggregation and modulates coagulation in preclinical work, so it carries a theoretical additive bleeding risk with antiplatelet and anticoagulant drugs (aspirin, clopidogrel, warfarin, DOACs) and around surgery 24Reference 24Curcumin, hemostasis, thrombosis, and coagulationView study →.
Drug-Interaction Profile
In healthy men, curcumin 1 g daily for two weeks lowered CYP1A2 activity by about 29%, measured with a caffeine probe 27Reference 27Plant polyphenol curcumin significantly affects CYP1A2 and CYP2A6 activity in healthy, male Chinese volunteersView study →. A curcumin–piperine extract (4 g curcuminoids with 24 mg piperine) did not change levels of midazolam (CYP3A4), flurbiprofen (CYP2C9) or paracetamol (glucuronidation and sulfation) in healthy volunteers 28Reference 28Effect of a herbal extract containing curcumin and piperine on midazolam, flurbiprofen and paracetamol (acetaminophen) pharmacokinetics in healthy volunteersView study →.
Laboratory and animal studies show curcumin inhibiting several CYP enzymes and P-glycoprotein, but few of these effects have been confirmed in people 25Reference 25ReviewPharmacokinetic interactions of curcuminoids with conventional drugs: A reviewView study →. It is still sensible to take care with narrow-therapeutic-index drugs. It may also affect iron status through chelation.
Reproductive safety: some preclinical reports describe uterine-stimulant and anti-implantation effects for curcumin, and turmeric is traditionally regarded as an emmenagogue; human reproductive data for isolated curcumin are lacking. Pregnancy/lactation is a per-herb / per-supplement decision and is not adjudicated on this molecule page.
- Low acute toxicity. Well tolerated orally, with a long dietary history and food-colour (E100) status; phase-I work tolerated up to 8 g/day of curcuminoids 23Reference 23Dose escalation of a curcuminoid formulationView study →.
- A real, if rare, hepatotoxicity signal — clustered in high-absorption/piperine-enhanced products, including a fatal case in the DILIN series; stop and seek care for signs of liver injury 26Reference 26Liver Injury Associated with Turmeric — A Growing Problem: Ten Cases from the Drug-Induced Liver Injury Network [DILIN]View study →.
- Bleeding & drug interactions. Additive antiplatelet/anticoagulant risk, and curcumin lowered CYP1A2 activity in healthy men, though it left CYP3A4 and CYP2C9 probe drugs unchanged — relevant around surgery and with narrow-therapeutic-index medicines 24,
27, .28Reference 24Curcumin, hemostasis, thrombosis, and coagulationView study →Reference 27Plant polyphenol curcumin significantly affects CYP1A2 and CYP2A6 activity in healthy, male Chinese volunteersView study →Reference 28Effect of a herbal extract containing curcumin and piperine on midazolam, flurbiprofen and paracetamol (acetaminophen) pharmacokinetics in healthy volunteersView study → - “Curcumin” is meaningless without the formulation. Absorption ranges from negligible (powder) to 20–30× (enhanced products); dose and risk both scale with the delivery system 4,
8, .9Reference 4Clinical trialInfluence of piperine on the pharmacokinetics of curcumin in animals and human volunteersView study →Reference 8Comparative absorption of a standardized curcuminoid mixture and its lecithin formulationView study →Reference 9Innovative preparation of curcumin for improved oral bioavailabilityView study → - Most in-vitro claims are unreliable. Curcumin’s PAINS/instability profile means glowing cell-assay results should not be taken as human evidence 1,
6Reference 1The Essential Medicinal Chemistry of CurcuminView study →Reference 6Stability of curcumin in buffer solutions and characterization of its degradation productsView study → .
Dosage
There is no single established dose, and the delivered systemic exposure depends far more on the formulation than on the milligram number on the label. Reported research figures:
| Application | Form | Dose used in trials |
|---|---|---|
| Osteoarthritis | Standardised curcuminoid extract (± piperine/phospholipid) | ~1,000 mg/day curcuminoids 11, |
| Ulcerative colitis (maintenance) | Curcumin | 1–2 g/day 13, |
| Metabolic syndrome / lipids | Curcuminoids + piperine | ~1,000 mg/day curcuminoids + ~10 mg piperine 15, |
| Depression | Curcumin (± piperine) | ~500–1,000 mg/day 17, |
| Phase-I tolerability ceiling | Unformulated curcuminoids | up to 8 g/day tolerated 23Reference 23Dose escalation of a curcuminoid formulationView study → |
Bioavailability-enhanced forms (Meriva, Theracurmin, BCM-95, piperine blends) deliver far more systemic curcumin per milligram, so their effective doses are lower and not comparable to plain powder 8,
References
- Nelson KM, Dahlin JL, Bisson J, Graham J, Pauli GF, Walters MA. (2017). The Essential Medicinal Chemistry of Curcumin. Journal of Medicinal Chemistry, 60(5), 1620–1637. https://pubmed.ncbi.nlm.nih.gov/28074653/
- Baker M. (2017). Deceptive curcumin offers cautionary tale for chemists. Nature, 541(7636), 144–145. https://doi.org/10.1038/541144a
- Anand P, Kunnumakkara AB, Newman RA, Aggarwal BB. (2007). Bioavailability of curcumin: problems and promises. Molecular Pharmaceutics, 4(6), 807–818. https://pubmed.ncbi.nlm.nih.gov/17999464/
- Shoba G, Joy D, Joseph T, Majeed M, Rajendran R, Srinivas PS. (1998). Influence of piperine on the pharmacokinetics of curcumin in animals and human volunteers. Planta Medica, 64(4), 353–356. https://pubmed.ncbi.nlm.nih.gov/9619120/
- Ireson C, Orr S, Jones DJ, et al. (2001). Characterization of metabolites of the chemopreventive agent curcumin in human and rat hepatocytes and in the rat in vivo, and evaluation of their ability to inhibit phorbol ester-induced prostaglandin E2 production. Cancer Research, 61(3), 1058–1064. https://pubmed.ncbi.nlm.nih.gov/11221833/
- Wang YJ, Pan MH, Cheng AL, et al. (1997). Stability of curcumin in buffer solutions and characterization of its degradation products. Journal of Pharmaceutical and Biomedical Analysis, 15(12), 1867–1876. https://pubmed.ncbi.nlm.nih.gov/9278892/
- Gupta SC, Patchva S, Aggarwal BB. (2013). Therapeutic roles of curcumin: lessons learned from clinical trials. The AAPS Journal, 15(1), 195–218. https://pubmed.ncbi.nlm.nih.gov/23143785/
- Cuomo J, Appendino G, Dern AS, et al. (2011). Comparative absorption of a standardized curcuminoid mixture and its lecithin formulation. Journal of Natural Products, 74(4), 664–669. https://pubmed.ncbi.nlm.nih.gov/21413691/
- Sasaki H, Sunagawa Y, Takahashi K, et al. (2011). Innovative preparation of curcumin for improved oral bioavailability. Biological & Pharmaceutical Bulletin, 34(5), 660–665. https://pubmed.ncbi.nlm.nih.gov/21532153/
- Kanai M, Imaizumi A, Otsuka Y, et al. (2012). Dose-escalation and pharmacokinetic study of nanoparticle curcumin, a potential anticancer agent with improved bioavailability, in healthy human volunteers. Cancer Chemotherapy and Pharmacology, 69(1), 65–70. https://pubmed.ncbi.nlm.nih.gov/21603867/
- Daily JW, Yang M, Park S. (2016). Efficacy of Turmeric Extracts and Curcumin for Alleviating the Symptoms of Joint Arthritis: A Systematic Review and Meta-Analysis of Randomized Clinical Trials. Journal of Medicinal Food, 19(8), 717–729. https://pubmed.ncbi.nlm.nih.gov/27533649/
- Kuptniratsaikul V, Dajpratham P, Taechaarpornkul W, et al. (2014). Efficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthritis: a multicenter study. Clinical Interventions in Aging, 9, 451–458. https://pubmed.ncbi.nlm.nih.gov/24672232/
- Hanai H, Iida T, Takeuchi K, et al. (2006). Curcumin maintenance therapy for ulcerative colitis: randomized, multicenter, double-blind, placebo-controlled trial. Clinical Gastroenterology and Hepatology, 4(12), 1502–1506. https://pubmed.ncbi.nlm.nih.gov/17101300/
- Lang A, Salomon N, Wu JCY, et al. (2015). Curcumin in Combination With Mesalamine Induces Remission in Patients With Mild-to-Moderate Ulcerative Colitis in a Randomized Controlled Trial. Clinical Gastroenterology and Hepatology, 13(8), 1444–1449. https://pubmed.ncbi.nlm.nih.gov/25724700/
- Panahi Y, Khalili N, Hosseini MS, Abbasinazari M, Sahebkar A. (2014). Lipid-modifying effects of adjunctive therapy with curcuminoids-piperine combination in patients with metabolic syndrome: results of a randomized controlled trial. Complementary Therapies in Medicine, 22(5), 851–857. https://pubmed.ncbi.nlm.nih.gov/25440375/
- Panahi Y, Hosseini MS, Khalili N, et al. (2016). Effects of curcumin on serum cytokine concentrations in subjects with metabolic syndrome: A post-hoc analysis of a randomized controlled trial. Biomedicine & Pharmacotherapy, 82, 578–582. https://pubmed.ncbi.nlm.nih.gov/27470399/
- Sanmukhani J, Satodia V, Trivedi J, et al. (2014). Efficacy and safety of curcumin in major depressive disorder: a randomized controlled trial. Phytotherapy Research, 28(4), 579–585. https://pubmed.ncbi.nlm.nih.gov/23832433/
- Ng QX, Koh SSH, Chan HW, Ho CYX. (2017). Clinical Use of Curcumin in Depression: A Meta-Analysis. Journal of the American Medical Directors Association, 18(6), 503–508. https://pubmed.ncbi.nlm.nih.gov/28236605/
- Menon VP, Sudheer AR. (2007). Antioxidant and anti-inflammatory properties of curcumin. Advances in Experimental Medicine and Biology, 595, 105–125. https://pubmed.ncbi.nlm.nih.gov/17569207/
- Balogun E, Hoque M, Gong P, et al. (2003). Curcumin activates the haem oxygenase-1 gene via regulation of Nrf2 and the antioxidant-responsive element. The Biochemical Journal, 371(Pt 3), 887–895. https://pubmed.ncbi.nlm.nih.gov/12570874/
- Antony B, Merina B, Iyer VS, Judy N, Lennertz K, Joyal S. (2008). A Pilot Cross-Over Study to Evaluate Human Oral Bioavailability of BCM-95CG (Biocurcumax), A Novel Bioenhanced Preparation of Curcumin. Indian Journal of Pharmaceutical Sciences, 70(4), 445–449. https://pubmed.ncbi.nlm.nih.gov/20046768/
- Aggarwal BB, Harikumar KB (2009). Potential therapeutic effects of curcumin, the anti-inflammatory agent, against neurodegenerative, cardiovascular, pulmonary, metabolic, autoimmune and neoplastic diseases. The International Journal of Biochemistry & Cell Biology, 41(1), 40–59. https://pubmed.ncbi.nlm.nih.gov/18662800/
- Lao CD, Ruffin MT, Normolle D, et al. (2006). Dose escalation of a curcuminoid formulation. BMC Complementary and Alternative Medicine, 6, 10. https://pubmed.ncbi.nlm.nih.gov/16545122/
- Keihanian F, Saeidinia A, Bagheri RK, Johnston TP, Sahebkar A. (2018). Curcumin, hemostasis, thrombosis, and coagulation. Journal of Cellular Physiology, 233(6), 4497–4511. https://pubmed.ncbi.nlm.nih.gov/29052850/
- Bahramsoltani R, Rahimi R, Farzaei MH. (2017). Pharmacokinetic interactions of curcuminoids with conventional drugs: A review. Journal of Ethnopharmacology, 209, 1–12. https://pubmed.ncbi.nlm.nih.gov/28734960/
- Halegoua-DeMarzio D, Navarro V, Ahmad J, et al. (2023). Liver Injury Associated with Turmeric — A Growing Problem: Ten Cases from the Drug-Induced Liver Injury Network [DILIN]. The American Journal of Medicine, 136(2), 200–206. https://pubmed.ncbi.nlm.nih.gov/36252717/
- Chen Y, Liu WH, Chen BL, et al. (2010). Plant polyphenol curcumin significantly affects CYP1A2 and CYP2A6 activity in healthy, male Chinese volunteers. The Annals of Pharmacotherapy, 44(6), 1038–1045. https://pubmed.ncbi.nlm.nih.gov/20484172/
- Volak LP, Hanley MJ, Masse G, et al. (2013). Effect of a herbal extract containing curcumin and piperine on midazolam, flurbiprofen and paracetamol (acetaminophen) pharmacokinetics in healthy volunteers. British Journal of Clinical Pharmacology, 75(2), 450–462. https://pubmed.ncbi.nlm.nih.gov/22725836/



