
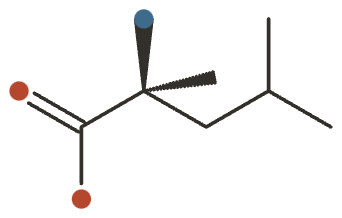
L-Leucine
L-Leucine is an essential branched-chain amino acid and the primary amino-acid trigger of the mTOR pathway that initiates muscle protein synthesis.

L-Leucine at a Glance
L-Leucine is an essential branched-chain amino acid whose distinguishing feature is pharmacological rather than nutritional: it is the amino-acid signal that activates mTORC1 and switches on the translational machinery of muscle protein synthesis. Of the three BCAAs, it is the one that actually does the anabolic signalling — isoleucine and valine do not.
The evidence has a sharp split down the middle. The acute signalling effect is one of the most reproducible findings in exercise nutrition. The long-term outcome of taking leucine on its own is a well-evidenced null.
That is not a contradiction — it is a mechanism. Firing the synthesis signal without supplying the other essential amino acids as building material cannot sustain new protein: the raw material has to come from somewhere, and if it isn’t eaten it comes from muscle breakdown. Leucine is the ignition, not the fuel.
So leucine helps most where the anabolic response is blunted — older adults, sub-threshold protein doses — and adds little on top of an already adequate, leucine-rich protein intake. Since leucine is abundant in ordinary dietary protein, dose relative to the meal matters far more than any branded isolate.
What It’s Used For
- Acute muscle protein synthesis signal — the best-established effect, and the source of the “leucine threshold” idea.
- Leucine-enriched protein for older adults — restores the anabolic response where it has become resistant.
- Sarcopenia (combined supplementation) — works in combination with vitamin D, protein and exercise; not alone.
The honest miss: isolated long-term leucine does not increase lean mass or strength — the meta-analytic weighted mean difference is 0.03 kg — and does not improve glycaemic control in type-2 diabetes. The signal fires; the outcome does not follow.
How It Works
Leucine is sensed directly. Sestrin2 binds it and releases its inhibition of the GATOR2 complex, which permits mTORC1 activation — and mTORC1 then phosphorylates p70S6K and 4E-BP1 to initiate mRNA translation. That is the entire mechanism behind the “leucine trigger.”
Two properties of that signal shape everything downstream. It responds to the peak and rate of rise in plasma leucine rather than the daily total, which is why a bolus around a meal or training session matters more than spreading small amounts through the day. And it saturates — past roughly 2–3 g per serving, more leucine does not mean more signal.
Leucine is also catabolised in muscle to α-ketoisocaproate and onward to HMB, the anti-catabolic metabolite that is supplemented separately.
The ceiling is oxidative. Plasma leucine stays stable up to about 500 mg/kg/day and then rises steeply — the point where the body can no longer keep pace with oxidation 9Reference 9Clinical trialDetermination of the tolerable upper intake level of leucine in adult men — clinical studyView study →.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Leucine is an essential branched-chain amino acid (BCAA) whose distinguishing feature is pharmacological rather than nutritional: it is the amino-acid signal that activates mTORC1 and switches on the translational machinery of muscle protein synthesis (MPS). The evidence posture is a sharp split — the acute signalling effect is one of the most reproducible findings in exercise nutrition, but the long-term outcome of taking leucine on its own is a well-evidenced null, because firing the synthesis signal without supplying the other essential amino acids as building material cannot sustain new protein. The most useful framing is deficiency-vs-repletion applied to a signal: leucine helps most where the anabolic response is blunted (older adults, sub-threshold protein doses) and adds little on top of an already adequate, leucine-rich protein intake. Because leucine is abundant in ordinary dietary protein, “form and dose relative to the meal” matters far more than any branded isolate.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up.
A leucine bolus, or a leucine-rich protein meal, produces a rapid and well-replicated rise in muscle protein synthesis by activating the mTORC1 pathway. This is the “leucine trigger” underlying the ~2–3 g per-serving threshold concept, and ingested leucine dose predicts the post-exercise MPS response in older adults in a quantitative systematic review 3Reference 3Systematic reviewAssociation of postprandial postexercise muscle protein synthesis rates with dietary leucine — systematic reviewView study →.
The signal is genuine and form-independent — it depends on plasma leucine kinetics — but it is an acute stimulus of synthesis rate, not evidence of accrued muscle. Leucine given alone cannot maximally or durably raise net synthesis, because the other essential amino acids required to build protein can only come from muscle breakdown 1Reference 1ReviewBranched-chain amino acids and muscle protein synthesis in humans: myth or reality? — reviewView study →.
Gap: an acute rise in synthesis rate is not the same as long-term muscle accretion; the signal saturates, and without co-ingested EAAs or protein, net balance is limited.
Older muscle shows “anabolic resistance” — a blunted MPS response to a given protein dose. Enriching a sub-optimal essential-amino-acid dose with extra leucine restores the response: raising leucine from 26% to 41% of a 6.7 g EAA drink significantly increased mixed-muscle fractional synthetic rate in elderly subjects who had not responded to the lower-leucine drink 2Reference 2Clinical trialA high proportion of leucine is required for optimal stimulation of the rate of muscle protein synthesis after resistance exercise — controlled clinical trialView study →.
This is a repletion-of-response effect — it matters precisely because the baseline response is deficient — and it argues for leucine as a modifier of a protein dose, not a standalone product.
Gap: benefit is demonstrated on the acute synthesis endpoint in small mechanistic trials; it is contingent on an otherwise sub-threshold protein dose and does not by itself establish long-term mass gain.
In a systematic review of 17 RCTs (1,418 older adults), leucine-isolated supplementation showed no effect on total lean mass (WMD = 0.03 kg, 95% CI −0.51 to 0.57), whereas leucine combined with vitamin D produced significant gains in handgrip strength and gait speed 4Reference 4Meta-analysisThe effect of leucine supplementation on sarcopenia-related measures in older adults: a systematic review and meta-analysis — meta-analysisView study →.
An evidence-based umbrella review of nutritional interventions for sarcopenia reaches the same conclusion — leucine/EAA supplementation is worthwhile as part of a multimodal approach (adequate protein, vitamin D, resistance exercise), not as a single agent 7Reference 7Systematic reviewNutritional interventions to improve muscle mass, muscle strength, and physical performance in older people: an umbrella review — systematic reviewView study →.
A 2026 RCT in pre-frail and frail older women found resistance training, but not added leucine, increased basal MPS in women already eating adequate protein 12Reference 12RCTResistance training, but not leucine, increased basal muscle protein synthesis in pre/frail older women — randomized controlled trialView study →.
Gap: the positive signal belongs to the combination; isolated leucine is null, and the benefit disappears where protein intake is already adequate.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| mTORC1 (via Sestrin2 leucine sensing) | ↑ activation → initiates mRNA translation | Acute MPS signalleucine-enriched protein |
| p70S6K / 4E-BP1 (downstream of mTORC1) | ↑ translation initiation | Acute MPS signal |
| BCAA transaminase → KIC → HMB | Leucine catabolism; HMB is anti-catabolic | Muscle preservation (HMB supplemented separately) |
| Branched-chain keto-acid dehydrogenase (BCKDH) | Rate-limiting leucine oxidation in muscle | Pharmacokineticssafety ceiling |
Pharmacokinetics
Leucine is absorbed rapidly from the gut and, unlike most amino acids, is metabolised primarily in skeletal muscle rather than the liver. Plasma leucine peaks quickly after an oral dose and drives the MPS signal via its concentration and rate of rise, not its total daily amount — which is why bolus timing around a meal or training session matters more than spreading small amounts through the day.
Radiolabelled ADME work confirms leucine is transaminated to α-ketoisocaproate and onward to the metabolite HMB, with only trace urinary excretion of leucine itself 10Reference 10AnimalA ¹⁴C-leucine absorption, distribution, metabolism and excretion (ADME) study in adult Sprague-Dawley rats — animal studyView study →. Oxidative capacity is finite: plasma leucine rises steeply once intake exceeds roughly 500 mg·kg⁻¹·d⁻¹, marking the point where the body can no longer keep pace with oxidation 9Reference 9Clinical trialDetermination of the tolerable upper intake level of leucine in adult men — clinical studyView study →.
Clinical trials
Leucine is an off-patent commodity nutrient, so industry-sponsored isolate trials are limited. Most high-quality human work studies leucine as a component of protein or EAA formulations, or within combined sarcopenia interventions 8Reference 8ReviewInternational Society of Sports Nutrition position stand: protein and exercise — reviewView study →. Registered activity is modest and concentrated in ageing, sarcopenia and clinical nutrition rather than in isolated-leucine efficacy.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| ~15(mostly combined/EAA) | ~5 | Few | Many |
Last checked: August 2026.
Dietary Sources
Leucine is abundant in ordinary complete-protein foods, so most people meet the requirement without supplementing. It is the most plentiful of the three BCAAs in animal and many plant proteins. Whey is unusually leucine-dense — around 10–11% of its protein — which is why whey and leucine-enriched formulas dominate the muscle-nutrition literature.
| Food | Approx. leucine per serving |
|---|---|
| Whey protein isolate (25 g) | ~2.5–3 g |
| Chicken / beef (100 g cooked) | ~1.7–2.2 g |
| Canned tuna / fish (100 g) | ~1.7–2.0 g |
| Soybeans (100 g) | ~1.4 g |
| Lentils (1 cup cooked) | ~1.3 g |
| Eggs (2 large) | ~1.1 g |
| Milk (250 mL) | ~0.7–0.8 g |
| Tofu, firm (100 g) | ~0.7 g |
A mixed diet supplying 1.4–2.0 g protein/kg/day — the ISSN range for exercising adults 8Reference 8ReviewInternational Society of Sports Nutrition position stand: protein and exercise — reviewView study → — delivers well above the leucine requirement, and a single leucine-rich meal of roughly 25–30 g quality protein typically clears the 2–3 g “threshold” on its own.
Intake & Dosage
These are doses studied in research, not a personal recommendation.
- Requirement: there is no standalone RDA for leucine. The adult requirement (~39 mg·kg⁻¹·d⁻¹, IOM/WHO) is normally met from dietary protein, and deficiency is not a concern on an adequate-protein diet.
- Studied supplemental doses: ~2–3 g per serving to reach the “leucine threshold,” often within a
5–10 g/day BCAA blend at a 2:1:1 leucine:isoleucine:valine ratio. Long-term isolated-leucine trials
used ~7.5 g/day (2.5 g × 3 meals) and found no gain in mass or strength 5,
6Reference 5RCTLong-term leucine supplementation does not increase muscle mass or strength in healthy elderly men — randomized controlled trialView study →Reference 6RCTProlonged leucine supplementation does not augment muscle mass or affect glycemic control in elderly type 2 diabetic men — randomized controlled trialView study → . - Timing and food: because the signal depends on the peak and rate of rise in plasma leucine, a bolus with or around a protein-containing meal or training session is more relevant than dividing it into many small doses. Taking leucine with a complete protein — not alone — supplies the other EAAs needed to convert the signal into net synthesis.
- No official upper limit, but an experimental metabolic ceiling of ~500–550 mg·kg⁻¹·d⁻¹ exists 9Reference 9Clinical trialDetermination of the tolerable upper intake level of leucine in adult men — clinical studyView study →. Do not read the absence of a formal UL as evidence that unlimited intake is safe.
- Leucine is a free amino acid, not a mineral salt, so the labelled gram amount is the leucine amount.
Safety
Leucine is an essential nutrient present in all dietary protein and is well tolerated in healthy adults at food-level and typical supplemental intakes.
- Well tolerated at usual doses. No serious acute adverse effects were seen across a graded-dose study up to the oxidative ceiling 9Reference 9Clinical trialDetermination of the tolerable upper intake level of leucine in adult men — clinical studyView study →.
- Contraindicated in maple-syrup-urine disease and other BCAA-catabolism disorders.
- A metabolic ceiling exists at ~500–550 mg/kg/day. Plasma leucine rises steeply beyond it — the rational limit for isolated supplementation 9Reference 9Clinical trialDetermination of the tolerable upper intake level of leucine in adult men — clinical studyView study →.
- Competes with levodopa. Large neutral amino acids share absorption and transport with levodopa — separate the dosing.
- Mildly insulinotropic. Theoretically additive with glucose-lowering medication, though a 6-month RCT in type-2 diabetes showed no change in glycaemic control 6Reference 6RCTProlonged leucine supplementation does not augment muscle mass or affect glycemic control in elderly type 2 diabetic men — randomized controlled trialView study →.
- Isolated BCAA loading unbalances other amino acids. It can transiently lower plasma tryptophan and tyrosine through transporter competition.
Full Safety & Interactions Detail
In a graded-dose study, plasma leucine remained stable up to about 500 mg·kg⁻¹·d⁻¹ and rose steeply beyond it, marking the ceiling of the body’s oxidative capacity. No serious acute adverse effects were seen across the tested range, but that ceiling is the rational limit for isolated supplementation 9Reference 9Clinical trialDetermination of the tolerable upper intake level of leucine in adult men — clinical studyView study →.
Very high, chronic isolated BCAA intakes are under active investigation for their relationship to insulin resistance — elevated circulating BCAAs are a biomarker of insulin resistance, though whether supplemental BCAAs cause it in humans is unresolved.
- Adverse effects: minimal at usual doses; gastrointestinal upset is possible with large boluses. Isolated BCAA loading can transiently lower plasma tryptophan and tyrosine through shared transporter competition.
- Interactions: leucine modestly stimulates insulin release, so people using glucose-lowering medication should be aware of the theoretical additive effect — clinical significance appears low, and a 6-month leucine RCT in type-2 diabetics showed no change in glycaemic control 6Reference 6RCTProlonged leucine supplementation does not augment muscle mass or affect glycemic control in elderly type 2 diabetic men — randomized controlled trialView study →. Free-amino-acid supplements may interfere with levodopa timing, since large neutral amino acids compete for absorption and transport; separate the dosing.
- Who should be cautious: people with maple-syrup-urine disease must avoid leucine loads, and those with advanced kidney or liver disease should use amino-acid supplements only under clinical supervision, as BCAA handling is altered.
Scope disclosure. Interactions were assessed partially — insulin and glucose-lowering agents, levodopa competition, and the MSUD contraindication were reviewed; a comprehensive drug-interaction screen was not performed. Pregnancy and lactation were assessed only at a high level: no dedicated trials of isolated-leucine supplementation were found, so treat that as “not assessed.” There is no official UL, only the experimental metabolic ceiling above. Where something was not studied, it is marked “not assessed,” not “safe.”
Dietary leucine is essential and safe; isolated supplements are not established. Food-level intake is not a concern in pregnancy or lactation. Isolated high-dose leucine supplementation has not been specifically studied in this group and is not recommended without clinical advice.
References
- Wolfe RR (2017). Branched-chain amino acids and muscle protein synthesis in humans: myth or reality? — review. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/28852372/
- Katsanos CS, et al. (2006). A high proportion of leucine is required for optimal stimulation of the rate of muscle protein synthesis after resistance exercise — controlled clinical trial. American Journal of Physiology-Endocrinology and Metabolism. https://pubmed.ncbi.nlm.nih.gov/16507602/
- Wilkinson K, et al. (2023). Association of postprandial postexercise muscle protein synthesis rates with dietary leucine — systematic review. Physiological Reports. https://pubmed.ncbi.nlm.nih.gov/37537134/
- Guo Y, et al. (2022). The effect of leucine supplementation on sarcopenia-related measures in older adults: a systematic review and meta-analysis — meta-analysis. Frontiers in Nutrition. https://pubmed.ncbi.nlm.nih.gov/35845777/
- Verhoeven S, et al. (2009). Long-term leucine supplementation does not increase muscle mass or strength in healthy elderly men — randomized controlled trial. American Journal of Clinical Nutrition. https://pubmed.ncbi.nlm.nih.gov/19321567/
- Leenders M, et al. (2011). Prolonged leucine supplementation does not augment muscle mass or affect glycemic control in elderly type 2 diabetic men — randomized controlled trial. The Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/21525248/
- Gielen E, et al. (2021). Nutritional interventions to improve muscle mass, muscle strength, and physical performance in older people: an umbrella review — systematic review. Nutrition Reviews. https://pubmed.ncbi.nlm.nih.gov/32483625/
- Jäger R, et al. (2017). International Society of Sports Nutrition position stand: protein and exercise — review. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/28642676/
- Pencharz PB, et al. (2012). Determination of the tolerable upper intake level of leucine in adult men — clinical study. The Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/23077191/
- Lee AJ, et al. (2015). A ¹⁴C-leucine absorption, distribution, metabolism and excretion (ADME) study in adult Sprague-Dawley rats — animal study. Amino Acids. https://pubmed.ncbi.nlm.nih.gov/25618754/
- Wu H, et al. (2015). Effect of beta-hydroxy-beta-methylbutyrate supplementation on muscle loss in older adults: a systematic review and meta-analysis — meta-analysis. Archives of Gerontology and Geriatrics. https://pubmed.ncbi.nlm.nih.gov/26169182/
- Jacob KJ, et al. (2026). Resistance training, but not leucine, increased basal muscle protein synthesis in pre/frail older women — randomized controlled trial. GeroScience. https://pubmed.ncbi.nlm.nih.gov/40926079/



