
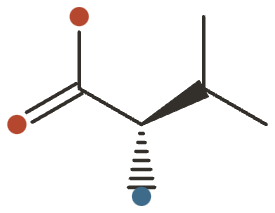
L-Valine
L-Valine is an essential branched-chain amino acid used as a muscle energy substrate and supplied within BCAA recovery blends.

L-Valine at a Glance
L-valine is an essential amino acid and one of the three branched-chain amino acids (BCAAs), alongside leucine and isoleucine. It is abundant in meat, dairy, eggs and soy.
What sets the BCAAs apart is that they bypass the liver — they are metabolised primarily in skeletal muscle rather than being processed first on absorption, which is why they are used as an exercise and muscle supplement rather than a general amino acid.
What It’s Used For
- Hepatic encephalopathy & cirrhosis — improves mental status and nutrition in advanced liver disease; its best-established medical use.
- Central (exercise) fatigue — reduces the perception of fatigue during prolonged exercise.
- Exercise muscle damage & soreness — lowers markers of muscle damage and soreness.
- Tardive dyskinesia — studied for involuntary movements caused by antipsychotics.
How It Works
Valine is glucogenic — it feeds into the citric-acid cycle via succinyl-CoA, so it can be converted to glucose, which distinguishes it from leucine. Skeletal muscle carries the enzymes to transaminate it directly, which is why BCAAs are taken up and burned by working muscle rather than by the liver.
The central-fatigue and encephalopathy uses share one mechanism: BCAAs compete with tryptophan for the transporter into the brain. More BCAA means less tryptophan crossing, so less serotonin — which reduces the central fatigue signal during endurance exercise, and in cirrhosis helps correct the amino-acid imbalance that drives encephalopathy.
The full trial record is in Pharmacology & Research below.
Pharmacology & Research
L-Valine is one of the three branched-chain amino acids (BCAAs) — the others being leucine and isoleucine — and one of the nine indispensable (essential) amino acids humans must obtain from the diet. Almost no clinical trial has ever tested valine on its own; the evidence base is overwhelmingly about the BCAA mixture, usually in a 2:1:1 leucine:isoleucine:valine ratio, so valine’s “efficacy” is really the efficacy of the group it travels in. The honest posture across that literature is modest: BCAAs help correct a real amino-acid deficit in liver cirrhosis and blunt some markers of exercise-induced muscle damage, but the popular idea that they build muscle on their own is not supported. Because valine is abundant in ordinary dietary protein, the deficiency-versus-repletion distinction dominates — most benefits appear only in people who are catabolic or protein-deprived, not in healthy, well-fed adults.
Support is an experimental score I’m building — a composite weighted by study type (human > animal > in vitro > review) and study volume. It’s a beta: a fast way to rank strength of evidence at a glance, not a validated metric. Each application links down to its write-up. Note that every row reflects the BCAA combination, not isolated valine.
In cirrhosis, muscle consumes BCAAs to detoxify ammonia into glutamine, so circulating BCAA levels fall while aromatic amino acids rise — a genuine deficit that oral BCAAs can correct 13Reference 13ReviewBranched-chain amino acids in health and disease: metabolism, alterations in blood plasma, and as supplements — reviewView study →.
The 2017 Cochrane review of randomized trials found BCAAs improved manifestations of hepatic encephalopathy without affecting mortality or quality of life 1Reference 1Meta-analysisBranched-chain amino acids for people with hepatic encephalopathy — Cochrane systematic review & meta-analysisView study →; the 2026 update reaffirmed a beneficial effect on encephalopathy with no mortality change 2Reference 2Meta-analysisBranched-chain amino acids for people with cirrhosis and hepatic encephalopathy — updated Cochrane systematic review & meta-analysisView study →.
An independent systematic review of 8 oral-BCAA trials (n = 382; mean dose ~0.25 g/kg/day) found improvement in 87/172 treated versus 56/210 controls (risk ratio 1.71, 95% CI 1.17–2.51; number-needed-to-treat ≈ 5) 3Reference 3Meta-analysisOral branched-chain amino acids have a beneficial effect on manifestations of hepatic encephalopathy — systematic review with meta-analyses of RCTsView study →.
BCAAs also improve some sarcopenia parameters in cirrhosis 14Reference 14Meta-analysisEffects of branched-chain amino acids on parameters evaluating sarcopenia in liver cirrhosis — systematic review & meta-analysisView study →.
Gap: This is a repletion benefit in sick livers, delivered as the full BCAA mix at gram-per-kilogram doses — it says nothing about isolated valine or about healthy people.
A meta-analysis of 8 trials found BCAAs significantly reduced creatine kinase (a muscle-damage marker) at <24 h and 24 h post-exercise versus placebo (e.g. mean difference −71.55 U/L at <24 h) 4Reference 4Meta-analysisBCAA supplementation and exercise-induced muscle damage in exercise recovery — meta-analysis of RCTsView study →.
Meta-analyses of delayed-onset muscle soreness (DOMS) report attenuated soreness in most included trials, but the authors emphasize inconsistent results, small samples, and no consensus on an effective protocol 5,
Effects are most visible with modest muscle damage and pre-exercise dosing.
Gap: Reduced blood markers and subjective soreness do not translate to demonstrated gains in strength, performance, or hypertrophy; trials are small and heterogeneous, and whole protein achieves the same recovery aims.
Two randomized, placebo-controlled trials tested high-dose BCAAs as a medical food in men with long antipsychotic-treatment histories. A 3-week trial (222 mg/kg three times daily; n = 18 per arm) found a robust, significant reduction in videotaped tardive-dyskinesia movements versus placebo 7Reference 7RCTEfficacy of the branched-chain amino acids in the treatment of tardive dyskinesia in men — RCTView study →.
An earlier small trial reported the same direction of effect 8Reference 8Clinical trialBranched chain amino acids decrease tardive dyskinesia symptoms — clinical trialView study →.
The rationale is that a BCAA load competes with phenylalanine for brain uptake, altering the amino-acid milieu thought to drive symptoms.
Gap: Small, single-sex, short trials at very high doses; not replicated in large populations, and not standard therapy compared with approved VMAT2 inhibitors.
The “central fatigue hypothesis” holds that BCAAs compete with tryptophan for transport across the blood–brain barrier, limiting serotonin synthesis and delaying perceived fatigue 15Reference 15ReviewCarbohydrates, branched-chain amino acids, and endurance: the central fatigue hypothesis — reviewView study →. A small RCT in taekwondo athletes found BCAAs combined with arginine and citrulline alleviated central fatigue after simulated matches 16Reference 16RCTBranched-chain amino acids, arginine, citrulline alleviate central fatigue after 3 simulated matches in taekwondo athletes — RCTView study →. Human trials of BCAAs alone for endurance or perceived exertion are mixed and generally unconvincing.
Gap: The mechanism is plausible but the human performance data are small, combined-ingredient, and inconsistent; NH₃ accumulation from BCAA loading may itself contribute to fatigue.
Mechanisms
| Target / pathway | Effect | Relevant to |
|---|---|---|
| Skeletal-muscle BCAA transaminase (BCAT) → BCKDH complex | Valine transaminated then oxidized for energy; purely glucogenic (yields succinyl-CoA, no ketone bodies) | Muscle energy metabolismnitrogen balance |
| Ammonia → glutamine detoxification in muscle | BCAAs donate nitrogen; consumption depletes BCAAs in cirrhosis | Hepatic encephalopathy |
| Large-neutral-amino-acid (LAT1) transport at blood–brain barrier | BCAAs compete with tryptophan and phenylalanine for brain uptake | Central fatiguetardive dyskinesia |
| mTORC1 signaling (chiefly leucine, not valine) | Activates translation initiation; valine contributes little on its own | Muscle protein synthesis (the overhyped claim) |
Pharmacokinetics
Valine is absorbed in the small intestine via sodium-dependent and LAT transporters shared with the other large neutral amino acids, so leucine, isoleucine, phenylalanine, tryptophan and tyrosine compete for uptake. Unlike most amino acids, BCAAs largely bypass first-pass hepatic catabolism — the liver has low BCAA-aminotransferase activity — and are transaminated primarily in skeletal muscle, which is why they appear quickly in the systemic circulation after ingestion 17Reference 17ReviewBranched-chain amino acids and brain metabolism — reviewView study →. Valine is purely glucogenic; its carbon skeleton feeds into succinyl-CoA and can be used for gluconeogenesis or oxidized for energy. There is no meaningful body “store” of free amino acids, so plasma levels track recent intake and fall during fasting or catabolic states.
Clinical trials
BCAAs are off-patent, inexpensive food substances, so most trial activity is investigator-initiated and concentrated in liver disease and sports nutrition rather than industry drug development; trials isolating valine specifically are essentially absent. The prior version of the Cochrane hepatic-encephalopathy review pooled 16 randomized trials, and the 2026 update added further newly published trials 2Reference 2Meta-analysisBranched-chain amino acids for people with cirrhosis and hepatic encephalopathy — updated Cochrane systematic review & meta-analysisView study →.
| Completed | Planned | Terminated | Preclinical |
|---|---|---|---|
| Dozens(BCAA mix; liver disease + exercise) | Several(fatigue, sarcopenia) | ≥1(ALS, stopped for excess mortality 11Reference 11RCTBranched-chain amino acids and amyotrophic lateral sclerosis: a treatment failure? — RCT (terminated for excess mortality)View study →) | Many(metabolic signaling) |
Last checked: July 2026.
Dietary Sources
Valine is present in essentially all complete dietary protein, so healthy people eating adequate protein reach their requirement easily; the amino acid is rarely limiting outside of severe protein malnutrition. As a branched-chain amino acid it travels with leucine and isoleucine wherever protein occurs. Animal proteins (meat, poultry, fish, eggs, dairy) and concentrated plant proteins (soy, legumes, seeds, and especially whey) are the richest sources. Refining and heavy processing that strips protein (e.g. polished grains, sugars, fats) dilutes valine density, but a mixed diet with any protein source supplies it. Roughly 85–95% of dietary amino acids from well-cooked protein are absorbed.
| Food (typical serving) | Approx. valine |
|---|---|
| Whey protein isolate (30 g) | ~1.7 g |
| Chicken breast (100 g cooked) | ~1.4 g |
| Beef (100 g cooked) | ~1.3 g |
| Canned tuna (100 g) | ~1.3 g |
| Soybeans / tofu (100 g firm) | ~0.5–0.9 g |
| Eggs (2 large) | ~0.8 g |
| Lentils (1 cup cooked) | ~0.9 g |
Values approximate; see NIH ODS and USDA FoodData Central for protein and amino-acid composition. U.S. intake data show essential-amino-acid intakes, including valine, comfortably exceed requirements for nearly the entire population 18Reference 18Amino acid intake and conformance with the Dietary Reference Intakes in the United States (NHANES) — essential-amino-acid intakes, valine included, exceed estimated requirementsView study →.
Intake & Dosage
These are doses studied in research, not a personal recommendation.
Requirement: The 2005 IOM Dietary Reference Intakes set an estimated average valine requirement near 26 mg/kg/day, giving an RDA around 24–26 mg/kg/day — roughly 1.8 g/day for a 70 kg adult, met by about 25–30 g of mixed dietary protein. National survey data confirm typical intakes are several-fold above this 18Reference 18Amino acid intake and conformance with the Dietary Reference Intakes in the United States (NHANES) — essential-amino-acid intakes, valine included, exceed estimated requirementsView study →.
Supplemental ranges (BCAA blends, not isolated valine):
- Sports/recovery: BCAA blends deliver ~5–20 g total BCAA per day, usually 2:1:1 leucine:isoleucine:valine, so ~1–4 g valine per serving.
- Hepatic encephalopathy / cirrhosis: oral BCAA doses of ~0.25 g/kg/day (roughly 12–18 g total BCAA daily), under medical supervision.
- Tardive dyskinesia (research only): very high BCAA doses (222 mg/kg three times daily) in short trials.
Practical notes: Isolated valine is not a mainstream supplement and no standalone dose is established — it is taken as part of the BCAA group. Amino-acid absorption is not rate-limited the way mineral absorption is, but taking BCAAs with or without food is a matter of preference and tolerance; pre-exercise dosing is common in the muscle-damage trials.
Safety
Valine is a dietary essential and is well tolerated at ordinary intakes — the concerns attach to high isolated BCAA loads rather than to valine itself, and they land hardest on people with liver, kidney, metabolic or neurodegenerative disease.
- Well tolerated from food and standard BCAA blends. Reported adverse effects are mild and mostly gastrointestinal.
- A randomized ALS trial was terminated early for excess mortality in the BCAA arm. Reason not to self-prescribe high-dose BCAAs in neurodegenerative disease.
- Maple syrup urine disease. People with this inherited disorder cannot metabolize BCAAs and must restrict valine strictly.
- Chronically elevated circulating BCAAs track insulin resistance and type 2 diabetes. Causal direction is debated, but extra BCAAs shouldn’t be assumed beneficial in metabolic disease.
- Renal impairment and hepatic failure. Nitrogen load and ammonia accumulation are the dose-limiting concerns.
- Shares the blood–brain-barrier transporter with levodopa. Separate dosing in Parkinson’s disease.
Full Safety & Interactions Detail
Valine from food and from standard BCAA blends is well tolerated; reported adverse effects at supplement doses are mild and mostly gastrointestinal (nausea, bloating). The dose-limiting concern with high BCAA loads is ammonia accumulation, because nitrogen from BCAA catabolism must be disposed of as urea and glutamine — relevant in advanced liver disease. Because valine shares the blood–brain-barrier transporter with tryptophan, phenylalanine and tyrosine, large BCAA doses can shift brain amino-acid balance; this is the basis of both the central-fatigue and tardive-dyskinesia rationales but also a reason for caution.
Two population-level signals deserve emphasis. First, chronically elevated circulating BCAAs are a consistent biomarker of insulin resistance and type 2 diabetes, and while the causal direction is debated, people with metabolic disease should not assume extra BCAAs are beneficial 12,
Second, a randomized ALS trial was terminated early for excess mortality in the BCAA arm 11Reference 11RCTBranched-chain amino acids and amyotrophic lateral sclerosis: a treatment failure? — RCT (terminated for excess mortality)View study → — a reason not to self-prescribe high-dose BCAAs in neurodegenerative disease.
Interactions and cautions: use caution with renal impairment (nitrogen load), hepatic failure (unless prescribed as therapy), and diabetes/insulin resistance. Individuals with the rare inherited disorder maple syrup urine disease cannot metabolize BCAAs and must restrict valine strictly. BCAAs may theoretically interfere with the action of drugs that share LNAA transport (e.g. levodopa in Parkinson’s disease) — separate dosing.
Verdict: adequate dietary valine is essential in pregnancy and lactation, but isolated high-dose supplementation is not established as safe and is not recommended. Valine is a required nutrient obtained from normal dietary protein; there is no evidence that supplemental BCAAs above dietary needs benefit pregnancy, and dedicated safety trials are lacking. Pregnant or breastfeeding individuals should meet needs through diet and consult a clinician before using BCAA supplements.
References
- Gluud, L. L., Dam, G., Les, I., et al. (2017). Branched-chain amino acids for people with hepatic encephalopathy — Cochrane systematic review & meta-analysis. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/28518283/
- Gluud, L. L., et al. (2026). Branched-chain amino acids for people with cirrhosis and hepatic encephalopathy — updated Cochrane systematic review & meta-analysis. Cochrane Database of Systematic Reviews. https://pubmed.ncbi.nlm.nih.gov/41542879/
- Gluud, L. L., Dam, G., Borre, M., et al. (2013). Oral branched-chain amino acids have a beneficial effect on manifestations of hepatic encephalopathy — systematic review with meta-analyses of RCTs. The Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/23739310/
- Rahimi, M. H., et al. (2017). BCAA supplementation and exercise-induced muscle damage in exercise recovery — meta-analysis of RCTs. Nutrition. https://pubmed.ncbi.nlm.nih.gov/28870476/
- Fedewa, M. V., et al. (2019). Effect of BCAA supplementation on muscle soreness following exercise — meta-analysis. International Journal for Vitamin and Nutrition Research. https://pubmed.ncbi.nlm.nih.gov/30938579/
- Weber, M. G., et al. (2021). The use of BCAA to decrease delayed-onset muscle soreness after a single bout of exercise — systematic review & meta-analysis. Amino Acids. https://pubmed.ncbi.nlm.nih.gov/34669012/
- Richardson, M. A., et al. (2003). Efficacy of the branched-chain amino acids in the treatment of tardive dyskinesia in men — RCT. The American Journal of Psychiatry. https://pubmed.ncbi.nlm.nih.gov/12777270/
- Richardson, M. A., et al. (1999). Branched chain amino acids decrease tardive dyskinesia symptoms — clinical trial. Psychopharmacology. https://pubmed.ncbi.nlm.nih.gov/10367552/
- Wolfe, R. R. (2017). Branched-chain amino acids and muscle protein synthesis in humans: myth or reality? — review. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/28852372/
- Kaspy, M. S., Hannaian, S. J., Bell, Z. W., et al. (2024). The effects of branched-chain amino acids on muscle protein synthesis, breakdown and molecular signalling in humans: an update — review. Nutrition Research Reviews. https://pubmed.ncbi.nlm.nih.gov/37681443/
- The Italian ALS Study Group. (1993). Branched-chain amino acids and amyotrophic lateral sclerosis: a treatment failure? — RCT (terminated for excess mortality). Neurology. https://pubmed.ncbi.nlm.nih.gov/8255440/
- Lynch, C. J., & Adams, S. H. (2014). Branched-chain amino acids in metabolic signalling and insulin resistance — review. Nature Reviews Endocrinology. https://pubmed.ncbi.nlm.nih.gov/25287287/
- Holeček, M. (2018). Branched-chain amino acids in health and disease: metabolism, alterations in blood plasma, and as supplements — review. Nutrition & Metabolism. https://pubmed.ncbi.nlm.nih.gov/29755574/
- Ismaiel, A., Bucsa, C., Farcas, A., et al. (2022). Effects of branched-chain amino acids on parameters evaluating sarcopenia in liver cirrhosis — systematic review & meta-analysis. Frontiers in Nutrition. https://pubmed.ncbi.nlm.nih.gov/35155535/
- Davis, J. M. (1995). Carbohydrates, branched-chain amino acids, and endurance: the central fatigue hypothesis — review. International Journal of Sport Nutrition. https://pubmed.ncbi.nlm.nih.gov/7550256/
- Chang, C. K., et al. (2016). Branched-chain amino acids, arginine, citrulline alleviate central fatigue after 3 simulated matches in taekwondo athletes — RCT. Journal of the International Society of Sports Nutrition. https://pubmed.ncbi.nlm.nih.gov/27418883/
- Sperringer, J. E., et al. (2017). Branched-chain amino acids and brain metabolism — review. Neurochemical Research. https://pubmed.ncbi.nlm.nih.gov/28417264/
- Berryman, C. E., Cheung, S. N., Collette, E. M., et al. (2023). Amino acid intake and conformance with the Dietary Reference Intakes in the United States (NHANES) — essential-amino-acid intakes, valine included, exceed estimated requirements. Journal of Nutrition. https://pubmed.ncbi.nlm.nih.gov/36805182/



